Breaking Down The Glomerular Filtration Barrier
The Anatomy Of The Glomerulus is one of those topics people memorize for exams and then immediately forget because they never actually had to diagnose a pathology through it. I spent years reading kidney biopsies under electron microscopy before it really clicked that the textbook diagram and what you're actually looking at are two different things. The diagram shows clean lines. The real thing is messy, variable, and full of edge cases that will trip you up. Let me start with what matters clinically rather than what you'll find in Gray's Anatomy. The filtration barrier has three layers: fenestrated endothelium, the glomerular basement membrane, and the podocyte foot processes. That's the standard answer. The actual answer involves charge barriers, size selectivity that changes with disease states, and a basement membrane whose composition varies between cortical and juxtamedullary nephrons.
Components Of The Anatomy Of The Glomerulus
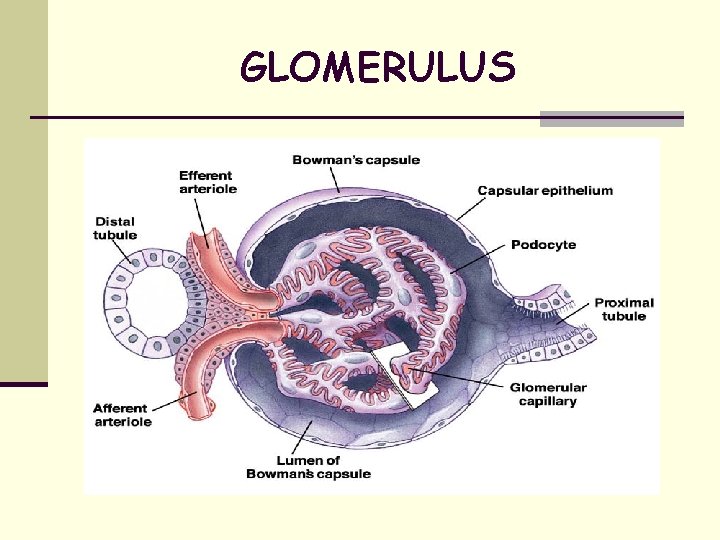
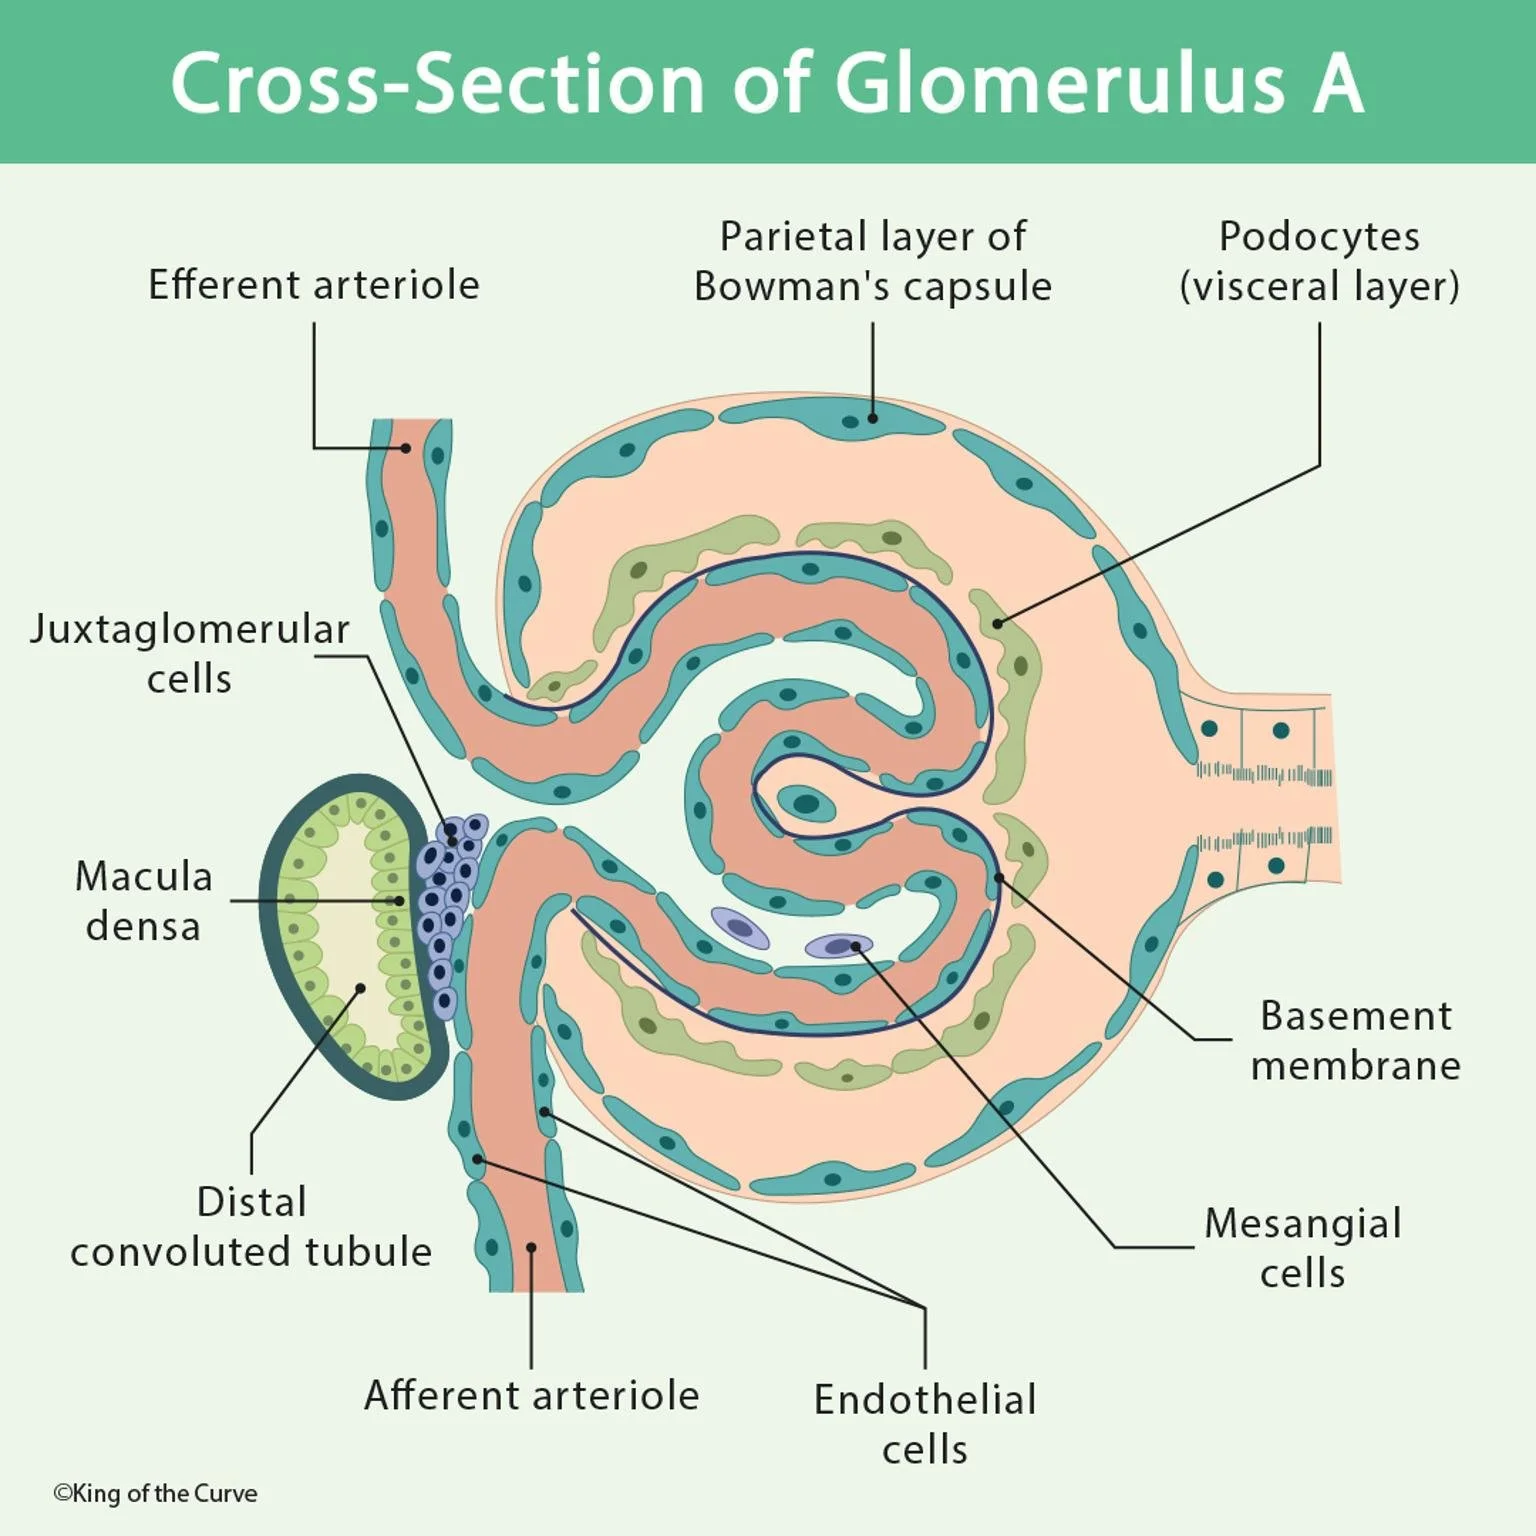
The endothelial layer faces the capillary lumen. Those fenestrations are 70 to 90 nanometers across and they don't have diaphragms. That's different from fenestrated capillaries elsewhere in the body. In the glomerulus, those open holes let plasma and everything dissolved in it approach the basement membrane without any cellular obstruction. You can see this clearly on thin section TEM, but on light microscopy with H&E staining, the endothelium is basically invisible. It blends into the capillary wall. This is where beginners miss things. They're looking for structures that aren't there at standard magnification. The glomerular basement membrane sits between the endothelium and the podocytes. It's about 300 nanometers thick in a healthy adult kidney. The three-layered appearance you see on silver stain—the lacunae and the dense laminae—is an artifact of the staining method, not a literal structural description. The actual ECM is a meshwork of type IV collagen networks, laminin, nidogen, and heparan sulfate proteoglycans. The heparan sulfate content is what gives the barrier its negative charge. When that gets depleted, which happens in early diabetic nephropathy, you get proteinuria before you see any structural change on light microscopy. I've seen cases where the protein-to-creatinine ratio was 4.2 and the biopsy looked essentially normal under the light microscope. The damage was entirely at the molecular level in the GBM. Podocytes are the third layer and honestly the most misunderstood. They're not simple sieves. Each podocyte sends out primary processes that branch into foot processes, and those foot processes interdigitate with neighboring podocytes. The slit diaphragm between adjacent foot processes is the final filtration gate. It's a specialized cell junction containing nephrin, CD2AP, and podocin. Genetic mutations in any of those three proteins cause congenital nephrotic syndrome. The slit diaphragm isn't a static fence. It remodels dynamically, and that remodeling is what goes wrong in conditions like FSGS.
Between the capillary loops you find the mesangium. Mesangial cells and mesangial matrix make up this region. The mesangial cells have contractile properties similar to smooth muscle cells, though they respond to different signals. They regulate capillary surface area available for filtration by contracting or expanding. More importantly, they produce mesangial matrix and phagocytose trapped immune complexes and debris. When mesangial cells proliferate—which happens in IgA nephropathy and diabetic nephropathy—they expand into the capillary lumens and physically reduce the filtration surface area. This is why mesangial expansion is such a bad prognostic sign. The Bowman's capsule surrounds everything. The parietal layer is simple squamous epithelium lining the outer boundary. The visceral layer is the podocyte layer we just covered. Between them is Bowman's space, which collects the filtrate. The parietal epithelium transitions into the proximal tubule at the urinary pole. This transition zone is where parietal epithelial cells can proliferate and form crescents in severe glomerulonephritis. Crescents compress the glomerular tuft and acutely reduce GFR. I've seen crescentic GN cases where the GFR dropped from 60 to under 15 in three days. The patient was on the phone the whole time, complaining about fatigue. These things escalate fast.
Get the Full Details
What The Diagrams Leave Out
Textbook illustrations show a neat spherical tuft of capillaries. Reality is more like a tangled ball of hoses with varying diameters and pressures. Afferent and efferent arterioles feed and drain the glomerulus, and the diameter difference between them is what creates the transcapillary hydrostatic pressure gradient. The afferent arteriole is wider, the efferent is narrower. This setup maintains high intracapillary pressure—about 55 mmHg—which drives filtration. But that high pressure is also what makes glomeruli vulnerable. Any condition that chronically elevates this pressure, like systemic hypertension or hyperfiltration from a solitary kidney, damages the barrier over time. The juxtaglomerular apparatus sits where the distal tubule contacts the vascular pole. Macula densa cells in the distal tubule sense sodium chloride concentration in the tubular fluid. They signal the juxtaglomerular cells in the afferent arteriole wall to adjust renin release. This is tubuloglomerular feedback. It's the kidney's way of matching GFR to tubular reabsorptive capacity. When you're dehydrated, the macula densa detects low NaCl, signals decreased afferent constriction is needed, and renin release increases to raise systemic blood pressure. The anatomy of this contact point is delicate. Damage here disrupts the entire feedback loop. Here's something most students don't learn until they're dealing with actual biopsies: the glomerulus isn't uniform. Cortical glomeruli are smaller with thinner basement membranes. Juxtamedullary glomeruli are larger and sit deeper in the cortex near the medulla. Their hemodynamic properties differ. Juxtamedullary glomeruli handle a larger per-glomerulus blood flow and have longer loops of Henle. When you're sampling a biopsy, you might get a mix of both types, and pathologists need to account for that variation when assessing things like segmental sclerosis. A sclerotic lesion in a juxtamedullary glomerulus looks different from the same lesion in a cortical glomerulus.
A Practical Problem And How I Handled It
Early in my fellowship, I was reviewing a pediatric nephrotic syndrome case. The light microscopy showed minimal changes. The immunofluorescence was negative. The diagnosis seemed straightforward—steroid-sensitive minimal change disease. But the child wasn't responding to steroids. The standard workup was done. Everything pointed to MCD, but the clinical picture didn't fit. I went back to the electron microscopy images, which I'd initially skimmed because the light microscopy and IF were so clean. There, barely noticeable, were subtle effacement patterns that weren't uniform. Some capillary loops had complete foot process fusion while others retained partial structure. That asymmetry suggested something beyond classic MCD. I recommended genetic testing for podocyte genes, which eventually identified a nephrin mutation. The child needed cyclosporine, not steroids. If I hadn't spent extra time on the EM images, we would have wasted months on an ineffective treatment while the disease progressed. That experience changed how I approach every glomerular biopsy. Clean light microscopy and negative IF don't mean the glomerulus is normal. They mean the pathology is below the resolution of those techniques. Electron microscopy or genetic testing might be necessary even when the initial workup looks complete.
Limitations And Where This Knowledge Falls Short
Understanding glomerular anatomy doesn't mean you can predict disease behavior. Two patients with identical biopsy findings can have wildly different outcomes. The same patient can have different lesions in different glomeruli within the same sample. Biopsy sampling error is real and significant. A standard core biopsy contains about 10 to 15 glomeruli. If a focal disease process affects only 20 percent of glomeruli, you might miss it entirely depending on which slice of tissue the pathologist examines. I've had cases where the initial biopsy was read as normal and the patient continued to decline, only to be diagnosed on repeat biopsy three months later. There's also no perfect non-invasive test that replaces biopsy for glomerular diseases. Urine protein electrophoresis, serum biomarkers, and imaging studies give you clues but not definitive answers. The glomerular filtration barrier's complexity means that functional changes often precede structural ones, and structural changes are heterogeneous even within a single glomerulus. You need the tissue to see what's actually happening. Advanced imaging techniques like confocal microscopy with specialized staining can provide more detail than routine TEM, but they're not universally available. Many centers still rely on standard light microscopy with routine stains plus immunofluorescence and occasional EM. Understanding the anatomy helps you interpret whatever level of detail you have access to, but it also means knowing when your tools aren't sufficient and recommending further workup.