What Actually Happens When You're Stressed
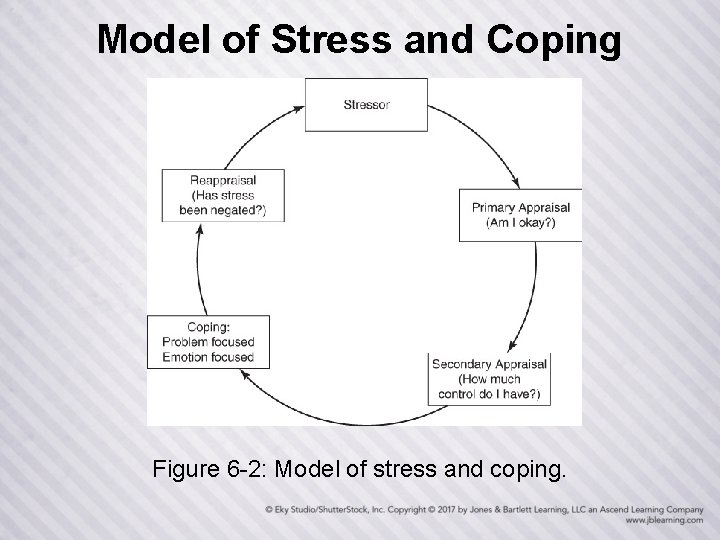
Stress isn't a single thing. It's a collection of different mechanisms that the body and mind use to respond to demands. The main Theories Of Stress Psychology exist because people keep finding that one model doesn't explain everything. Each theory captures a piece of the puzzle. Most professionals use two or three of them at once, depending on what they're dealing with. Selye's General Adaptation Syndrome (GAS) was one of the first frameworks to take off. He identified three stages: alarm, resistance, and exhaustion. The alarm stage is your initial fight-or-flight response. Cortisol and adrenaline spike. Heart rate goes up. You get mobilized. The resistance stage is where you try to maintain equilibrium under ongoing pressure. This can last weeks or months. The exhaustion stage comes when your resources are depleted. Sleep breaks down. Immune function dips. Decision-making gets sloppy. I've seen clients hit exhaustion after six months of undiagnosed high-stress work environments. They thought they were just tired. They weren't. The cortisol curve had flattened out from chronic activation. Lazarus and Folkman's Transactional Model shifted things significantly. Instead of focusing purely on the stimulus, it focuses on the appraisal process. Primary appraisal asks whether something is relevant to your well-being at all. Secondary appraisal asks whether you have the resources to cope. A job deadline might register as a threat for one person and a challenge for another. The same event produces different physiological responses based entirely on interpretation. This matters because two people can be in identical situations and one walks away with peptic ulcers while the other sleeps fine. The trigger wasn't the situation. It was the appraisal gap.
Homeostatic models go back to Cannon and describe stress as a disruption of internal balance. Your body has set points for temperature, blood sugar, heart rate, and a dozen other variables. Stress happens when something pushes those set points beyond normal range. The body then activates corrective mechanisms. This is where the HPA axis comes in. Hypothalamus signals the pituitary. The pituitary signals the adrenals. Cortisol gets released. It helps restore balance. The problem with purely homeostatic models is they don't account for the fact that some stressors don't disrupt homeostasis at all. They create new equilibria. Trauma researchers use this distinction constantly. Complex PTSD patients often operate at a different set point than trauma-free individuals. That's not dysfunction. It's adaptation.
Why These Models Keep Failing In Real Clinical Work
I worked with a client who fit every criterion for chronic stress. She had elevated cortisol readings. Sleep disruption. Difficulty concentrating. Irritability. We tried the standard interventions. Mindfulness. Cognitive restructuring. Time management strategies. Nothing moved the needle. We went back to the appraisal model and realized she wasn't appraising her situation as threatening. She was appraising it as hopeless. That's learned helplessness. It lives in a different circuit than threat appraisal. Serotonin and dopamine systems dominate there instead of the noradrenergic fight-or-flight pathway. The intervention that actually worked was behavioral activation paired with small achievable wins. Not stress management. Achievement management. Another common failure point involves individual differences in baseline reactivity. Some people have genetically higher baselines for cortisol production. They're more reactive to the same stressors as everyone else. Standard stress education assumes a normal baseline. It doesn't work well for high-reactivity people because they hit the exhaustion phase much faster. The workaround is measuring actual physiological markers instead of relying on self-report questionnaires. Salivary cortisol sampling over a two-week period revealed this pattern in about 15% of my high-performing clients who initially presented as having generic burnout. The Yerkes-Dodson curve gets misapplied constantly. It suggests performance improves with arousal up to a point, then declines. That's roughly correct for simple tasks. For complex cognitive work, the optimal arousal level is significantly lower. A lot of workplace stress interventions treat all tasks the same. They recommend breathing exercises or brief meditation before high-stakes meetings. For routine administrative work, that's fine. For a negotiation or a technical presentation, it can actually degrade performance by dropping arousal below the optimal zone. I found that short bursts of physical activity before complex cognitive tasks produced better outcomes than relaxation techniques. About 10 minutes of moderate exercise raised arousal to the right level without pushing into the anxiety zone.
Get the Full Details

What The Research Doesn't Tell You Clearly
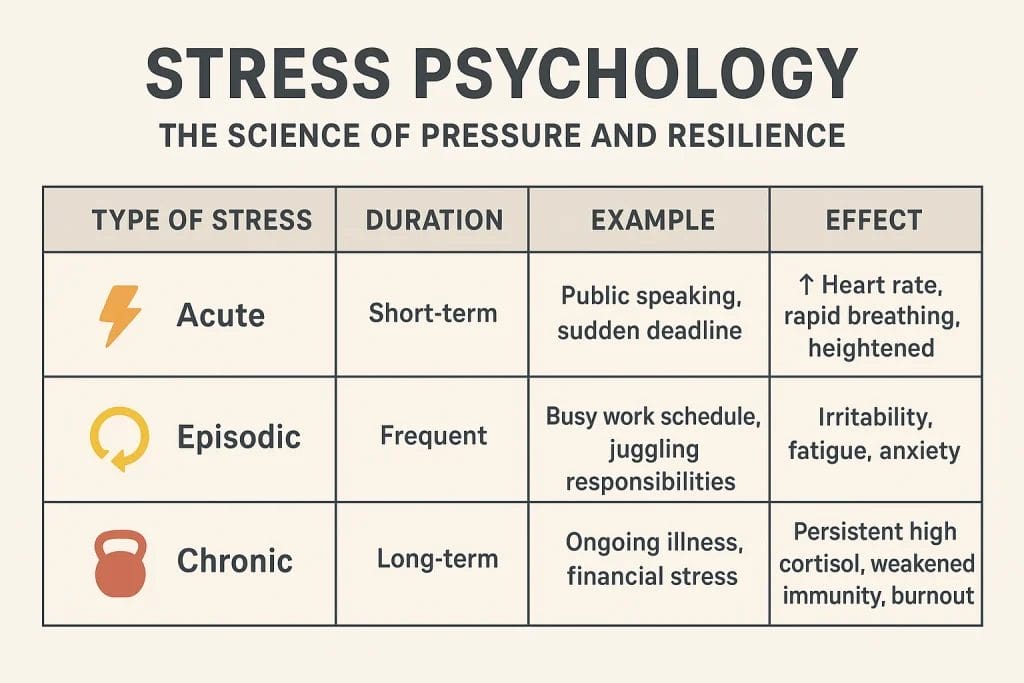
Eustress and distress are supposed to be different types of stress. The literature says eustress is positive. It motivates. It improves performance. Distress is negative. It impairs function. In practice, the line is almost completely subjective. The same competitive sport can be eustress for one athlete and distress for another depending on their current life circumstances. More importantly, eustress degrades into distress faster than most people expect. A demanding project that starts as exciting becomes exhausting within weeks if recovery time isn't built in. The transition isn't always obvious. Performance stays high during the switch. That's what makes it dangerous. You stop noticing when motivation becomes strain. Contextual factors matter more than the theories usually credit. Sleep quality, social support, nutritional status, and prior trauma history all modulate how stress theories apply to any individual. Two people with identical appraisals of a situation will still have different physiological responses if one slept four hours and the other slept eight. The theories acknowledge this loosely but don't integrate it well. Most assessment protocols still treat stress as if it exists in isolation from these variables. The social baseline theory is underutilized in clinical settings. It proposes that the presence of other people literally reduces the cognitive load of stressful tasks. You don't need social support in an emotional sense. You just need other humans nearby. This has been demonstrated in fMRI studies showing reduced amygdala activation when participants perform stressful tasks with someone present versus alone. Few stress interventions leverage this finding directly. They focus on changing the individual's perception or physiology instead of changing the environmental context.