The lips are one of those things everyone looks at but nobody actually studies until they need to. Whether you're doing filler work, reconstructive surgery, or just studying head-and-neck anatomy for exams, understanding the anatomy of the lips matters because the margin between a good result and a botched one is usually measured in millimeters.
I spent years reading cadaver labs and drawing cross-sections until the layers stopped being abstract. Here is how it actually works when you put a needle or a scalpel in there.
Understanding Anatomy Of The Lips In Practice
The lip is not a single structure. It is a stack of tissue layers sitting on top of bone and muscle, and each layer does something different. That means any procedure or diagnosis has to account for depth, not just surface appearance.
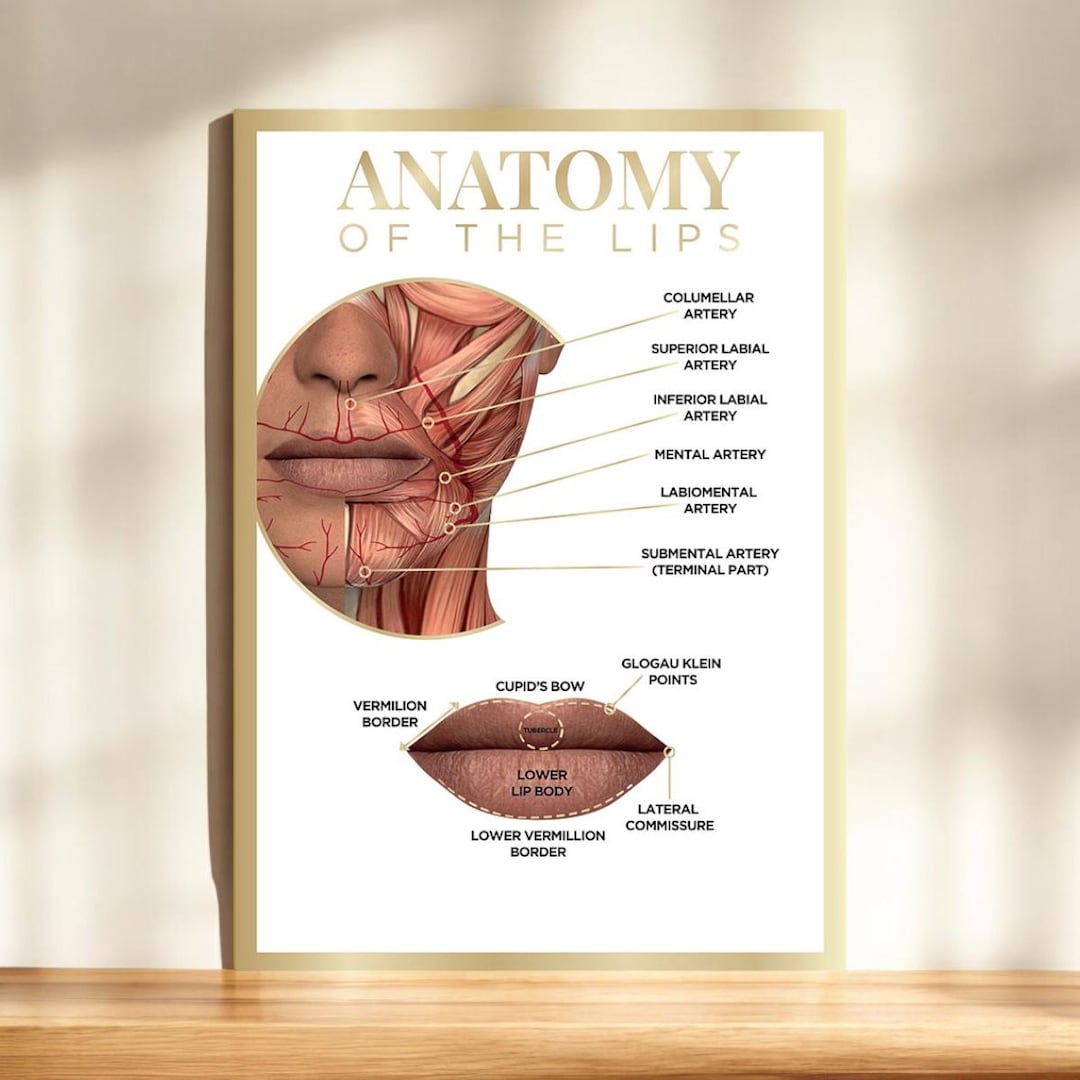
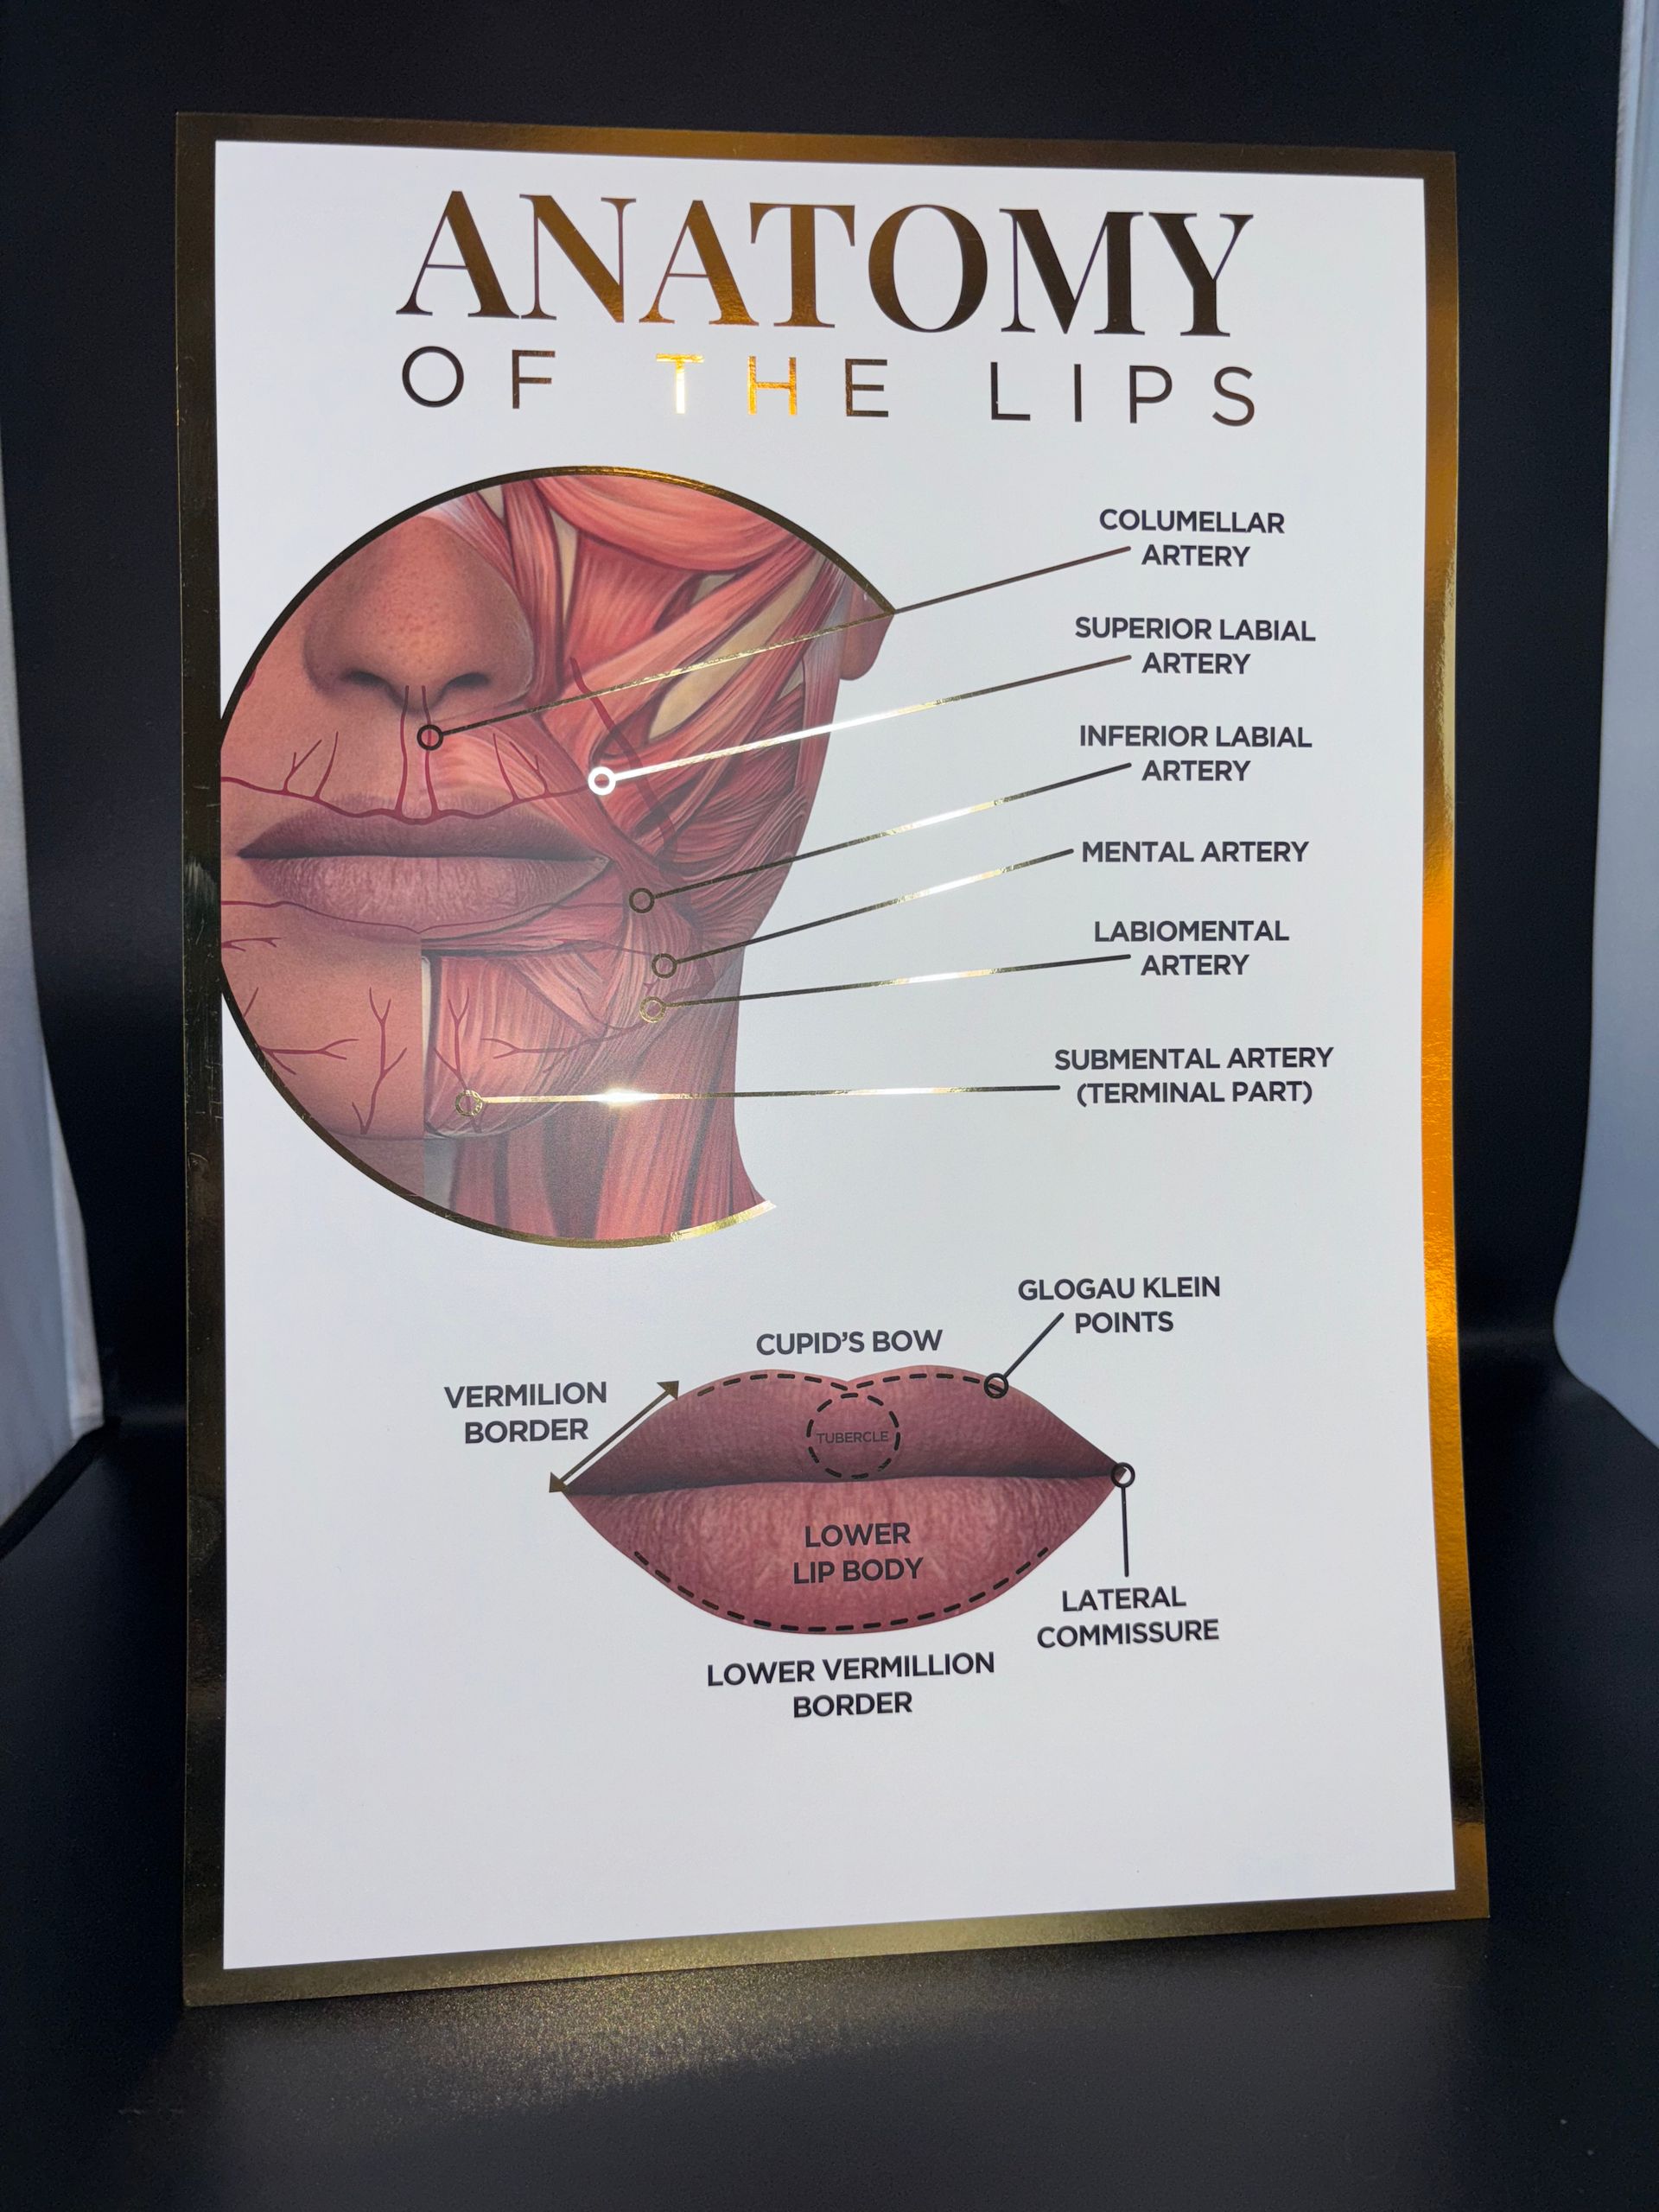
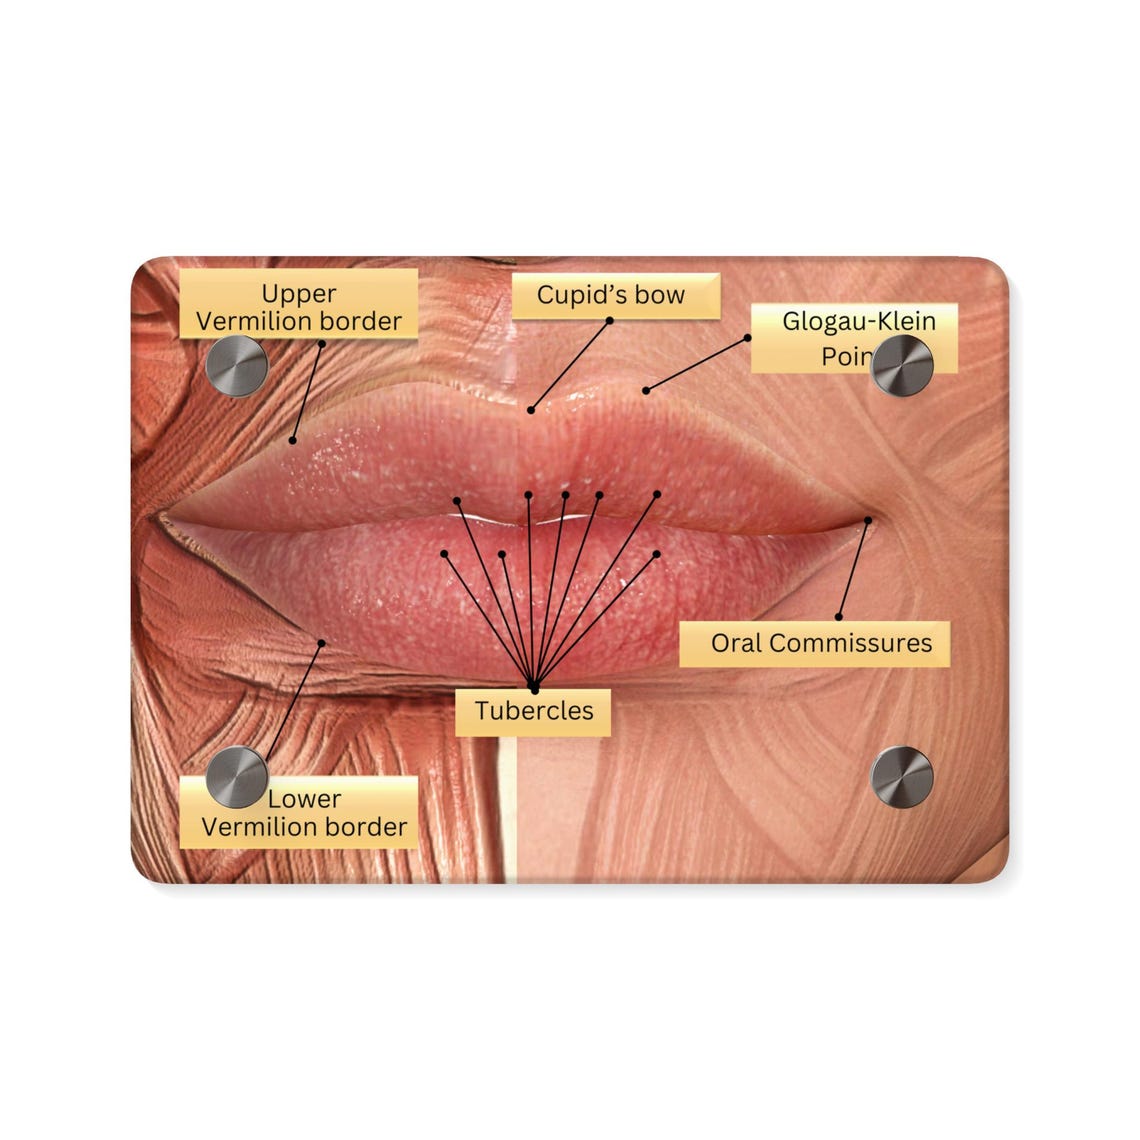
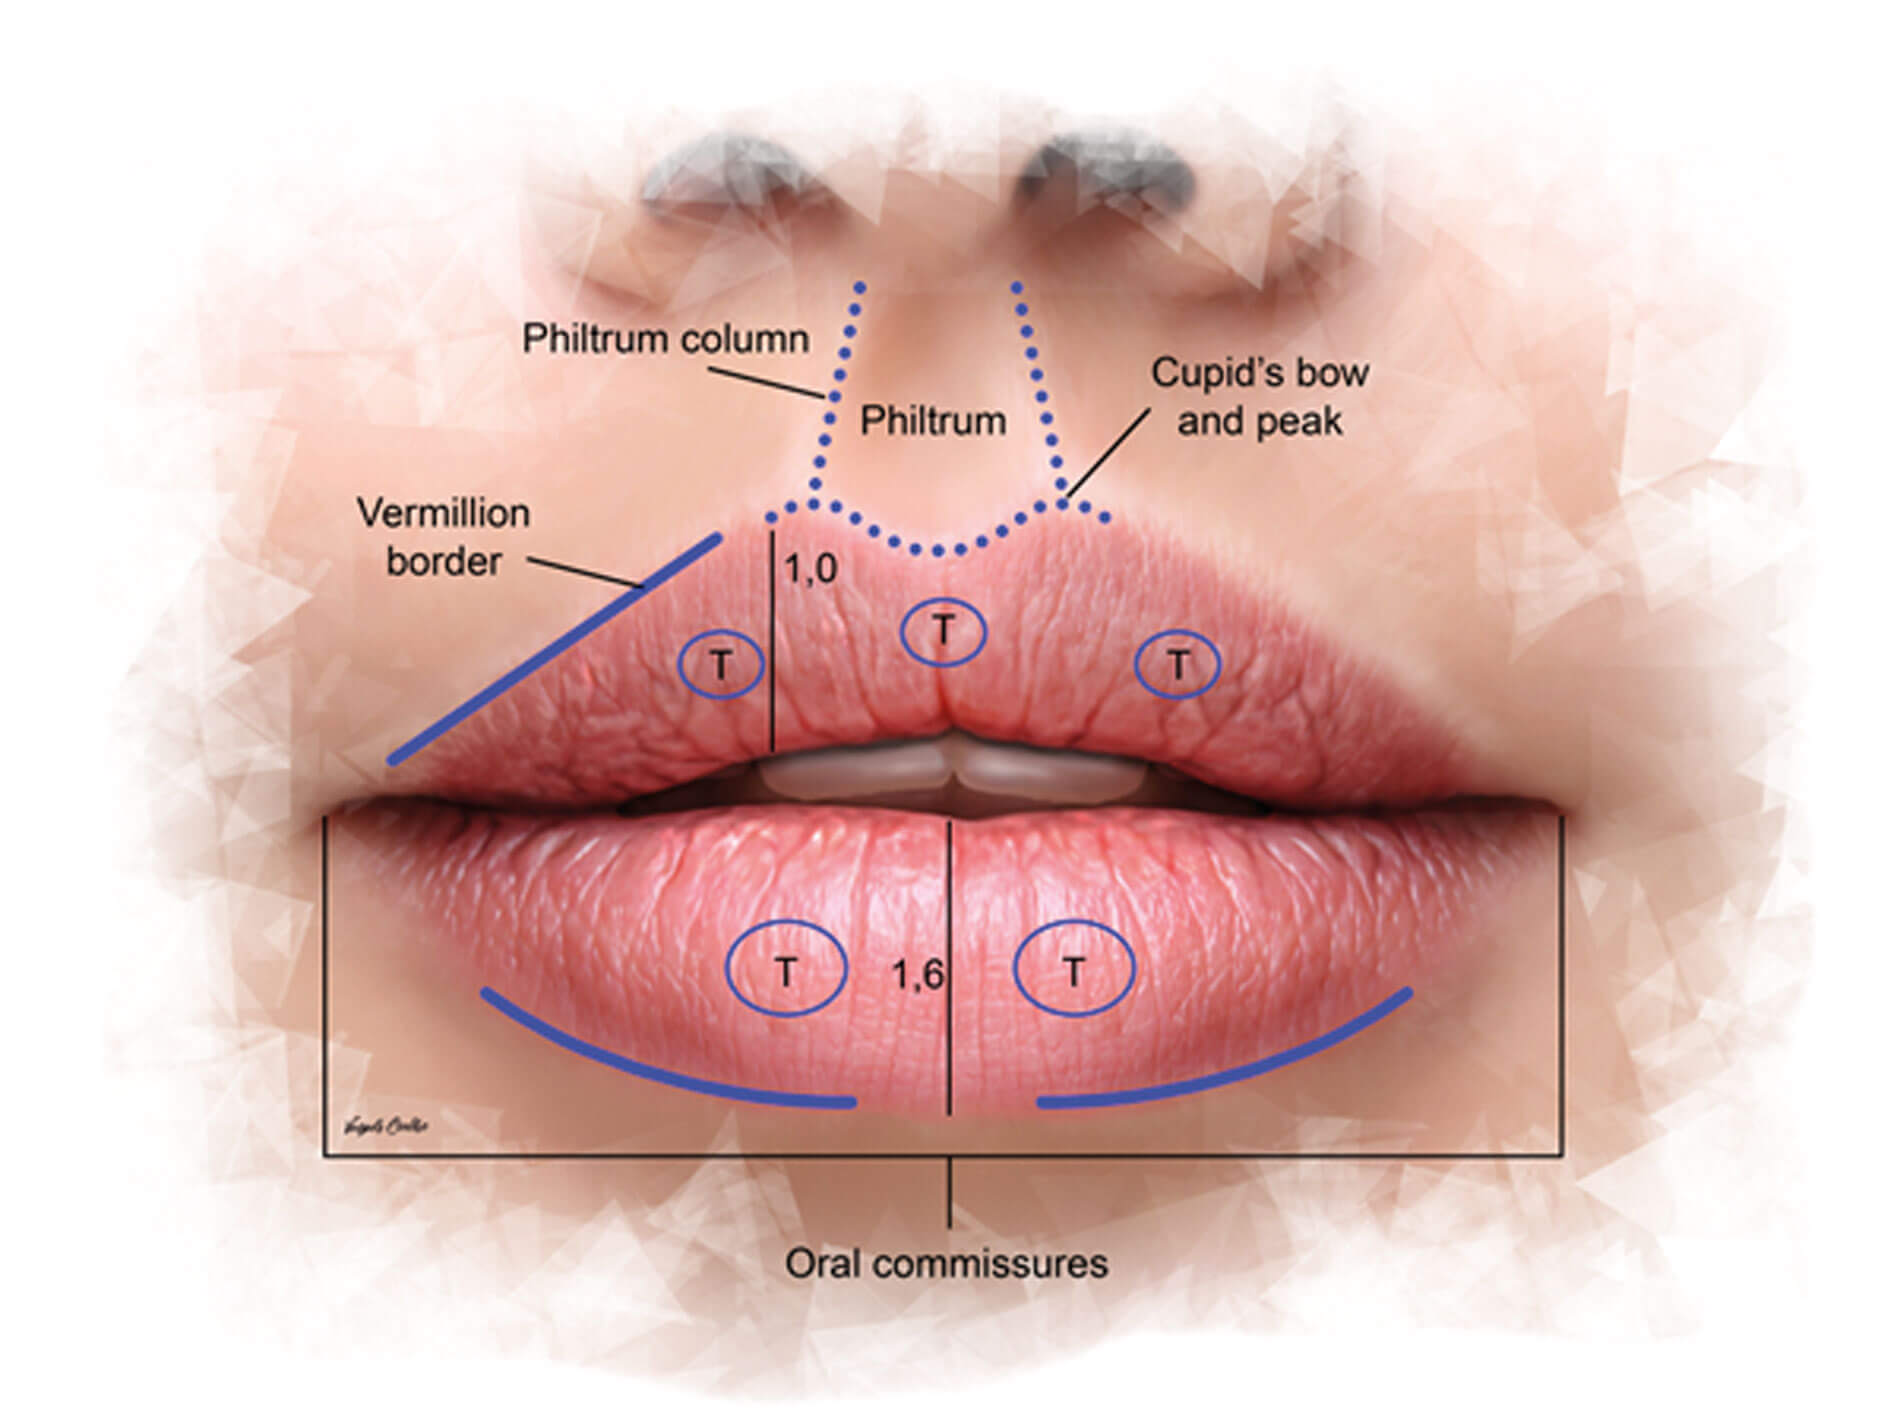
Starting from the outside and moving in, the first thing you hit is the skin. This is thin facial skin with hair follicles, sebaceous glands, and a fair bit of subcutaneous fat in the cutaneous portion. The vermillion border marks the transition from this skin to the red part of the lip. That border is not a sharp line on most people. It undulates. The peaks sit at the Cupid's bow and the lateral corners, and the troughs sit between them. The color change happens because the vermilion mucosa is much thinner than skin, the underlying capillary network is closer to the surface, and there is no keratin layer or melanin protection.
The red portion itself is specialized mucosa. It is moist, non-keratinized stratified squamous epithelium with a dense capillary plexus just beneath it. There are no salivary glands in the vermilion itself, which is why dryness and cracking happen so easily. You will find minor salivary glands on the inner mucosal surface, but they are sparse compared to the rest of the oral cavity.
Beneath that mucosa sits the orbicularis oris muscle. This is not a simple sphincter like a ring. It is a complex interwoven muscle with superficial, intermediate, and deep portions, and the fibers blend into the many perioral muscles that control expression. The muscle gives the lip its bulk and its dynamic function. When you purse, smile, or speak, the orbicularis is doing most of the work, supported by zygomaticus, levator, depressor, and buccinator fibers that merge into it.
Below the muscle is the labial mucosa on the inside, which lines the vestibule and attaches to the alveolar ridges of the maxilla and mandible. The frenula connect the inner lip to the gum tissue in the midline and sometimes laterally. This attachment point matters clinically because tight frenula can affect denture fit and orthodontic outcomes.
The blood supply comes primarily from the labial branches of the facial artery. These run along the (medial) aspect of the orbicularis, close to the mucosal surface, and anastomose across the midline with the contralateral side. This means bleeding from one side can be significant because the vessels are well connected. The facial artery itself comes off the external carotid, and the angular artery anastomoses with the ophthalmic system near the medial canthus. For anyone doing anything invasive near the medial lip, that connection is worth noting because embolization risk, though rare, exists in that corridor.
Venous drainage follows the arterial routes into the facial vein, which empties into the internal jugular. The facial vein has few valves, which is relevant for infection spread. A abscess in the lip or upper jaw can theoretically track backward toward the cavernous sinus through this valveless network.
Lymphatic drainage splits by location. The lower lip drains primarily to the submental and submandibular nodes. The upper lip drains to the submandibular and preauricular nodes. This split matters for oncology staging because malignancies in different lip zones behave differently and metastasize to different basins.
Innervation is equally layered. The upper lip gets sensory input from the infraorbital nerve, a branch of the maxillary division of the trigeminal nerve (V2). The lower lip and chin area are supplied by the mental nerve, a branch of the inferior alveolar nerve coming off the mandibular division (V3). The orbicularis oris itself receives motor innervation from the buccal and marginal mandibular branches of the facial nerve (CN VII). If you are doing any kind of regional block for dental or cosmetic work, knowing exactly where these nerves exit their bony channels is what keeps you from going in blind. The infraorbital foramen sits roughly 5 to 10 mm below the orbital rim in the mid-pupillary line, and the mental foramen is usually found between the premolars on a panoramic film. I have seen practitioners miss the mental foramen by a centimeter because they were relying on palpation alone rather than imaging.
Common Misunderstandings About Lip Anatomy
One thing that comes up constantly is the assumption that the vermilion border is the same thickness all the way across. It is not. The upper lip vermilion is typically higher in the central portion, measuring around 8 to 11 mm at the peak of the Cupid's bow, and tapers toward the corners where it may be only 3 to 5 mm. The lower lip vermilion is generally fuller, averaging around 10 to 12 mm. These numbers vary by sex, age, and individual anatomy, but the central upper lip being narrower than the lower lip is a consistent pattern.
Another frequent error is treating the orbicularis oris as a simple boundary. The muscle extends beyond what you see on the surface. Its superficial fibers sweep outward into the surrounding facial muscles, and the deeper fibers interdigitate with the modiolus at the corner of the mouth. The modiolus is a dense fibromuscular node about 1 cm lateral to the oral commissure where multiple facial muscles converge. It is a key structural anchor, and disrupting it during surgery or injection can change lip dynamics in ways that are hard to reverse.
When I worked on a revision case a few years back, the patient had had multiple filler treatments in the vermilion zone and the border was essentially gone. The practitioner had injected too superficially, scattering product into the mucosa instead of placing it in the submuscular or deep intramuscular plane. The result was asymmetry, palpable nodules, and a flattened vermilion border that looked natural from a distance but felt wrong up close. We ended up using hyaluronidase to dissolve the misplaced filler and then re-establishing the border with a very conservative micro-droplet technique placed deep against the muscle, not in the mucosa. That case reminded me that depth matters more than volume every time.
Age-Related Changes You Need To Account For
Lip anatomy changes with age in predictable ways, and those changes are often mistaken for purely aesthetic concerns when they are really structural. The vermilion border everts and flattens because the supporting connective tissue degrades and the orbicularis loses tone. The white roll, which is the pale ridge just above the vermilion in younger people, disappears. Skin fine lines develop around the oral aperture due to sun damage and repetitive movement. The overall lip volume decreases because both the mucosal layer and the submucosal fat atrophy. The dental support also recedes over time, especially after tooth loss, which removes the anterior structural foundation for the lips.
For clinicians, this means that a young patient and an older patient present completely different challenges even when the complaint sounds similar. Filler placement that works for a 25-year-old with good structural support will look unnatural in a 65-year-old with significant atrophy and lost dental support. The older lip needs volumetric restoration that follows the natural layering of the anatomy, not just surface plumping.
What Most People Miss About Clinical Relevance
The labial arteries are not surface structures you can reliably palpate, but they run in a relatively consistent position about 5 to 8 mm from the vermilion border on the aspect of the orbicularis. If you are injecting in the vermilion zone, staying too lateral and too deep increases the chance of intravascular placement. The risk is low but real, and awareness of that vascular plane reduces it further.
Cleft lip anatomy is another area where textbook diagrams fall short of surgical reality. The classic unilateral cleft involves disruption of the orbicularis oris continuity, descent of the muscle fibers into the nasal floor, and attenuation of thelevator labii superioris alaeque nasi. Repair requires not just closing the skin and mucosa but reapproximating the muscle in its proper anatomic position. Getting the muscle alignment wrong leads to poor dynamic function and visible scarring. The nasolabial angle, the philtral columns, and the alar base position all depend on that muscular reconstruction.
Herpes simplex virus latency is another practical concern that ties directly to anatomy. The virus establishes latency in the trigeminal ganglion and reactivates along the sensory branches that supply the lip. Primary outbreaks often affect the gingiva and oral mucosa broadly, while recurrent outbreaks tend to localize at the vermilion border or the junction between the vermilion and skin. The localized nature of recurrences corresponds to the dermatomal distribution of the involved nerve branches.
Practical Takeaways
If you are studying this for exams, focus on the layering and the neurovascular landmarks. The infraorbital and mental nerve exit points are high-yield. If you are doing procedures, focus on depth and plane selection. The anatomy does not punish superficial injections gently. It punishes them with visible, long-lasting problems that take months to resolve. The labial artery anastomoses mean bleeding will not stop because you missed one vessel. The lymphatic drainage patterns matter for any lesion evaluation. And the modiolus is a structural landmark you should never ignore during surgical work near the oral commissure.
The anatomy of the lips is compact but dense. Every millimeter of difference in needle depth or injection plane changes the outcome. The tissue layers are real, the nerves are specific, and the blood supply is robust. Treat it with that level of respect and the results follow.
Gallery Anatomy Of The Lips
Lip Anatomy Poster Foiled Detailed Anatomy of the Lips for Aesthetic Clinics A3 - Etsy UK
A3 Gold Foil Anatomy Poster - Anatomy of the lips
Customized With Logo Anatomy of the Lips Nurse Injector Medspa Display, Structure of the Skin ...
Anatomy of lips with detailed labeled parts description vector illustration – Artofit
Anatomy Of Inner Lips And Nose - Infoupdate.org