Understanding Arm Vein Anatomy for Clinical Access
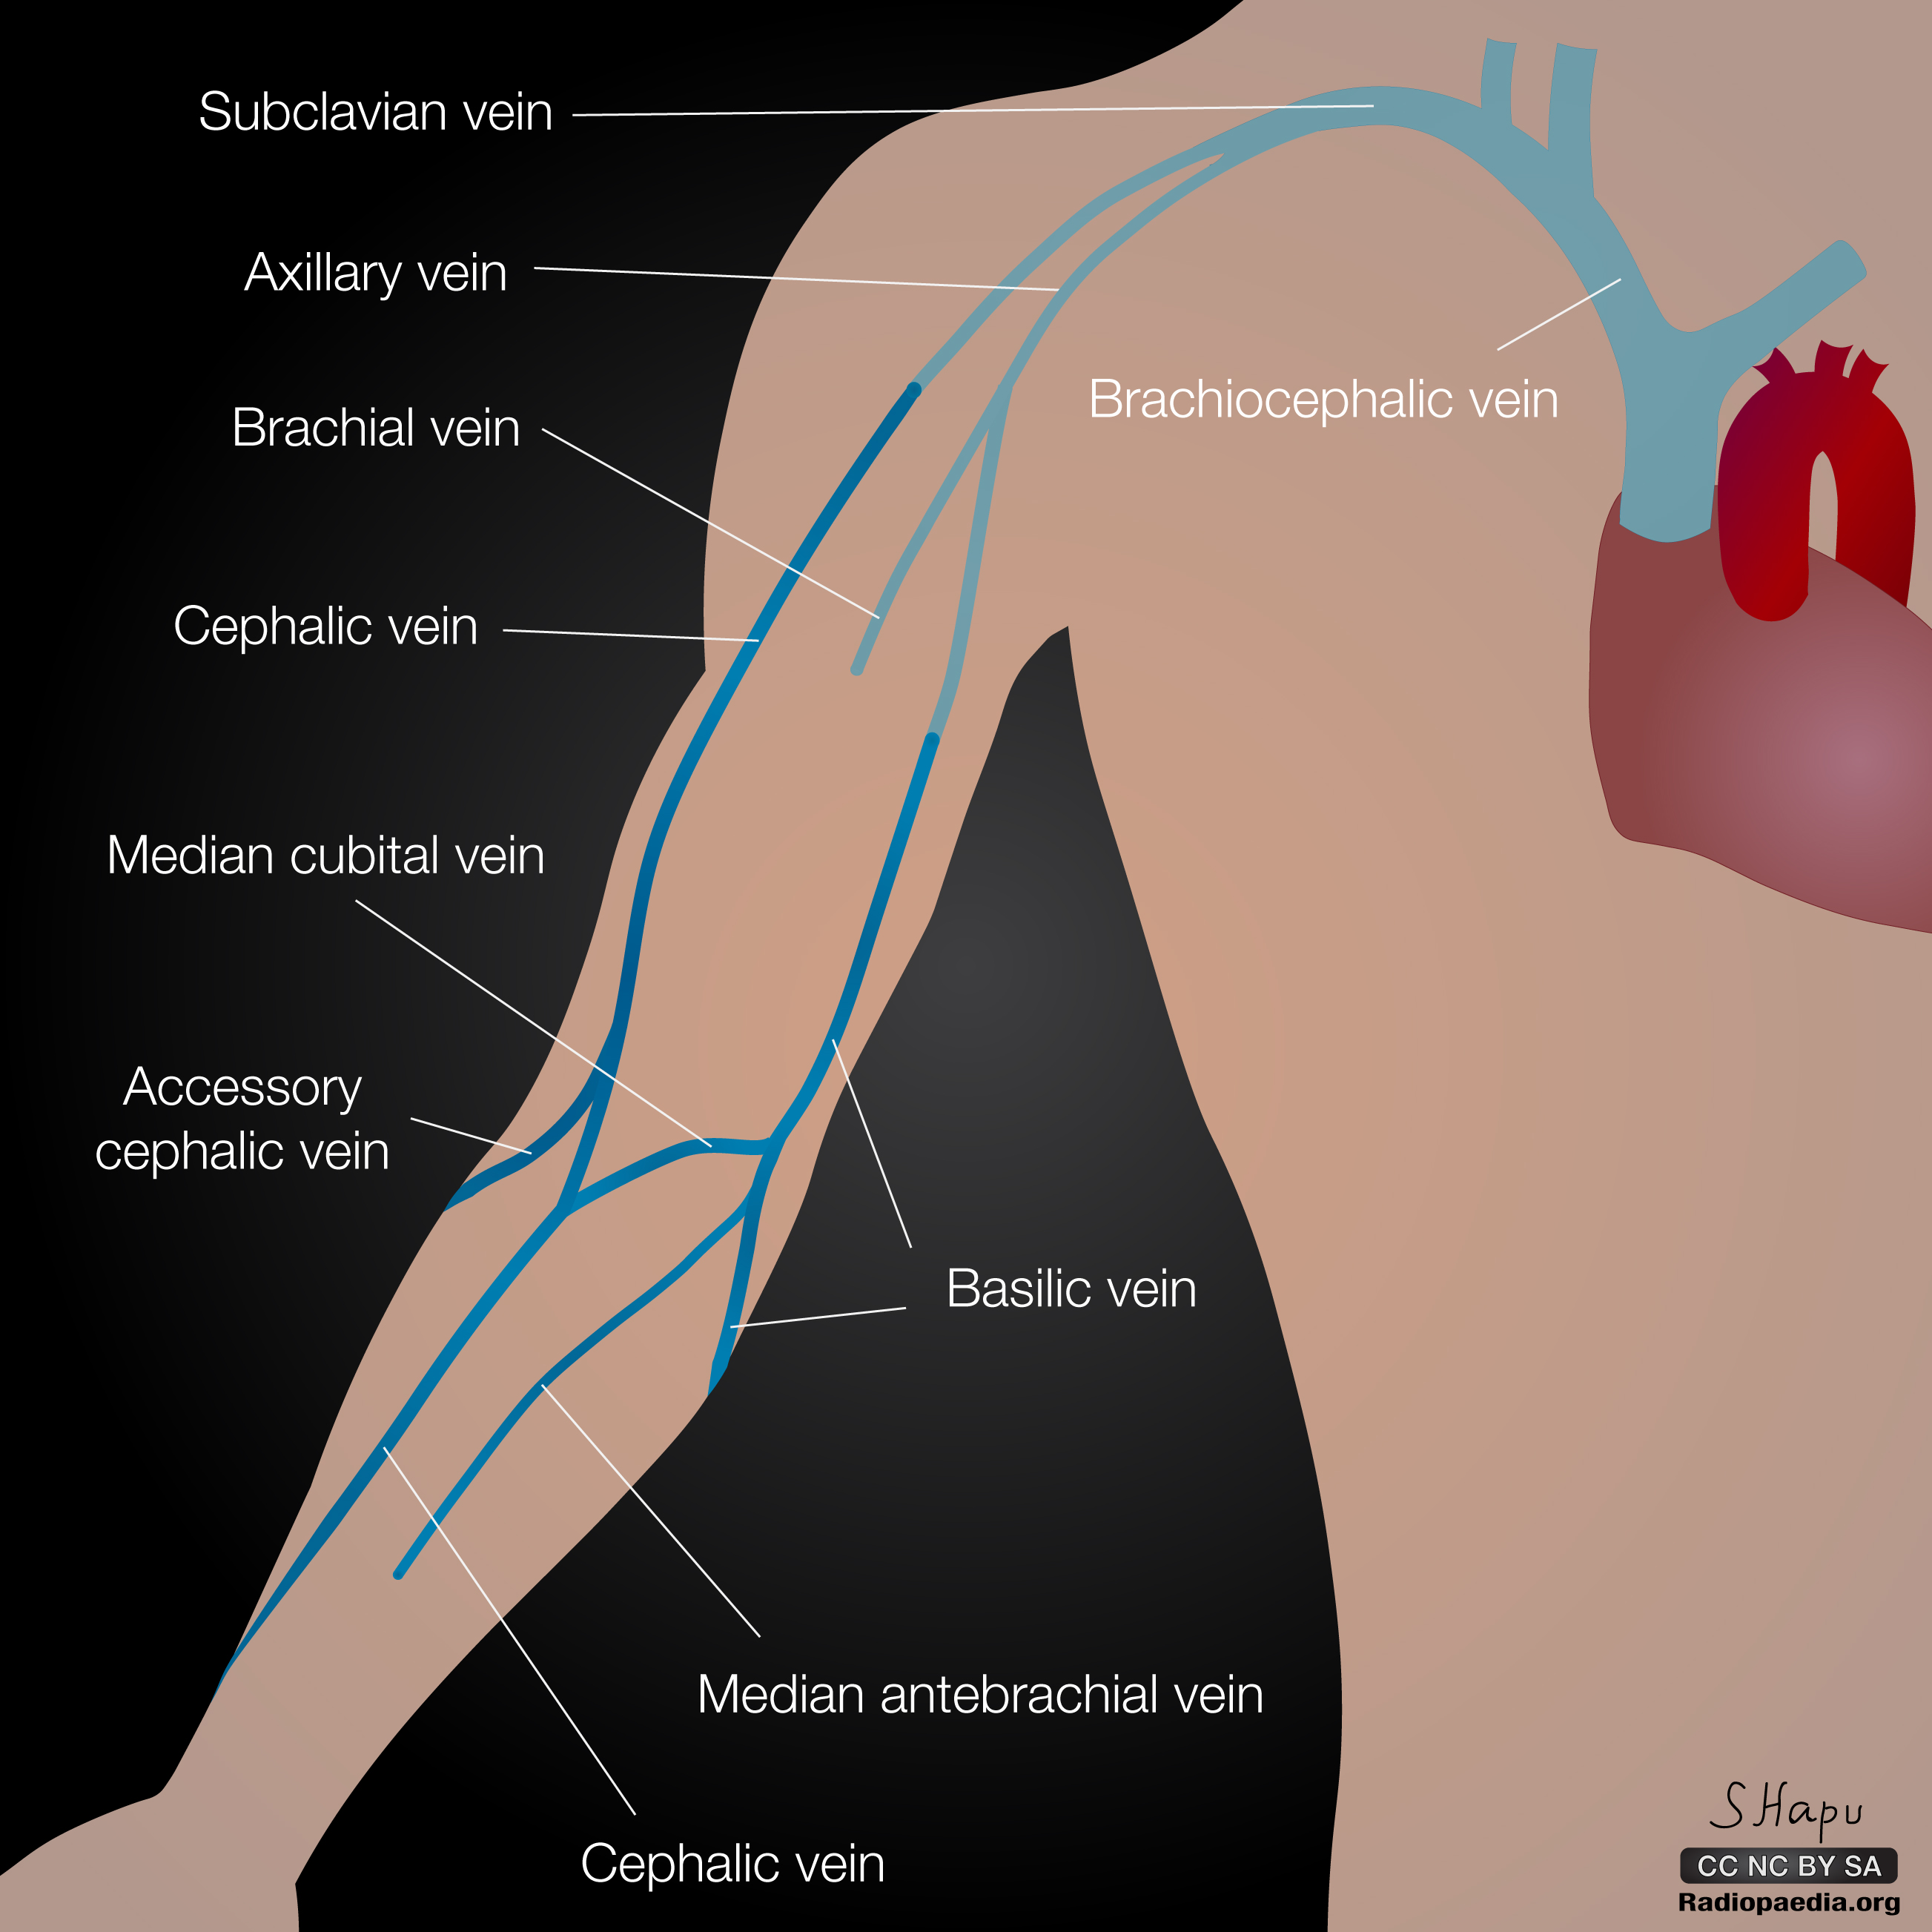
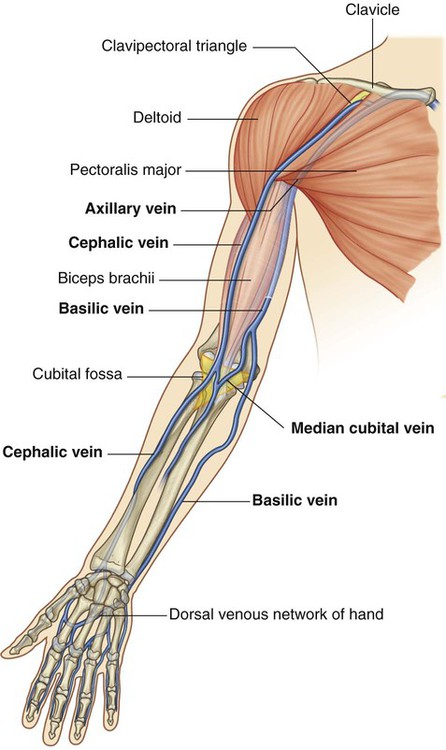
The venous system in the upper extremity is layered. Superficial veins sit just under the skin and are what nurses, phlebotomists, and emergency physicians actually work with day to day. Deep veins run alongside arteries inside the muscle compartment and only become relevant during advanced procedures like central line placements or when superficial routes have failed. The median cubital vein at the antecre fossa remains the most frequently used site because it is large, relatively fixed, and usually easy to palpate. That said, it is also the vein most likely to cause hematoma if you miss the lumen on the first pass, which is why understanding the surrounding anatomy matters more than memorizing access sites.
Practical Anatomy Of Veins In Arm For Phlebotomy And IV Placement
When I started doing venipuncture in a busy emergency department, I quickly learned that textbook diagrams do not prepare you for the reality of dehydrated patients, obese patients, or people with collapsed veins from repeated draws. The cephalic vein running along the lateral aspect of the arm is often the most predictable landmark, but its course is variable. In some patients it dives deep before reaching the deltopectoral groove, which means what looks like a promising vein on the surface can actually be unsupported by surrounding tissue and prone to rolling. I once attempted a peripheral IV on a patient whose cephalic vein looked robust until I advanced the catheter and met firm resistance. The vein had bifurcated into two smaller channels, neither wide enough for a 18-gauge catheter. I switched to the contralateral arm and accessed the basalcephalic branch instead, which was smaller but had better wall integrity. That took longer but prevented infiltration.
The median cubital vein connects the cephalic and basilic systems and is the preferred draw site in most outpatient laboratories. It is superficial, lacks nearby arteries, and typically has thinner walls than the more muscular basilic vein. The tradeoff is that it sits directly over the bicipital aponeurosis and the brachial artery. If you angle the needle too medially or advance past the venous wall, you can hit the artery, which presents as bright red pulsatile blood and requires immediate pressure for at least five minutes. I learned this from watching a colleague miss on a diabetic patient with fragile vessels and then spending twenty minutes applying pressure before the bleeding stopped.
The basilic vein runs along the medial side of the arm and is larger than the cephalic in many people, but it is also closer to the brachial artery and the median nerve. Needling too deeply in the antecre fossa risks nerve injury, which presents as a sharp electric shock sensation radiating down the forearm. The workaround is to approach from a lateral angle and keep the needle below the level of the bicipital aponeurosis. Ultrasound guidance eliminates most of this guessing, but it adds about two to three minutes per attempt and is not always available in primary care settings.
Deep Versus Superficial Systems And When They Matter
Superficial veins drain into the deep system through perforator veins at regular intervals. The most clinically relevant perforators are located in the antecre fossa and along the medial aspect of the forearm near the basilic vein. These junctions are where varicose veins form when valve incompetence allows retrograde flow, and they are also the sites where sclerotherapy injections are most effective for treating chronic venous insufficiency. If you are studying for licensing exams, focus on the paired deep veins that follow the brachial, radial, and ulnar arteries. They communicate with the superficial system through septal perforators and become the primary route for venous return when superficial pathways are compromised.
Peripheral IV catheters are sized from 14-gauge through 24-gauge, with 20-gauge and 22-gauge being the most common choices for adults. A 14-gauge catheter has an internal diameter of about 2.1 millimeters and can deliver fluids rapidly, which matters in trauma resuscitation. The downside is that it requires a large vein and causes significant discomfort if it infiltrates. A 24-gauge catheter is easier to place in fragile veins but limits infusion rates to roughly 120 milliliters per hour, which may be insufficient for patients requiring aggressive volume resuscitation.
Vein size changes with temperature, hydration status, and sympathetic tone. Cold hands constrict peripheral vessels within seconds, making even prominent veins nearly invisible to both sight and palpation. Warming the arm with a warm compress for two to three minutes restores venous diameter in most cases. I have seen this turnaround consistently in patients presenting for outpatient blood draws during winter months, where the failure rate without pre-warming can exceed thirty percent compared to single-digit rates after warming.
Common Pitfalls That Are Not Covered In Training Manuals
Rolling veins are the most frequent complication during peripheral IV placement, affecting approximately forty percent of attempts in inexperienced hands. The vein moves laterally when the needle contacts it because the surrounding connective tissue does not anchor it firmly. Stabilizing the skin by pulling it taut below the insertion site with your thumb reduces rolling significantly, but this technique requires practice and is often skipped under time pressure.
Blunted needles create a different problem. A needle that has been used multiple times or accidentally touched bone develops a microscopically irregular tip that tears rather than punctures the venous wall. This increases the risk of hematoma formation and infiltration. In my experience, switching to a fresh needle after two unsuccessful passes reduces complication rates more effectively than continuing with the same needle and increasing angulation.
Deep vein thrombosis in the arm is rare but serious. Primary upper extremity DVT accounts for less than five percent of all DVT cases and is associated with indwelling catheters, pacemaker leads, or repeated trauma to the venous system. Patients present with arm swelling, pain, and sometimes cyanosis. The diagnosis requires duplex ultrasound because physical examination alone misses up to thirty percent of cases. I encountered a patient who developed subtle arm swelling after a routine PICC line placement and was initially dismissed as having a soft tissue injury. It took three days of persistent questioning before we obtained an ultrasound that confirmed the thrombosis, and by then the line had to be removed.
Note: This guide covers general anatomical concepts for educational purposes. Clinical procedures should be performed by trained healthcare professionals following established protocols and institutional guidelines.
Gallery Anatomy Of Veins In Arm
Anatomy Of Veins In The Arm Fig. Forearm And Hand Arterial And Venous
Upper Arm Veins Upper Limb Veins Anatomyzone 20190106 PDF) Anatomy Of
Anatomy Of The Arm Veins Antique Illustration Of Human Body Anatomy
Veins Of The Arm Injection Time!: SEXY GIRLS with their SLEEVES ROLLED UP!
Veins Of The Arm