Muscle and Ligament Insertion Anatomy: A Practical Guide
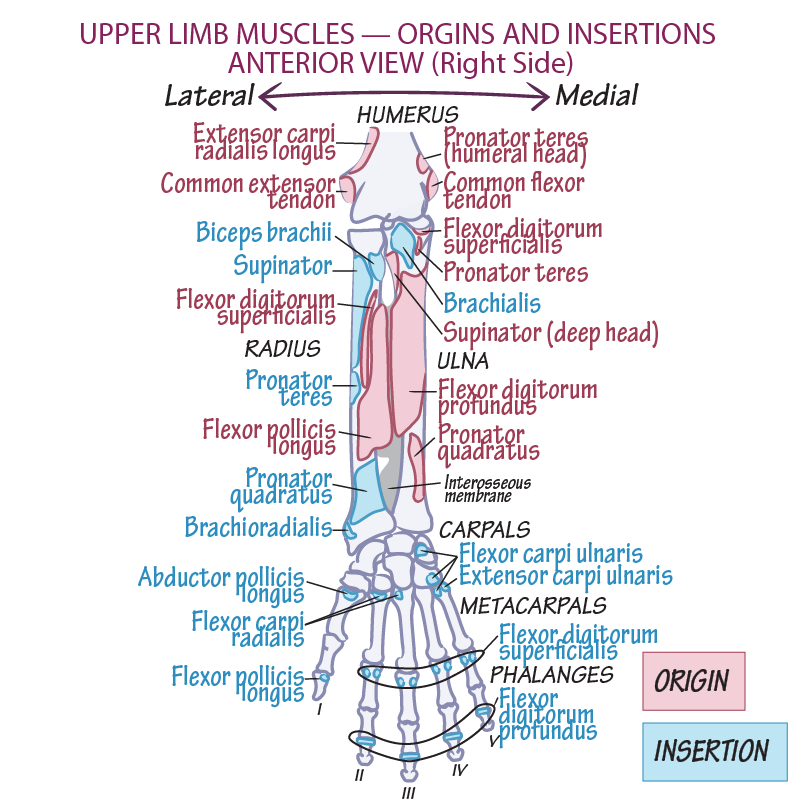
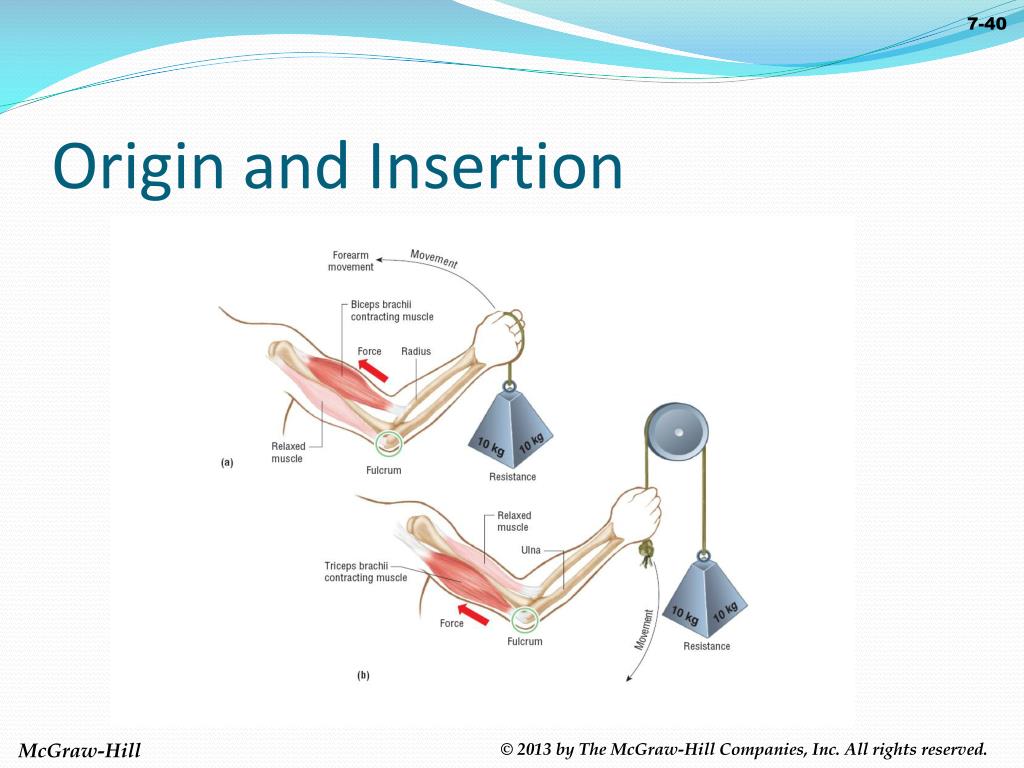
Every musculoskeletal structure has two attachment points. One end anchors to a stable bone, usually called the origin. The other end attaches to the bone that moves during contraction, usually called the insertion. That is the basic framework. In practice, it gets messier, and the distinction matters a lot when you are actually looking at anatomy or working near these structures. The insertion point is where the contractile force of a muscle or tensile force of a ligament transfers into movement or stabilization. Tendons converge at the insertion, often fanning out or forming a narrow cord depending on the muscle. Ligaments sit at joint capsules and attach directly to periosteum in most cases. The tissue at the insertion site is mechanically distinct from the mid-belly. Collagen fibers orient differently, and the extracellular matrix composition shifts as you approach the bone interface. This transition zone is called the entheses, and it is where most injuries accumulate over time. Students often memorize origin and insertion lists without understanding what changes during movement. A muscle does not always pull the insertion toward the origin in a straightforward linear fashion. Closed chain movements flip the relationship. Think about a squat or a pull-up. The distal attachment becomes relatively fixed, and the proximal attachment moves instead. The labels stay the same, but the biomechanics invert. This is something you will notice quickly if you ever do palpation work or ultrasound imaging in real patients.
Not every structure follows a clean origin-to-insertion model. Some muscles have multiple insertion points, like the deltoid, which fans across the lateral clavicle, acromion, and spine before converging toward the humerus. Others have dual bellies or accessory heads that blur the line between what is origin and what is insertion. The coracobrachialis is a small muscle with a short belly and a clean insertion on the medial humerus, but its dual-head origin on the coracoid process makes it a poor candidate for simple memorization. These exceptions are not trivia. They show up in clinical scenarios constantly.
Common Clinical Insertion Sites
Certain insertion points come up repeatedly in procedural work. The deltoid insertion on the deltoid tuberosity of the humerus is a standard intramuscular injection site, though not the deepest option available. The quadriceps tendon inserts on the patella and continues as the patellar ligament to the tibial tuberosity. This entire extensor mechanism is critical for knee stability and a frequent site of overload injuries. The Achilles tendon inserts on the calcaneus and carries massive tensile loads during gait. Ruptures here are common, and surgical repair requires careful attention to the insertion geometry to restore function properly. Nerve block procedures rely heavily on knowing where muscles insert so you can avoid accidental tendon penetration. The supraspinous muscle inserts along the supraspinous fossa of the scapula, and the infraspinous muscle inserts on the greater tubercle of the humerus. These posterior shoulder insertions are close to the axillary nerve and the posterior circumflex humeral artery. Approaching from the wrong angle without image guidance increases the risk of vascular injury significantly. I learned this the hard way early in residency when I attempted an interscalene block using surface landmarks alone on a patient with abnormal scapular positioning due to a prior thoracic surgery. The needle tip registered near the axillary artery rather than the intended neural targets. Switching to real-time ultrasound immediately corrected the trajectory, and the procedure completed safely. That experience changed how I approach every upper extremity block since.
Get the Full Details

Pitfalls and Limitations
Textbook descriptions of insertion points assume standard anatomy. They do not account for anatomical variants, which appear in roughly 10 to 15 percent of the population for major muscle attachments alone. Accessory heads, split insertions, and anomalous origin points are not rare. If you are learning this material for surgical planning, ultrasound-guided procedures, or sports medicine evaluation, relying exclusively on atlas references is risky. Imaging should supplement your anatomical knowledge whenever possible. Another common error is assuming the insertion is always the distal attachment. Proximal insertions exist. The psoas major, for example, inserts on the lesser trochanter of the femur, which is proximal relative to many thigh muscles but distal relative to its lumbar origins. Confusion about directionality leads to incorrect movement analysis, especially in rehabilitation settings where therapists need to predict how altered biomechanics will affect a patient's gait or posture. Ligament insertions are often overlooked in favor of muscular ones, but they deserve equal attention. The anterior cruciate ligament inserts on the anterior intercondylar area of the tibia and the lateral femoral condyle. The posterior cruciate ligament inserts on the posterior intercondylar area. These tibial footprints are critical for surgical graft placement during reconstruction. Placing a graft millimeters away from the native insertion point alters knee kinematics and increases failure rates. Research shows that anatomic single-bundle ACL reconstruction with proper footprint placement has significantly better outcomes than non-anatomic techniques. This is not a minor detail.
Practical Takeaways
When studying insertion anatomy, focus on the functional implications rather than rote memorization. Ask yourself what happens when that insertion point is compromised. What movements are lost? What compensatory patterns emerge? How does surgical repair alter the tension-length relationship? These questions make the material stick better than any flashcard system. If you are working clinically, learn to palpate insertion points on live subjects. The lateral epicondyle, the greater tubercle, the calcaneal insertion, the iliac crest — these are all accessible surface landmarks that become clearer through repeated physical examination. Palpation reinforces spatial understanding in a way that images alone cannot replicate. Spend time with cadavers if you have the opportunity. Nothing clarifies the three-dimensional relationships between insertion points, surrounding neurovascular structures, and fascial planes like direct dissection. The anatomy of insertion points is foundational but incomplete without understanding the dynamic context in which those structures operate. Movement changes everything. Variants are the norm, not the exception. Clinical application demands more than textbook knowledge. Build your understanding around function, and the details will follow.