Why You Need a Proper ABI Worksheet
The Ankle Brachial Index Worksheet is one of those documents that looks simple on paper but becomes a nightmare during actual patient assessment if you haven't thought through the workflow. I used to scribble numbers on scrap paper and recalculate by hand, which sounded fine until I was dealing with 30 patients in a day and my math started drifting. That's when I built a proper template and stuck with it. Here's how to actually use one without wasting time or making errors.
Setting Up Your Ankle Brachial Index Worksheet
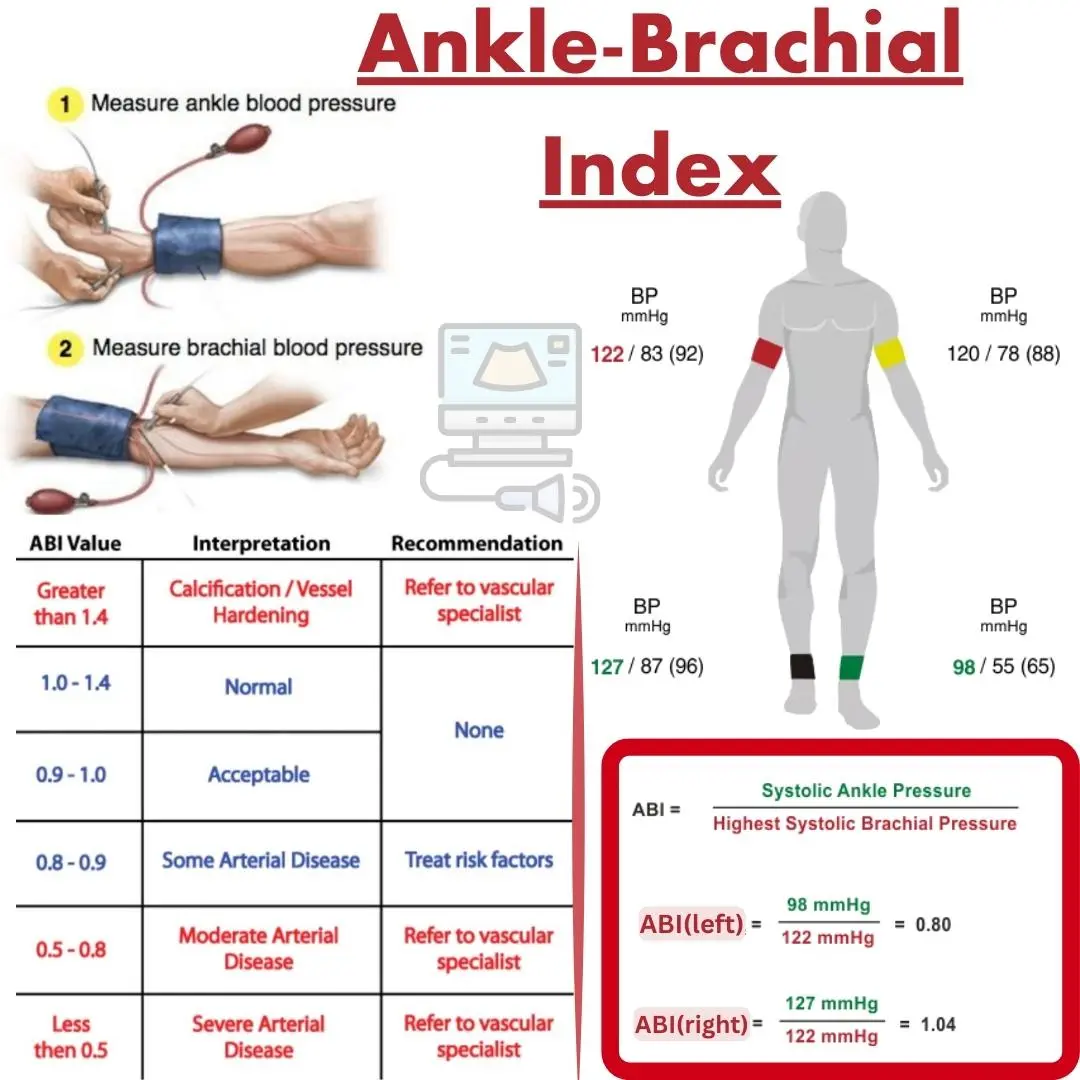
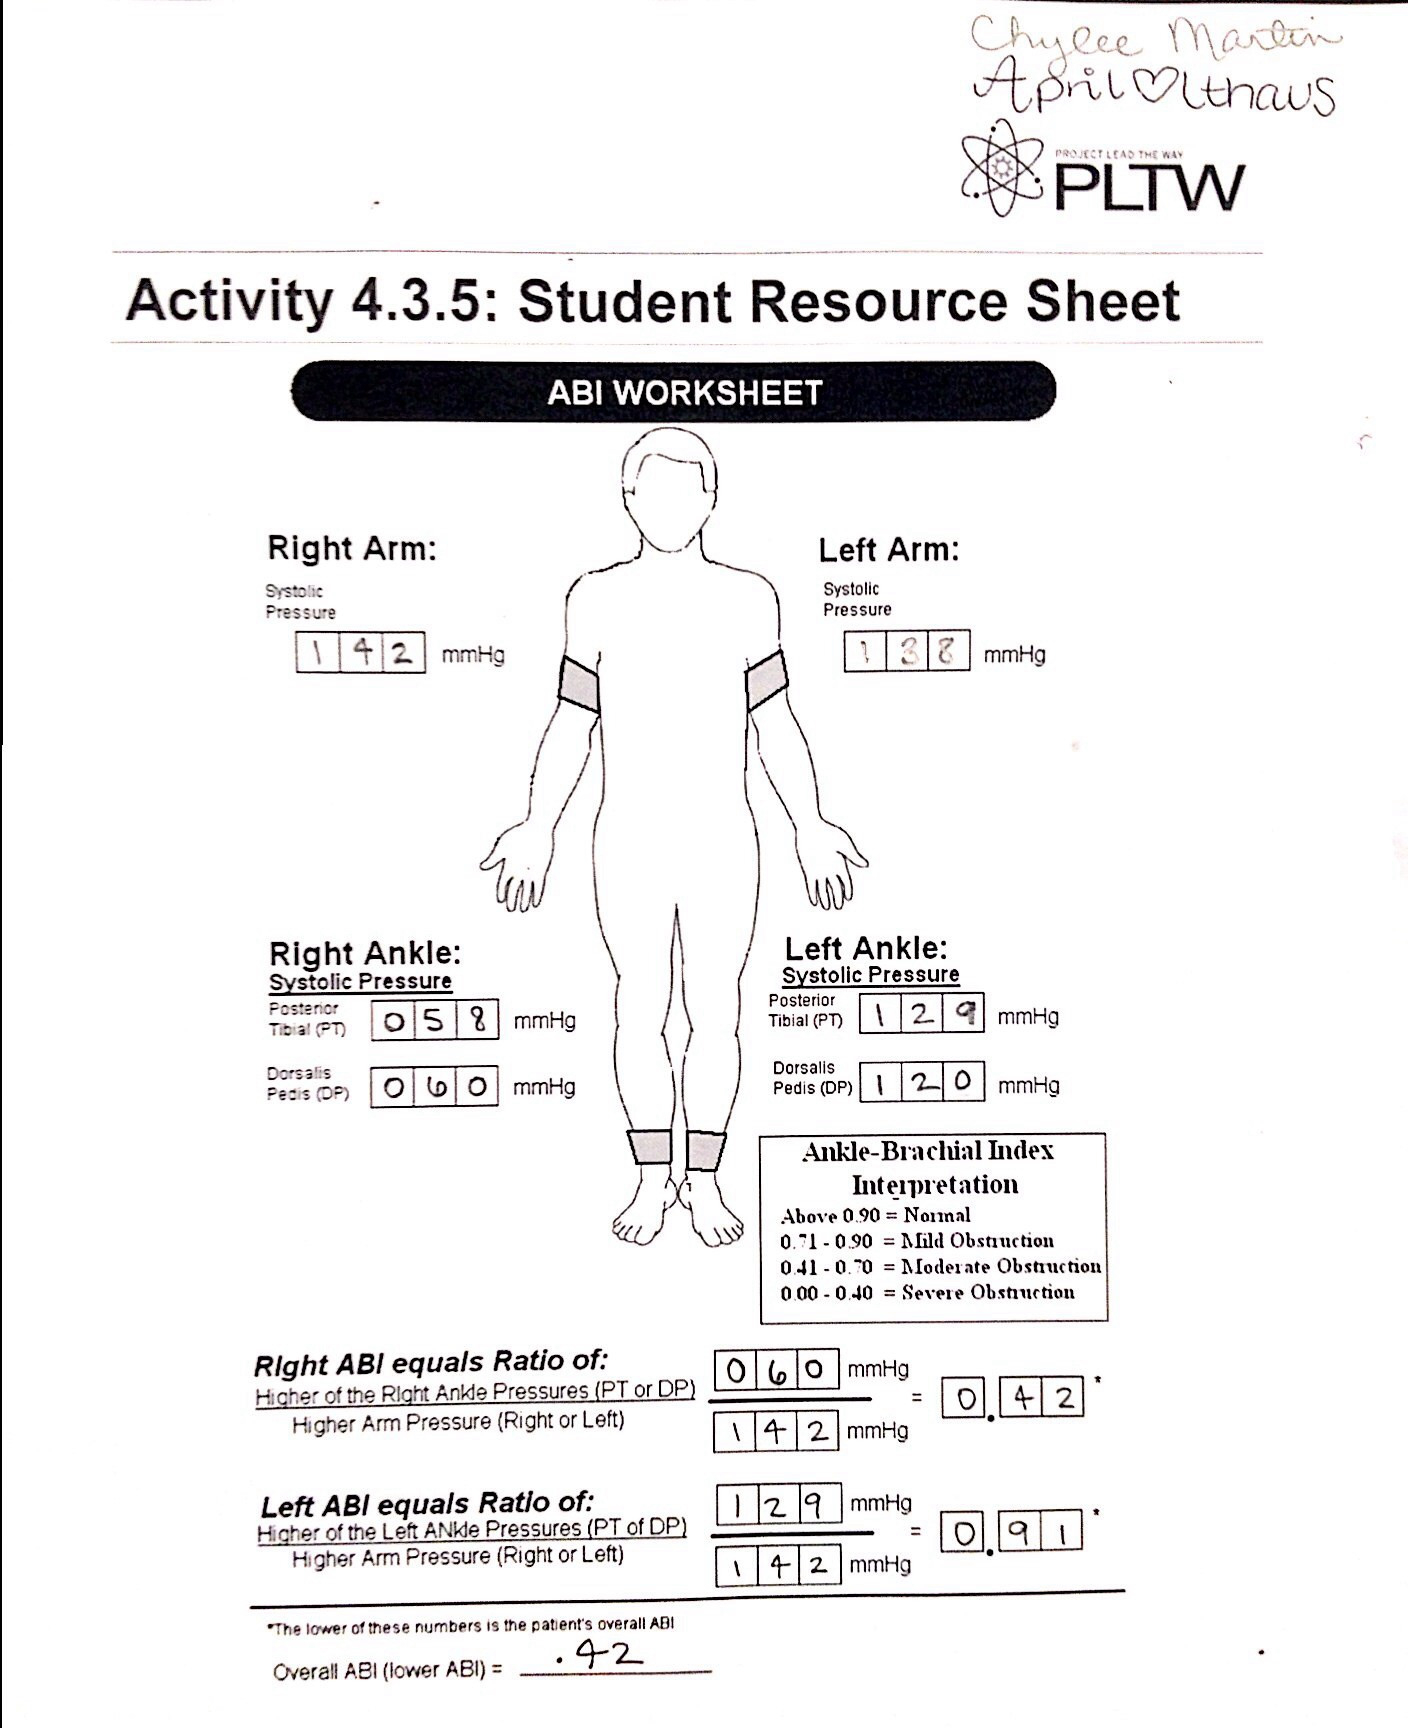
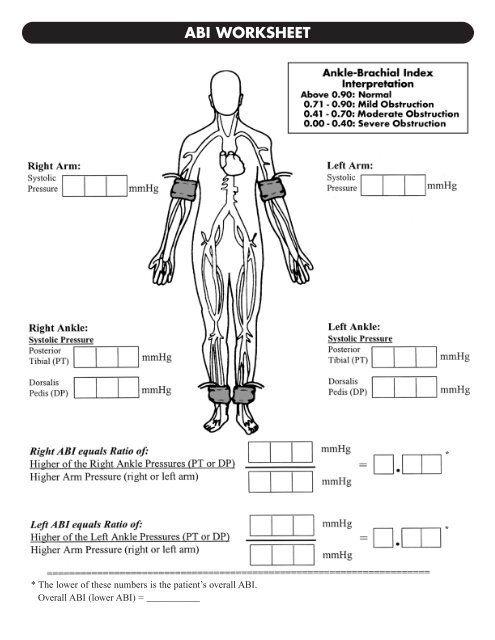
A functional ABI worksheet needs columns for four values per leg: right and left dorsalis pedis pressures, right and left posterior tibial pressures, and then the brachial systolic reference. The index itself is calculated by dividing the highest ankle pressure by the highest arm pressure on the same side. That's it in theory. In practice, your worksheet should also include fields for pulse quality notation, compression artifacts, and a final interpretation column. Most basic templates skip the compression artifact note, which is a mistake I made early on. You'd be surprised how often elevated ankle pressures from medial calcinosis throw off the entire reading, and if you don't document that possibility at the time of measurement, you've lost the context forever. Keep the worksheet split into left and right sections with a clear brachial reference row at the top. I use a single brachial value as the denominator for both sides rather than taking separate arm readings for each leg. It saves about 90 seconds per patient and the clinical difference is negligible unless you have subclavian stenosis, which you'd likely already know from symptoms or a pulse discrepancy.
Running Through a Measurement
Start with the patient supine for at least five minutes. That rest period matters more than most clinicians give it credit for. I've seen rest times compressed down to ninety seconds in busy clinics, and the resulting ABI can shift by 0.1 to 0.2 points depending on residual vasodilation or venous pooling. Measure all four limb pressures using a handheld Doppler with a 10 MHz probe. Dorsalis pedis first, then posterior tibial on each leg. Record the highest usable systolic pressure for each site. If you can't get a clean signal, try repositioning the ankle slightly or applying a bit more gel. A weak signal usually means the probe angle is wrong, not that the vessel is occluded. For the brachial pressure, take both arms and use the higher of the two as your reference. Write it clearly at the top of your worksheet so there's no ambiguity about which value you're dividing by. I've seen people accidentally use the lower arm pressure, which inflates every ABI on that page and can turn a normal result into a falsely abnormal one.
Get the Full Details
Calculate each ABI, document it immediately, and flag any value above 1.30. That's the non-compressible threshold where the result is unreliable and you need an alternative test like toe-brachial index or pulse volume recording.
Edge Cases That Break Standard Worksheets
Here's something that tripped me up for months: diabetic patients with calcified vessels. I had a case where the ABI read 1.45 on the right and 1.38 on the left, which the standard worksheet would classify as non-compressible borderline. The patient had rest pain and a non-healing ulcer on the right foot. The ABI was lying to us because the vessels wouldn't collapse under the cuff. The workaround was straightforward but easy to miss if you're focused only on filling out the worksheet correctly. I switched to measuring dorsalis pedis and posterior tibial peak systolic velocities with spectral Doppler, then calculated a toe-brachial index using a pediatric cuff on the big toe. The toe pressures came back at 0.42 and 0.38, which matched the clinical picture far better than the ankle pressures ever did. If your worksheet doesn't have a section for toe pressures and alternative indices, add one. It takes three extra lines and saves you from misclassifying a critical case.
Common Pitfalls and What They Cost You
The biggest error source isn't calculation. It's inconsistent cuff sizing. Using a standard adult cuff on a patient with large calves or significant edema will overestimate ankle pressures by 10 to 20 mmHg. I learned this the hard way when a follow-up study showed discrepant ABIs compared to a vascular lab using properly sized cuffs. The discrepancy was entirely technique-driven. Another issue is probe pressure. Pressing too hard with the Doppler probe compresses the artery beneath the skin and gives a falsely low reading. The fix is to use the lightest contact that still produces a clean signal. It feels counterintuitive at first because you want to press down to get a signal, but light contact is what gives you accuracy. Temperature also matters. I've seen cold patients drop their toe and ankle pressures by 15 to 30 mmHg simply from a room that was too cool. Warming the extremities for ten minutes before measurement eliminates this variable entirely and makes your worksheet data far more reliable.
 (1).jpg)
Interpreting the Numbers
An ABI between 0.91 and 1.30 is normal. Below 0.90 indicates peripheral arterial disease. Below 0.40 suggests critical limb ischemia. Above 1.30 means non-compressible vessels. These thresholds are well established but they come with a caveat that most worksheets don't mention: the test has a 5 to 10 percent false-negative rate in diabetic and elderly populations because the calcification problem I described earlier. Don't treat a single ABI as definitive when the clinical picture doesn't match. A normal ABI in a symptomatic diabetic patient is a red flag, not reassurance. Repeat the measurement after warming, check both posterior tibial and dorsalis pedis signals carefully, and if doubt remains, move to toe pressures or referral for vascular imaging. Your worksheet should end with a results interpretation section that forces you to write down whether the clinical presentation aligns with the numeric result. That single line catches more diagnostic errors than anything else on the page.
Where to Get or Build Your Template
Most hospital procurement departments have a standard ABI worksheet in their packet, but they're often generic and missing the nuance fields I mentioned. A properly designed one should take about twenty minutes to set up in Excel or Google Sheets if you're building from scratch, and it should include automatic calculation columns so you're not doing division by hand. What I use is a simplified sheet with pre-formatted rows for each measurement site, an automatic ABI column that flags values outside 0.91 to 1.30 in yellow, and a comments section at the bottom for artifact notes or alternative testing recommendations. It cut my documentation time from roughly four minutes per patient down to about ninety seconds and eliminated calculation errors almost entirely. If you're looking for a ready-made template, search for the American Heart Association or Society for Vascular Surgery ABI documentation forms. They're free and cover the essential fields. Just add your own compression artifact column and toe pressure section before you start using it clinically.