Understanding The Structures Around The Ankle
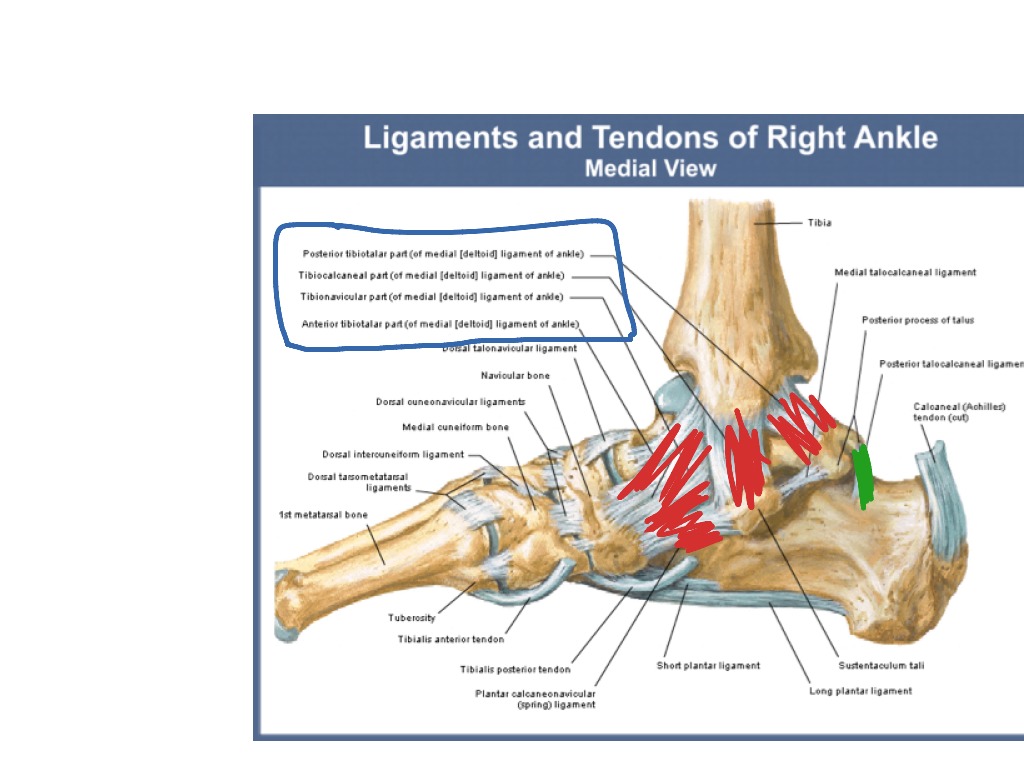
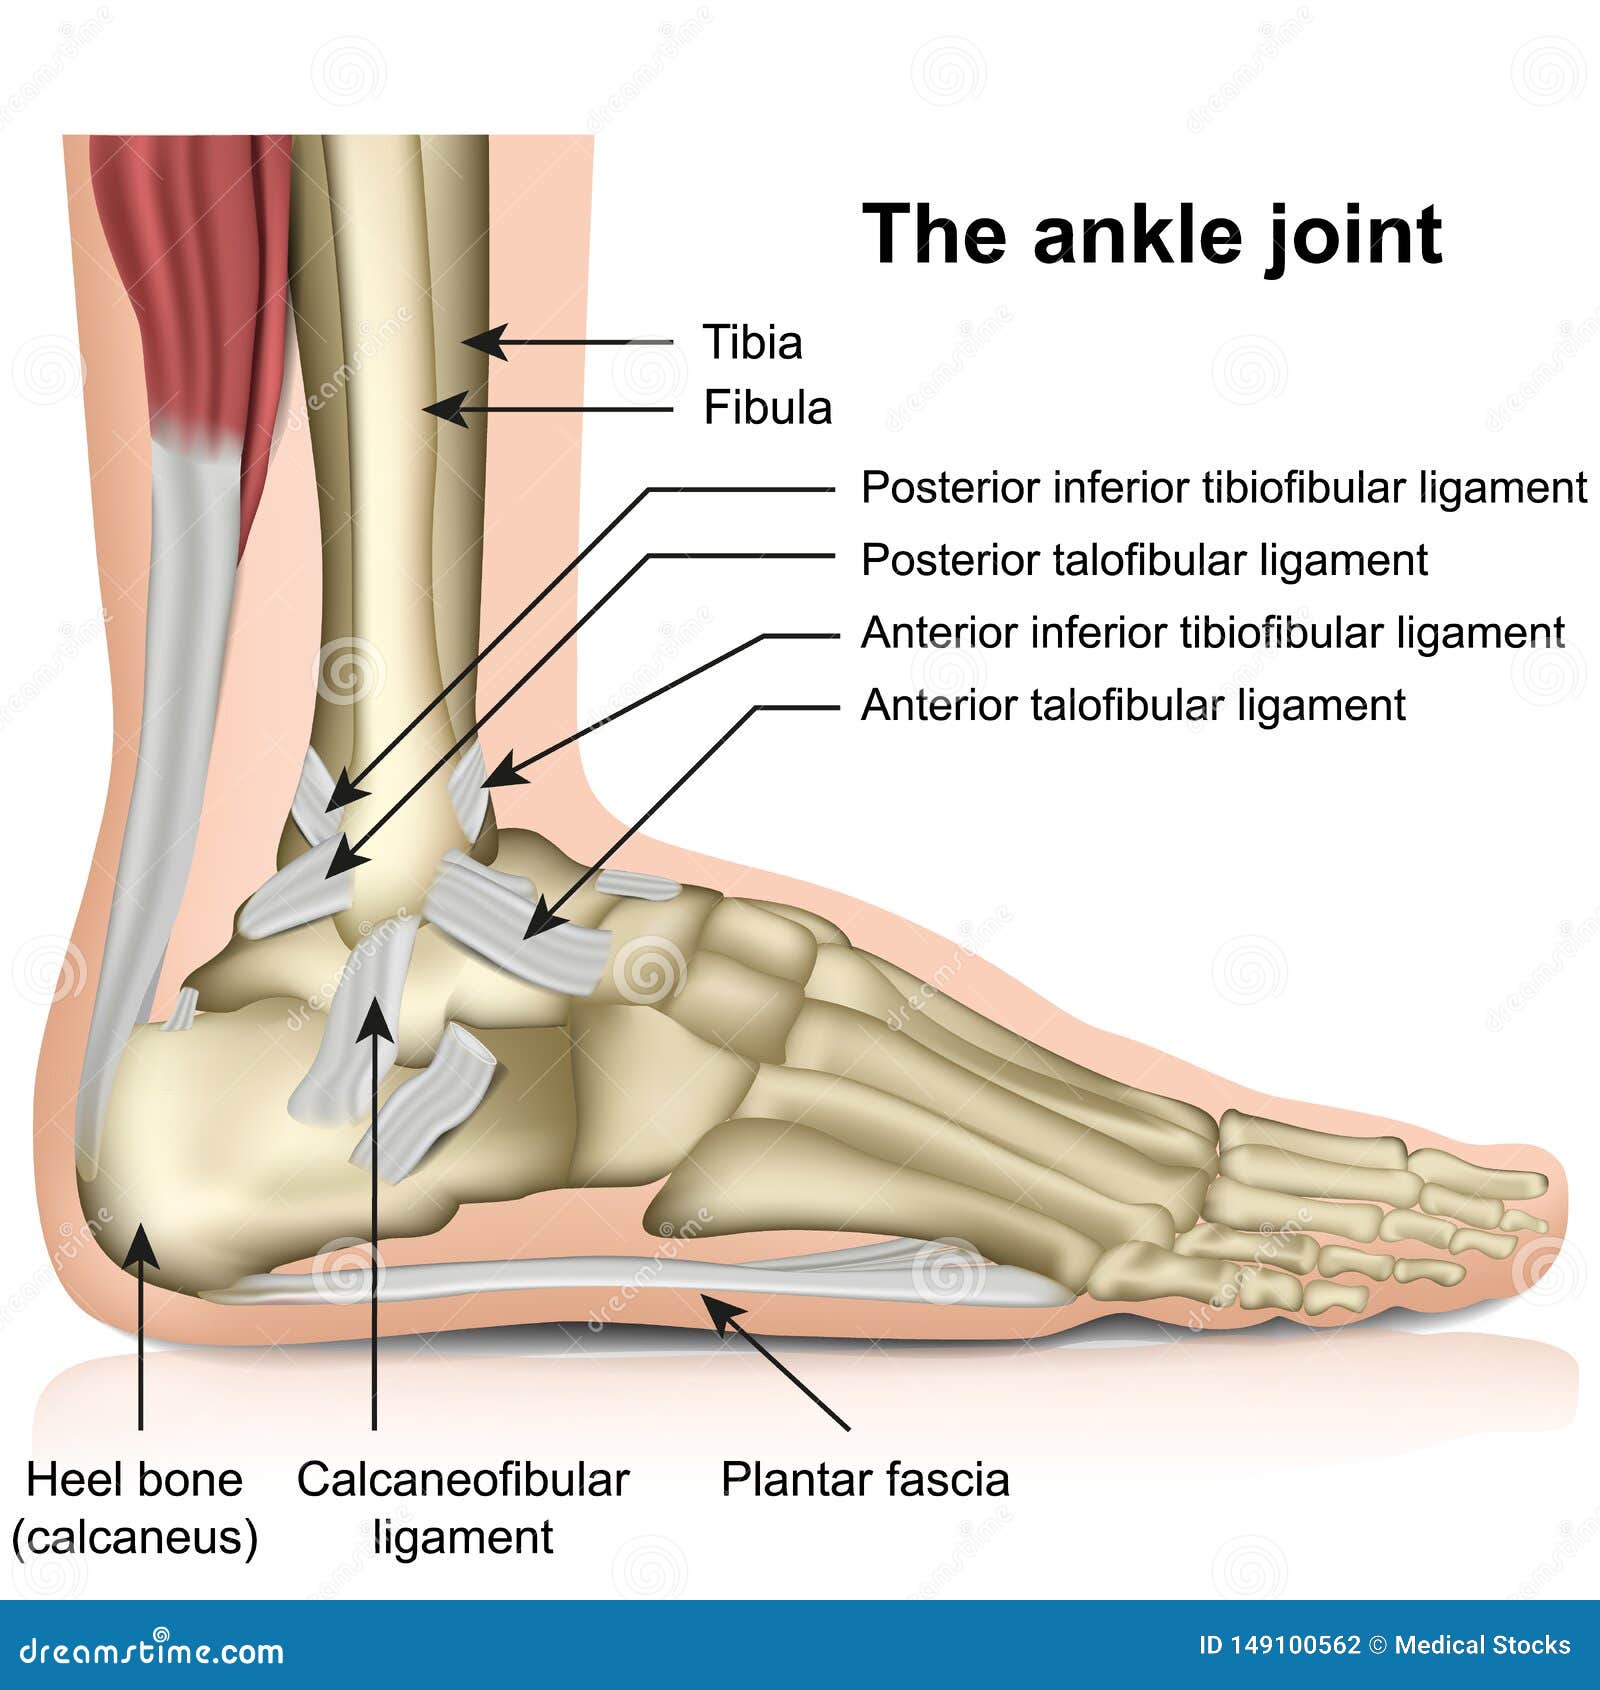
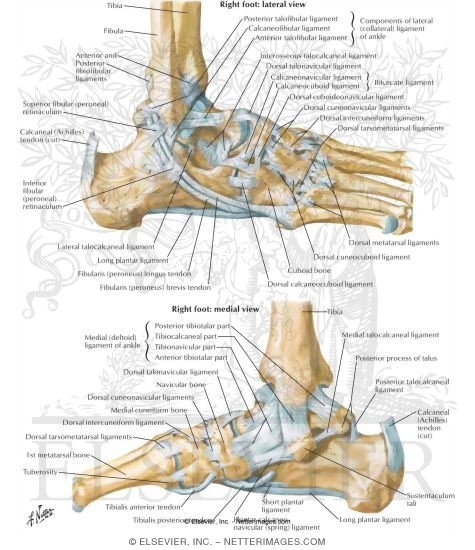
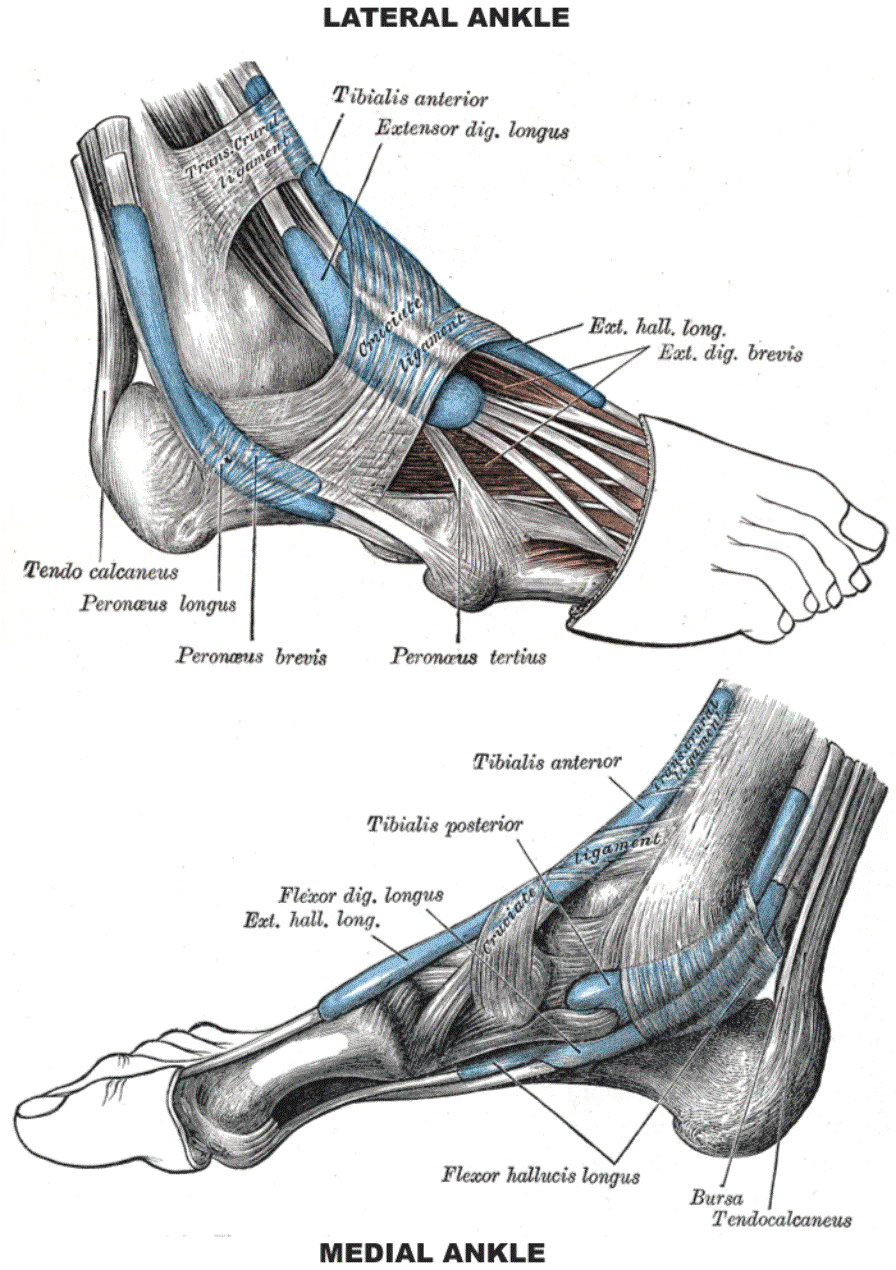
The ankle holds together because of a dense network of tendons and ligaments that most people only notice when something goes wrong. The region is technically compact, but the arrangement is complicated enough that injuries here rarely resolve cleanly without knowing exactly what structure is involved. Tendons connect muscle to bone. In the ankle, the main ones run behind the medial malleolus inside the tarsal tunnel and along the outside of the leg. The posterior tibialis tendon, flexor digitorum longus, and flexor hallucis longus travel through that tunnel. The peroneal tendons run behind the lateral malleolus. The Achilles tendon attaches at the back and carries the bulk of force during walking and jumping. Ligaments connect bone to bone and provide the static stability. On the inside, the deltoid ligament is a thick triangular band with superficial and deep layers. On the outside, the anterior talofibular ligament, calcaneofibular ligament, and posterior talofibular ligament form the lateral collateral complex. These three handle most inversion stress.
I spent years reviewing imaging for sports medicine cases, and the thing that trips people up consistently is assuming every sprained ankle is just a lateral ligament issue. It is not. I had a patient who kept reinjuring the same ankle after what was diagnosed as a standard ATFL sprain. The actual problem was a chronic peroneal tendon subluxation over the lateral malleolus that the initial X-rays completely missed. MRI with dynamic imaging clarified it. The workaround was straightforward surgical repair of the superior peroneal retinaculum, not another round of physical therapy.
How The Structures Work Together Under Load
During normal gait, the ankle goes through dorsiflexion and plantarflexion while the subtalar joint handles inversion and eversion. The ligaments tighten at different points in that range. The ATFL is the weakest of the lateral ligaments and is the first to fail during a typical inversion sprain. That is why most ankle sprains involve this single structure. The deltoid ligament is far stronger. Isolated tears are rare. When you see a deltoid injury, it usually comes with a significant fracture or dislocation. I have seen this pattern repeatedly in trauma cases where the fibula is fractured at the same level as the medial side fails. The force required to tear the deltoid on its own is much higher than what causes a lateral sprain. The Achilles tendon bears roughly four times body weight during running and up to six times during sprinting or jumping. It is also the most commonly injured tendon in the ankle region. The area about two to six centimeters above the insertion point has the poorest blood supply, which is why tears and ruptures cluster there rather than at the bone attachment or farther up in the muscle belly.
Get the Full Details
One detail that is easy to miss is the relationship between the flexor hallucis longus tendon and the posterior ankle. FHL tenosynovitis is common in dancers and football players who spend a lot of time on their toes. The pain is often felt deep in the back of the ankle and can be confused with impingement or even a stress fracture of the navicular. A resisted big toe flexion test usually distinguishes it quickly.
What Goes Wrong And How To Approach It
Acute lateral ankle sprains are graded by the number of ligaments involved. Grade one means stretching without tearing. Grade two is a partial tear, usually of the ATFL with some CFL involvement. Grade three is a complete rupture of all three lateral ligaments. Most cases are grade one or two and resolve within two to four weeks with proper loading during rehab. The common mistake in rehab is resting too long. Complete immobilization for more than ten days actually delays recovery. Early controlled movement within a brace or boot improves collagen alignment and reduces scar tissue formation. I usually recommend weight-bearing as tolerated from day one with a rigid brace for two weeks, then progressive balance work starting around day five. Chronic ankle instability affects about twenty percent of people after a significant sprain. The issue is not always structural laxity. Often it is proprioceptive damage that never properly healed. The mechanoreceptors in the stretched ligaments do not always recover full function. Balance training on unstable surfaces for six to eight weeks is usually necessary even after the ligaments have healed.
Posterior ankle impingement is another area where the anatomy matters. The os trigonum, a small extra bone behind the talus, is present in about ten to fifteen percent of the population. When the foot points downward, the os trigonum can get pinched between the tibia and talus. This causes sharp pain at the back of the ankle and is frequently misdiagnosed as Achilles tendinitis. A lateral X-ray looking at the end-range plantarflexion position will show it clearly. Peroneal tendon tears are often missed on initial evaluation. The pain is on the outside of the ankle and behind the lateral malleolus. Patients describe it as a deep ache that worsens with activity. A cavus foot type and high arches are common predisposing factors. Ultrasound is usually sufficient for diagnosis and allows comparison with the other side. Physical therapy can manage mild cases, but full thickness tears usually require surgical repair or debridement.
When Imaging Actually Helps
X-rays are useful for ruling out fractures in the ankle. The Ottawa Ankle Rules are the standard guideline for deciding when to order them. If there is bone tenderness at the posterior edge of the lateral malleolus, the medial malleolus, the base of the fifth metatarsal, or the navicular, or if the patient cannot bear weight for four steps, an X-ray is indicated. Following these rules avoids unnecessary imaging in about fifty percent of ankle injuries. MRI is the go-to for soft tissue problems. It shows ligament tears, tendon inflammation, and cartilage damage. Ultrasound is faster, cheaper, and equally good for tendon pathology when done by someone who knows what to look for. I use ultrasound routinely for peroneal tendons and the Achilles because I can compare both sides in real time and ask the patient to move through the painful range. CT scans are mainly for complex fractures. They are not useful for ligaments or tendons. The one exception is preoperative planning for intra-articular fractures where the bone fragment displacement needs to be mapped out in three dimensions.
The ankle is not a simple hinge joint. The interaction between its tendons and ligaments creates both stability and mobility, and that complexity is exactly what makes injuries here so frustrating to manage. Understanding which structure is involved changes the entire treatment approach.