Getting Movements Back When Your Spine Wants to Fuse
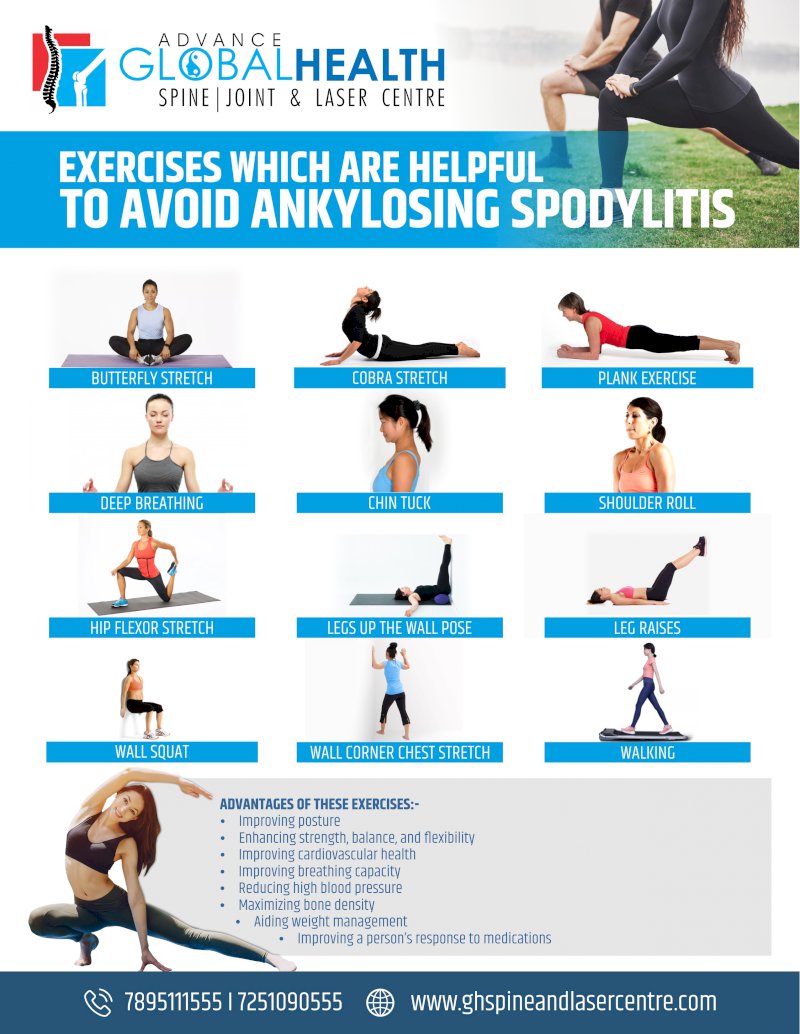
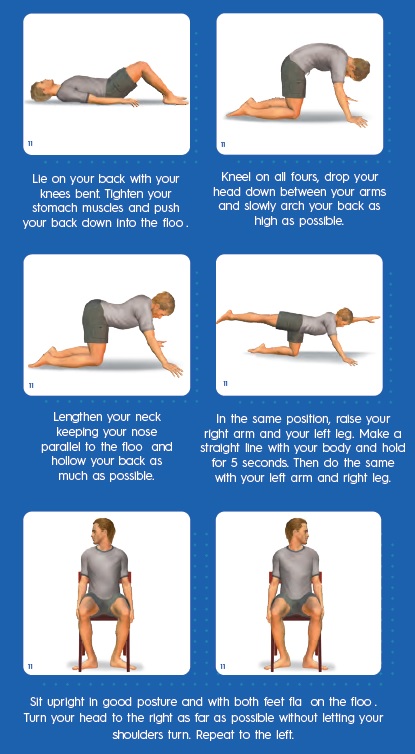
Most people with AS find out pretty quickly that sitting still is the enemy. I spent years watching patients lose range of motion in their hips and thoracic spine simply because they stopped moving through the full arc during flares. The standard advice is "keep moving," but that's not actually helpful when you're trying to figure out what movements are safe during active inflammation versus remission. Here's what I've learned from actually doing this work day after day. The core goal is maintaining spinal mobility and chest expansion while managing pain. The typical protocol involves a combination of daily stretching, postural exercises, and aerobic conditioning. I usually have patients start with ten minutes of gentle range-of-motion work first thing in the morning, before the stiffness sets in. The morning routine matters more than anything else for long-term outcomes. From there, the focus shifts to three areas: spinal extension, hip mobility, and thoracic expansion. Most AS patients develop a flexion-dominant posture over time, so counteracting that requires deliberate extension work. Prone press-ups, cat-cow movements, and seated extension holds are staples. Hip flexor stretches are non-negotiable because tight hip flexors pull the lumbar spine into further flexion. Chest expansion breathing exercises every day — that one gets skipped by everyone until they can't take a deep breath during a walk up stairs.
I had a patient last year who'd been doing the standard stretches for months with no improvement in his thoracic mobility. Turned out he had a significant rib joint involvement that made conventional breathing exercises nearly useless for his level of restriction. I switched him to side-lying rib cage mobilization using a small foam roller placed laterally against the costovertebral joints, held for two minutes per side, and we saw measurable improvement in his chest expansion within three weeks. Something most protocols don't cover.
What Actually Works and What Doesn't
Aerobic exercise is where a lot of patients get stuck. Swimming is the go-to recommendation and it genuinely is one of the better options because the water supports the spine while allowing full movement. But not everyone can swim regularly. Cycling works if you adjust the handlebars high enough to maintain an upright posture — a dropped handlebar position reinforces that forward flexion pattern you're trying to prevent. Walking is fine on flat surfaces, but uneven terrain becomes a problem when balance starts getting affected by hip involvement or spinal stiffness. The biggest mistake I see is patients pushing through sharp pain during flares. Dull ache is expected. Sharp, localized pain near the sacroiliac joint or along the spine means the inflammatory process is active and aggressive stretching can make things worse. During a flare, I scale back to gentle movement within a pain-free range and emphasize positioning strategies — things like sleeping with a thin pillow under the knees to reduce lumbar curve stress, or using a firm mattress rather than a soft one that lets the spine sag into flexion overnight. Posture education is technically part of the therapy but it's where most programs fall apart. Telling someone to "stand straight" doesn't help when their proprioception is shot from years of adapting to a flexed posture. I use tactile cues and visual feedback — having patients stand against a wall and mark where their head, upper back, and buttocks should contact it, then checking throughout the day. It's basic stuff but the consistency of it matters more than anything flashy.
Get the Full Details

Limitations You Need to Know About
Physical therapy for AS has real boundaries. Once vertebral fusion has occurred, no amount of stretching will restore that range of motion. The therapy is about preserving what's there, not reversing structural change. I've seen patients waste months and money chasing programs that promise to "break up" fused segments, which isn't physiologically possible. Surgery is the only option for significant fixed deformity, and even that has limited scope. Another hard limitation is fatigue management. AS causes systemic inflammation that produces genuine, exhausting fatigue. Some days the best physical therapy is recognizing that pushing hard will set recovery back by days. I've had to dial back sessions to half the intended volume because the patient was running on four hours of sleep and their CRP was elevated. The program doesn't get better — the patient's capacity changes. For patients with advanced peripheral joint involvement or significant cardiovascular complications, the exercise prescription needs serious modification. Standard protocols don't account for hip arthroplasty recovery, which is common in this population. I coordinate with orthopedic surgeons on post-surgical timelines and adjust accordingly. There's no point in prescribing hip extension stretches when the patient is in protective spasm from a recent replacement.
Medication adherence and physical therapy don't replace each other. NSAIDs and biologic DMARDs control the inflammatory drive. Exercise maintains function. Having a patient do perfect exercises while their disease is uncontrolled medically is a waste of everyone's time. The best outcomes come from both happening simultaneously, not one compensating for the other. The evidence for specific exercise protocols in AS is moderate at best. Cochrane reviews consistently show that exercise improves function and reduces pain compared to no exercise, but the difference between various exercise modalities — stretching versus strengthening versus aerobic — tends to be small. What seems to matter most is adherence over years, not the particular exercise selected on any given week. That's a harder message to sell than a fancy new protocol, but it's what the data actually supports.