What we actually do when the antibody screen comes back positive
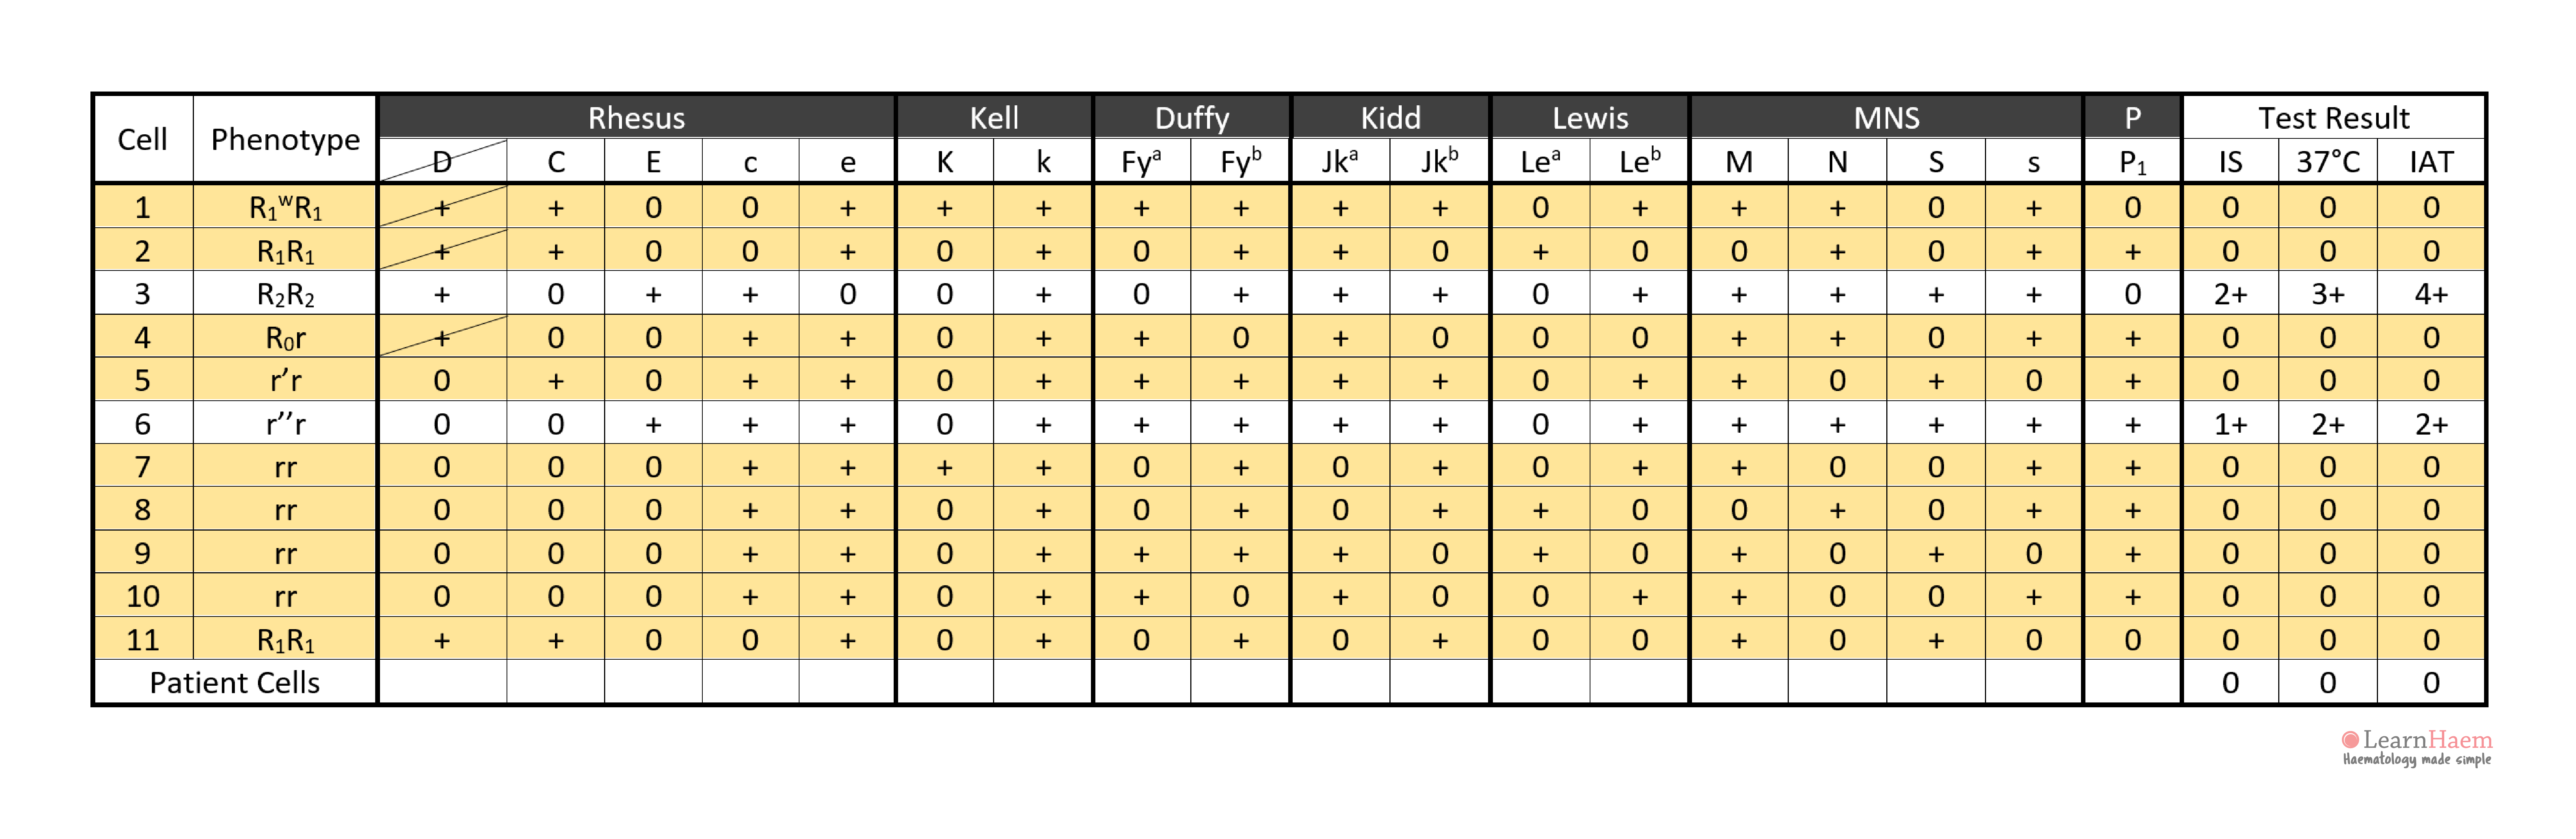
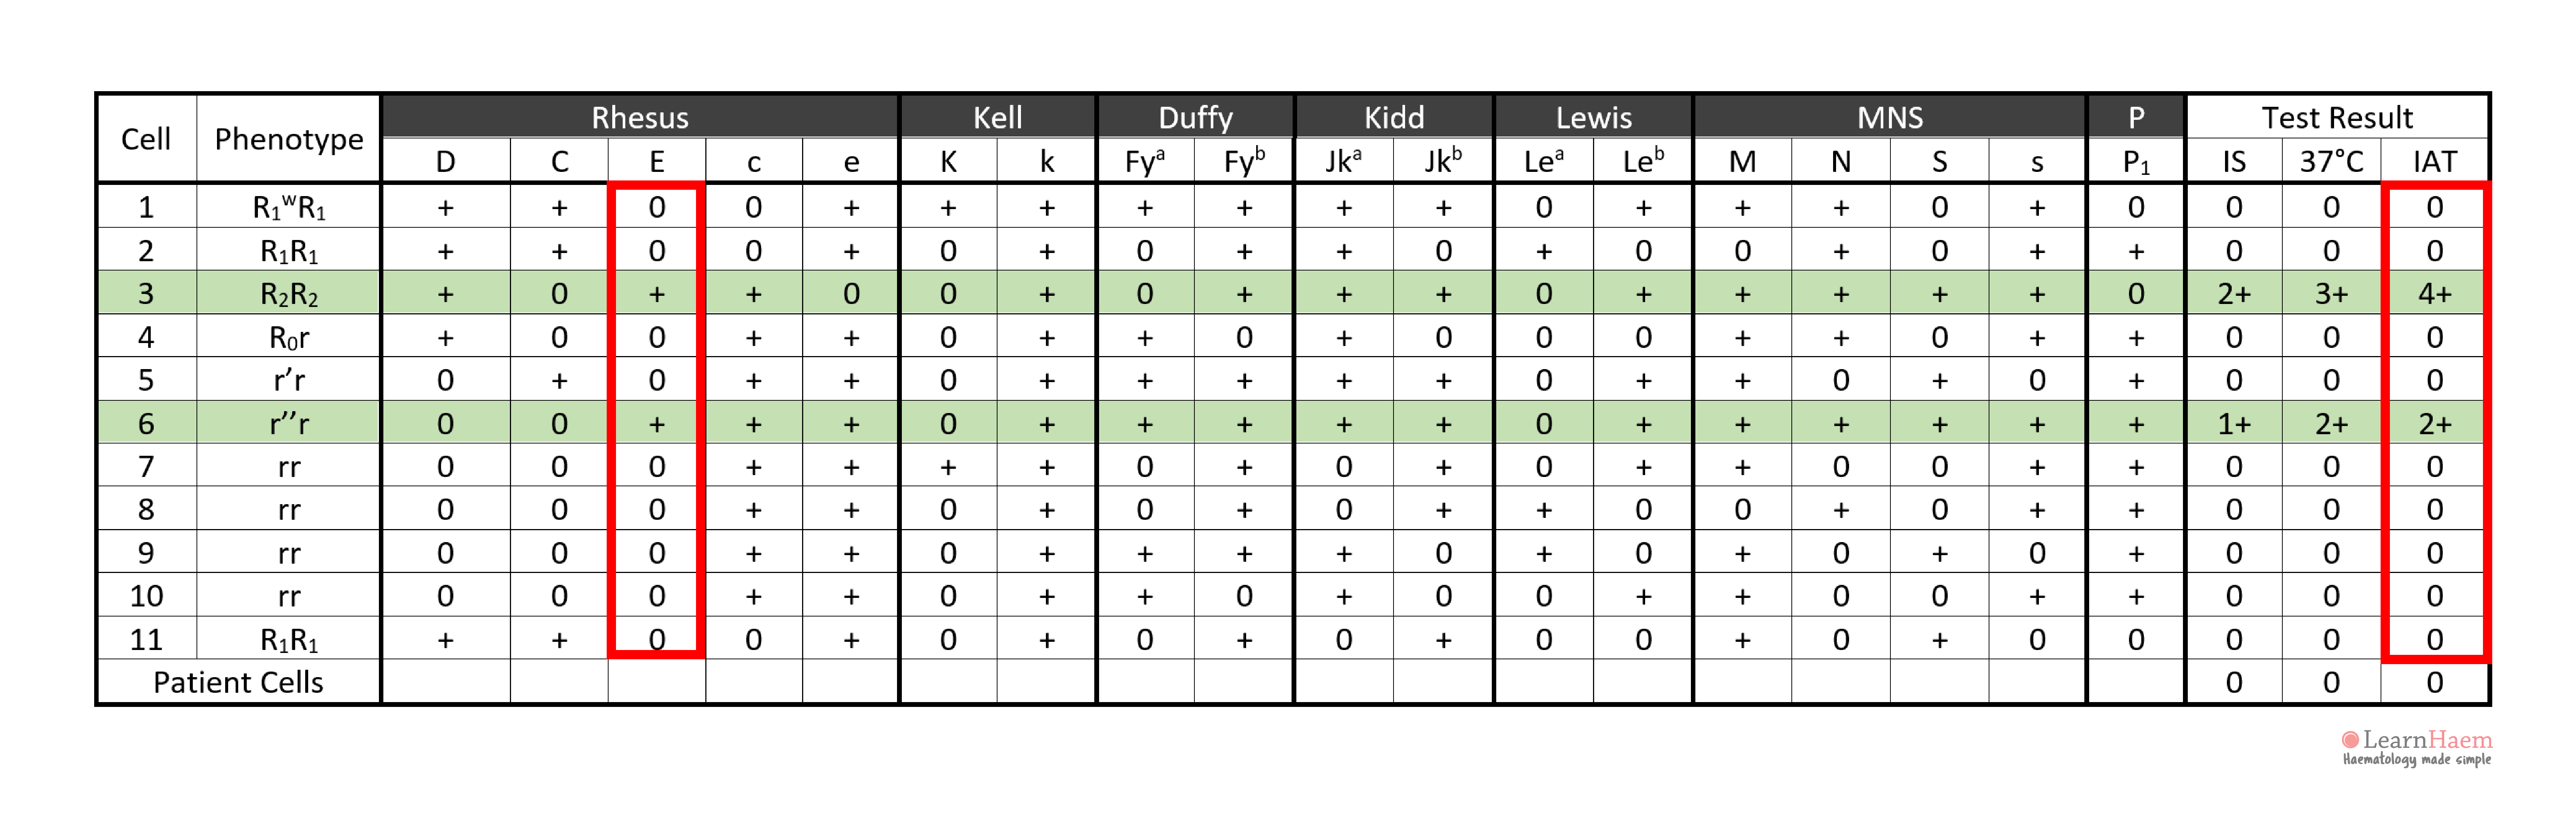
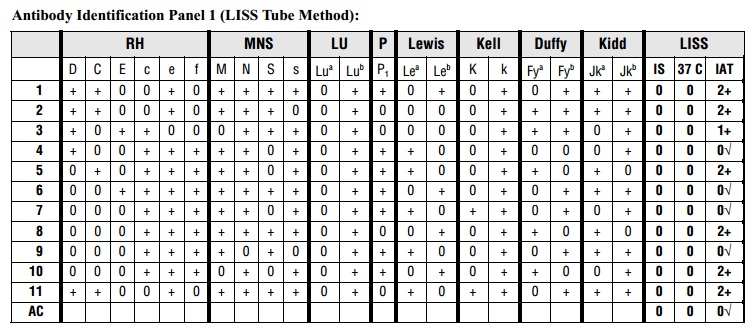
I have been running antibody identification panels in the immunohematology lab for over a decade now, and the process never gets easier even though it stops being stressful once you internalize the logic. A positive indirect antiglobulin test or antibody screen triggers a sequence that most newer technologists approach as a checklist, but it really works better as a deductive puzzle where every reagent cell you look at eliminates one more possibility. The panel itself is a set of four to six reagent red cells with known antigen profiles. You run them against the patient's serum using either LISS, PEG, or an enzyme-treated format depending on your lab's standard operating procedure. The output is a pattern of reactivities — which cells are positive and which are negative — and your job is to find the antibody or combination of antibodies that explains that pattern. It sounds simple on paper until you sit down at 4 PM with a panel where three cells show 2+ reactivity, two show 1+, and the autocontrol is also weakly positive. Here is what actually matters in practice. You start by ruling out the easy stuff: a positive autocontrol means you need to consider a direct antiglobulin test issue, cold autoantibodies, or drug interference before you chase alloantibodies. Then you go through the antigen table and cross off any antibody whose corresponding antigen is missing from the positive cells. If an antibody is reacting, its antigen must be present on every positive reagent cell and absent from every negative one. That elimination step is where most beginners waste time because they forget to check the antigen frequency in the population — an anti-Kidd antibody is common enough that you should not dismiss it just because the pattern looks messy, while an anti-Lutheran might genuinely be rare in your patient population.
I had a case last year where the panel suggested a single antibody but the dosage pattern was inconsistent. Three cells were 3+, two were 2+, and one positive cell was only 1+. Every algorithm in our software pointed to anti-Kidd, but the dosed cell did not match the expected strength. I repeated the panel, then ran an enzyme phase separately and noticed that the weak 1+ reaction was actually a combination — a weak anti-Kidd masked a low-titer anti-M that was only visible because the enzyme treatment enhanced M reactivity without destroying Kidd antigens. The computer gave up at that point. Manual resolution took me another twenty minutes and confirmed both antibodies. The takeaway here is that your software is only as good as its assumptions, and it will not rescue you when multiple low-frequency antibodies overlap. There are two things that most training programs do not emphasize enough. First, the strength of reactivity matters more than you think. A 4+ reaction with one cell and a 1+ reaction on another cell with the same antigen is rarely the same antibody. That discrepancy usually means either dosage is in play or you are dealing with two separate specificities. Second, elution is often presented as a last resort in textbooks, but in my experience it is worth attempting earlier than people expect. If you have a warm autoantibody coating the patient's own cells, the serum may still contain an underlying alloantibody that the autoantibody is masking. An eluate run against the panel can reveal that hidden specificity, and it typically takes forty-five minutes from start to finish if you are efficient with the protocol. The limitations of this whole approach are worth stating plainly. Antibody identification panels fail when the patient has developed an antibody against a low-prevalence antigen that is simply not present on any of the reagent cells. There is nothing in a standard twelve-cell panel that covers that scenario, and your only option is referral to a reference laboratory. Similarly, mixed-field agglutination from a recent transfusion can make the panel unreadable because you are looking at a mixture of donor and recipient cells, and the reactivity patterns become internally contradictory. In those cases you wait for the patient to clear the transfused cells or you proceed with antigen-negative blood based on the serological history alone.
Another persistent problem is the reagent lot variability. Different manufacturers use different cell sources, and the same antigen can express at different strengths on cells from different donors. A panel that gives you clean unambiguous results with one manufacturer's cells might give you ambiguous weak positives with another. This is why we validate each new lot before releasing it into routine use, and it is one of those quality control steps that looks bureaucratic until you realize you spent three hours troubleshooting a lot-related artifact instead of doing actual patient work. For documentation purposes, which is the part that makes administrators happy and technologists roll their eyes, you need to record the antibody ID panel lot numbers, the reagent source, the phase used, the autocontrol result, the eluate if performed, and the final identified specificity or ruled-out list. This is not optional in an accredited laboratory. A missing lot number during a proficiency testing failure review will not be forgiven by the inspector. If you are studying for board certification or just trying to get competent, the best practice I can recommend is to work through at least fifty unsupervised panel interpretations before you touch a patient sample independently. Most of your errors will come from the same five patterns: misreading dosage, missing a combination of two antibodies, ignoring a positive autocontrol, skipping the enzyme phase when you should have run it, and trusting the computer's suggestion without verifying the cell-by-cell logic. Once you have seen those mistakes repeatedly in practice they stop appearing as surprises and start appearing as flags that make you slow down and double-check your work.
Get the Full Details