Writing Meaningful Treatment Targets
I spent years watching therapists write goals that looked great on paper but absolutely went nowhere during sessions. The gap between what gets documented and what actually moves the needle is wider than most people realize. Let me walk through how this actually works in practice. Start with the assessment data, not a template. I see too many clinics grab a standardized form and start filling in blanks without looking at what the person's actual communication breakdown looks like in their daily life. A goal like "Patient will name 80% of core vocabulary" tells you nothing about whether the patient can ask for water at dinner or tell a nurse they need pain medication. Functional observation matters more than standardized scores here. The framework I use pulls from the ICF model because it forces you to address impairment, activity, and participation separately. You might have a patient who scores poorly on the WAB-R but compensates remarkably well in casual conversation because they rely on gesture and context. Writing goals only around the standardized score means you're treating the wrong problem. Document the real limitation, not the test result.
Here's where most people mess up: they write the goal around the deficit instead of the function. Instead of "improve naming accuracy," write "patient will communicate drink preference independently using word retrieval strategies in restaurant settings." The first one gives you a number. The second one gives you a life improvement. Both matter, but the second one is what keeps people coming back and what families actually notice. I had a patient once who was essentially nonfluent after a left MCA stroke. Everyone was hammering her on melodic intonation therapy because the literature supports it for agrammatism. She wasn't making progress. The breakthrough came when I stopped trying to fix her speech and started working on written sentence completion. She could produce full sentences by reading and filling in blanks even though she couldn't speak them. We built a comm system around that strength — she'd write key words and we scaffolded from there. Six weeks later she was using single words with more confidence because the pressure to produce fluent speech was gone. That was the counterintuitive part: her strongest modality wasn't oral at all.
Structuring Measurable Objectives
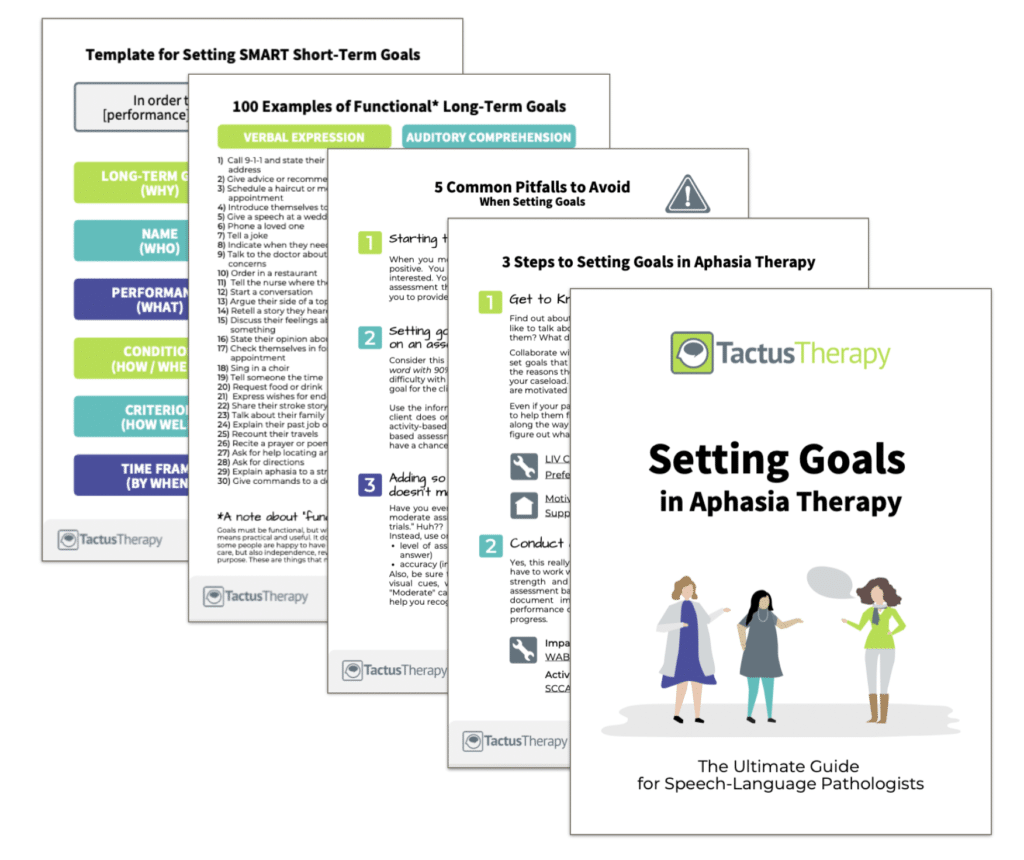
Every goal needs a measurable component, but the metric has to match the target. If the goal is about functional communication in a noisy environment, testing it in a quiet clinic room is useless. I set up role-play scenarios that approximate the real conditions. A coffee shop test with background noise and a time limit gets you closer to reality than a picture-card drill in a sound-treated booth. The SMART framework still applies, but "achievable" gets misused constantly. A patient with severe anomic aphasia who scores 2/40 on the Boston Naming Test cannot realistically be expected to name 20 objects spontaneously within six weeks. That doesn't make the goal invalid — it makes the timeline and the scaffolding the variables you adjust. Use errorless learning techniques, then systematically fade the prompts. Document the prompt hierarchy at baseline so you can measure fade progress objectively. Progress monitoring should happen at every session, not just at 4- or 6-week intervals. I use a simple trial-by-trial tracking sheet that logs accuracy percentage alongside the level of cue required. Over time you're looking for two things: the accuracy number going up and the cue level coming down. If accuracy improves but cue dependency stays flat, you haven't actually built independence. That's a common blind spot.
Get the Full Details

Common Pitfalls in Goal Formulation
One thing nobody talks about enough is the ceiling effect with mild aphasia cases. These patients often look fine on casual conversation and score close to average on standardized measures, so the goals become vague and unmeasurable. "Improve conversational fluency" is not a treatment target. It's a wish. For mild cases, I drill into specific breakdowns — circumlocution efficiency, word-finding time under pressure, conversation repair strategies. Track the number of successful self-repairs per 10-minute interaction. That's measurable. That's treatable. Another pitfall is stacking too many goals at once. A patient dealing with both anomia and auditory comprehension deficits shouldn't be working on both simultaneously unless the schedule allows it. Cognitive load during therapy is real. I typically run one primary goal with a secondary maintenance goal at reduced intensity. The primary goal gets the focused drill work. The secondary goal gets woven into functional activities without explicit instruction time. Family involvement should be baked into the goal structure from session one, not added as an afterthought. The caregiver needs to know exactly what strategy the patient is practicing and how to prompt without enabling. I write a one-page strategy summary for each goal that goes home with the family. It includes what to expect, what counts as progress, and what to avoid. Most therapy documentation never makes it out of the clinic folder.
The hardest part is knowing when a goal isn't working and pivoting. I set a three-session rule: if a patient isn't showing any movement on a trial-by-trial basis after three consecutive sessions with the same approach, I change something. Could be the modality, the cueing strategy, the context, or the baseline difficulty level. Staying faithful to a failing method isn't dedication. It's waste. Documentation for insurance still demands the standardized language, so you'll write the measurable impairment-level goal to satisfy the payer and the functional participation-level goal to satisfy the treatment plan. Both belong in the chart. Just don't confuse the insurance goal with the therapy goal. They serve different purposes and one of them doesn't actually change anyone's life.