How to Actually Use Arterial Blood Gas Practice Questions Without Losing Your Mind
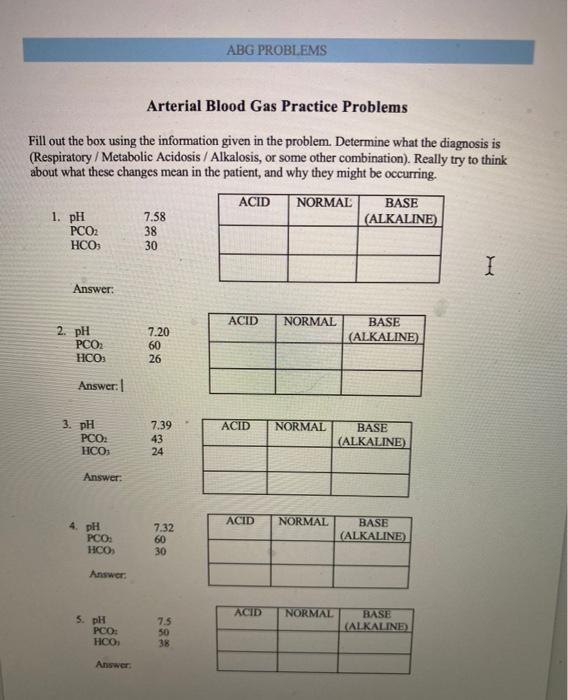
Most people approach ABG interpretation the wrong way. They memorize a six-step algorithm and then panic when the numbers don't fit neatly into any category. I have watched residents freeze in front of a monitor showing a pH of 7.31 with a pCO2 of 52 and a bicarb of 28, completely unable to tell if they were looking at a compensated respiratory acidosis or something mixed. The truth is that practice questions work only if you force yourself to actually work through them without peeking at the answer first. Reading someone else's interpretation is not studying. Here is how I actually use them. Pick a question, write down your answer on paper before looking at any explanation, and then grade yourself harshly. If you got the pH direction right but missed the compensation status, that is still wrong. Partial credit does not exist on the wards when a patient's trend is worsening and you are trying to explain it to an attending. The core framework most people learn looks like this. First check the pH. Below 7.35 is acidemia, above 7.45 is alkalemia. Then look at the pCO2 and the bicarbonate to figure out which one is driving the problem. The pCO2 moves in the opposite direction of the pH in primary respiratory disorders, while bicarbonate moves in the same direction. After that you assess compensation using either the acute or chronic formulas depending on the clinical context. Finally you check the anion gap if there is a metabolic acidosis component.
That framework sounds clean on paper. In practice it breaks down fast. Let me give you a specific example from when I was working nights in the ICU. A patient came in with sepsis, and the ABG showed a pH of 7.28, pCO2 of 34, bicarb of 14, and a lactate of 6.8. On the surface that looked like a straightforward metabolic acidosis with appropriate respiratory compensation. But when I recalculated the expected pCO2 using Winters formula, which is 1.5 times the bicarbonate plus 8, I got an expected pCO2 of about 29. The actual pCO2 was 34. That meant there was a concurrent respiratory acidosis on top of the high anion gap metabolic acidosis, not just simple compensation. The patient was tiring out. Missing that secondary respiratory component by blindly accepting the pCO2 as "appropriate" would have been a serious error. This is exactly the kind of edge case that good practice questions should force you to confront, and the kind where the six-step algorithm alone will mislead you if you are not actually calculating the expected values. One thing that rarely gets emphasized in review sessions is the role of the delta-delta, also called the delta gap. When you have a high anion gap metabolic acidosis, the change in anion gap should roughly equal the change in bicarbonate. If the bicarbonate has not dropped as much as the anion gap rose, there is likely a concurrent metabolic alkalosis. If the bicarb dropped more than the anion gap increased, there is a hidden normal anion gap metabolic acidosis alongside the high one. I see this constantly in real patients and almost never see it tested properly in basic practice sets. A diabetic in DKA who is also vomiting will throw off the expected relationship and present a much trickier picture than any single-mechanism question would suggest. Another counter-intuitive point that beginners consistently miss is that a normal pCO2 in the setting of significant metabolic acidosis is actually a bad sign. Everyone thinks normal means fine, but in severe metabolic acidosis you should expect the patient to hyperventilate and drive the pCO2 down. A pCO2 that sits at 40 in the presence of a bicarb of 12 tells you the respiratory compensation is inadequate, which usually means the patient is fatiguing or has a concurrent lung problem. That single detail can change whether you intubate or buy time with noninvasive support.
When I build my own practice question sets, I pull from multiple sources and then add clinical context that most commercial reviews strip out. An ABG number without the clinical story is almost useless. The same pH and pCO2 values mean completely different things in a COPD exacerbation versus a salicylate overdose versus a post-op patient on a ventilator. I always write the vignette first, then present the lab values, and only then ask for the interpretation. This forces you to integrate data rather than just crunch numbers in a vacuum. I recommend working through at least twenty varied practice questions before you feel confident, but quality matters more than quantity. Twenty poorly written questions that all follow the same pattern will give you false confidence. You need questions that include mixed disorders, chronic versus acute differentiation, and scenarios where the compensation formulas do not apply cleanly. Pulmonary embolism with a normal pCO2 is one of those classic traps. The old teaching says respiratory alkalosis with low pCO2 is the hallmark of PE, but up to a quarter of patients with proven PE have a completely normal ABG. Relying on the ABG to rule anything in or out in that context is dangerous. For free practice questions, the UWorld ABG section and the Amboss question bank both have solid material, though you need subscriptions for full access. Open resources like Geeky Medics and Medscape have decent standalone ABG tutorials with sample questions. The Johns Hopkins ABG interpreter workbook is older but still one of the clearest practical guides available. There are also various PDFs floating around on university critical care websites that contain question sets with detailed worked solutions, though you have to vet them for accuracy since not all are authored by clinicians.
Get the Full Details

Here is a short set of practice questions you can work through right now. Try each one without looking at the answers below. Question one: pH 7.33, pCO2 60, bicarb 31. What is the primary disorder and is compensation appropriate? Question two: pH 7.50, pCO2 30, bicarb 24. Is this a simple disorder or mixed?
Question three: pH 7.22, pCO2 28, bicarb 10, sodium 140, chloride 108. Calculate the anion gap and determine if there is a mixed disorder. Question four: A known COPD patient presents with pH 7.36, pCO2 65, bicarb 36. Is this acute or chronic? Question five: pH 7.48, pCO2 50, bicarb 34. Identify all components of this disorder.
Answers: One is a partially compensated respiratory acidosis. The expected bicarb for acute elevation is roughly 1 mEq per 10 mmHg above 40, giving about 26, and for chronic about 3.5 per 10, giving roughly 31, so this is consistent with chronic respiratory acidosis with some metabolic compensation, likely an acute on chronic picture given the pH is not fully normalized. Two is a mixed respiratory alkalosis and metabolic alkalosis because the bicarb should be lower if this were a simple respiratory alkalosis. Three gives an anion gap of 22, indicating a high anion gap metabolic acidosis, and the delta-delta shows an additional non-anion gap metabolic acidosis as well. Four is chronic compensated respiratory acidosis given the elevated bicarb reflecting renal retention over days. Five is a mixed disorder with both respiratory and metabolic alkalosis present simultaneously. The main limitation of practice questions as a learning tool is that they tend to present idealized or single-mechanism cases. Real patients rarely cooperate with textbook patterns. You will encounter situations where the electrolyte data conflicts with the ABG, where the clinical timeline contradicts the expected compensation, or where the lab value itself is unreliable due to sample errors. An arterial sample drawn from a radial artery with incomplete collateral circulation can show artificially elevated pCO2 and depressed pH simply because of local stasis. I once had a patient whose ABG looked like severe respiratory failure but the venous sample told a different story, and the arterial line was later found to be dampened. Always correlate with clinical findings and consider repeating the sample if the numbers feel wrong. If you want to get better at this faster, stop doing questions passively. Write out the full interpretation for each one including the compensation calculation and the delta gap when relevant. Verbalizing or writing forces you to confront every step, and that is where the gaps in your understanding show up. Do five questions this way and you will learn more than twenty questions where you glance at the answer after two minutes of confusion.

There is also a practical timing issue worth noting. Fresh arterial samples should be analyzed within fifteen to twenty minutes if kept at room temperature, otherwise the cells continue consuming oxygen and producing carbon dioxide, which shifts the values downward. If you are practicing with drawn samples rather than simulated cases, that degradation can make your interpretation chase a moving target. This is why most training programs use simulators or pre-captured digital cases rather than actual blood draws for routine practice. The bottom line is that ABG interpretation is a skill built through repeated deliberate practice with feedback, not through passive reading or rote memorization of algorithms. The practice questions are only useful if they challenge you with mixed disorders and realistic clinical scenarios, and if you force yourself to commit to an answer before seeing the solution. The ones that make you uncomfortable are the ones that will actually stick with you when the real patient walks in with a confusing set of numbers and you need to think clearly under pressure.