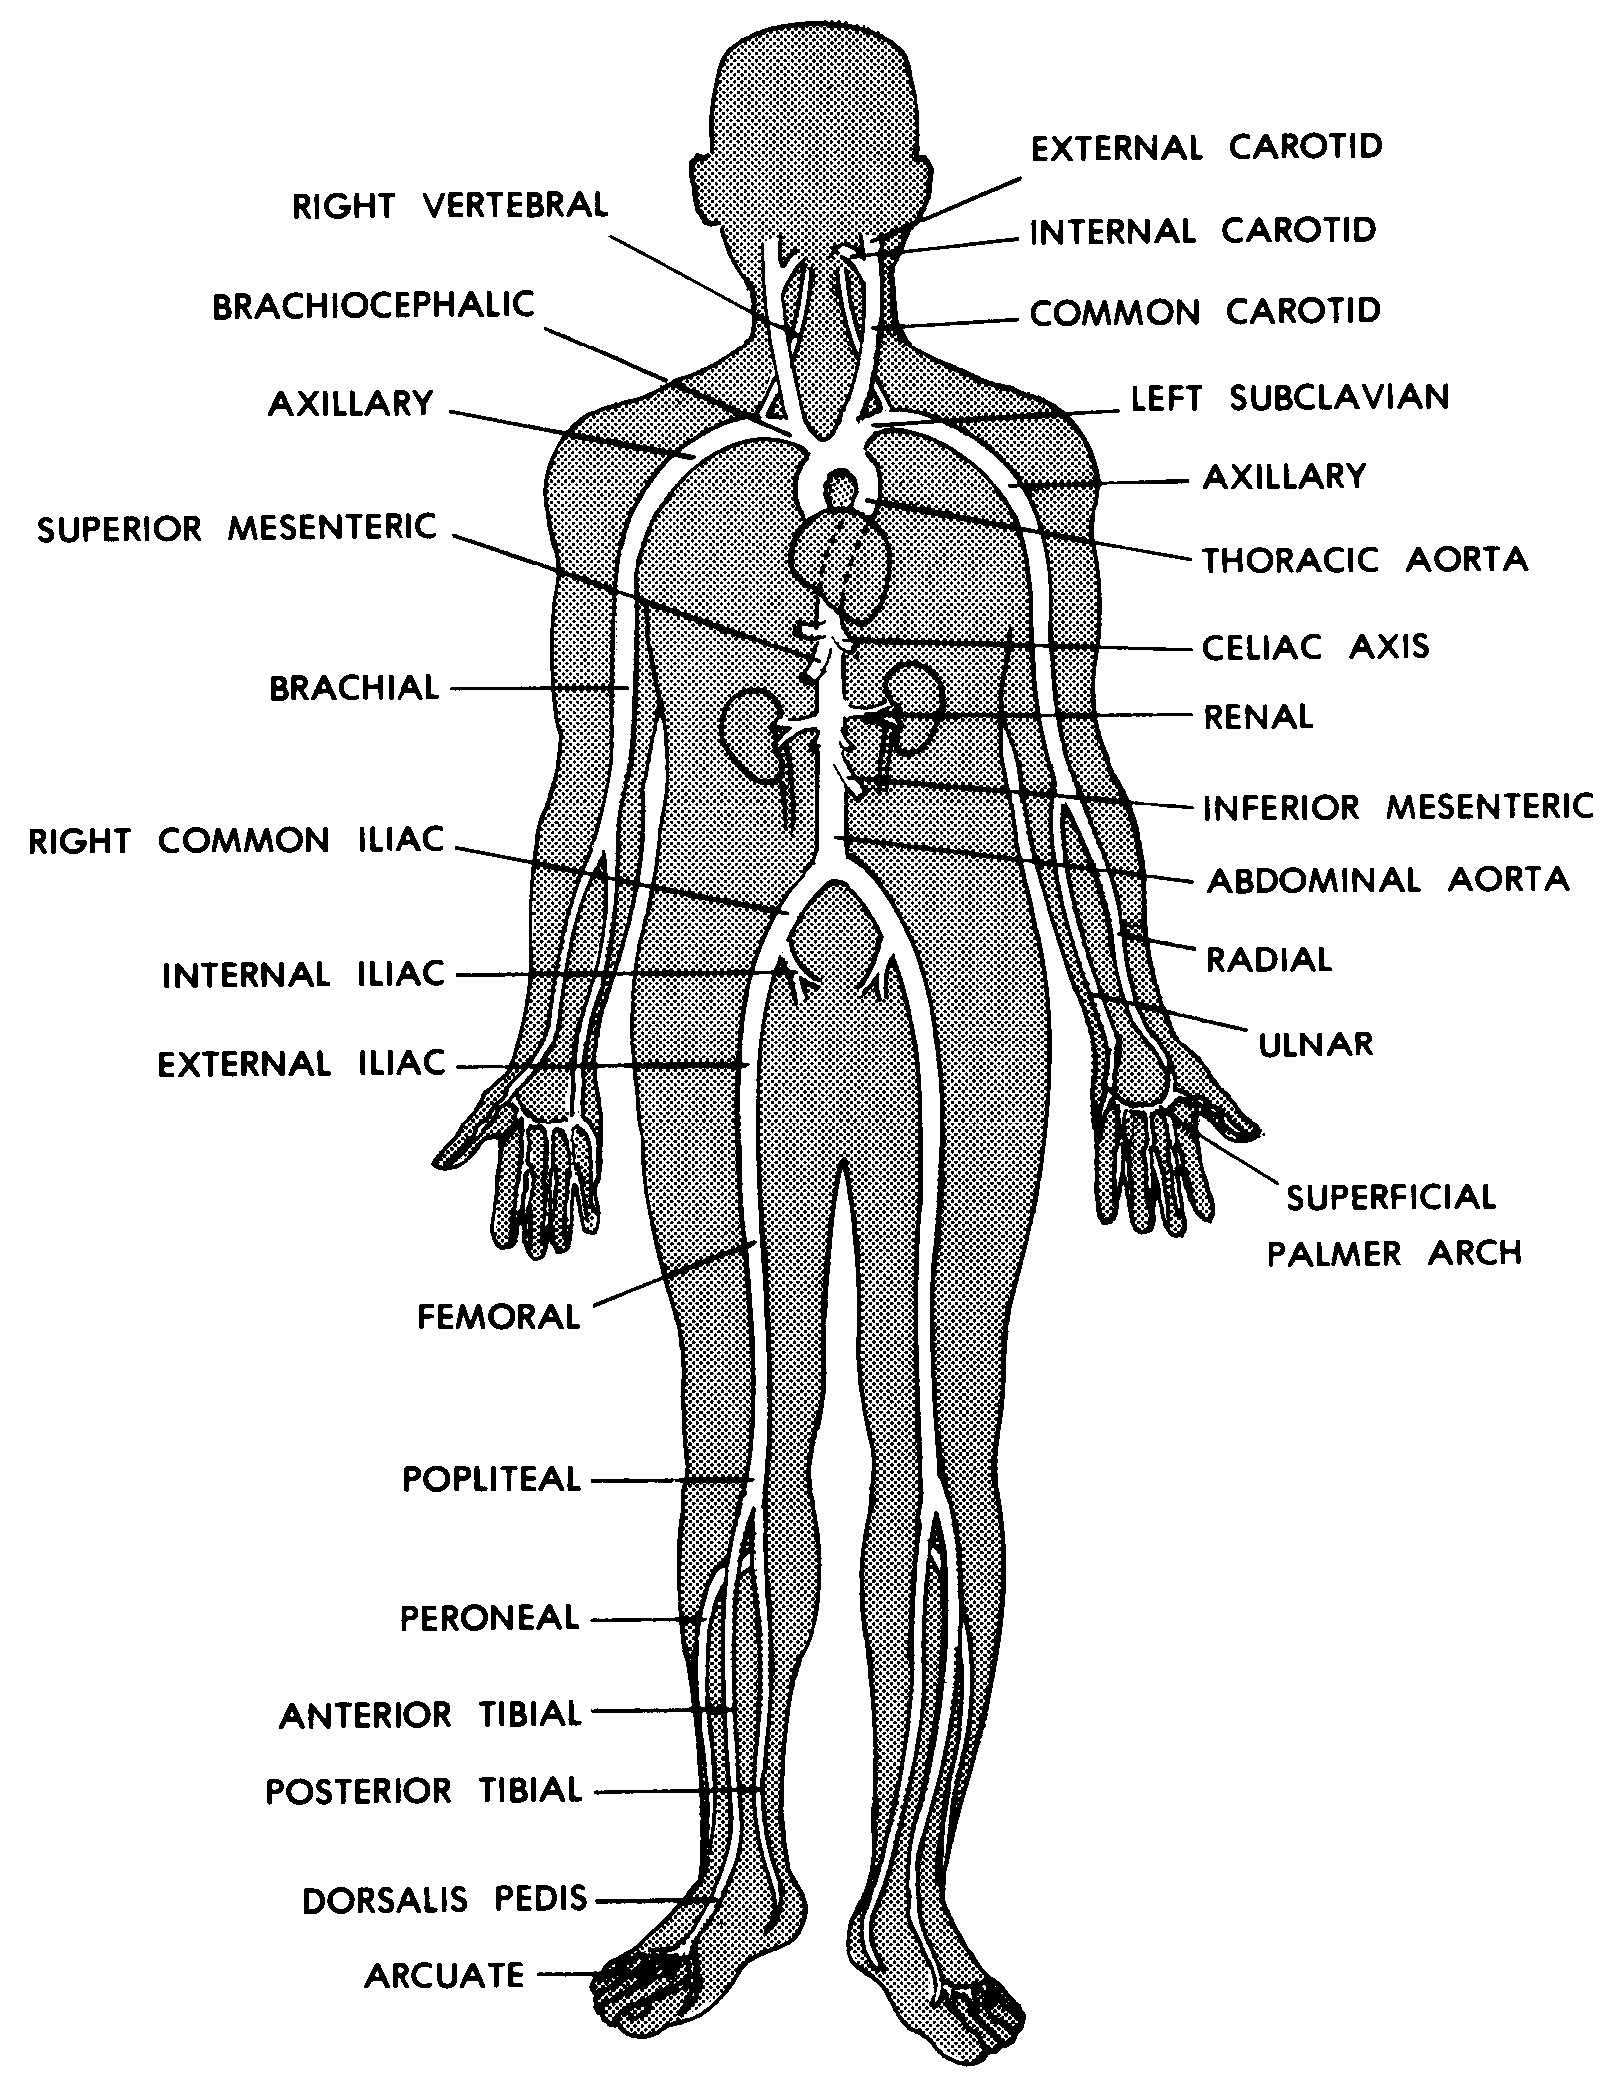
The Arterial Network: What Actually Moves Blood Where It Needs To Go
When you look at a diagram of the circulatory system, arteries are usually drawn in bright red, thick-walled and prominent. The reality is messier. Arteries Of The Body serve as the conductive framework for oxygenated blood leaving the heart, but their architecture varies wildly depending on where they sit and what pressure they must handle. Understanding this system is less about memorizing names and more about grasping the functional logic behind vessel design. Arteries branch from the aorta in a pattern that prioritizes flow efficiency over anything else. The largest arteries are elastic arteries, meaning their walls contain a high proportion of elastin fibers that allow them to stretch during systole and recoil during diastole. This recoil is what maintains continuous blood flow between heartbeats. Without it, you would get pulsatile flow in the capillaries, which would be far less efficient for nutrient exchange. The smaller muscular arteries follow, distributing blood to specific organ regions. Then come the arterioles, which are the primary resistance vessels and the main point of blood pressure regulation through vasoconstriction and vasodilation. I spent years working with cadaver specimens and clinical imaging, and one thing became immediately clear: textbook diagrams vastly overrepresent the uniformity of arterial branching. In practice, there is enormous anatomical variation between individuals. During a surgical dissection last year, I encountered a patient whose right common hepatic artery arose from the superior mesenteric artery instead of the celiac trunk. This variant occurs in roughly twelve percent of the population. If you operate based solely on the standard diagram, you will miss the vessel entirely or accidentally ligate the wrong one.
How To Approach Studying And Identifying Arterial Anatomy
The most effective way to learn arterial anatomy is to work from proximal to distal, following the aorta from its origin at the left ventricle outward. Start with the ascending aorta and aortic arch, then trace each major branch systematically. The key branches off the aortic arch are the brachiocephalic trunk, the left common carotid artery, and the left subclavian artery. From there, follow each region independently rather than trying to memorize everything at once. Coronal cross-sections and CT angiography images are more useful than traditional anterior view illustrations because they show the actual spatial relationships between arteries and surrounding structures. A standard anterior diagram of the upper limb will show you the subclavian becoming the axillary, then the brachial, then the radial and ulnar. But that tells you nothing about how the brachial artery sits directly against the humerus, or why the radial pulse is palpable at the wrist but the ulnar is much harder to locate clinically. Practical tip: Use the rule of thirds when palpating pulses. The temporal artery is palpable just anterior to the tragus of the ear. The carotid pulse is found in the triangle between the sternocleidomastoid and trachea, roughly at the level of the thyroid cartilage. The brachial pulse is medial to the biceps tendon in the antecubital fossa. The radial pulse is lateral on the ventral wrist, just distal to the styloid process. The femoral pulse is midway between the anterior superior iliac spine and the pubic symphysis, just inferior to the inguinal ligament. The dorsalis pedis pulse is on the dorsal foot, lateral to the extensor hallucis longus tendon. The posterior tibial pulse is behind and slightly below the medial malleolus.
Common Pitfalls That Beginners Keep Making
One persistent error is assuming that all arteries follow a predictable path. The arterial system has multiple anastomotic networks specifically designed to bypass blocked or compressed vessels. The circle of Willis at the base of the brain is the most famous example, but collateral circulation exists throughout the body. The scapular anastomosis connects the subclavian system to the axillary system through branches of the suprascapular, circumflex scapular, and thoracodorsal arteries. This means an occlusion of the axillary artery proximal to these branches does not necessarily cause limb ischemia if the collaterals are well developed. Another frequent mistake is confusing arterial supply territories. The middle colic artery supplies the transverse colon, while the left colic artery from the inferior mesenteric supplies the descending colon. The junction between these two territories at the splenic flexure is a watershed zone with relatively poor collateral flow, making it vulnerable to ischemia during low-flow states like severe hypotension or mesenteric vascular disease. I once reviewed a case where a medical student was called out for identifying the gastroduodenal artery as a branch of the splenic artery. The gastroduodenal artery actually arises from the common hepatic artery, which itself comes from the celiac trunk. The splenic artery takes a tortuous course along the superior border of the pancreas and gives off the short gastric arteries and the left gastroepiploic artery. These distinctions matter when you are interpreting cross-sectional imaging or planning surgical approaches to the upper abdomen.
Get the Full Details

The Microcirculation: Where Arteries Actually End Up Matter
Arterioles are the terminal branches before the capillary beds, and they are where the real regulation happens. Their walls contain smooth muscle arranged in a spiral pattern, and contraction of this muscle increases vascular resistance and raises blood pressure. The body regulates this through sympathetic nervous system output, local metabolic factors, and circulating hormones. When you stand up quickly and feel lightheaded, that is your baroreceptors detecting a pressure drop and triggering increased sympathetic tone to constrict arterioles in non-essential beds. The precapillary sphincters at the entrance to capillary beds provide another layer of control. These are rings of smooth muscle that can open or close individual capillaries based on local tissue demand. In resting skeletal muscle, only about twenty percent of capillaries are perfused at any given time. During exercise, that number rises dramatically as metabolic byproducts like carbon dioxide, hydrogen ions, and adenosine trigger vasodilation of the precapillary sphincters and arterioles supplying active muscle.
Special Considerations In Clinical Practice
Arterial puncture sites for blood gas analysis are well known, but the complications are often underestimated. The radial artery is preferred because it is superficial and has good collateral flow through the ulnar artery, but even here complications occur. About one in five hundred needle sticks results in a hematoma large enough to warrant compression therapy. The risk increases significantly if the patient is on anticoagulants or has a positive Allen test, which indicates inadequate collateral circulation through the ulnar artery. Arterial line placement in the ICU is another area where textbook knowledge falls short of clinical reality. The radial artery is the most common site, but it is also the most prone to thrombosis and ischemic complications. I have seen forearm ischemia develop in patients with marginal peripheral circulation who received a radial arterial line without proper collateral assessment. The baseline recommendation is to perform an Allen test before placement, but even that test has limitations. It assesses palmar arch collateral flow, not the full spectrum of hand perfusion potential. A workaround I learned the hard way: When placing arterial lines in patients with known peripheral vascular disease or diabetes, I check the Doppler signal quality at the dorsalis pedis and posterior tibial arteries first. If either signal is weak or monophasic, I avoid radial access and move to the femoral artery instead, accepting the higher infection risk because limb ischemia is a worse outcome. Femoral arterial lines also tend to stay patent longer in critically ill patients who have poor peripheral perfusion.
What Standard References Get Wrong About Arterial Anatomy
Most introductory texts present the arterial system as a clean hierarchical tree, but the reality includes redundant loops, variable origins, and asymmetrical branching patterns that do not appear in simplified diagrams. The celiac trunk and the superior mesenteric artery have extensive anastomoses through the pancreaticoduodenal arteries, creating a collateral pathway between the foregut and midgut circulations. This is functionally important because it means a proximal occlusion of either vessel may not cause immediate bowel ischemia if these connections are robust. The vertebral arteries are another case where diagrams oversimplify. They arise from the subclavian arteries and ascend through the transverse foramina of the cervical vertebrae, but their course and caliber are highly variable. In about thirty percent of people, one vertebral artery is hypoplastic, meaning the basilar artery is supplied predominantly by the other side. This matters for neurovascular surgery and endovascular procedures because manipulating a catheter in the dominant vertebral artery carries different risks than working on a collateral vessel. Deep femoral artery anatomy is frequently underappreciated in general circulation discussions. The profunda femoris arises from the lateral posterior aspect of the femoral artery about four centimeters below the inguinal ligament and gives rise to the medial and lateral circumflex femoral arteries. These vessels are critical collateral pathways in cases of external iliac or common femoral occlusion. During endovascular interventions for peripheral artery disease, preserving the origin of the profunda femoris is considered essential because loss of flow through this vessel significantly increases the risk of limb loss.

Practical Exercises For Retaining Arterial Anatomy
Tracing arteries on blank anatomical outlines is more effective than passive reading. Draw the aorta, then add the major branches one region at a time. Start with the head and neck, then the upper limbs, then the abdominal branches, then the lower limbs. Fill in the smaller branches and anastomotic connections as you go. The process of drawing forces you to make decisions about spatial relationships that reading alone does not require. CT and MRI datasets from radiology departments or open-access platforms like Visible Body or Radiopaedia are excellent for understanding three-dimensional arterial relationships. Coronal, sagittal, and axial views from the same dataset allow you to see how the arteries relate to veins, nerves, and organ surfaces simultaneously. This spatial understanding is what separates someone who can identify an artery on a diagram from someone who can locate it in a live surgical or interventional setting. Pulse palpation practice on willing subjects is another practical exercise that improves retention more than any amount of flashcard review. Finding the carotid pulse requires pressing in the right location with the right amount of pressure. Press too hard and you stimulate baroreceptors and drop the person's blood pressure. Press too lightly and you will not feel the pulse at all. The femoral pulse requires firm pressure just inferior to the inguinal ligament, and the dorsalis pedis pulse can be nearly impossible to find in patients with peripheral edema or advanced arterial disease.