Getting Your Eyes On The Skin Properly
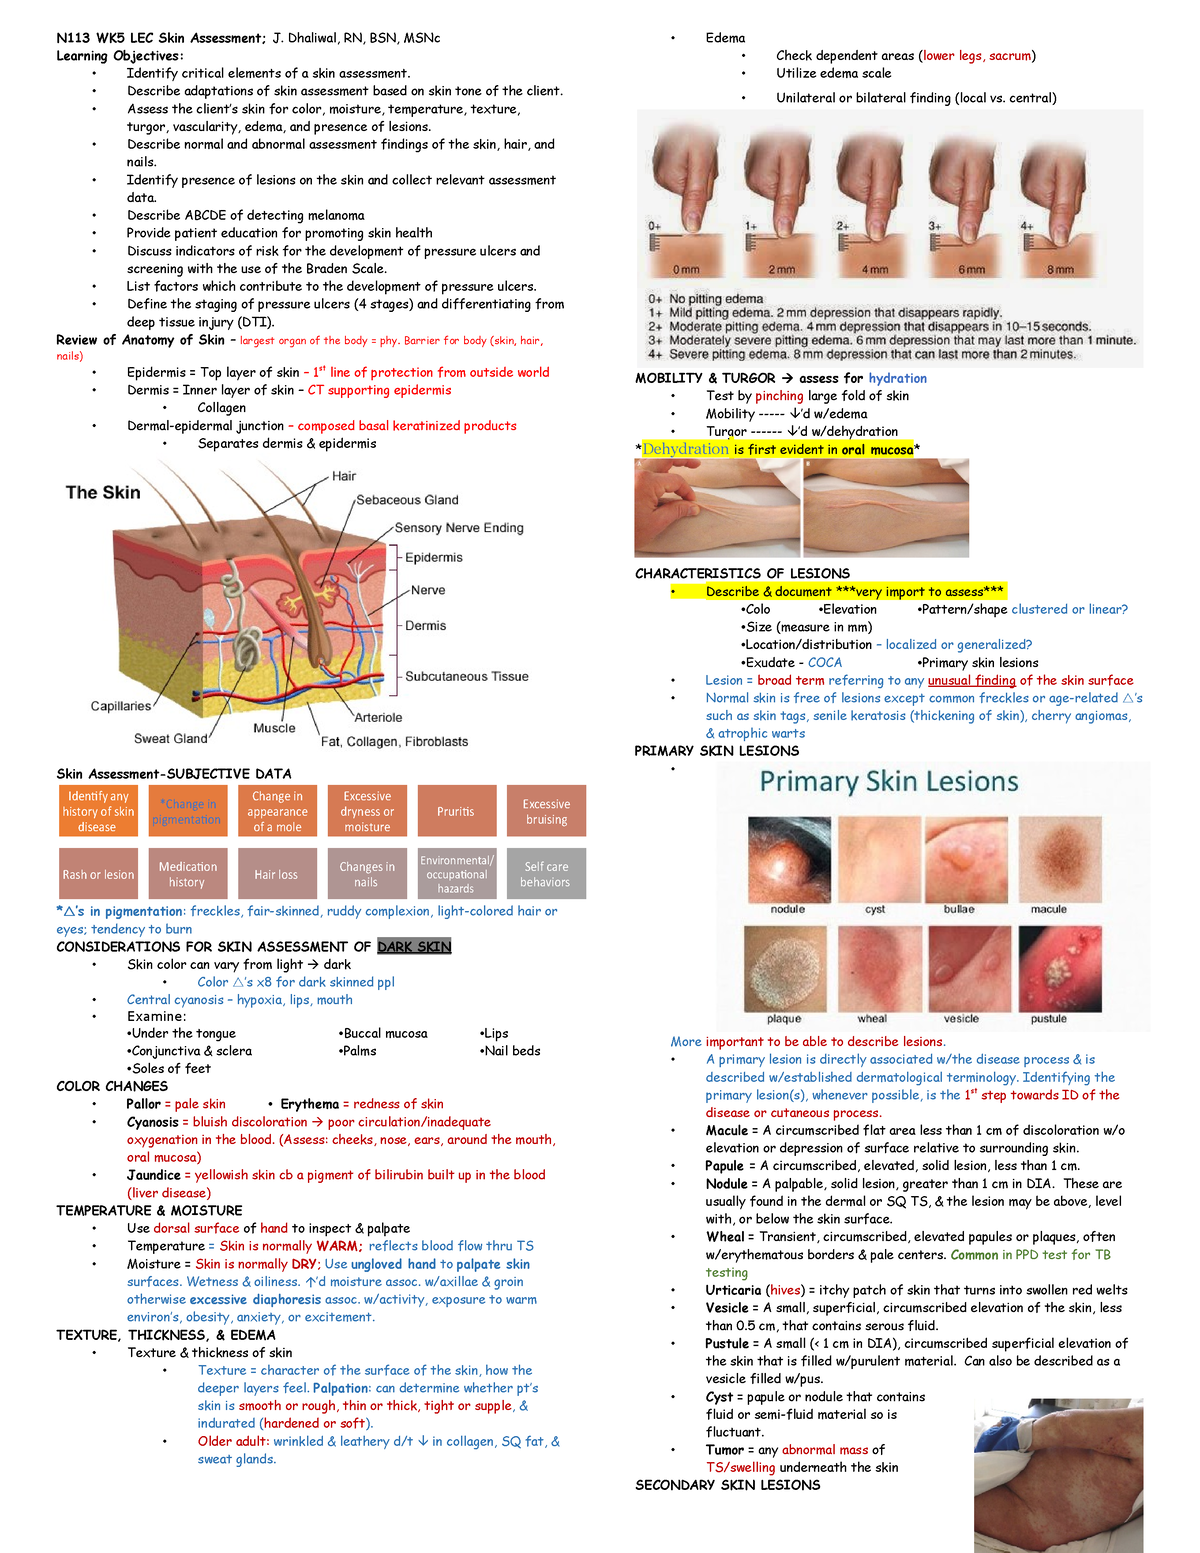
I have been doing skin assessments for years, and the single biggest mistake I see even among experienced clinicians is treating the visual inspection like a casual glance. It isn't. A proper Assessment Of The Skin requires deliberate, systematic attention to detail, and if you rush it, you will miss things. I learned this the hard way in my second year of practice when a patient came in with what appeared to be a benign seborrheic keratosis on his back. It looked textbook — well-circumscribed, waxy, stuck-on appearance. I documented it and sent him on his way. Three months later, a colleague flagged it, and a biopsy confirmed it was actually a pigmented basal cell carcinoma. I had looked at it and seen what I expected to see rather than what was actually there. The technique itself is built on two fundamental maneuvers: inspection and palpation. You assess everything in that order, and you do not skip from one to the other without completing the first. Inspection means looking at the skin under adequate lighting with the naked eye and noting color, texture, thickness, lesions, and distribution. Palpation means feeling the skin for temperature, moisture, turgor, consistency, edema, and the characteristics of any lesions you identified visually. The standard approach uses natural daylight whenever possible because artificial lighting distorts color perception, which is the most important visual cue you have. When I assess skin, I start with the general appearance of the entire integumentary system before narrowing my focus to any specific area of concern. This means checking the hands, the nail beds for clubbing or cyanosis, the mucous membranes, and the scalp. Each of these gives you information that the skin on the trunk or extremities does not. A patient with palmar erythema might have underlying liver disease. Nail clubbing points toward cardiopulmonary pathology. These are not dermatological findings in isolation — they are systemic signals wearing skin as a disguise.
The Practical Assessment Of The Skin Protocol
Here is how I actually walk through a full skin assessment in a clinical setting, the way it plays out at 4 PM after a long schedule when your attention is starting to drift and that is exactly when mistakes happen. First, I position the patient so that all areas are accessible. For a general assessment, this means the patient is in a gown or draped appropriately with good overhead lighting. I begin at the head and work downward systematically — scalp, face, neck, anterior and posterior trunk, all four extremities including the palms and soles, and the fingernails and toenails. I do not stop at the obvious lesion. The obvious lesion is almost never the only thing going on. In that same back exam where I missed the BCC, I also overlooked three actinic keratoses scattered across the patient's shoulders because my attention had locked onto the single pigmented lesion. For inspection, I use the mnemonic ABCDE for any pigmented lesion: asymmetry, border irregularity, color variation, diameter greater than 6 millimeters, and evolution. But I treat this as a starting point, not a checklist. Melanomas do not always fit all five criteria, and not every lesion that fits them is malignant. I have seen perfectly symmetric, uniformly colored nevi that were clinically stable for twenty years and turned out to be early nodular melanomas upon biopsy. The evolution criterion — change over time — is the single most sensitive indicator, but it requires that you have a baseline or that the patient has been paying attention, which most have not.
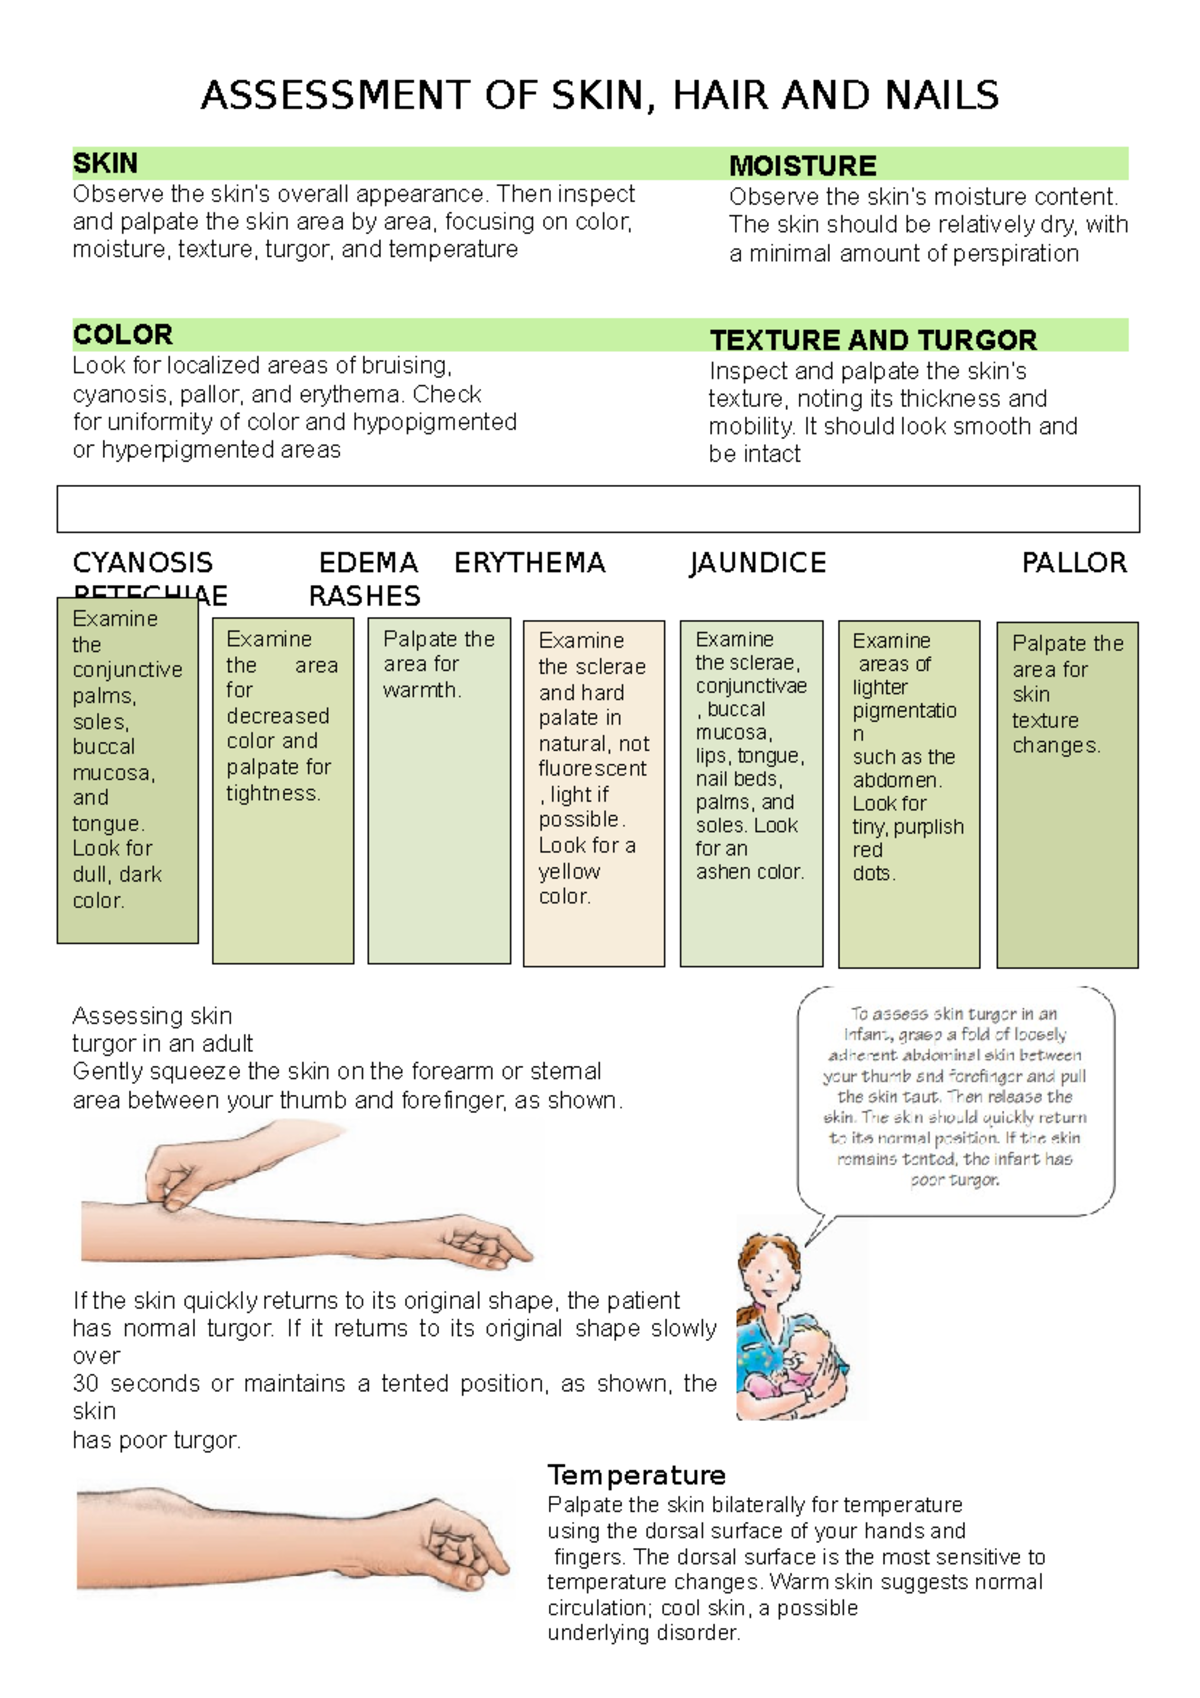
Palpation follows inspection and provides information that vision alone cannot. I assess skin turgor by pinching the skin on the anterior chest or forearm and timing how quickly it returns to position. In dehydrated patients or those with significant weight loss, turgor is diminished and the skin tent. But turgor assessment is unreliable in elderly patients because elastosis from chronic sun exposure produces the same finding. I use the forehead or the sternum for turgor in older adults instead. Temperature is assessed with the dorsal aspect of my hand, which is more sensitive to thermal differences than the palmar surface. Moisture is noted as dry, normal, or diaphoretic, and consistency is described as soft, indurated, or fluctuant. When I encounter a lesion, I document its dimensions in millimeters using a ruler or a dermatome gauge. I note whether it is elevated or flat, whether it is mobile or fixed to underlying structures, and whether it is tender. A fixed lesion that feels anchored to the fascia or muscle beneath it is far more concerning than one that moves freely under the skin. I also use dermoscopy when available — a handheld dermatoscope that illuminates the skin at magnification and reveals structural patterns invisible to the naked eye. Pigment network disruption, atypical vascular patterns, and blue-white veils are dermoscopic features that change the pre-biopsy probability estimate significantly.
Get the Full Details

Special Situations That Complicate Assessment Of The Skin
Darkly pigmented skin changes how you read everything. The classic ABCDE criteria were developed primarily on lighter skin tones, and applying them uncritically to darker skin produces both false positives and false negatives. On Fitzpatrick skin types V and VI, melanomas often present on the palms, soles, or nail beds — acral lentiginous melanoma accounts for a disproportionate number of melanoma diagnoses in Black patients. The lesion may not be pigmented at all. I had a patient with a painless, slowly enlarging nodule on his sole that I initially attributed to a callus or foreign body reaction. It was a melanoma. There was no pigment to draw my attention. On dark skin, any new, changing, or unusual lesion deserves the same urgency regardless of color. Elderly skin introduces its own set of problems. Senile purpura from chronic sun damage and fragile capillaries can mimic bleeding disorders. Cherry angiomas are nearly universal after age fifty and are irrelevant unless they change. Seborrheic keratoses multiply and can be numerous enough to cause diagnostic confusion. The key is knowing what is normal for that age group and flagging anything that deviates. I keep a mental catalog of what typical aged skin looks like so that atypical findings stand out rather than blending into the background noise of normal senescent change. I also deal frequently with patients who have extensive tattoos covering the areas I need to examine. Tattoos distort color assessment and can obscure lesions beneath the ink. I have learned to palpate tattooed areas more carefully because a subcutaneous nodule will feel abnormal even if it is not visible. I also photograph tattooed regions with a dermatoscope when possible, as the magnification and polarized light can sometimes penetrate superficial pigment enough to reveal underlying pathology.
What Clinical Assessment Cannot Tell You
The most important limitation of any Assessment Of The Skin is that visual and tactile examination alone cannot establish a definitive diagnosis for the majority of lesions. What it can do is stratify risk and determine which lesions need biopsy and which can be monitored. A clinically suspicious lesion that looks like melanoma should be biopsied regardless of how confident you feel. A clinically benign-appearing lesion that the patient is worried about should still be evaluated with dermoscopy before being dismissed. I have biopsied lesions that looked completely harmless and found squamous cell carcinoma in situ, and I have reassured patients about lesions that looked alarming and were entirely benign after dermoscopic evaluation. Dermoscopy improves diagnostic accuracy from approximately 70 percent with naked-eye examination alone to roughly 85 to 90 percent, but it still falls short of histopathology as the gold standard. The bottleneck is that dermoscopy requires training and experience — studies show that even dermatologists with fellowship training in dermatoscopy have variable performance, and primary care clinicians typically need substantial case volume to reach acceptable accuracy thresholds. If you are doing skin assessments without dermoscopy and you are not a dermatologist, your sensitivity for melanoma is considerably lower than it could be, and referral thresholds should be set accordingly. Body habitus is another practical limitation. In patients with significant adiposity, skin folds create shadowing and make inspection of the inframammary region, gluteal cleft, and intertriginous areas difficult. I use a mirror for the patient to inspect areas I cannot visualize, and I recommend that patients perform monthly self-examinations with a hand mirror and a partner-assisted full-body check using a wall mirror and a handheld mirror. Most melanomas are detected by patients themselves, not by clinicians during routine visits, and the window between patient detection and clinical diagnosis is where delay happens.
Documentation Standards That Matter
Proper documentation during an Assessment Of The Skin is not bureaucratic busywork. It is the mechanism by which change is tracked over time. I document the size of every lesion in millimeters, its exact anatomical location usingLandmarks rather than vague descriptions, and I photograph lesions that warrant follow-up. A photograph taken today with a scale bar is worth more than a thousand words in a progress note written six months from now. I use a lesion mapping approach where I take a full-body anterior and posterior photograph and mark the positions of concerning lesions with a surgical pen, then revisit those exact sites at subsequent encounters. The documentation should include your impression — benign, suspicious, or malignant — and your plan for each lesion. A lesion marked as suspicious with a plan for biopsy within two weeks is legally and clinically defensible. A lesion marked as benign with no follow-up plan is a liability if it progresses. I learned this after a patient with a "benign-appearing" lesion I documented without a plan returned eighteen months later with an ulcerated melanoma that had been present but unnoticed on my original examination. The chart showed I had seen it. It showed nothing about whether I had assessed it adequately. For patients at high risk — those with a personal history of melanoma, multiple atypical nevi, or significant family history — I perform serial total-body photography using a system like MelaFind or whole-body photographic mapping. This creates a baseline against which new or changing lesions can be compared objectively. The technology is not perfect and has limitations in sensitivity for early superficial spreading melanoma, but it has caught lesions that would have been missed on periodic clinical examination alone. The cost and time investment is significant, and it is not appropriate for every patient, but for the right population it reduces interval melanoma diagnosis, which is the failure mode you want to avoid.

A Common Pitfall With Assessment Of The Skin
Anchor bias is the most dangerous cognitive error in skin assessment. Once you label a lesion as benign, you stop looking for features that contradict that label. I fell into this trap with a lesion on a patient's scapula that I classified as a dysplastic nevus based on its size and slightly irregular border. I did not palpate it thoroughly enough to notice that it was firmer than the surrounding tissue and had a subtle firmness at its base. When the patient returned six months later complaining of tenderness, I re-examined it and noticed that the color had changed slightly and the border was no longer well-defined. Biopsy confirmed superficial spreading melanoma with early vertical growth phase. I had anchored on the nevus diagnosis and failed to reassess it properly at the follow-up visit. I make a point now of documenting a fresh impression at every encounter rather than carrying forward the previous assessment without critical re-evaluation. Another pitfall is over-reliance on the ABCDE rule at the expense of the ugly duckling sign. The ugly duckling sign means that a lesion that looks different from all the other nevi on a patient's body is suspicious regardless of whether it meets ABCDE criteria. A uniformly colored, symmetric mole that stands out as different from every other mole on that person is more concerning than an asymmetric, multicolored mole that looks identical to the patient's other atypical nevi. I use the ugly duckling sign as my primary screening tool and ABCDE as a secondary confirmation for lesions that already look abnormal. This reverses the order most textbooks teach it, but it reflects how the examination actually works in practice — you scan the whole field first, then zoom in on the outliers. The skin is the largest organ in the body and the most accessible for clinical examination, but accessible does not mean easy. An Assessment Of The Skin done carefully, systematically, and with awareness of its limitations will catch the vast majority of clinically significant findings. It will not catch everything, and pretending otherwise does a disservice to the patients you are examining. The goal is not perfection. The goal is a reproducible method that reduces the chance of missing what matters, documents your reasoning clearly, and knows when to call in a specialist rather than betting your judgment on a glance.