How We Actually Use the Axial And Appendicular System Divide
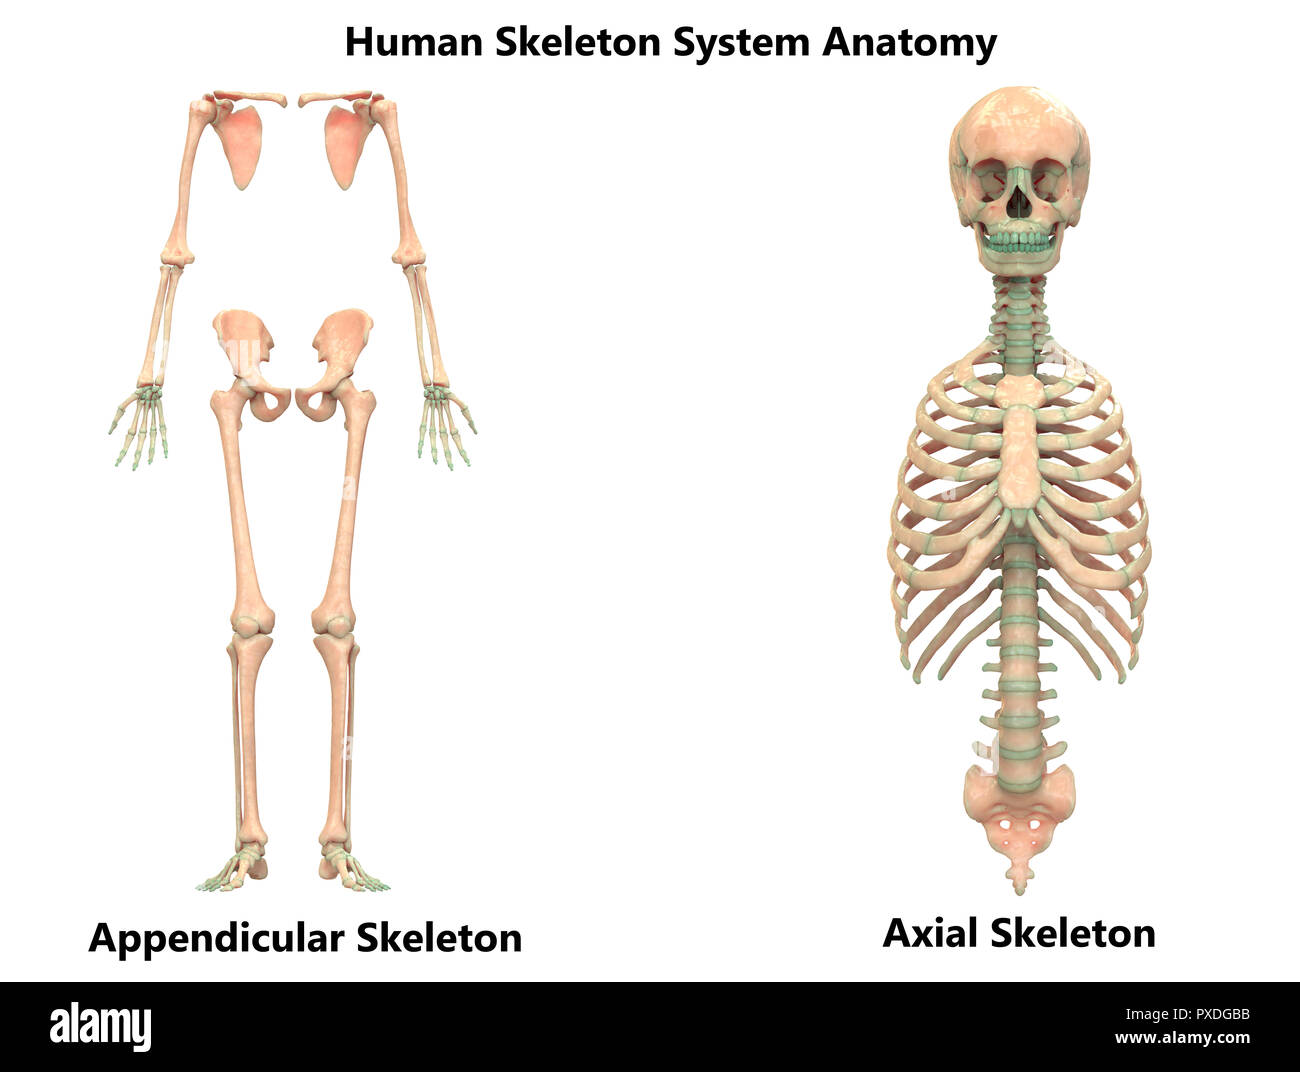
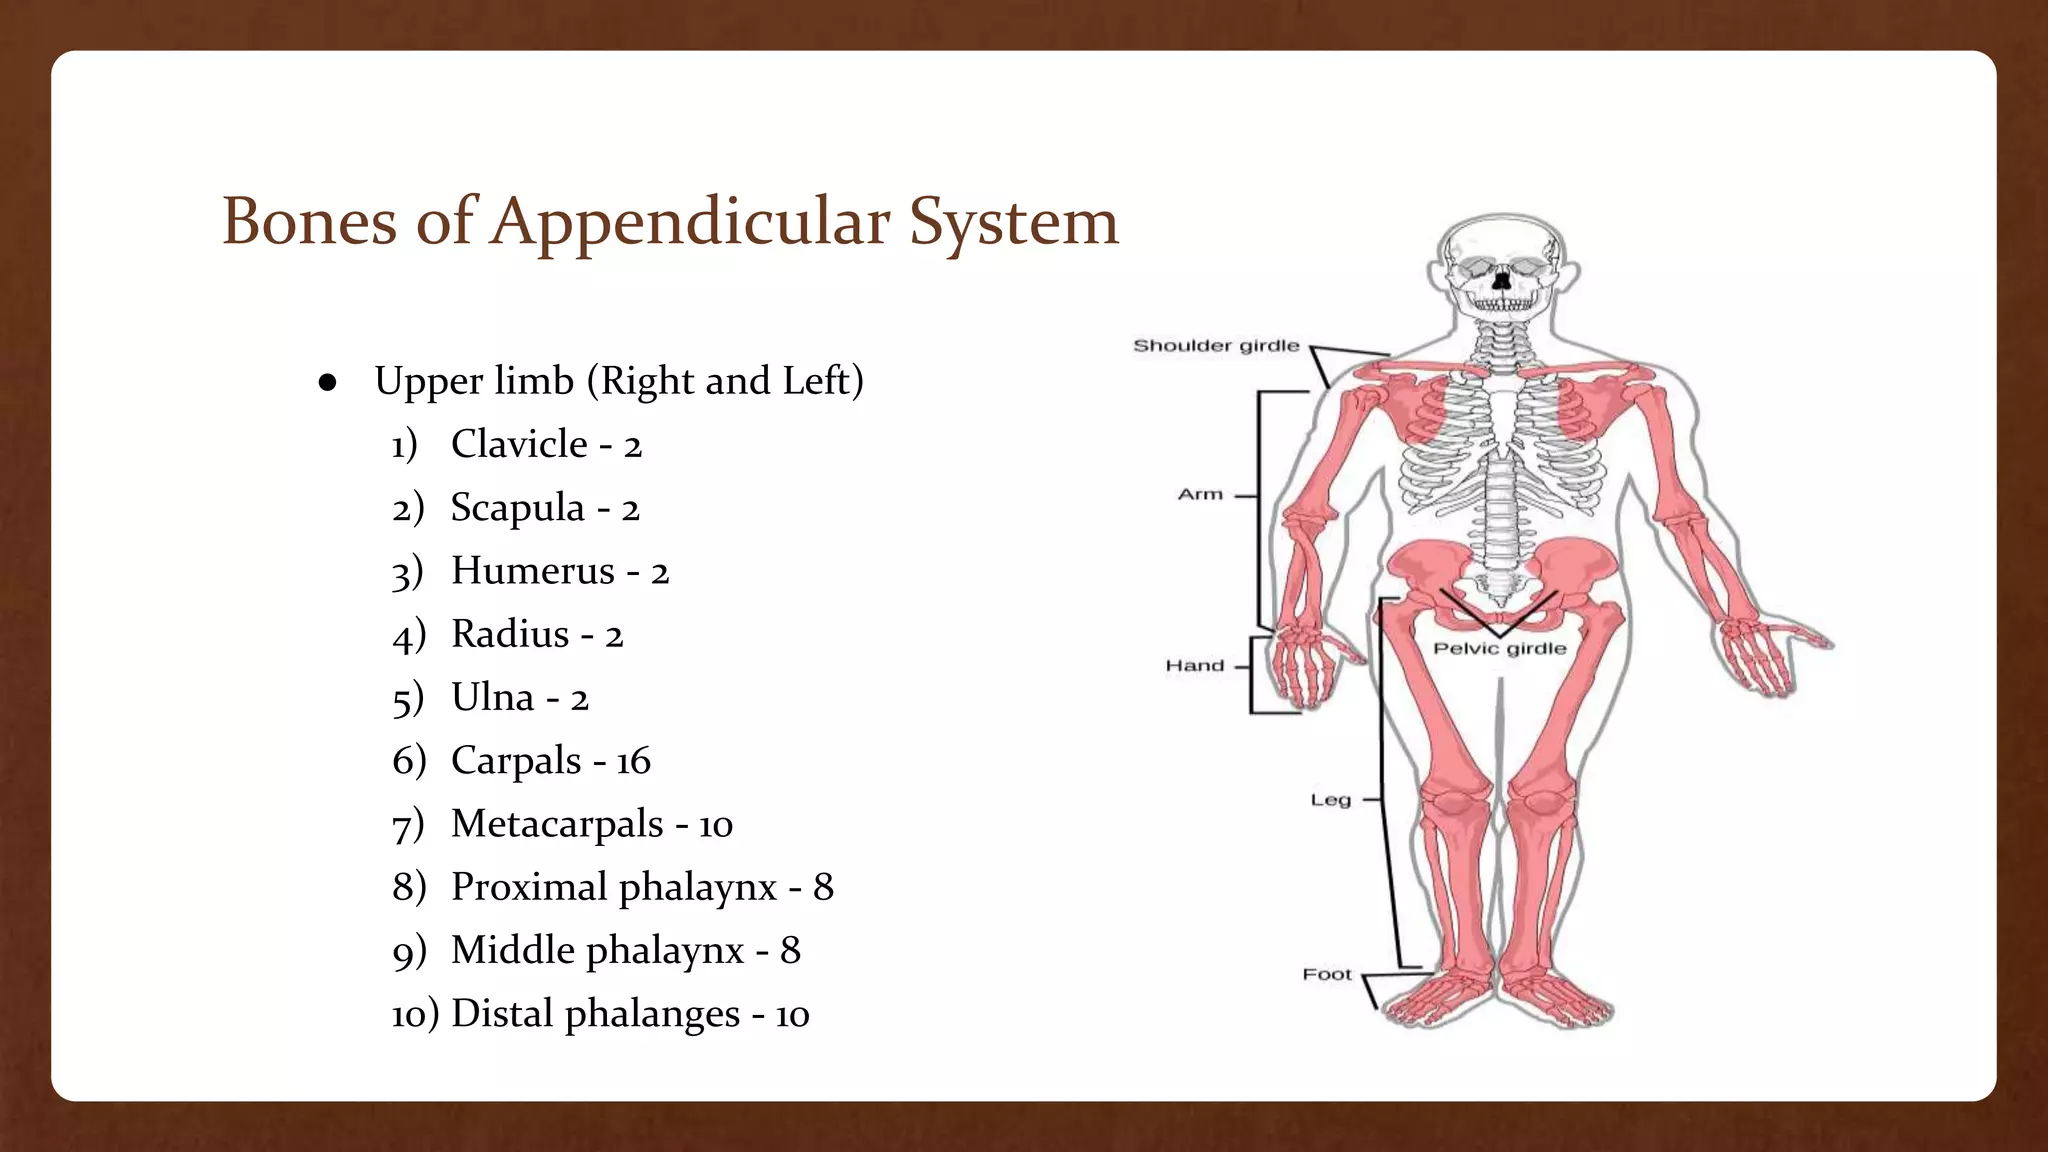
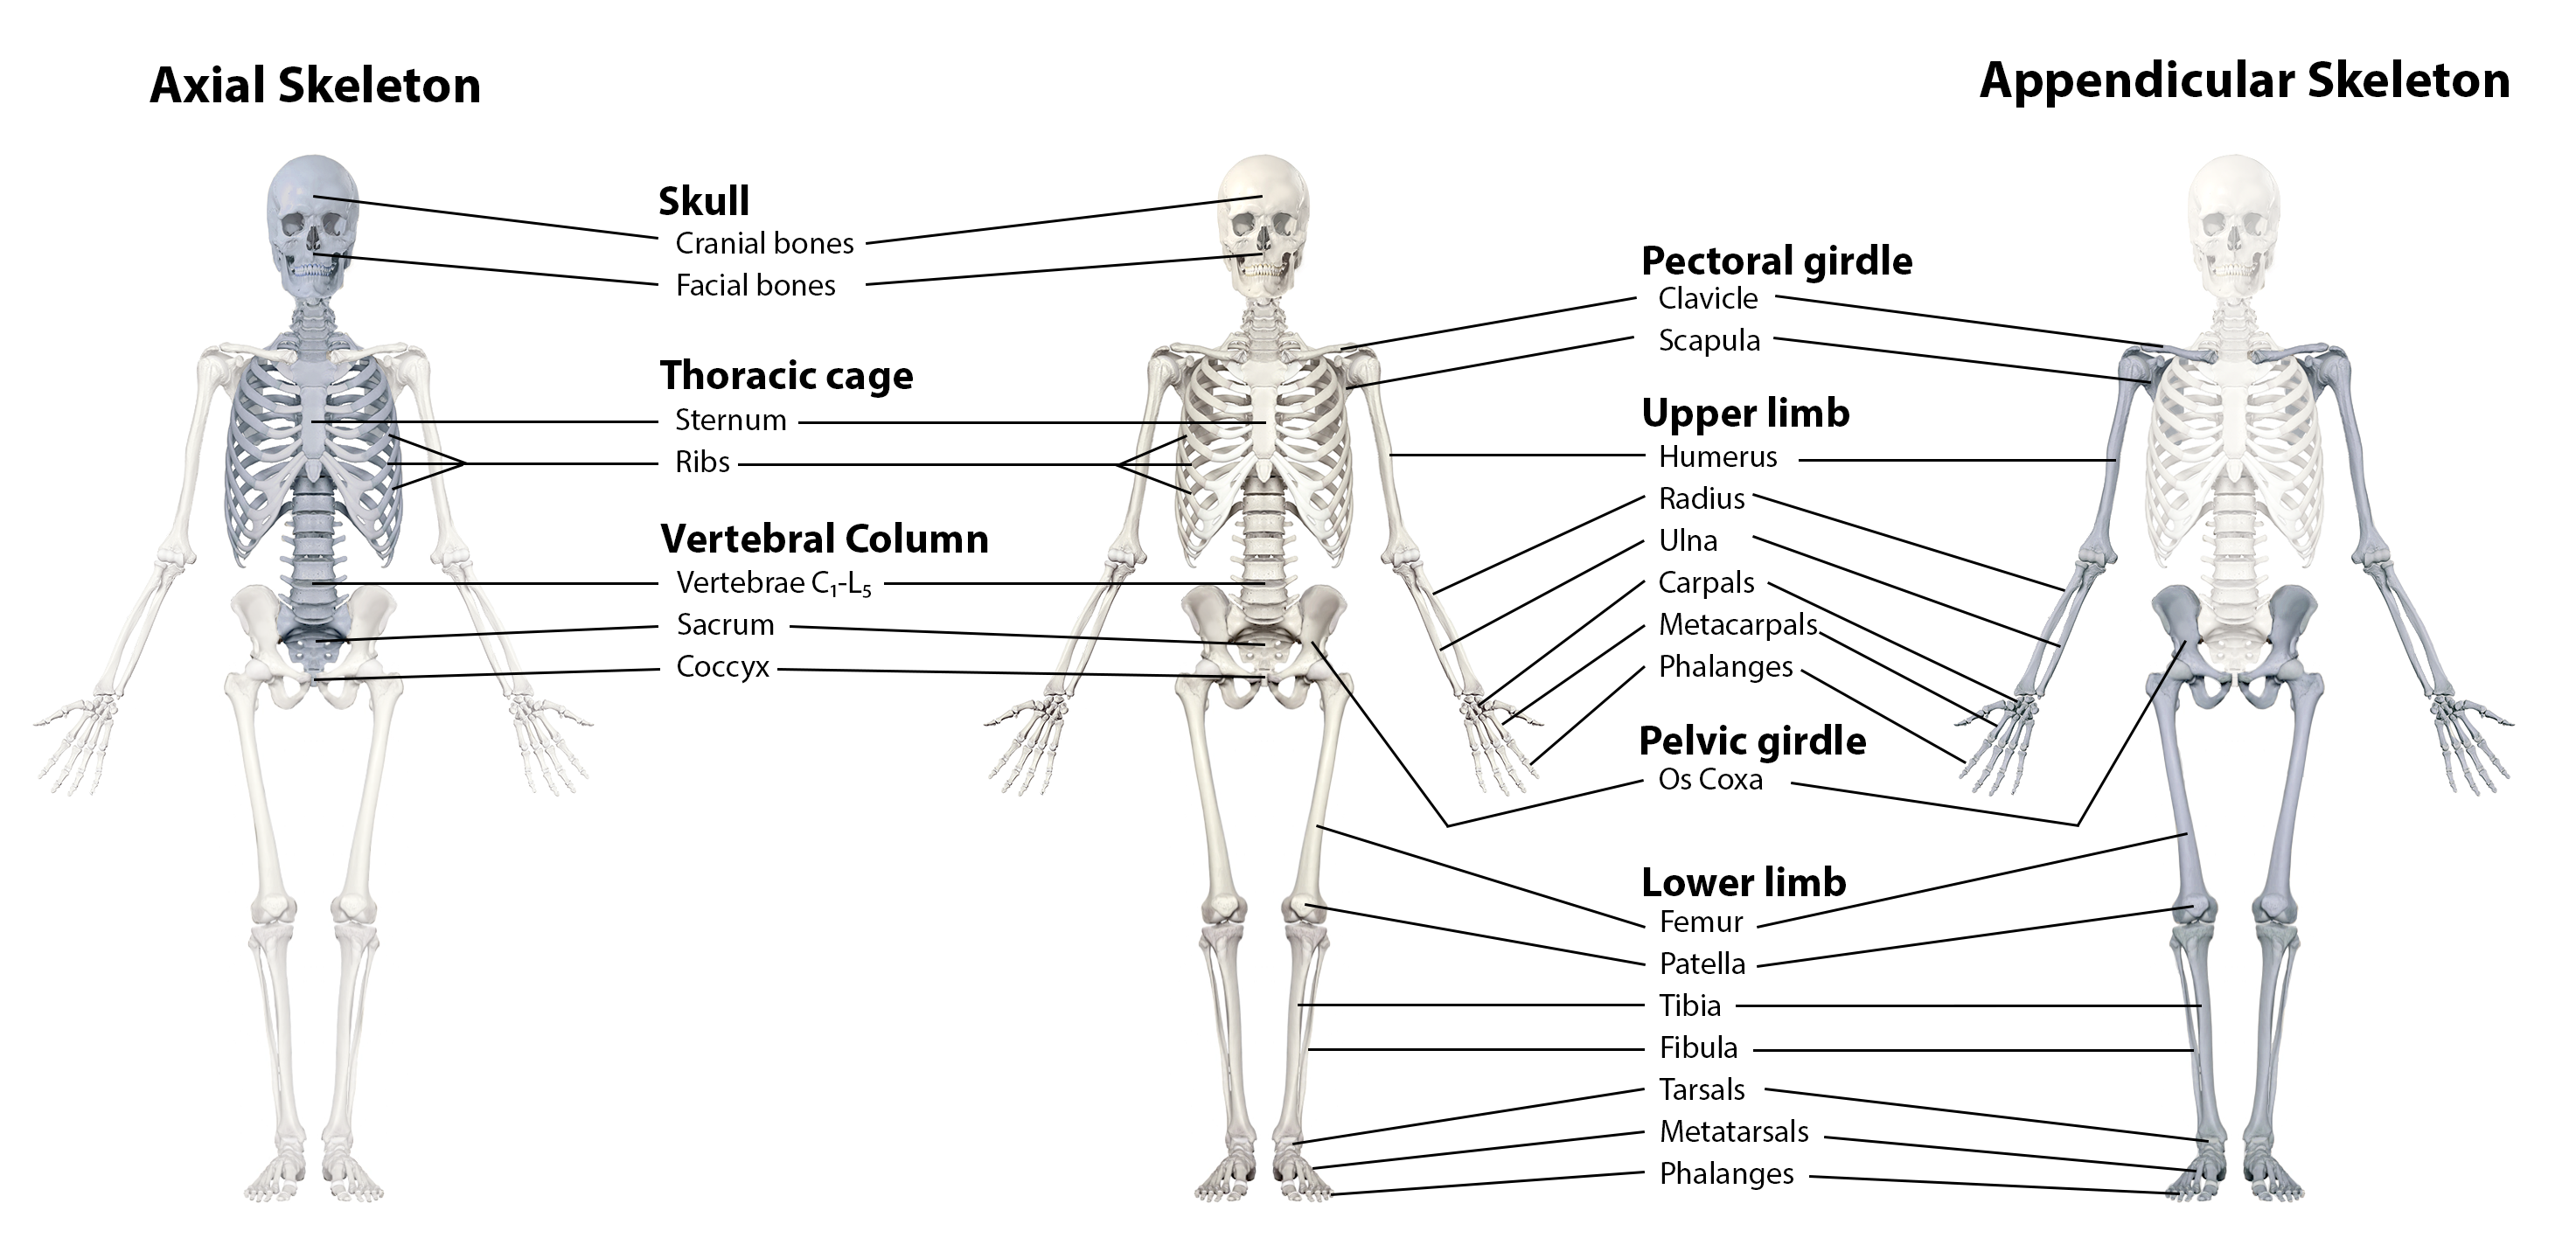
The axial skeleton is the skull, vertebral column, rib cage, and sternum. The appendicular skeleton is everything else—shoulder girdles, arms, pelvic girdles, legs, and hands and feet. You've seen this in every anatomy textbook. What you haven't necessarily seen is how this division actually plays out when you're dealing with real patients, real imaging, and real clinical communication. It matters because it gives clinicians a shared language. When a radiologist says a fracture is in the appendicular system, you immediately know we're talking about a limb or girdle, not the central axis. When they say axial, it's spine, skull, or thorax. This cuts through ambiguity faster than describing every bone individually. A CT report saying "L4 transverse process fracture" tells me more when I immediately categorize it as axial versus calling it a spinal fracture without context. But here's the thing most students miss: this classification is anatomical, not biomechanical. The systems don't operate independently. The pelvis sits at the junction between both, and that junction is where most of the clinical headaches happen.
The Problem With Treating These Systems as Separate
I spent years working in orthopedic imaging and physiatry, and the moment I stopped treating axial and appendicular elements as separate domains is the moment my diagnostic accuracy improved. The SI joint alone destroys this framework every single day. It's technically part of the appendicular girdle, but its dysfunction radiates into the axial lumbar spine. I had a patient with chronic lower back pain for eight months. Every lumbar MRI was clean. The pain pattern was classic axial discogenic, but nothing showed up on imaging. It turned out to be SI joint referral pain masquerading as a disc problem. We wasted four months and three specialist consultations before someone actually palpated the SI joint. That's not a rare edge case. Sacroiliac dysfunction accounts for roughly 15 to 30 percent of lower back pain cases, and it's consistently missed because clinicians stick to the axial framework when the pathology originates at the appendicular-axial junction.
What Beginners Get Wrong About This System
First mistake: assuming the sternum and clavicle are interchangeable anchors for upper extremity assessment. They're not. The clavicle is a strut that transfers force from the upper limb to the axial skeleton through the sternoclavicular joint. The sternum bears load differently. When I see a clinician assess shoulder stability by pressing on the sternum, something is fundamentally broken in their reasoning. Second mistake: treating the pelvic girdle as just another appendicular component. The pelvis is a weight-transfer structure. It connects the axial column to both lower limbs simultaneously. That means a unilateral hip problem often manifests as axial compensation—lumbar scoliosis, contralateral hip hike, altered gait mechanics that eventually load the spine asymmetrically. I've seen athletes with "unexplained" disc degeneration at L4-L5 who traced it back to a subtle leg length discrepancy from a childhood femoral neck fracture. The appendicular injury caused axial pathology three decades later. A third thing: the rib cage doesn't just protect organs. It's a mechanical unit that participates in every breath, every core stabilization maneuver, and every trunk rotation. Costovertebral joint restrictions can limit thoracic extension by 40 percent or more, which cascades into compensatory lumbar hypermobility. That's an axial structure causing appendicular compensation, or more accurately, a failure of one system to do its job that overloads the other.
Get the Full Details

Practical Assessment Approach
When I'm evaluating someone, I start with the axial column and move outward. Spine alignment, rib mobility, pelvic position. Then I assess each appendicular segment independently before looking at how they connect. Shoulder girdle first, then the arm. Pelvic position, then the leg. The order matters because proximal instability creates distal dysfunction, and you'll miss the root cause if you start at the hand or foot. For the upper extremity, I check scapulothoracic rhythm before looking at the glenohumeral joint. Most impingement syndromes I encounter aren't subacromial problems at all—they're scapular dyskinesis caused by weak serratus anterior and lower trapezius. The pathology sits at the interface between appendicular (scapula) and axial (thoracic cage), which is exactly why the textbook classification obscures it. For the lower extremity, I assess hip mobility before knee mechanics. The knee doesn't fail on its own. It fails because the hip above it isn't controlling femoral rotation or the ankle below it isn't managing pronation. I had a runner come to me with recurrent patellofemoral pain. Three physical therapists, six months of Quads strengthening, no improvement. We found her hip internal rotation was 35 degrees short of normal bilaterally. Once we addressed that, the knee pain resolved in four weeks. The appendicular system isn't a collection of independent levers. It's a kinetic chain, and the axial skeleton is the anchor point.
Clinical Scenarios Where the Classification Fails Completely
Trauma is the easiest example. A fall on an outstretched hand can transmit force through the clavicle, across the sternoclavicular joint, and into the cervical spine. I've seen clavicle fractures with concurrent C7 transverse process fractures because the energy traveled along that continuum. No amount of axial-versus-appendicular thinking prevents that injury pattern, but understanding the pathway does help you hunt for associated injuries. Oncology is another area where the boundary blurs. Ewing sarcoma and osteosarcoma don't respect anatomical classifications. A tumor originating in the iliac wing—an appendicular structure—can extend through the sacroiliac region and compromise the lumbar plexus, creating axial neurological symptoms. Treatment planning requires understanding both systems simultaneously, not in isolation. Developmental conditions like scoliosis further demonstrate the artificial nature of this divide. Adolescent idiopathic scoliosis is classified as an axial deformity, but the rotational component displaces ribs laterally, which is appendicular skeletal change. The treatment—bracing, surgery, observation—addresses the axial column but must account for the appendicular rib deformity or you get poor cosmetic outcomes even with acceptable coronal plane correction.
Learning This Material Effectively
Flashcards of bone names won't help you clinically. You need to understand connections. When you study the humerus, don't just memorize its attachments. Understand how the teres major inserts on the medial lip and how tightness there restricts shoulder abduction by limiting glenohumeral translation. That's an appendicular muscle affecting appendicular joint mechanics, which then creates axial compensation through scapular upward rotation patterns. Use cadaver dissection or high-quality 3D anatomy software where you can trace structures through their functional relationships. The Netter illustrations are fine for initial exposure, but they flatten the three-dimensional reality. HMA or Complete Anatomy let you isolate individual structures and then see how they articulate with neighbors. Spend more time on the junction points—the Sternoclavicular joint, the acromioclavicular joint, the SI joint, the symphysis pubis. These are where the classification breaks down and where clinical problems actually live. When studying the axial skeleton, focus on segments, not individual vertebrae. The cervical spine moves as a unit, the thoracic as a unit, the lumbar as a unit. Each has distinct mobility patterns. Cervical rotation is primarily C1-C2. Thoracic rotation follows the rib cage. Lumbar rotation is limited and usually indicates compensation from above or below. Learning these segmental principles is more clinically useful than memorizing that T4 corresponds to the nipple line.
The Limits of This Framework
The axial and appendicular classification is a teaching tool, not a biological reality. Bodies don't organize themselves this way. Fascial continuities like the anterior Oblique System and posterior Oblique System cross these boundaries constantly. The thoracolumbar fascia connects the latissimus dorsi (appendicular) to the lumbar vertebrae (axial). The rectus sheath connects the sternum to the pubic symphysis. These connections mean that dysfunction in one region almost always affects another, regardless of which system it technically belongs to. Don't treat this classification as a diagnostic algorithm. It's a communication shorthand and a learning scaffold. The moment you start believing the body respects these boundaries clinically, you'll miss the very pathologies I described above. Study the systems, learn the terminology, use it for clear documentation and collaboration, then set it aside when you're actually examining a patient. The most efficient approach I've found combines structural knowledge with functional assessment. Know where every bone is and what attaches to it. Then watch how the person moves. The gap between the anatomical classification and the biomechanical reality is where competent clinical practice lives.