What Actually Came Out of the Human Genome Project
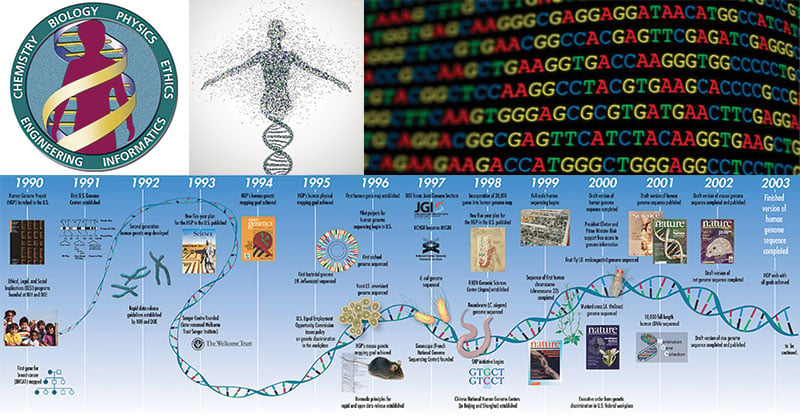
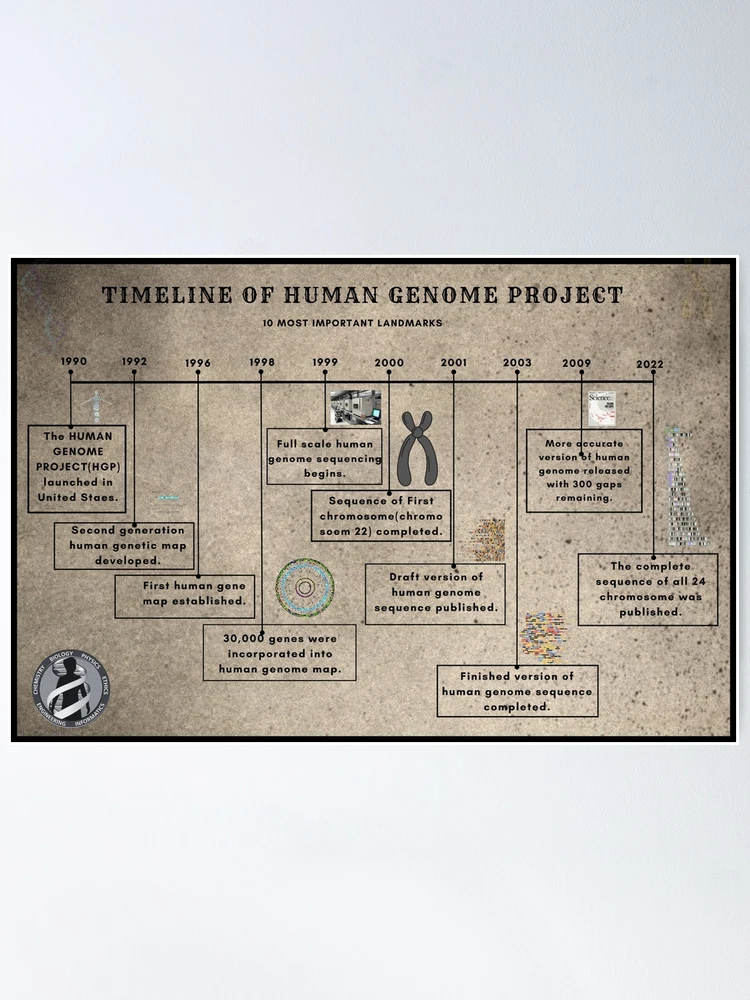
The Human Genome Project finished its first draft in 2003, after running for about 13 years and costing roughly 2.7 billion dollars. It mapped the entire sequence of human DNA base pairs — around 3.1 billion of them. That number sounds concrete, but the reality is messier than most people realize. The draft coverage had gaps. Even the "finished" version left out certain repetitive regions that current sequencing tech still struggles to read reliably. People often treat it like the project just handed us a complete blueprint for human biology. It didn't. What it really gave us was a reference coordinate system — a standardized sequence we all agree to use when reporting variants, doing gene therapy, or running clinical tests. That distinction matters more than you'd think.
Key Findings Of The Human Genome Project
Here's what actually came out of it, not the press release version: The human genome contains somewhere between 20,000 and 25,000 protein-coding genes. That number is shockingly low when you consider we once expected it to be 100,000. Nematodes have a similar gene count. The complexity of humans comes from alternative splicing, regulatory networks, and epigenetic machinery — not raw gene numbers. This was genuinely surprising to a lot of people in the field. Only about 1.5 percent of the genome codes for proteins. The rest is non-coding DNA, and calling it "junk DNA" was always a misleading shorthand. We now know large swaths of it regulate gene expression, produces functional RNA molecules, and maintains chromosomal structure. The ENCODE project later found that a high percentage of this non-coding region is biochemically active, though "active" doesn't always mean "important."
Any two random humans share roughly 99.9 percent of their DNA sequence. The remaining 0.1 percent translates to about 3 million single nucleotide differences. That's where individual variation comes from — SNPs, indels, structural variants. The 1000 Genomes Project and later gnomAD expanded on this significantly. Somatic mutation rates and germline mutation rates are different things. The genome project primarily captured a composite reference from a few anonymous donors. It wasn't one person's genome. That's a detail that gets glossed over constantly in popular writing, and it causes confusion when people try to match their own sequencing results against the reference. Copies of certain gene families vary wildly between individuals. The CYP450 family, olfactory receptor genes, and HLA regions are highly polymorphic. Standard reference genomes don't capture this diversity well, which is why population-specific reference panels matter for clinical interpretation.
Get the Full Details
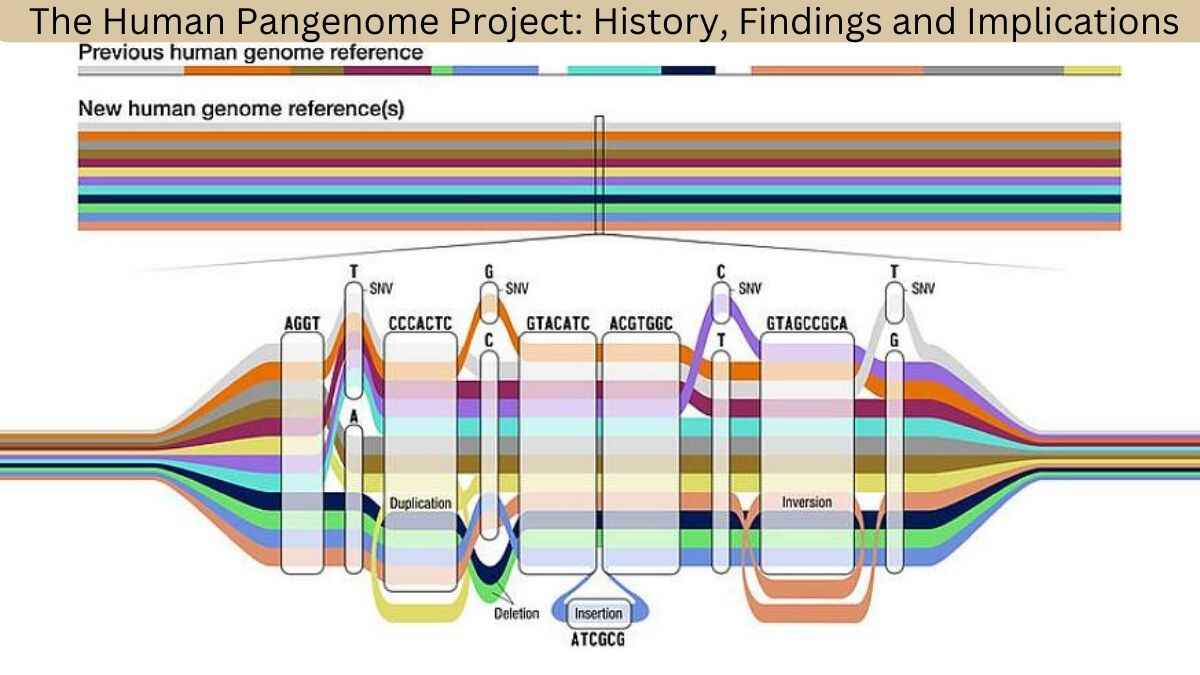
I remember running into this a few years back when I was working on a clinical variant call set. A patient had a suspected pathogenic variant in a duplicated region — basically the read alignments looked fine, but the variant caller kept flagging it as low confidence. The issue was that the reference genome had collapsed that particular segment, so reads from the patient's actual duplicated copy couldn't map uniquely. I worked around it by pulling the segmental duplication map from the DGVar database, then remapping with a decoy-aware alignment pipeline and using a tool like Manta for structural variant calling instead of relying solely on SNP/indel callers. It took about three extra hours of computational work, but it caught the real variant that would have otherwise been missed or misclassified. This kind of edge case comes up more often than you'd expect in practice, especially with clinically actionable genes that sit in complex genomic neighborhoods.
Why the Project Mattered More Than People Realize
The immediate output wasn't a medical revolution. It was infrastructure. Before the HGP, there was no standardized human genome reference anyone trusted. Research labs were using older, patchy assemblies from different sources. The project gave the world GRCh37 (hg19) and later GRCh38, along with the annotation pipelines and data standards that made large-scale genomics possible. Next-generation sequencing technologies owe everything to the push that happened during the project's later years. The cost of sequencing dropped from roughly $100 million per genome down to under $1,000 within a decade, partly because the HGP created the demand and framework for those improvements. Population genetics became a real field rather than a theoretical exercise. Projects like HapMap, 1000 Genomes, gnomAD, and the UK Biobank all built directly on the reference framework the HGP established. Without it, you couldn't do a GWAS study or interpret a rare disease genome meaningfully.
The ethics component — the EHDP, which stood for "Ethical, Legal and Social Implications" — was the first time a major scientific project dedicated 3 to 5 percent of its budget specifically to studying the societal impact of its own work. That set a precedent. GINA (the Genetic Information Nondiscrimination Act) and similar frameworks trace their roots back to conversations that started during the HGP era.
What the Reference Genome Still Gets Wrong
Even GRCh38, the current standard, has known gaps. The centromeric and telomeric regions, the acrocentric short arms with their ribosomal RNA gene arrays — these are still mostly missing or incompletely resolved. The Telomere-to-Telomere consortium published a truly gapless assembly (T2T-CHM13) in 2022, but it's based on a hydatidiform mole cell line, not a representative diploid human genome. It filled in about 200 megabases of previously missing sequence, much of it in highly repetitive regions. The T2T assembly is a scientific achievement, but it hasn't replaced GRCh38 as the clinical reference. Most diagnostic pipelines, variant databases, and EHR-integrated genomics tools still use GRCh38 coordinates. The transition will take years, and some clinical labs may never fully migrate because the cost of revalidating every assay against new coordinates is substantial. Another limitation nobody talks about enough: the reference genome is inherently biased toward certain ancestries. The original HGP donors were predominantly of European descent, and while later projects have diversified, the reference architecture and many annotation pipelines still carry that bias. Variant interpretation for non-European populations remains significantly less accurate, and this is a recognized problem in clinical genomics right now.
Practical Takeaway
If you're working with genomic data, treat the reference genome as a coordinate system, not a truth. It's a tool. Know its version, know its limitations, and don't trust variant calls in poorly mapped regions without orthogonal validation. Sanger sequencing or long-read validation catches errors that short-read pipelines will quietly pass through. It happens more than you'd think in routine clinical work, particularly in genes like BRCA1, STRC, and CYP2D6 where pseudogenes and paralogous sequences make short-read alignment unreliable.