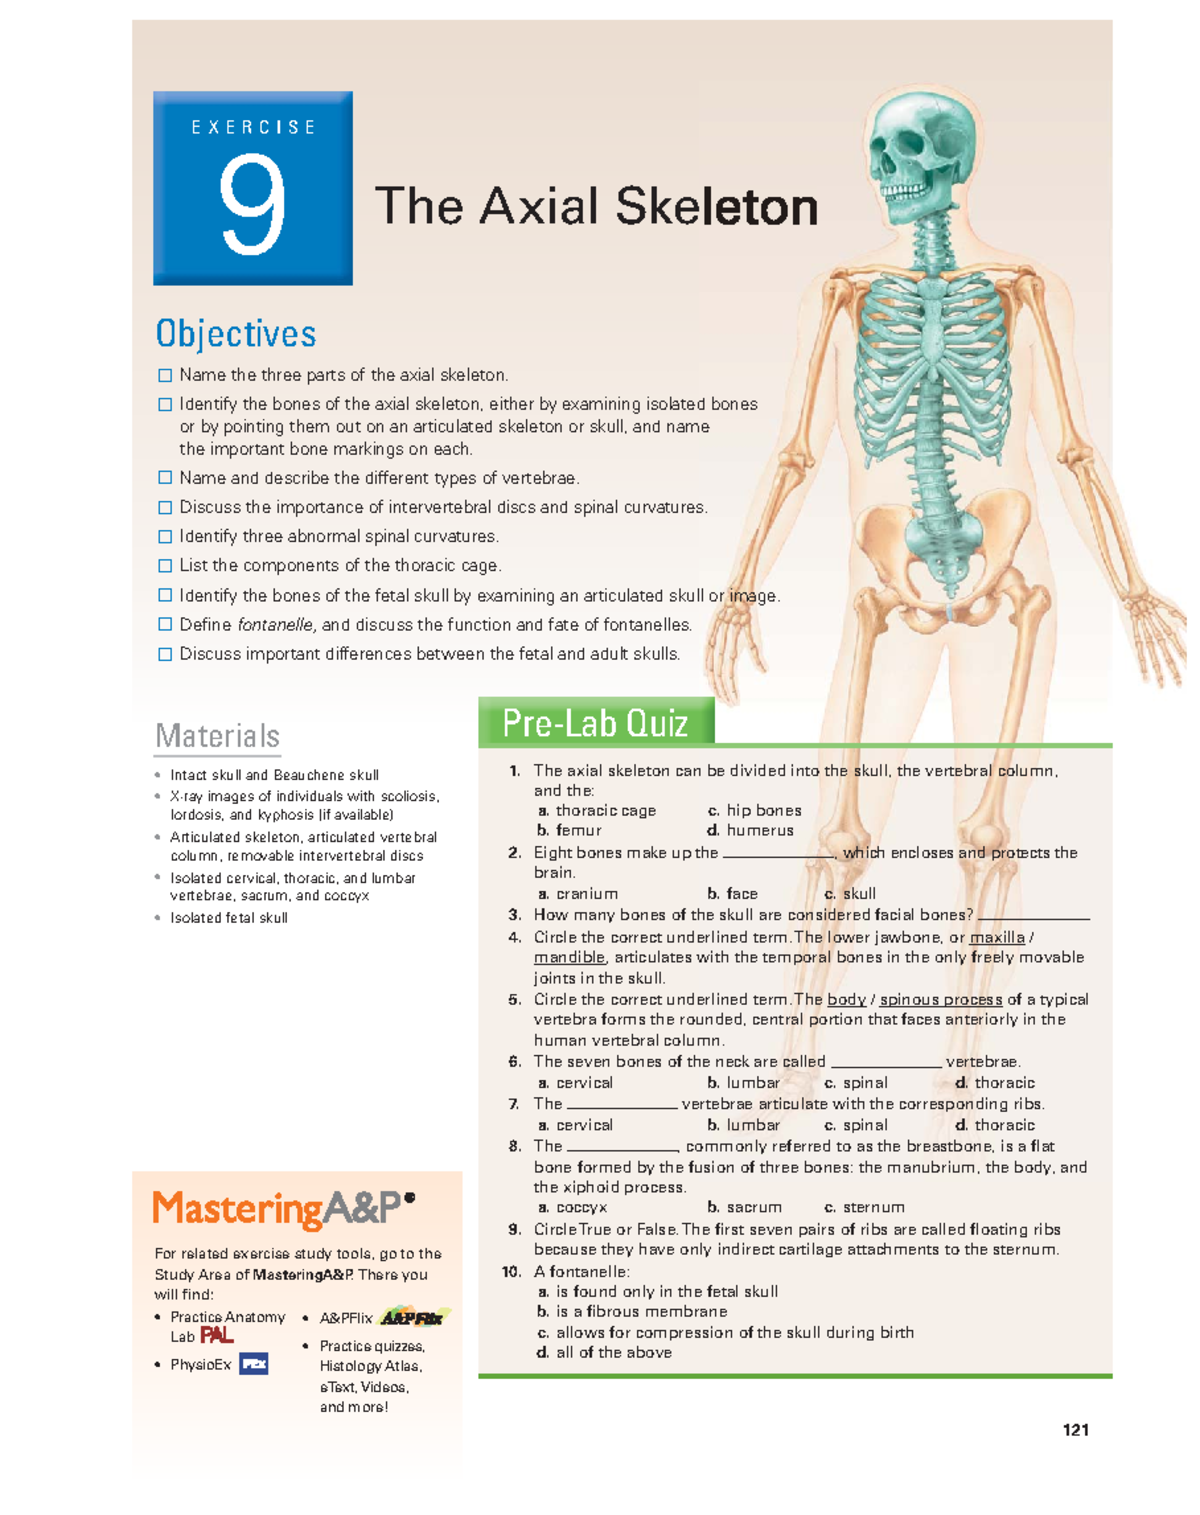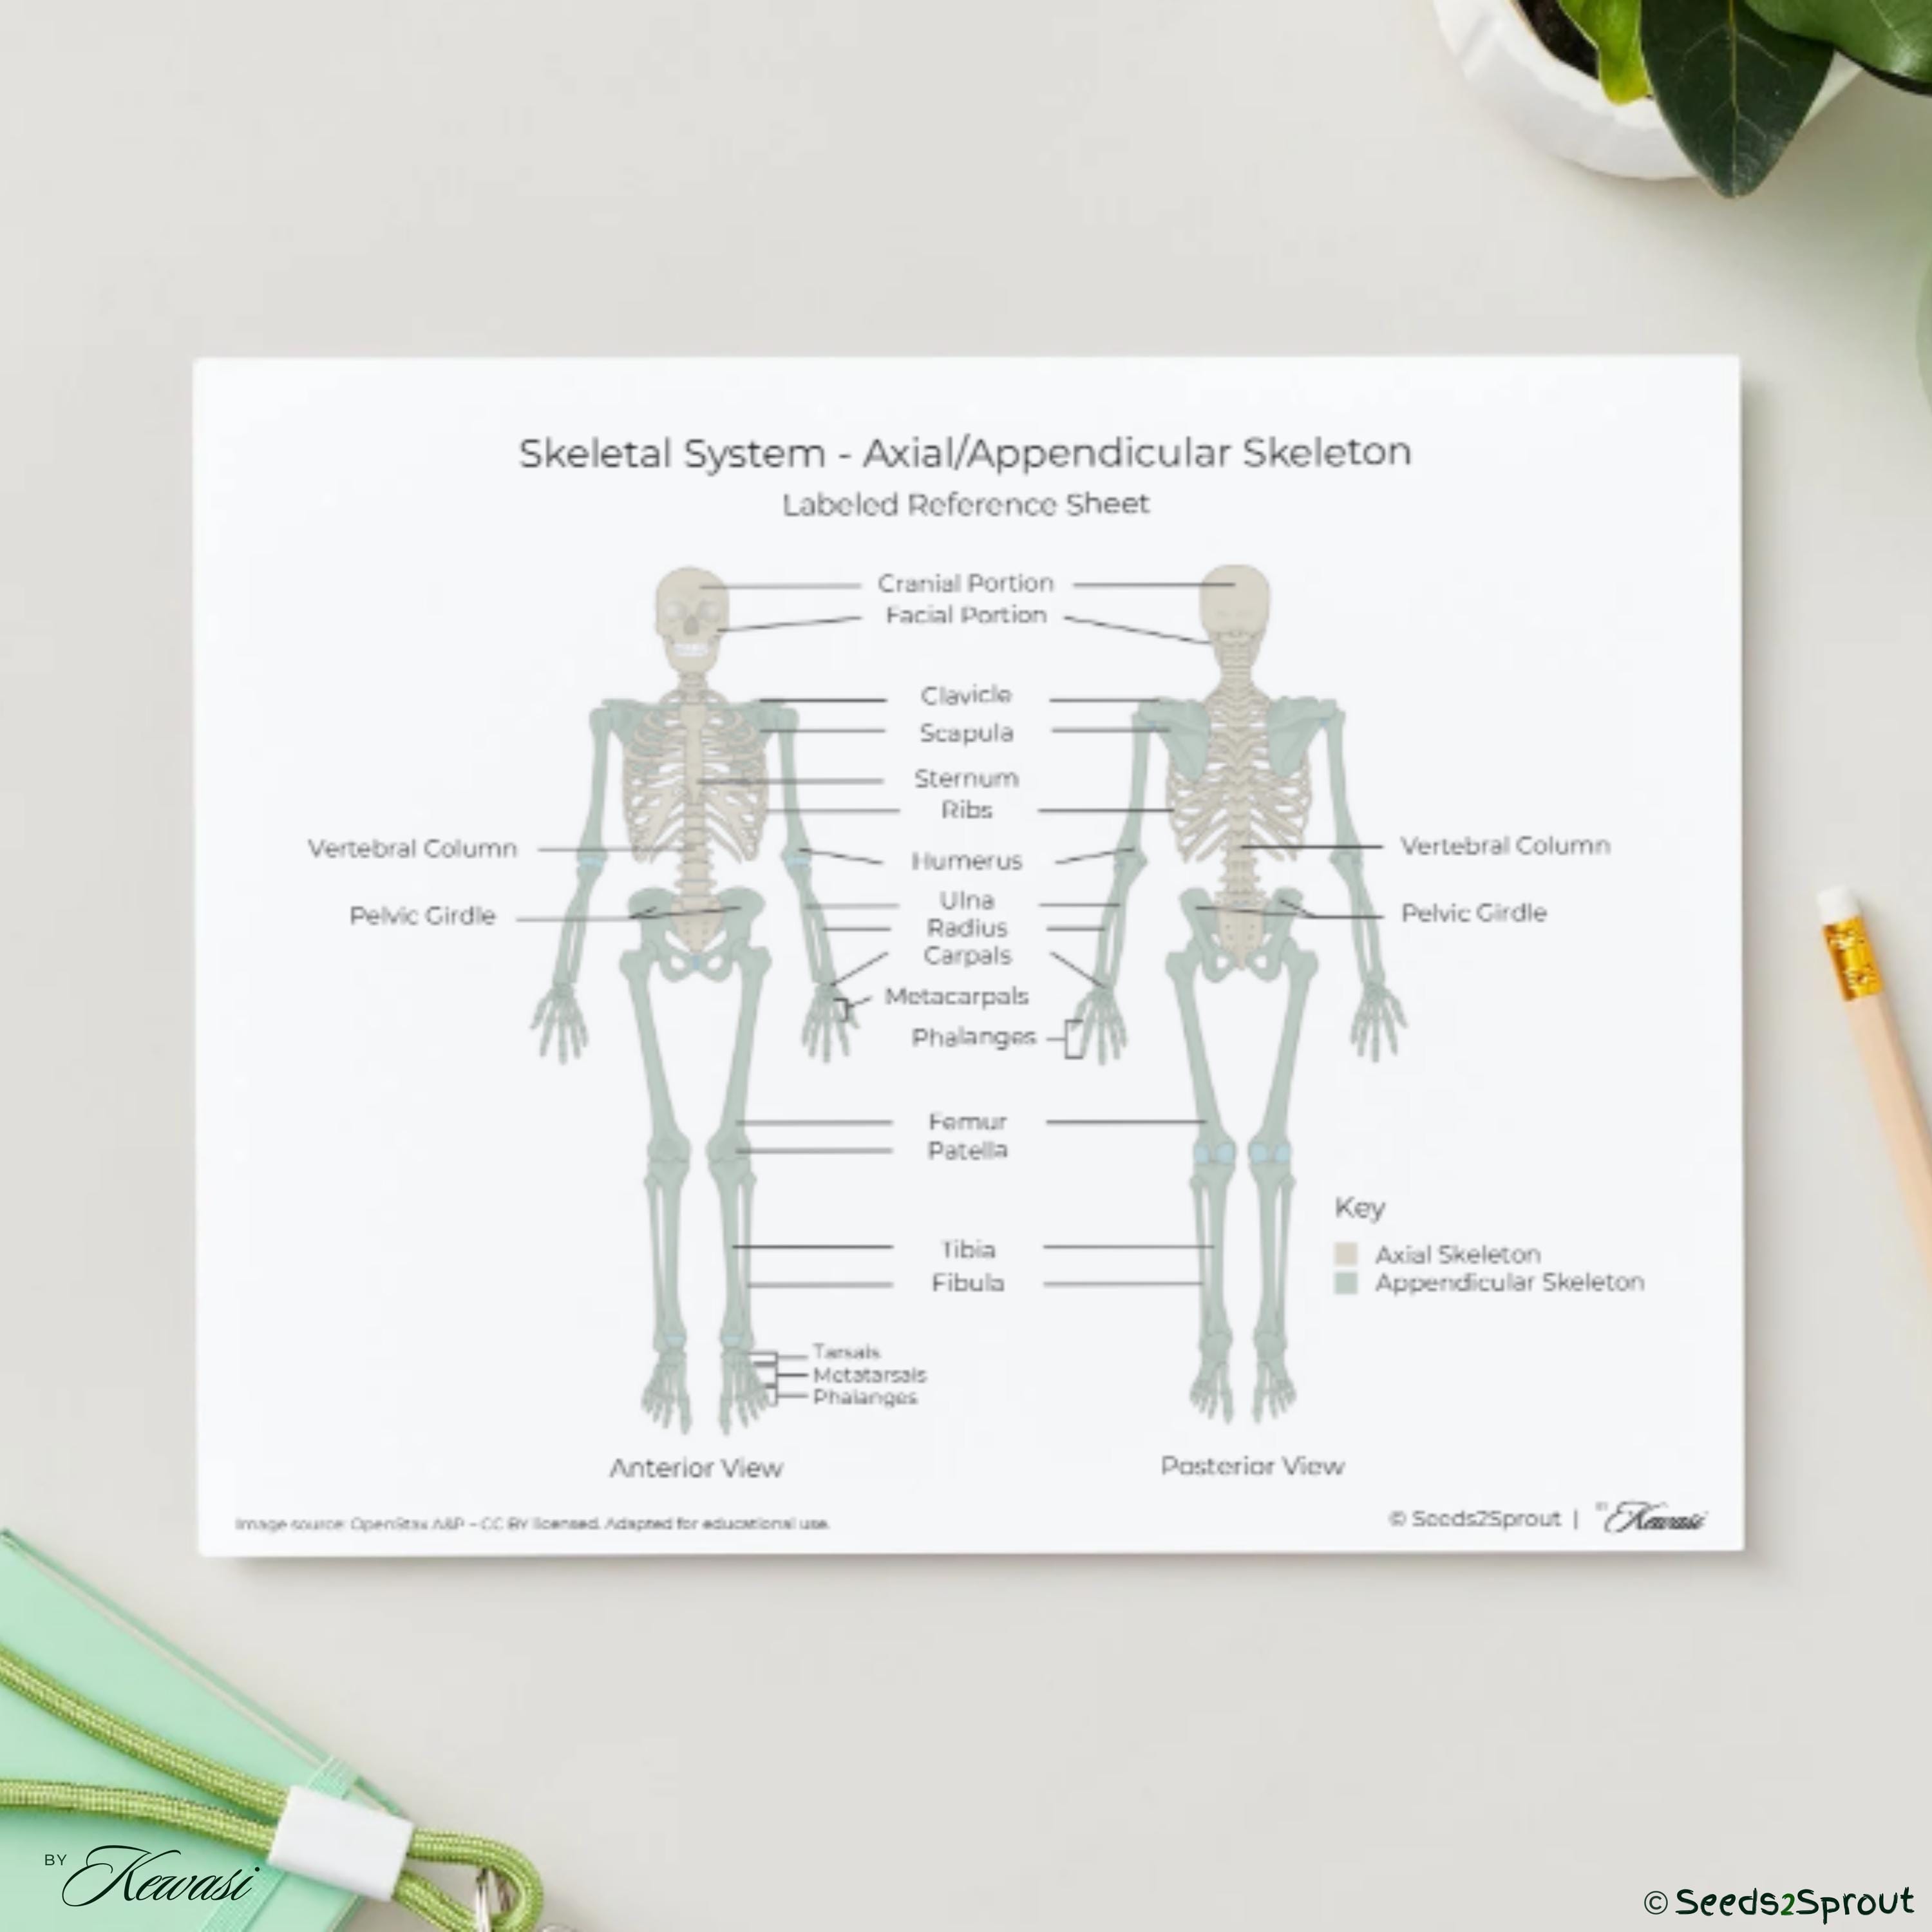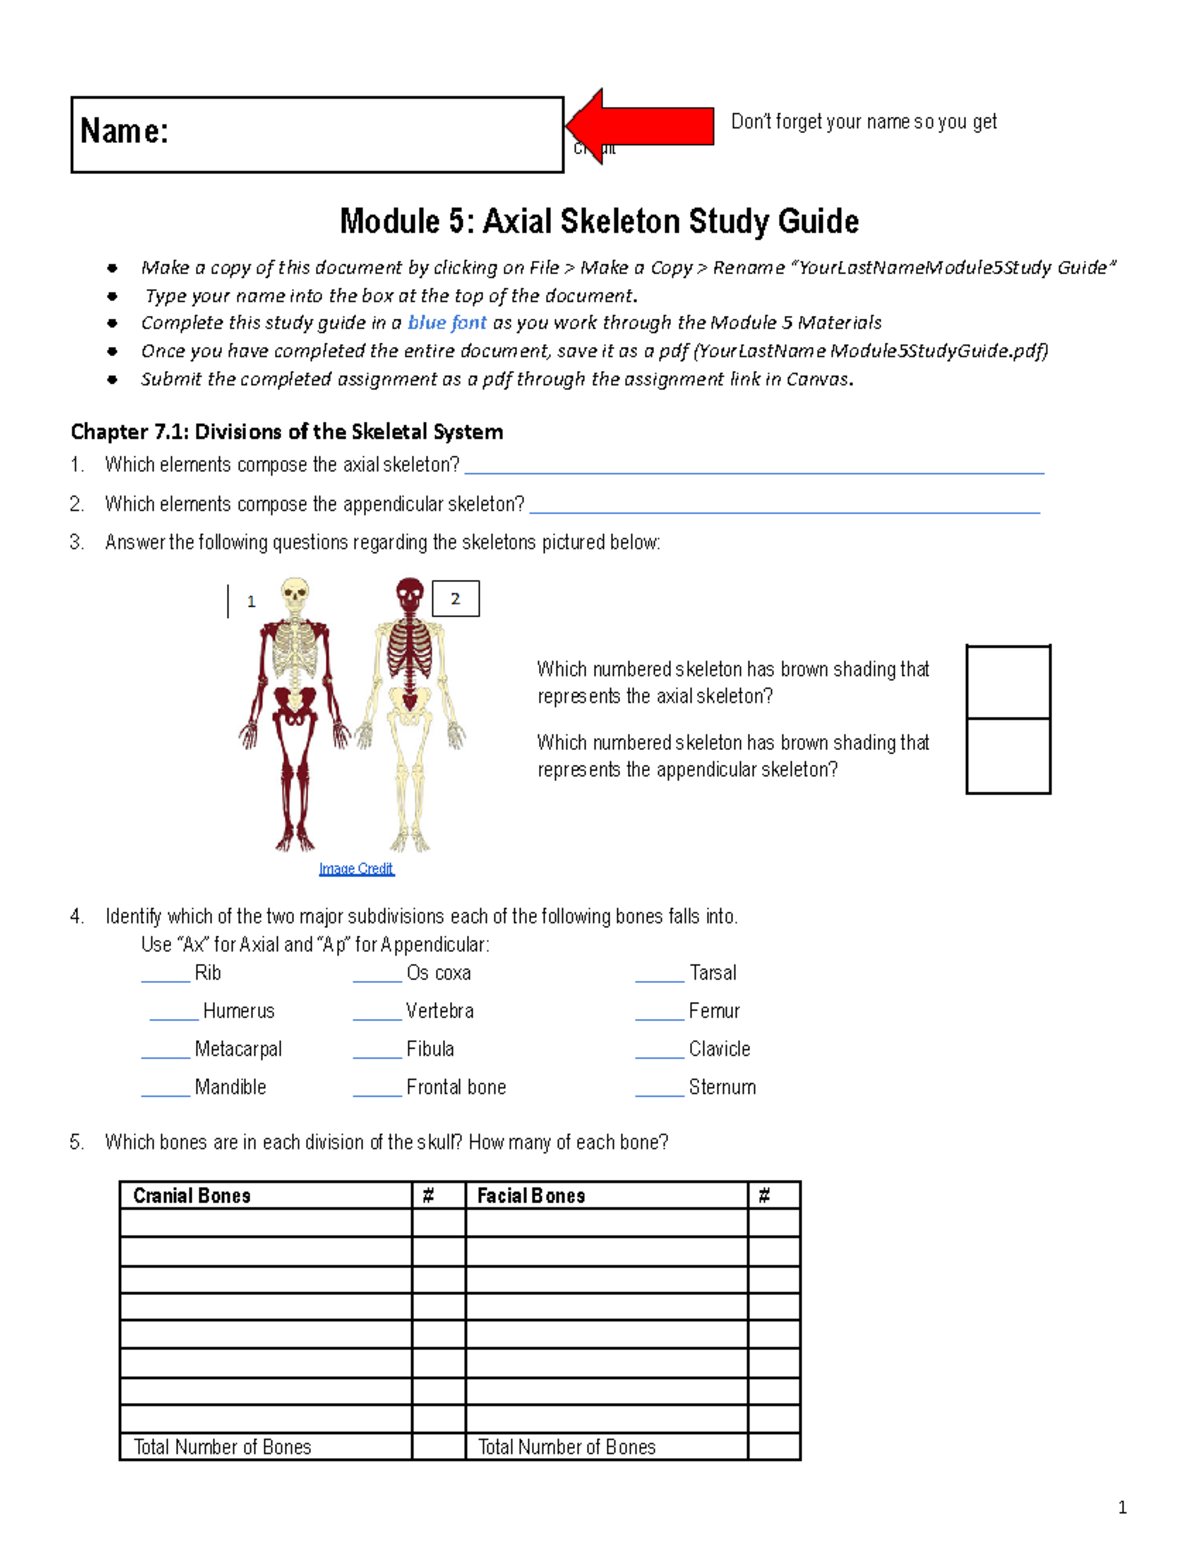
Getting Your Axial Skeleton Study Guide Images Right
Most people looking for axial skeleton study guide images are undergraduates in their second semester of anatomy, trying to figure out what a pterygoid process looks like from the lateral view before their practical exam. I've been helping people with this for a long time, and the main issue isn't finding images — it's knowing which ones to trust and how to use them efficiently.Where to Find Axial Skeleton Study Guide Images That Actually Work
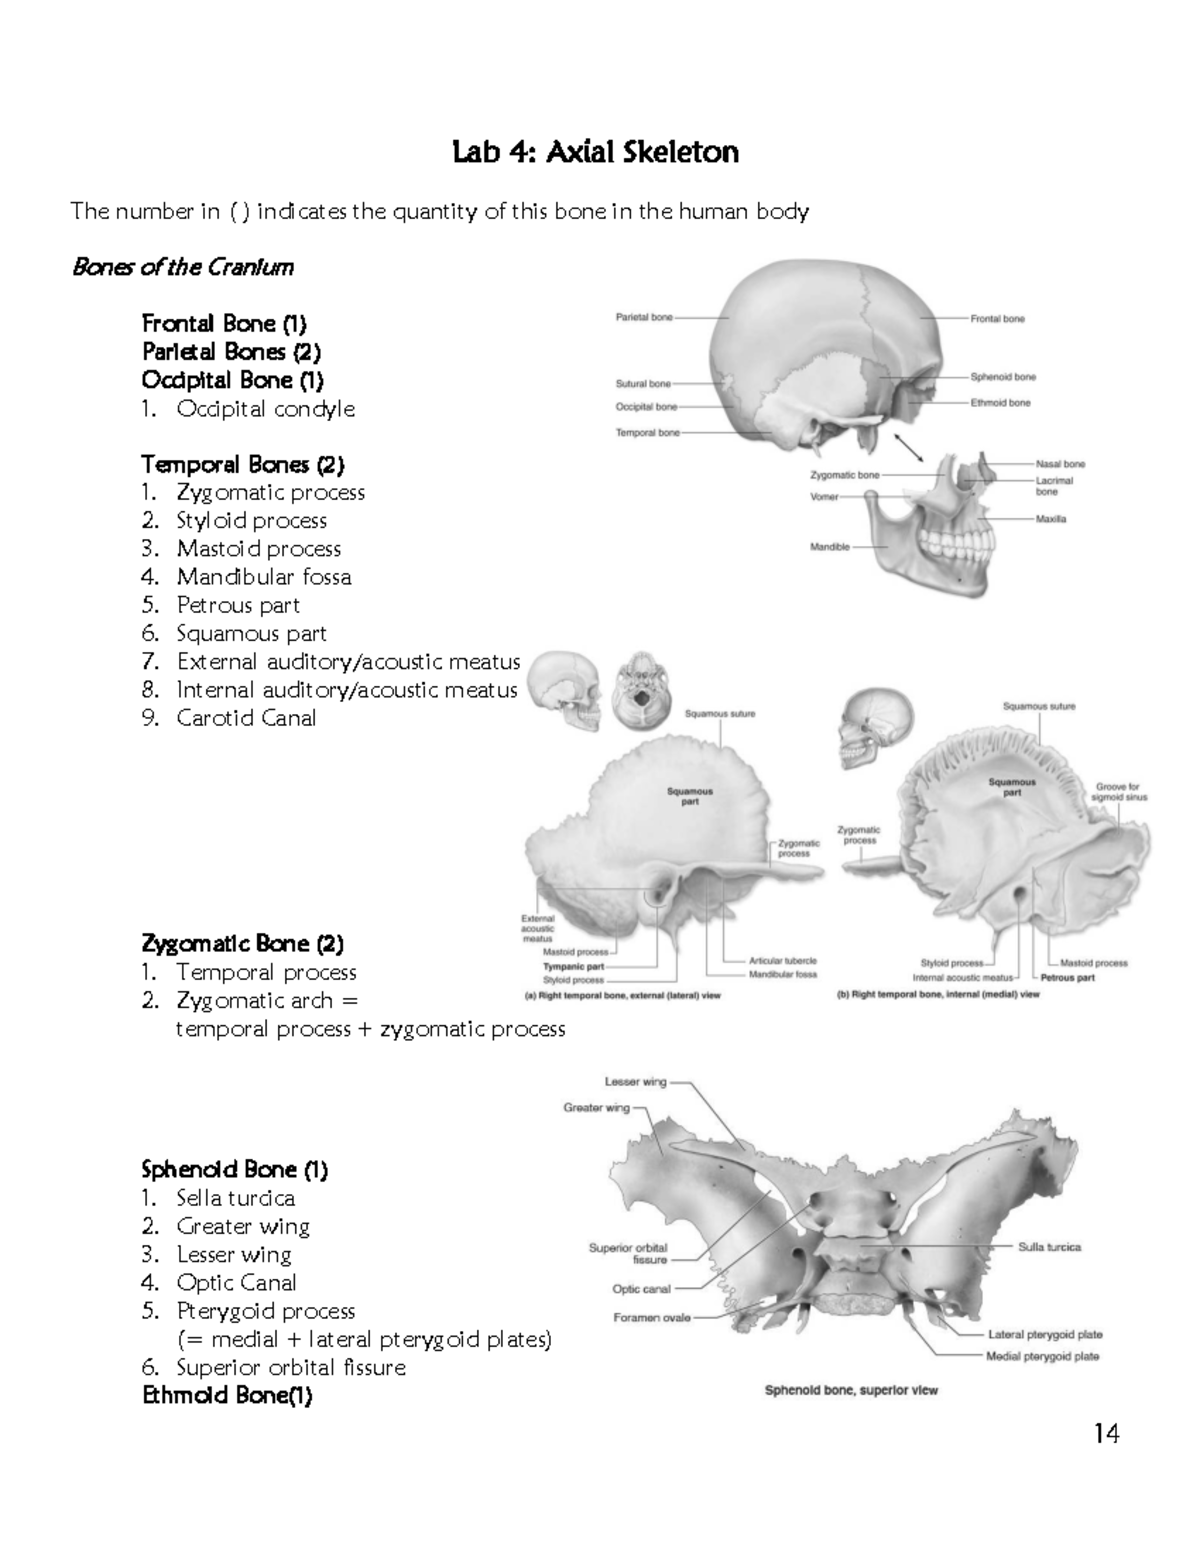
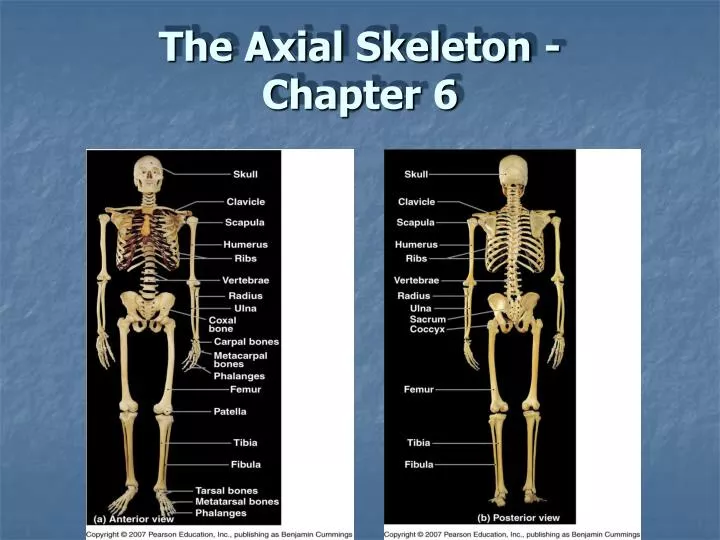
You have a few reliable sources. The first is Gross Anatomy byomos by KD Tripathi — the figures are clear and the labeling conventions match what most examiners expect. The second is Netter's Atlas of Human Anatomy, Plate 36 through 42, which covers the skull, vertebral column, and thoracic cage. If you want free resources, AnatomyZone's YouTube videos paired with their downloadable PDFs are solid, though the labeling sometimes omits structures that show up on practical exams. I recommend building your own image set rather than downloading someone else's completed set. When you trace through the images yourself, you actually remember the relationships. A student I worked with last year had memorized every foramen and sulcus from a pre-made diagram but completely blanked when presented with a real specimen because the diagram had been simplified too much. The real structure has variations that textbook images don't capture.The biggest pitfall with axial skeleton images: most diagrams flatten the three-dimensional relationships between structures. The clivus, for example, sits at an angle between the sphenoid and occipital bones that a lateral view simply cannot convey. You need both lateral and basal views together to understand that junction. Without both, you'll struggle with questions about the hypophyseal fossa or the foramen lacerum. Sinciput region: frontal bone, nasals, maxilla, zygomatic, inferior nasal concha, vomer, palatine, mandible, and the three pairs of conchae in the lateral wall of the nasal cavity. The superior concha is often tested separately because of its attachment to the ethmoid. Neurocranium: frontal, parietal (two, obviously), temporal (squamous, tympanic, petrous, mastoid portions), occipital (squamous, lateral, basilar, and foramen magnum margins), sphenoid (body, greater and lesser wings, pterygoid plates), and ethmoid (cribriform plate, perpendicular plate, crista galli).
Foramina and canals that appear repeatedly on exams: superior and inferior orbital fissures, optic canal, foramen rotundum, foramen ovale, foramen spinosum, foramen lacerum, jugular foramen, hypoglossal canal, styloid process attachments, and the mastoid foramen. The flow of the middle meningeal artery through foramen spinosum is a classic practical question. Vertebral column: cervical vertebrae have transverse foramina, bifid spinous processes (mostly), and body dimensions that increase from C3 to C7. The axis has the dens. C1 (atlas) has no body and no spinous process — just anterior and posterior arches with lateral masses. C7 has a prominent spinous process that doesn't bifurcate. Thoracic vertebrae have costal facets on the body and transverse processes. Lumbar vertebrae have massive bodies and kidney-shaped vertebral foramina. Thoracic cage: true ribs (1 through 7), false ribs (8 through 10), floating ribs (11 and 12). The sternum has three parts — manubrium, body, and xiphoid process. The angle of Louis at the manubriosternal joint is the key surface landmark for counting ribs.
A Real Problem I Encountered With These Images
I spent weeks dealing with a discrepancy between a popular digital axial skeleton atlas and an actual cadaver dissection. The atlas showed the foramen lacerum as a clean, open space between the sphenoid and temporal bones. In the cadaver, it was almost entirely filled with cartilage and connective tissue — there was no "open" foramen at all. The structures passing through its periphery were the internal carotid artery (which actually passes over it, not through it) and the greater petrosal nerve. This is the kind of thing that catches people off guard on practical exams because the imaging they studied didn't reflect the real anatomy. My workaround was simple: I overlaid my cadaver reference photos onto the digital atlas and marked every discrepancy. That became my personal study set, and it turned out to be far more valuable than either source alone. I'd recommend anyone with access to a lab doing the same.Counter-Intuitive Things About the Axial Skeleton
The hyoid bone is the only bone in the body that doesn't articulate with another bone. It's suspended by ligaments and muscle attachments. Students often miss this on written exams because it sounds too simple to be worth testing, but it comes up regularly. The sacrum and coccyx vary enormously between individuals. The number of fused sacral segments ranges from four to five, and the curvature is different enough that a one-size-fits-all diagram is misleading. If you're studying for a practical, expect to identify the posterior median crest, the dorsal sacral foramina (and the nerves exiting them), and the sacral hiatus. The hiatus is clinically relevant for caudal epidural anesthesia. Another thing beginners consistently get wrong: the vertebral artery does not pass through all transverse foramina. It enters at C6 and runs upward through C5 to C1. The suboccipital triangle formed by rectus capitis posterior major, obliquus capitis superior, and rectus capitis lateralis contains the vertebral artery at the V3 segment. This is tested frequently in neuroanatomy sections.Practical Workflow for Using These Images Effectively
Don't just look at your study images passively. Cover the labels, draw the bone outline from memory on a whiteboard, then uncover and mark where you went wrong. Repeat until the outline matches perfectly. This active recall method typically cuts your retention time by half compared to passive review. I've seen it work for students who were struggling to distinguish a temporal bone from a sphenoid bone under timed conditions. If you're using digital images, annotate them directly with free tools like PDF Annotator or even Google Drawings. The act of drawing the lines and typing the labels yourself reinforces the spatial relationships in a way that reading pre-labeled diagrams never will.For the vertebral column specifically, I found that creating a comparison table alongside my images was the most efficient approach. Column one: vertebra type. Column two: distinguishing features. Column three: common errors. Column four: clinical correlation. This took about twenty minutes to set up and saved me hours during exam prep.
Get the Full Details