What Actually Happens in Behavioral Therapy
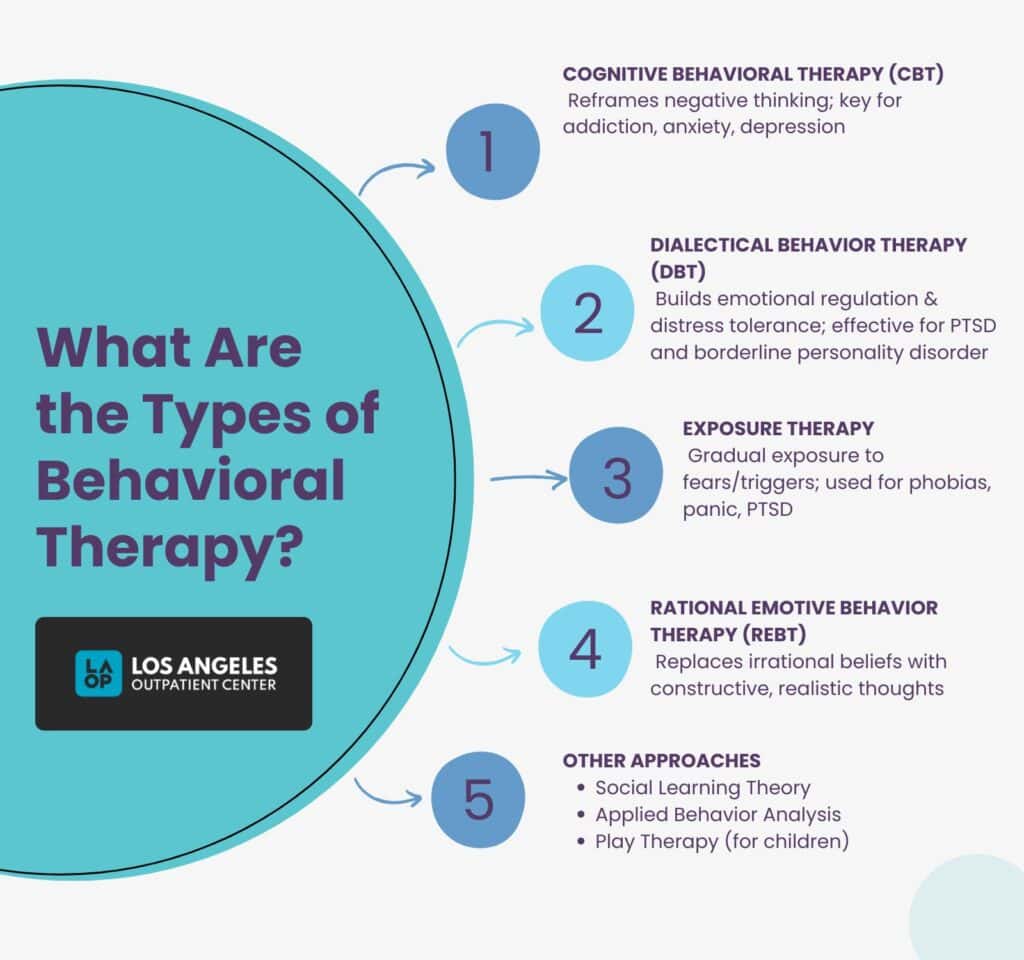
Behavioral therapy definition psychology comes up constantly in online forums and Reddit threads because people keep trying to pin down exactly what it is versus other forms of treatment. The short version is that behavioral therapy is a structured, evidence-based form of psychotherapy that focuses on changing observable behaviors through conditioning techniques rather than exploring unconscious motives or childhood trauma. The long version involves a lot more nuance that most definitions skip over entirely. The formal Behavioral Therapy Definition Psychology centers on the idea that maladaptive behaviors are learned and can therefore be unlearned or replaced. You're not digging into why someone avoids social situations. You're looking at the avoidance pattern itself, identifying what maintains it, and systematically interrupting that maintenance cycle. Exposure therapy, systematic desensitization, reinforcement schedules, and stimulus control are the core tools in the toolbox. I want to address something most introductory resources get wrong about behavioral therapy. People assume it's purely about positive and negative reinforcement like you'd see in a lab setting with rats pressing levers. That's a misunderstanding that does the approach a disservice. Real clinical behavioral therapy involves complex contingency analysis where multiple reinforcement schedules interact simultaneously. A patient might be avoidantly reinforced through anxiety reduction while also receiving social reinforcement from family members who accommodate the behavior. Untangling those contingencies takes actual clinical skill and isn't just about reward charts.
Here's a specific problem I ran into recently that nobody warns you about. I was working with a client who had developed what looked like straightforward OCD-related contamination fears. Standard exposure and response prevention protocol should have worked cleanly within six to eight sessions. Instead, the contamination behaviors were being maintained by a secondary contingency I completely missed at first. The client's spouse was unknowingly participating in family accommodation by performing excessive cleaning rituals themselves. Every time the client avoided touching certain surfaces, the spouse would clean them, which reduced the client's anxiety and reinforced the avoidance. But it also reinforced the spouse's own compulsive cleaning behavior in a feedback loop neither of us noticed until session four. The workaround was to bring the spouse into the treatment framework and restructure the contingency entirely. We had to stop treating the client in isolation because the maintenance system extended beyond their individual behavior. Once the spouse agreed to stop the accommodation behaviors and instead gently redirect when the cleaning urge came up, the exposure protocol started actually working. The contamination fears dropped significantly within the expected timeframe after that shift. This kind of systemic complexity gets glossed over in textbooks but shows up constantly in practice. Another thing worth noting about behavioral therapy that practitioners rarely mention upfront is the dropout rate. Behavioral interventions tend to have higher early dropout rates compared to some other modalities because the work is actively uncomfortable by design. Exposure work is literally designed to generate distress. Clients often leave within the first three sessions because the discomfort feels worse than whatever they were already dealing with. This isn't a flaw in the approach but it is a practical reality that affects outcomes significantly.
If behavioral therapy doesn't fit a situation, it doesn't fit a situation. It's not effective for conditions where the primary issue isn't maintainable through behavioral mechanisms. Severe personality disorders with entrenched relational patterns often require approaches that address underlying schemas and attachment issues more directly. Psychodynamic and schema-based approaches can be more appropriate there. Behavioral therapy also struggles when cognitive distortions are so severe that they prevent engagement with the behavioral work itself. That's where combining CBT elements becomes necessary rather than optional. The research literature supports behavioral therapy strongly for anxiety disorders, obsessive-compulsive disorder, certain addiction protocols, and behavioral pediatric issues. The effect sizes are generally in the moderate-to-large range depending on the specific condition and treatment fidelity. But the research also consistently shows that therapist competence and proper implementation matter enormously. Poorly delivered behavioral therapy is often no better than placebo, which is true for almost every psychological intervention but particularly relevant here because the techniques look deceptively simple on paper. If you're looking for actual resources on this topic, the Association for Behavioral and Cognitive Therapies maintains a solid therapist directory and their publications list covers the most current research. The Journal of Contextual Behavioral Science publishes work on newer developments in third-wave behavioral approaches that extend traditional models. Those are starting points that will point you toward more specialized material if you need it.




