The Reality of Writing Care Plans for Bipolar Disorder
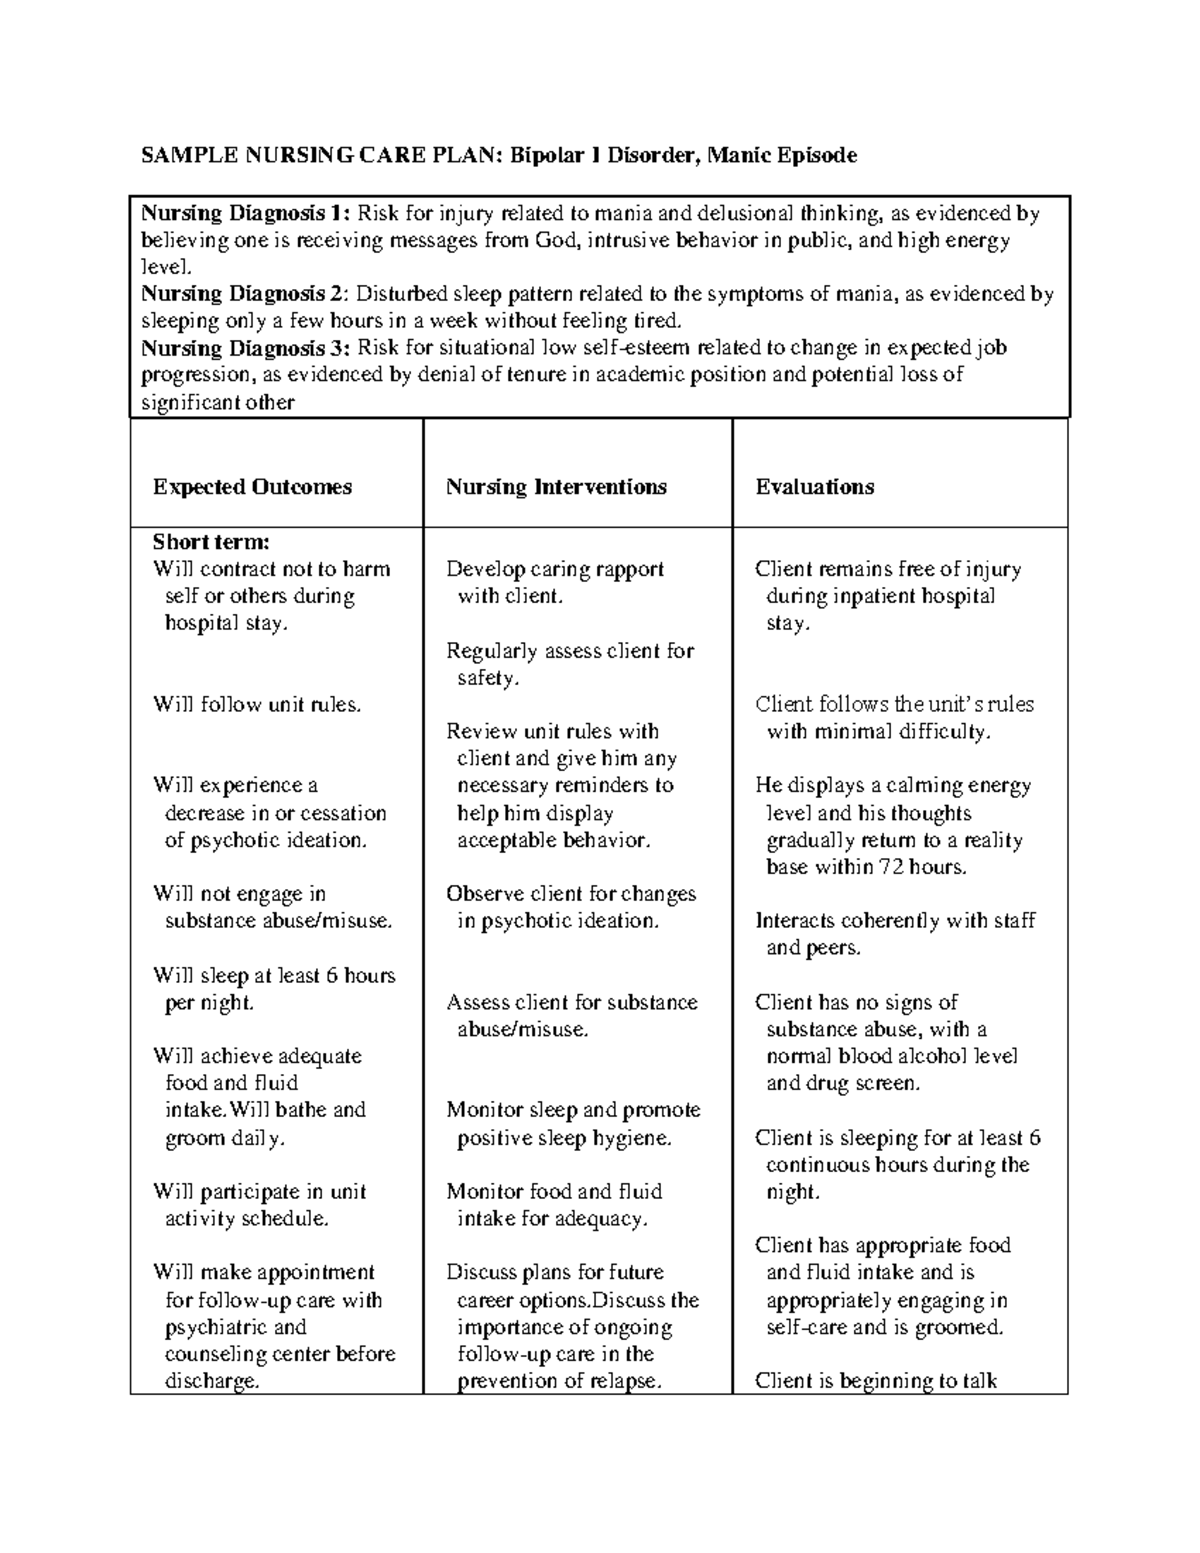
Nursing care plans for bipolar disorder are one of those things that look straightforward on paper and fall apart the moment you try to apply them. I have written more of these than I care to count, and the ones that actually help are the ones that account for the unpredictable swings between mania, depression, and everything in between. The problem most nurses run into is that they write care plans for the textbook version of bipolar disorder, not the patient sitting in front of them. A proper care plan needs to address at least three distinct phases because a patient can shift from manic to depressive in a matter of days, sometimes within the same shift. When I was working in the acute psych unit, we had a patient who presented with severe mania, got stabilized on lithium and valproate, and then crashed into a melanchoic depressive episode by day four. Our care plan from admission was completely useless by that point because it had only addressed the manic presentation. We spent the next three days rewriting it. That is exactly why rigid, one-size-fits-all templates fail so often. The essential components break down into diagnosis, objectives, interventions, and evaluation, but the real work is in the specificity. A NANDA diagnosis like Risk for Self-Harm is not enough on its own. You need to specify the context, the patient's current protective factors, the access to means, and the monitoring interval. I used to see care plans that listed Imbalanced Nutrition: Less Than Body Requirements for a manic patient without specifying caloric targets or a feeding schedule. That is a diagnosis that sounds professional but does nothing for the patient. The intervention side is where most plans go wrong because they stay vague. Instead of encourage oral intake, you write offer high-calorie finger foods every two hours during waking period and document intake hourly. That tells someone exactly what to do at 3 AM when they are working a solo night shift.
Physiological monitoring is non-negotiable for patients on mood stabilizers. Lithium requires trough level checks, thyroid function tests, and renal panels at regular intervals. Valproate needs LFTs and platelet counts. Carbamazepine requires CBC with differential. These are not optional additions to the care plan. They are central to it. I had a case where a patient on carbamazepine developed agranulocytosis because the care plan did not specify weekly CBC monitoring for the first month. The infection that followed nearly killed them. That is a failure of the care plan, not just the medication management.
Common Pitfalls and What I Changed
One thing that catches people off guard is the interaction between bipolar disorder care and medical comorbidities. Patients with bipolar disorder have disproportionately high rates of metabolic syndrome, cardiovascular disease, and diabetes. Atypical antipsychotics like olanzapine and quetiapine worsen all of these. A care plan that ignores weight, blood glucose, and lipid monitoring is incomplete regardless of how well it addresses the psychiatric symptoms. I started adding metabolic tracking as a mandatory section for any bipolar patient admitted with a new antipsychotic prescription. Baseline and monthly checks for the first six months. It adds maybe twenty minutes to the initial assessment but prevents catastrophic outcomes down the line. Another pitfall is the assumption that patients will comply with medication during a manic episode. They will not. The care plan needs to account for this through behavioral interventions and potentially legal frameworks depending on jurisdiction. Involuntary treatment orders, assisted medication administration, and de-escalation protocols are all relevant sections. I learned this the hard way when a patient refused oral lithium during a manic surge, hid it in their cheek, and then vomited it up when no one was watching. The care plan had assumed compliance. The workaround was switching to a long-acting injectable formulation where clinically appropriate and adding explicit refusal documentation procedures. Sleep disruption is both a symptom and a trigger in bipolar disorder. It deserves a dedicated section in the care plan with concrete sleep hygiene interventions, not just a generic note about promoting rest. This includes environmental modifications like reducing noise and light, establishing a consistent bedtime routine, timing of stimulant medications, and monitoring for signs of decreased sleep need as an early warning sign of relapse. Sleep is the canary in the coal mine for manic relapse and I treat it with the same seriousness as vital sign monitoring.
Get the Full Details

Practical Framework for Building the Plan
Start with a thorough biopsychosocial assessment. You cannot write an effective care plan without understanding the patient's substance use history, medication adherence patterns, family support system, and previous treatment responses. A patient who has failed three different mood stabilizers needs a fundamentally different care plan than one who has never been medicated. Include collateral information from family members when possible and document any gaps in the history. Priority nursing diagnoses should be ranked by acuity and risk. Safety concerns always come first. Risk for injury, risk for self-harm, and risk for other-directed aggression take precedence over social isolation or disturbed thought processes even though those are important. Once the immediate safety issues are addressed, move to nutritional status, sleep-wake pattern disturbance, and ineffective health maintenance. The order matters because it determines what gets documented and prioritized during handoff. Evaluation criteria need to be measurable and time-bound. Patient will verbalize understanding of medication regimen is not a valid outcome measure because it says nothing about actual behavior change. Patient will demonstrate correct medication administration technique and identify three side effects requiring immediate provider notification within 48 hours is measurable and verifiable. I used to write outcome statements that were impossible to evaluate objectively. Switching to observable and measurable criteria cut down the evaluation discussion time during case conferences significantly and made it easier to justify continued hospitalization or recommend step-down placement.
When the Standard Approach Fails
There are scenarios where a traditional nursing care plan is insufficient. Patients with treatment-resistant bipolar disorder, those with co-occurring personality disorders, or individuals who are actively psychotic need a multidisciplinary approach that goes beyond standard nursing interventions. Electroconvulsive therapy considerations, intensive outpatient program transitions, and peer support specialist involvement are areas where nursing care plans often lack guidance. I recommend supplementing the nursing care plan with a documented treatment resistance assessment and a clear transition pathway rather than trying to make the care plan do everything it was never designed to do. The care plan is a living document, not a form to complete and file. It needs revision at least once per shift for acutely unstable patients and after any significant clinical event such as a medication change, a behavioral crisis, or a new medical diagnosis. I stopped treating care plans as administrative checkboxes about five years into my career and started viewing them as communication tools between shifts. That mindset shift improved the quality of my documentation and the continuity of care my patients received.