How Bone Age Assessment Actually Works in Practice
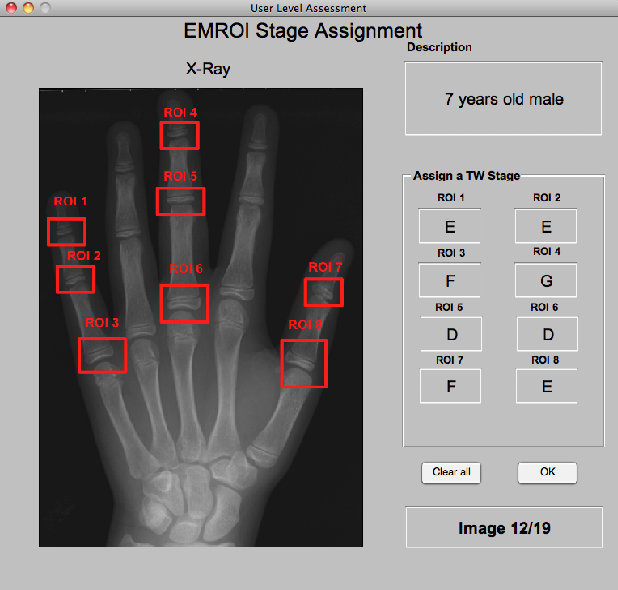
People coming into this usually want a tool that takes a wrist X-ray and spits out a number. The reality is messier than that. I work in pediatric endocrinology imaging and I've spent years doing this by hand and running software against it, and the gap between the two is where most errors come from. Before we talk about any calculator, you need to understand what we're actually looking at. The standard technique is the Greulich and Pyle atlas method, sometimes the Tanner-Whitehouse 3 (TW3) approach. Greulich and Pyle is visual comparison—hold the X-ray next to reference plates and pick the closest match. TW3 scores individual bones. The calculator tools you find online usually implement a variant of the TW3 scoring system or attempt automated landmark detection. Most of them focus on the distal radius, ulna, and carpal bones in the left wrist because that's the standardized region.
Bone Age Calculator X Ray: What You Actually Get
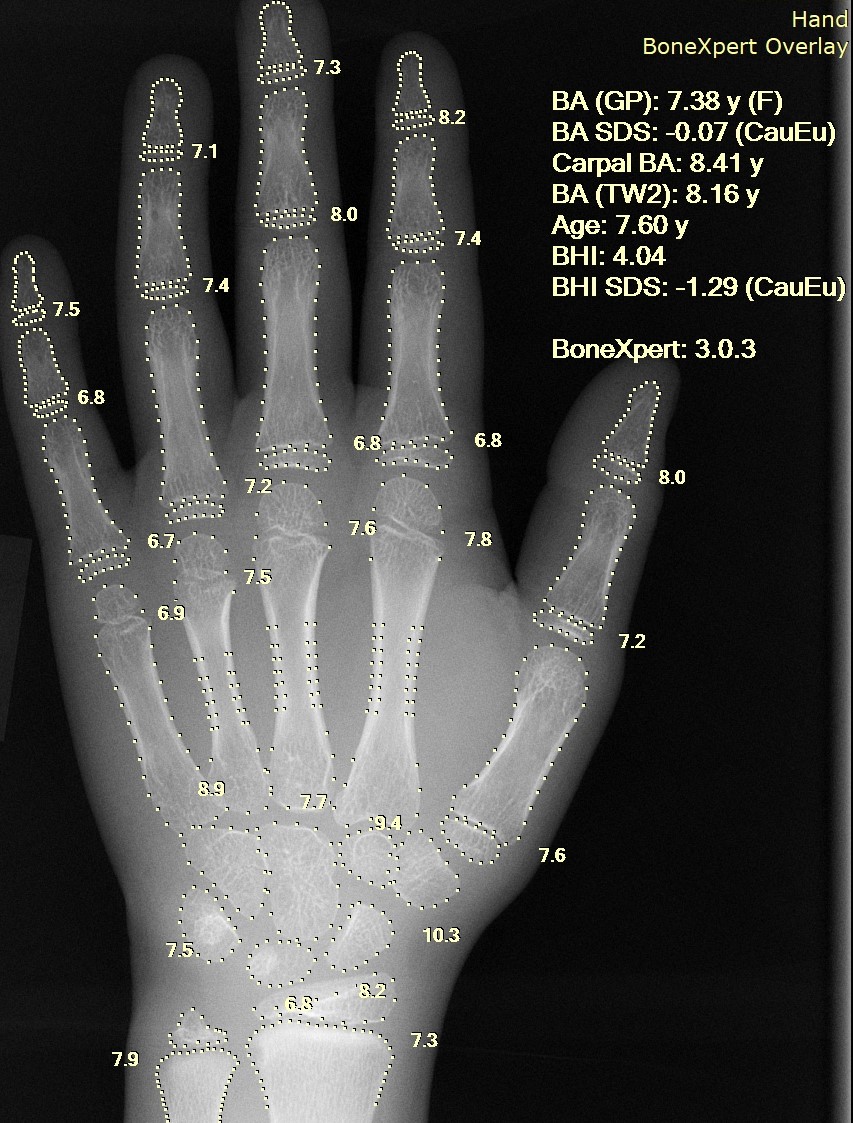
Here's the practical breakdown. Upload a properly positioned PA (posteroanterior) wrist radiograph, the software attempts to identify ossification centers, and it generates a predicted bone age. Some tools give you a single number. Better ones give you a confidence range and show which bones were actually scored. The worst ones give you a precise-looking number with zero transparency about what went into it. I recently had a case that exposed how brittle a lot of these systems are. A 13-year-old female with Turner syndrome, chronic growth hormone therapy, and a history of radial dysplasia. The automatic Bone Age Calculator X Ray output gave a bone age of 11 years and 2 months. Visually, that felt wrong. The carpal bones were there but the scaphoid and lunate had that irregular, chunky appearance typical of delayed maturation, while the distal radial epiphysis looked more mature than the overall picture suggested. I pulled the manual Greulich and Pyle plates and scored it at approximately 9 years. That's a two-year difference, and in clinical terms, that changes everything about treatment decisions. The fix was straightforward but labor-intensive. I traced the ossification centers manually on the PACS workstation and applied the TW3 scoring by hand. The algorithm had confused the fragmented appearance of the dysplastic epiphysis with normal stage variation. What tripped it up was that the image itself was borderline quality—slight rotation and the hand wasn't fully pronated, which shifts the carpal overlap pattern in a way that throws off automated detection.
What the Tools Do Well and Where They Break
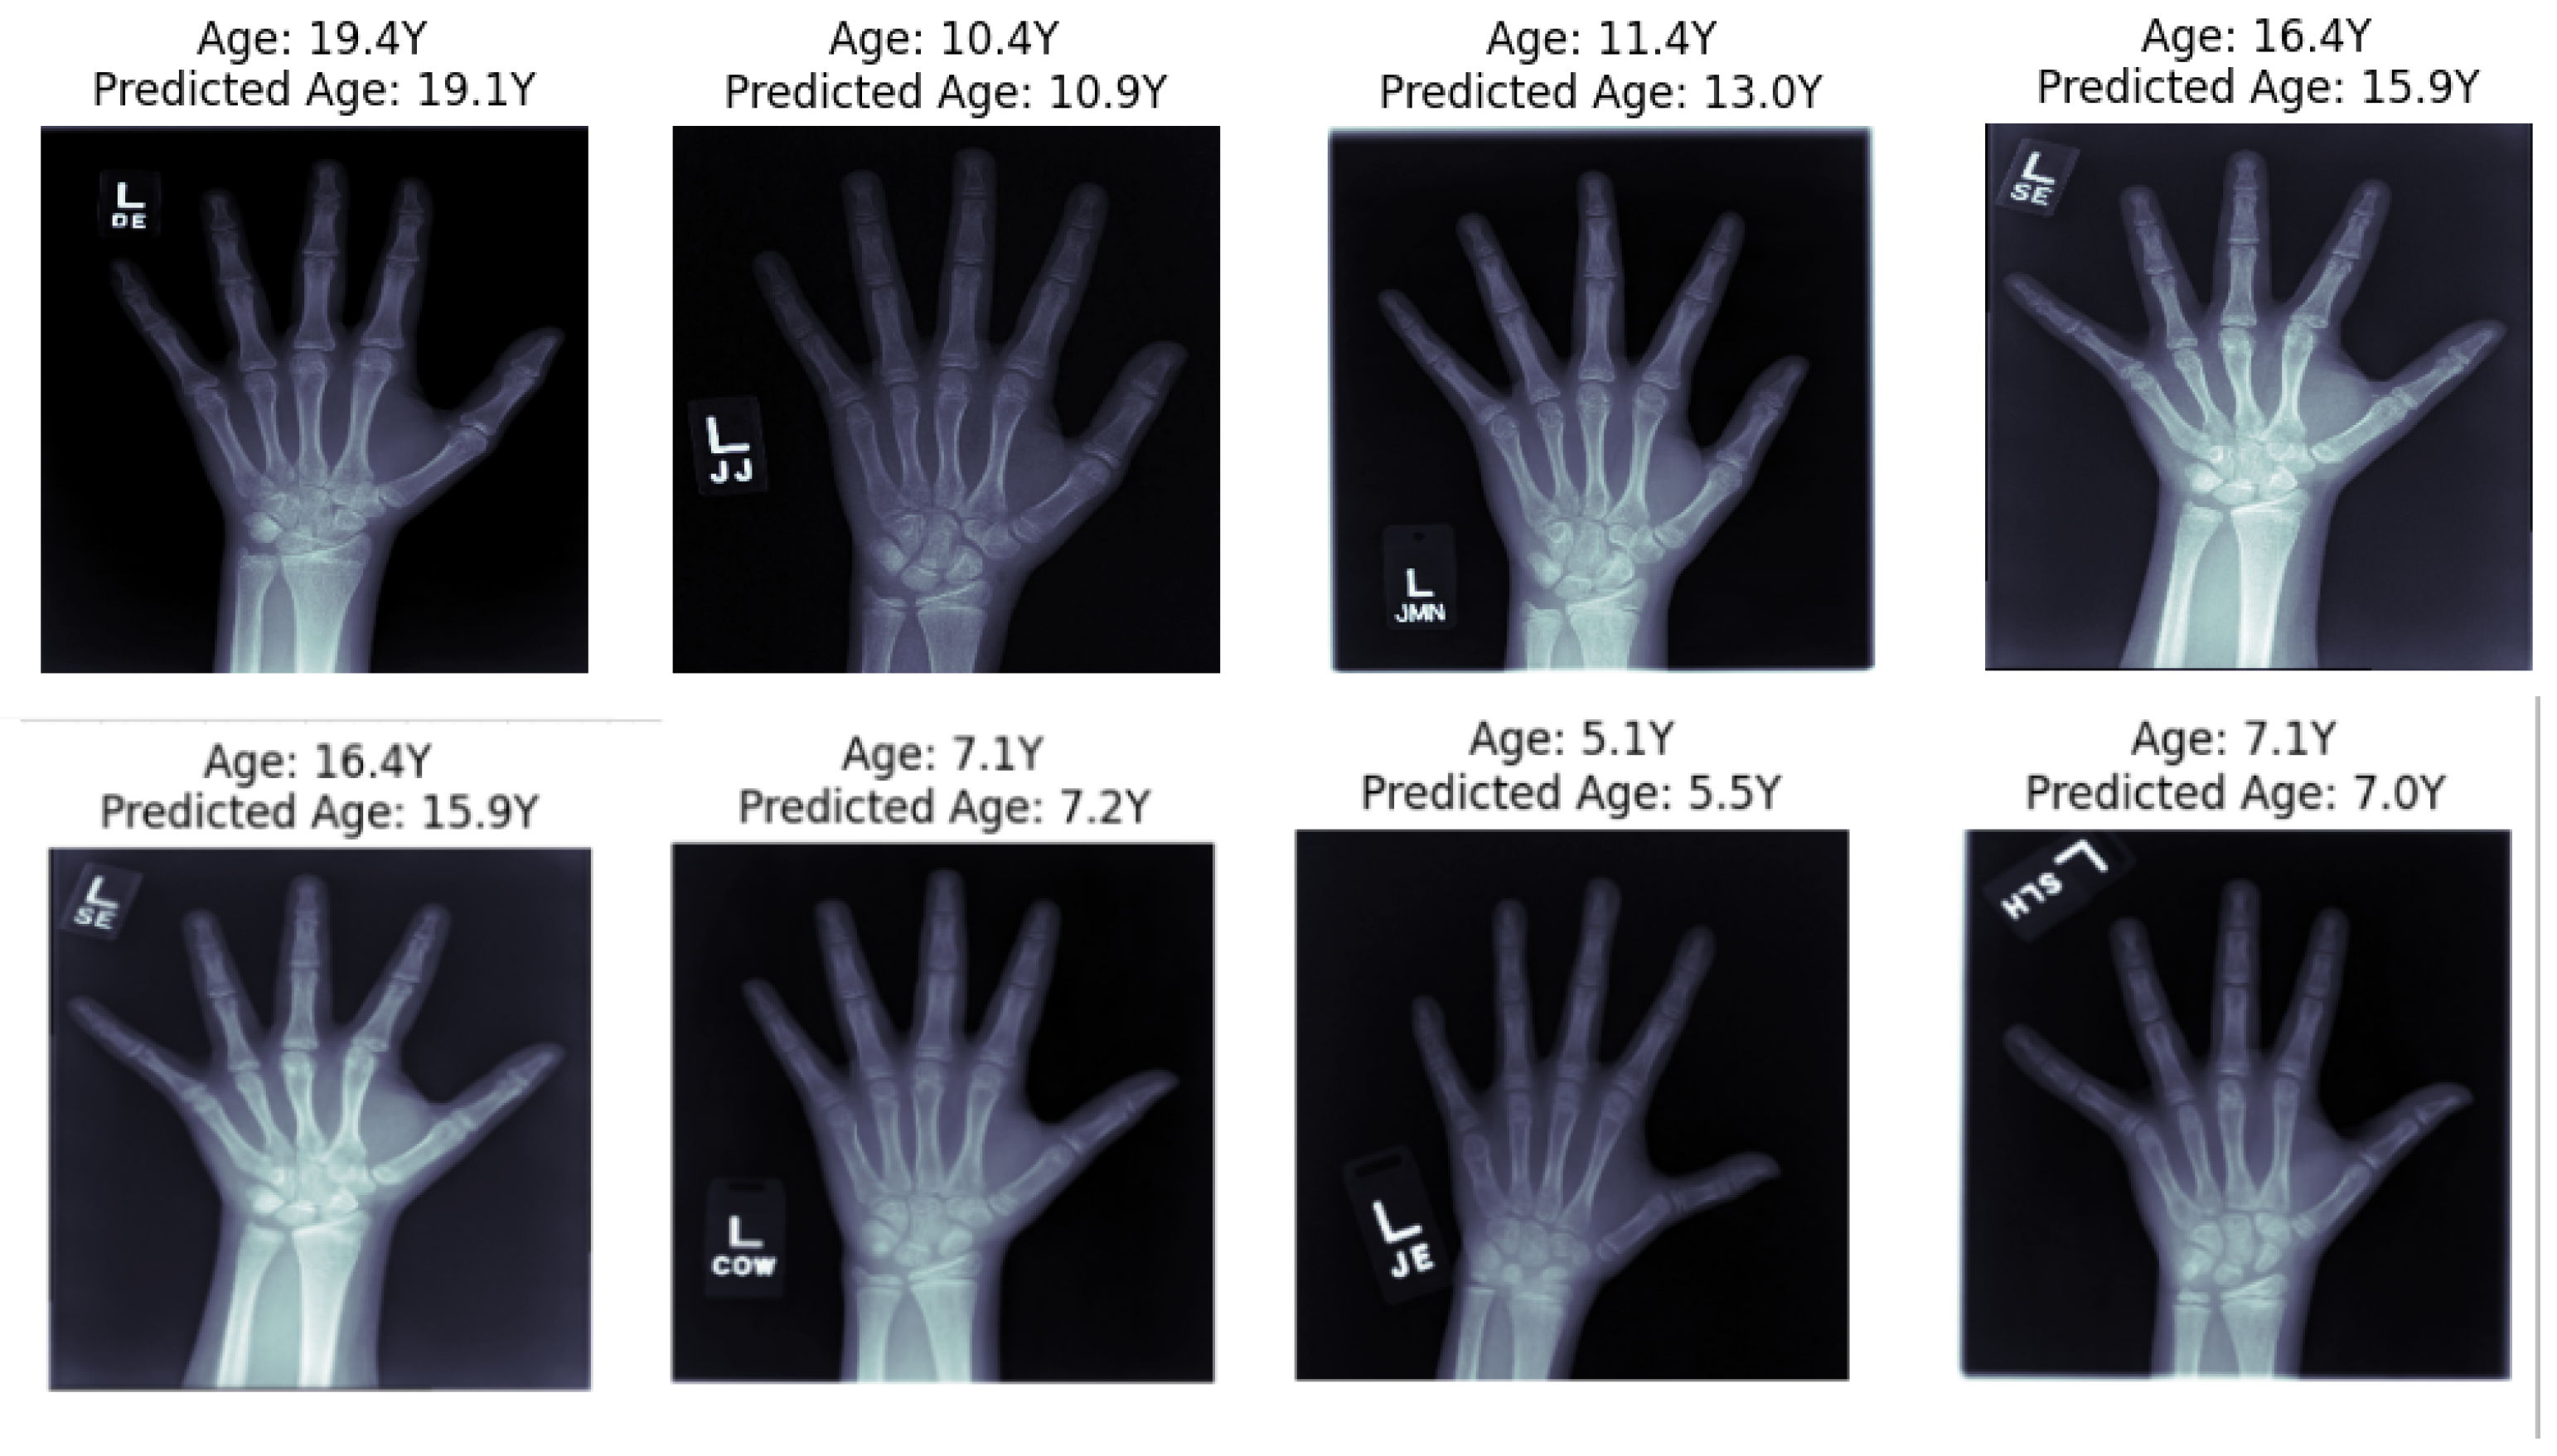
Automated calculators have gotten significantly better over the last three years. Deep learning models trained on large pediatric datasets can now identify the major ossification centers in well-positioned images with reasonable accuracy. For a typical prepubertal child with no skeletal abnormalities, the automated bone age usually lands within six to twelve months of a trained reader. That's clinically acceptable for screening and monitoring. Where they consistently underperform is in any population outside the training distribution. And I mean that literally. The models are trained heavily on Caucasian pediatric populations. When I run a Bone Age Calculator X Ray on a child of African or South Asian descent, the systematic bias shifts the result by roughly four to eight months in either direction depending on the tool. It's a known limitation in the literature and the developers mostly acknowledge it in small print. Another failure mode that nobody warns you about: recent fractures. If a child has broken their wrist in the last three to six months, the healing callus and remodeled bone look like advanced ossification. The algorithm reads it as accelerated skeletal maturity. I've seen cases where a fractured wrist was misread as two years ahead of chronological age. The workaround is to image the contralateral side if possible, or go back to manual atlas comparison where you can visually discount the trauma site.
Get the Full Details

Setting Up a Proper Workflow
If you're a clinician considering this for your practice, start with the basics of image quality before you even think about the software. A good wrist radiograph has the fingers slightly spread, the thumb externally rotated so the epicondyles are superimposed, and the hand flat without dorsiflexion. If the technologist gets that wrong, no calculator in the world will save you. I've seen images where the ulnar styloid process is completely obscured by positioning and the automated system flagged it as absent—that alone drops the bone age by months. For the actual process, I recommend running the automated tool first and then independently reviewing every result. Don't accept the output blindly. Check that the software identified the correct bones. Look at the carpal arrangement. Verify the radial and ulnar epiphyseal widths match what you'd expect. This adds about ninety seconds to a two-minute automated read, and it catches the vast majority of errors. If you need a specific recommendation, the open-source approaches based on MONAI or TensorFlow Health have been the most transparent for clinical use. Commercial platforms like EndoPoll and BoneXpert are more polished but cost is a factor and you lose interpretability. For teaching purposes, nothing beats working through the Greulich and Pyle atlas yourself for the first hundred cases. It builds an internal reference that no calculator replaces.
The biggest thing I want people to understand is that bone age is a clinical tool, not a measurement with physical precision. It estimates skeletal maturity from a two-dimensional projection of complex three-dimensional anatomy. The numbers mean something in aggregate across populations, but any single reading has a margin of error that professionals routinely understate. When you present a bone age result, giving a range rather than a point estimate is more honest and more useful than the calculators make it seem.