Understanding Neurons and Their Supporting Infrastructure
Brain cells exist in two primary categories: neurons and glial cells. Neurons handle electrical and chemical signaling. Glial cells handle structural support, metabolism, insulation, and waste clearance. The ratio is roughly one neuron to one glial cell in most brain regions, though certain areas like the cerebellum have significantly more glial support. The commonly cited figure of 100 billion neurons is inaccurate. The actual number is closer to 86 billion, according to work by Suzana Herculano-Houzel's team using isotropic fractionation. A neuron receives input through its dendrites. The signals summate at the soma. If the membrane potential crosses threshold, an action potential fires down the axon. At the axon terminals, calcium influx triggers vesicle release. Neurotransmitters cross the synapse and bind to receptors on the next cell. This is the basic mechanism repeated across roughly 100 trillion synapses in a human brain. The process takes milliseconds. Myelination speeds conduction velocity from about 0.5 meters per second in unmyelinated fibers to up to 120 meters per second in heavily myelinated ones. Glia are not just fillers. Astrocytes regulate the extracellular ion environment, clear glutamate from synapses, supply lactate to active neurons, and participate in the blood-brain barrier. Oligodendrocytes produce myelin in the CNS. Microglia act as resident immune cells, performing surveillance and phagocytosis. Recent studies show they also prune synapses during development through the complement cascade. You cannot ignore glia if you want to understand how brain tissue actually functions.
Practical Considerations for Working With Neural Tissue
If you are recording from brain tissue, the first thing you will notice is that signal quality depends heavily on preparation. Acute slices maintain reasonable physiology for about 4 to 6 hours in artificial cerebrospinal fluid at 32 to 34 degrees Celsius. Beyond that, metabolic waste accumulates and synaptic function degrades. Chronic implants introduce a glial scar within weeks. The scar tissue encapsulates the electrode and increases impedance. Signal amplitude drops. You will see this in your recordings as a progressive loss of single-unit isolations. I ran into a specific issue a few years back working with penetrating Utah arrays in rodent cortex. After about three weeks, the LFP amplitude in the affected channels dropped by roughly 60 percent, and the signal-to-noise ratio for spike sorting became unreliable. The standard workaround was to switch to a higher-impedance coating on the shanks and adjust the recording thresholds upward. It did not fully restore the lost units, but it stabilized whatever signal remained. Nothing you do will prevent glial encapsulation entirely. The tissue responds to any foreign object.
Common Misconceptions and Technical Pitfalls
The idea that we only use 10 percent of our brains is entirely fabricated. Imaging studies show widespread activation even during simple tasks. Another persistent myth is that neurogenesis stops after development. It does not. Adult neurogenesis occurs in the subgranular zone of the dentate gyrus and the subventricular zone. The rate declines with age, but the process continues throughout life in healthy individuals. The functional significance of newly generated neurons in adults remains debated, though there is decent evidence for their role in pattern separation within the hippocampus. A more practical concern for anyone working with neural data is volume conduction. When you place an electrode, you are picking up signals from nearby neurons, not just the one right next to the tip. Spike sorting algorithms attempt to separate these overlapping waveforms, but they are not perfect. Incorrect sorting introduces false positives. I have seen papers where claimed "selective" neural responses turned out to be artifacts of poor cluster isolation. Always report your clustering metrics. If your isolation distance is below 1.7 or your L-ratio is above 0.05, treat your single-unit claims with skepticism. The blood-brain barrier is another area where intuition fails. It is not a uniform wall. Certain regions like the circumventricular organs lack a tight barrier to allow chemical sensing. Drug delivery strategies that work systemically often fail because the barrier excludes molecules larger than about 500 Daltons and those that are not lipophilic. Convection-enhanced delivery and focused ultrasound with microbubbles are workarounds, but both carry risk. Focused ultrasound can cause temporary barrier opening lasting several hours, but repeated exposure may lead to cumulative damage.
Get the Full Details
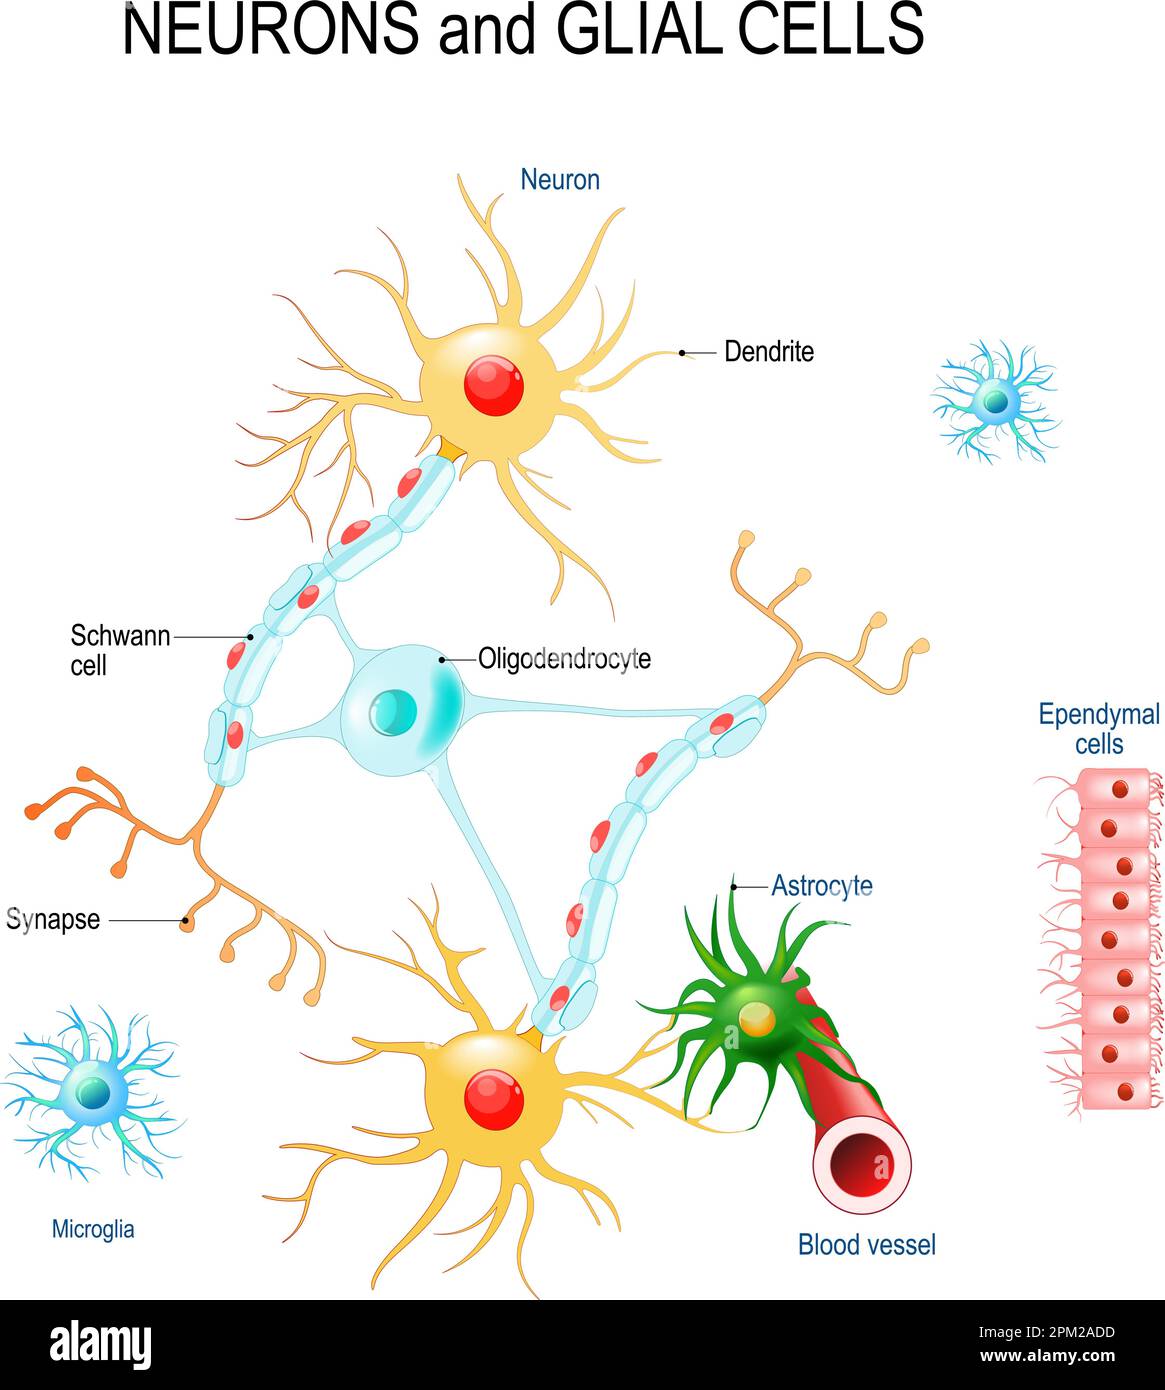
Structural Organization and Regional Differences
Cortical layers follow a consistent six-layer architecture in the neocortex. Layer 4 receives thalamic input. Layers 2 and 3 handle intracortical communication. Layer 5 projects to subcortical structures. Layer 6 feeds back to the thalamus. This laminar organization is disrupted in the agranular cortex of motor areas where layer 4 is reduced. The hippocampus has a trisynaptic circuit: dentate gyrus to CA3 via mossy fibers, CA3 to CA1 via Schaffer collaterals, and CA1 to the subiculum. Disruption at any point changes the output. Seizure propagation often follows these pathways. White matter tracts connect regional gray matter. The corpus callosum contains roughly 200 million axons per hemisphere in humans. The internal capsule carries motor and sensory fibers between the cortex and brainstem. Damage to these tracts causes disconnection syndromes. Split-brain patients studied by Sperry and Gazzaniga demonstrated that information presented to one hemisphere does not automatically reach the other without the connecting pathway. Language processing is typically lateralized to the left hemisphere in right-handed individuals, but this is a statistical tendency, not an absolute rule.
Methodological Notes for Researchers
If you are doing electrophysiology, the choice between in vivo and in vitro recording shapes your conclusions. In vivo recordings capture behaviorally relevant activity but introduce motion artifacts, anesthesia effects, and recording drift. In vitro slice recordings offer controlled conditions but lack the network context present in a living animal. Both approaches have value. The key is matching your method to your question. Calcium imaging provides population-level data at the cost of temporal resolution. GCaMP signals reflect spiking activity with a delay of roughly 100 to 200 milliseconds and a decay time constant of several hundred milliseconds. You can infer spike timing with deconvolution algorithms, but the estimates become unreliable at high firing rates above 20 to 30 Hz. For precise timing questions, stick to electrical recording. For population dynamics across hundreds of cells, imaging is more practical. Pharmacology in brain tissue has its own complications. Drug diffusion through brain slices is slower than through solution. A 300-micrometer slice may take 30 to 60 minutes to reach steady-state drug concentration depending on the molecule's lipophilicity and molecular weight. Never assume rapid equilibration. Perfuse long enough and verify with control experiments. Systemic administration in vivo adds another variable because of pharmacokinetics, blood-brain barrier penetration, and off-target effects. Local microinjection using osmotic pumps or direct infusion reduces systemic exposure but causes tissue displacement and localized toxicity at high concentrations.
Brain Cells In Brain: Key Takeaways for Practical Work
The fundamental unit is the neuron-glial ensemble, not the neuron alone. Glial cells modulate synaptic transmission, regulate blood flow, and maintain homeostasis. Any model of brain function that excludes glia is incomplete. Signal quality in recordings degrades over time due to biological responses to implants. Plan your experimental timeline accordingly. Spike sorting requires validation. Publish your isolation metrics. Do not claim single-unit precision without supporting data. The brain is regionally specialized but highly interconnected. Damage or dysfunction in one area propagates through network connections. Localized interventions rarely stay local. The blood-brain barrier is selective but not absolute. Drug design must account for molecular properties and regional variations in permeability. Method selection should match the spatial and temporal scale of your question. No single technique captures everything.