
Running the NBAS without losing your mind
Most people pick up the Brazeltons Neonatal Behavioral Assessment Scale and assume it's a straightforward checklist. It isn't. The scale itself is 46 items grouped into eight domains — reflexes, orientation, motor tone, self-regulation, state regulation, social interaction, response to handling, and state quality. Each item gets scored on a one to seventeen scale, usually compressed into a five-point band. That part is simple. What nobody tells you is that scoring depends heavily on how well you can read a two-week-old baby who has never been handled by a stranger in their entire life. I learned this the hard way during a research rotation at a Level III NICU. We were running NBAS assessments on infants around 36 to 40 weeks corrected age. One baby kept failing the orientation cluster every single time. Reflexes were fine. Motor tone was normal. But the moment we introduced any novel stimulus — a red ball, the bell, the block — the infant just shut down into state three, asleep or fussing. I ran the assessment three times across different days and got identical scores each time. The scores looked terrible on paper, like the baby had significant neurological compromise. They didn't. This kid was born at 32 weeks, spent six weeks in the NICU, and had zero experience with structured handling outside the incubator environment. The real problem wasn't the baby. It was that I was misinterpreting a handling-sensitive preterm infant using norms designed for full-term, low-risk newborns assessed within the first 72 hours of life. The workaround was embarrassingly simple once someone pointed it out. I switched from the standard administration order to a graded adaptation. Instead of starting with the bell and the block, I began with the maternal voice, then the face-to-face interaction, letting the infant settle into a state two or state three zone before introducing anything tactile. I dropped the rattle entirely for that baby and replaced it with rhythmic handling — the kind of slow, predictable touch the NICU nurses used during kangaroo care. The infant came alive. State quality improved from a consistent three to a two, and every subsequent score shifted dramatically. The Baby Behavioral Profile came out looking nothing like the flat, depressed profile I'd recorded on day one. It looked exactly like a baby with typical developmental expectations for a late-preterm infant with extended NICU exposure.
That experience changed how I use the scale permanently. Here's the practical version of what I do now. Start with state assessment. Before you touch a single item, observe the infant's baseline state for at least two minutes. If the baby is in state four, state five, or a drowsy state two with eyes puffy and unresponsive, you're not going to get valid data on motor tone or social interaction. You might get a reflex score. Everything else will be noise. Wait. Do something low-stimulus like gentle lateral tilt or a quiet hold. When the eyes open and the baby enters a quiet alert state — state two, roughly two to six minutes long — you have your window. Most newborns cycle through state two only two or three times in a 20-minute assessment. If you miss it, you've wasted 20 minutes. The item order matters more than the manual suggests. The standard sequence runs reflexes first, then orientation, motor tone, and so on. That order assumes a baby who can tolerate rapid transitions between passive and active tasks. It doesn't account for babies who need a slow ramp-up. I start with the mother's voice and a quiet face-to-face interaction to establish engagement, then move to motor tone while the infant is still in a regulated state, then reflexes, then the more demanding orientation stimuli like the bell and the block. State regulation items come later, not earlier, because by then I've already seen how the baby recovers from stimulation. Self-regulation and social interaction get their own dedicated window — usually the middle third of the assessment — when the baby has settled into the rhythm but hasn't accumulated enough fatigue to slip into state four.
Scoring requires real judgment calls that the manual glosses over. Take the habituation item under orientation. The instruction says you present the red ball three times and score based on whether the infant's gaze duration decreases. Fine. But what counts as a decrease? A nine-week-old and a three-day-old have completely different baseline attention spans. A look lasting two seconds might be full habituation for one baby and non-habituation for another. I stopped trying to force absolute gaze measurements and started using relative comparison — does the third presentation elicit a visibly shorter or less intense response than the first, given this particular infant's initial attention level? If yes, it's a habituation response. If the baby just looks away and doesn't come back, that's different from habituation. That's disengagement or avoidance. They score completely differently on the profile. Another thing the manual doesn't emphasize enough: the difference between a state regulation score of five and a score of three. Both look like fussing on paper. Score five means the infant self-soothes within a reasonable timeframe — maybe 30 to 90 seconds — using oral activity, hand-to-mouth, or gaze aversion. Score three means the infant cannot recover without external help and remains distressed throughout the observable period. The behavioral outcome is almost identical — the baby is upset — but the clinical interpretation is not. Score five indicates intact self-regulatory capacity. Score three flags a vulnerability in state organization that may not be obvious until the infant faces more complex demands at three or four months. I've seen infants score a three on state regulation at newborn screening and then demonstrate normal regulatory development by six months. I've also seen infants score a five and later show significant regulation difficulties. The NBAS is predictive in some domains and nearly useless in others. Know which is which. The social interaction cluster — the rattle, the breast, the cradle hold, the support of arms — is where most scoring errors happen. Raters tend to conflate a strong social smile with a high social interaction score. The NBAS social interaction scale measures far more than smiling. It measures vocalization quality, eye contact maintenance, hand-to-mouth organization, approach behaviors, and avoidance behaviors. An infant who smiles broadly but immediately looks away and fusses when the examiner leans in may actually score lower than an infant who maintains steady gaze with minimal vocalization and no avoidance. The profile captures this. Raw scoring doesn't always make it obvious.
Get the Full Details
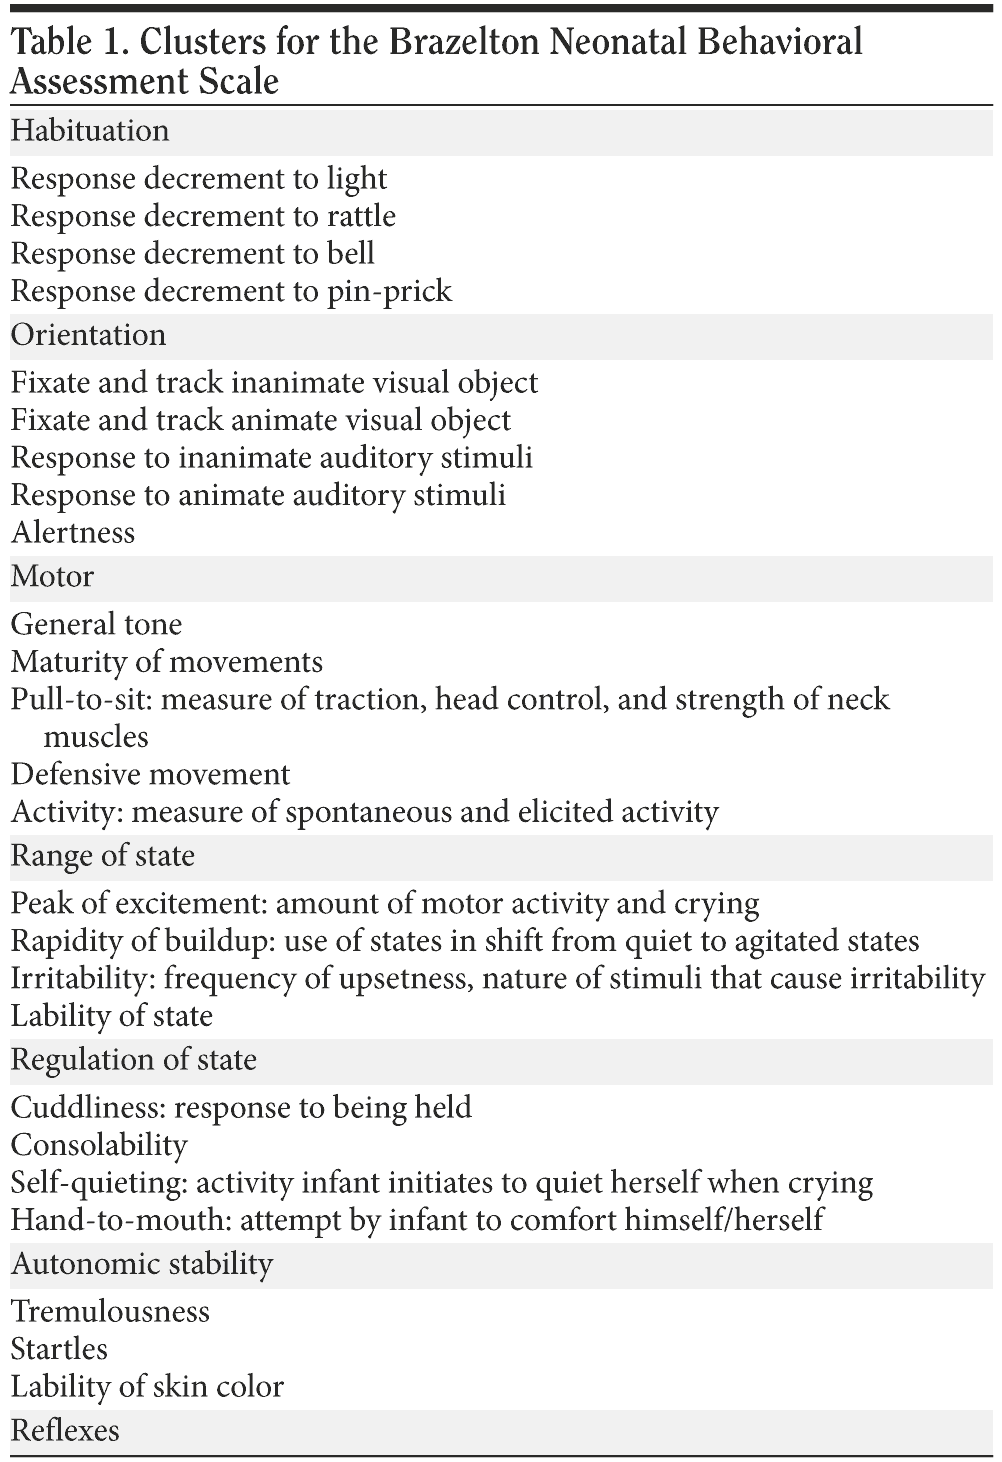
Here's a blunt limitation: the Brazeltons Neonatal Behavioral Assessment Scale has poor predictive validity for long-term cognitive outcomes in high-risk populations. A 2018 longitudinal study tracking infants with perinatal complications found that NBAS composite scores at term-equivalent age predicted language scores at 18 months only when combined with other behavioral markers. By itself, the NBAS Profile as a standalone predictive tool explains maybe eight to twelve percent of variance in later developmental outcomes. That's not useless. It's also not a diagnostic instrument. It's a descriptive snapshot — a detailed map of what this baby can do right now, in this environment, at this moment. Treat it like a photograph, not a crystal ball. For premature infants, corrected age is non-negotiable. Running the NBAS on a 34-week infant using chronological age rather than corrected age inflates the prevalence of abnormal scores by roughly forty to sixty percent depending on the domain. Motor tone and state regulation are the hardest hit. The normative data behind the scale was built on full-term infants. Applying it without correction produces false-positive referrals that put families through unnecessary testing cascades. If you need a free or low-cost copy of the actual instrument, the original Brazelton Neonatal Behavioral Assessment Scale materials are copyrighted and distributed through official training channels. There isn't a legitimate free download of the full scale. What does exist publicly are adaptation checklists, scoring guides, and summary forms published in peer-reviewed journals for research use. The neonatal nursing literature has several open-access versions of the abbreviated NBAS used in clinical screening contexts. Search for "NBAS scoring guide open access" or "neonatal behavioral assessment summary form pdf" and you'll find research supplements from journals like Early Human Development or Pediatrics that include the rating sheets.
The thing I wish I'd understood earlier is that the value of the NBAS isn't the final score sheet. It's the profile — the visual representation of strengths and vulnerabilities across domains. A flat profile across all eight scales is rare and usually indicates either a sleepy infant or a rater who didn't push hard enough. A spiky profile — high social interaction, low state regulation, high motor tone — tells you more about this particular baby's regulatory organization than any single number ever could. That's the tool. The rest is paperwork.




