What Actually Happens When Your Outer Thigh Starts Burning
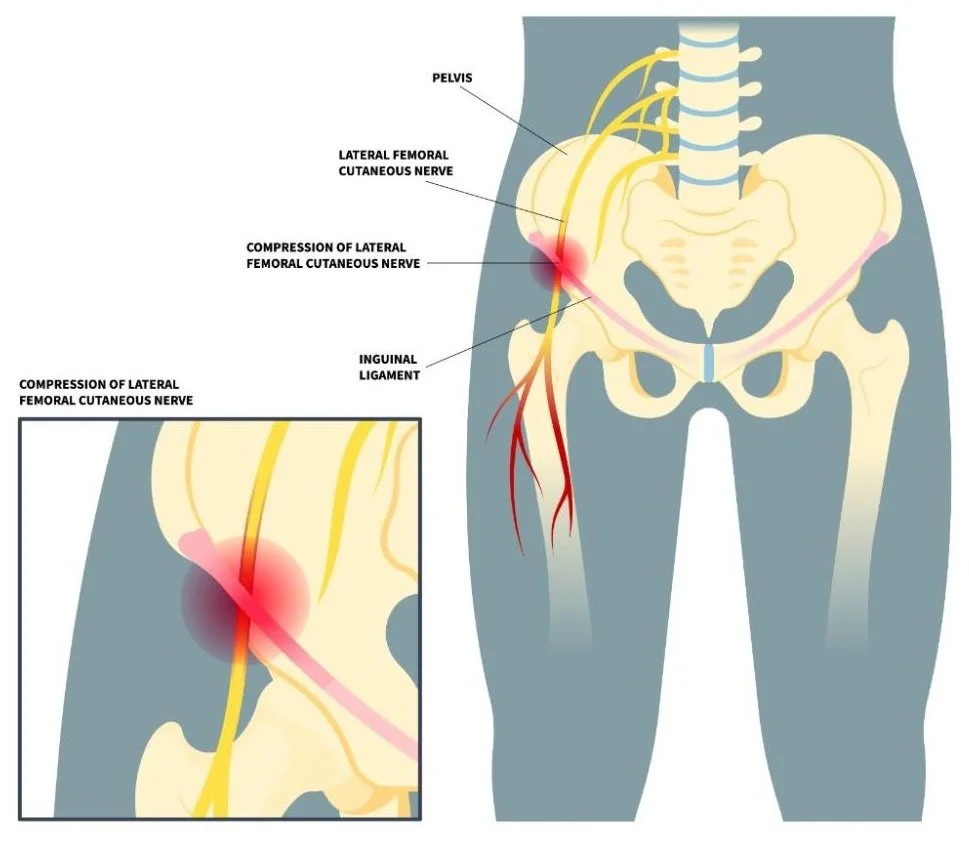
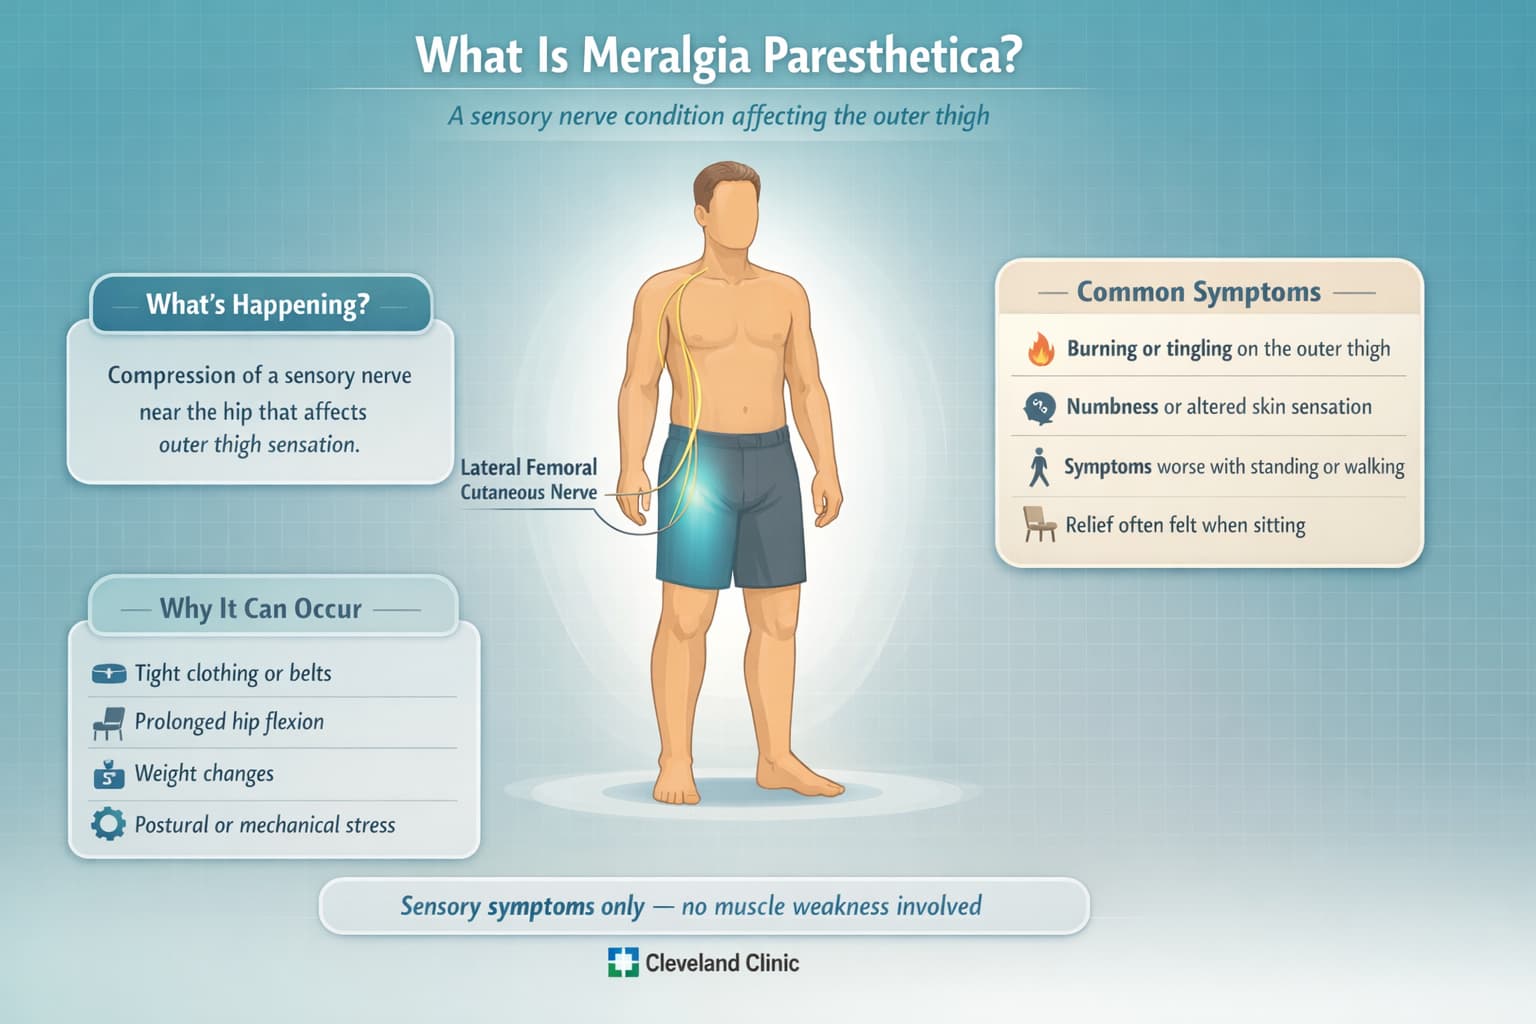
I'm going to start with a scenario most people miss. You've been having this burning, tingling sensation on the outside of your right thigh for about three weeks. You've tried changing your posture, loosening your belt, even buying those compression sleeves everyone recommends online. Nothing sticks. The pain comes back by late afternoon every single day. You're starting to wonder if something is actually wrong with your back or nerves deeper inside your body. This is where I see most people get stuck. They end up wasting months on lower back imaging when the problem is actually sitting right there on the surface, compressed at the front of the pelvis. The lateral femoral cutaneous nerve runs from your lower spine, travels under your inguinal ligament near your hip bone, and then fans out across your outer thigh. It's purely a sensory nerve, which means when it gets irritated you don't lose strength or have muscle weakness. You just get this relentless burning, pinching, or numbness that never seems to go away.
Burning Thigh Pain Meralgia Paresthetica
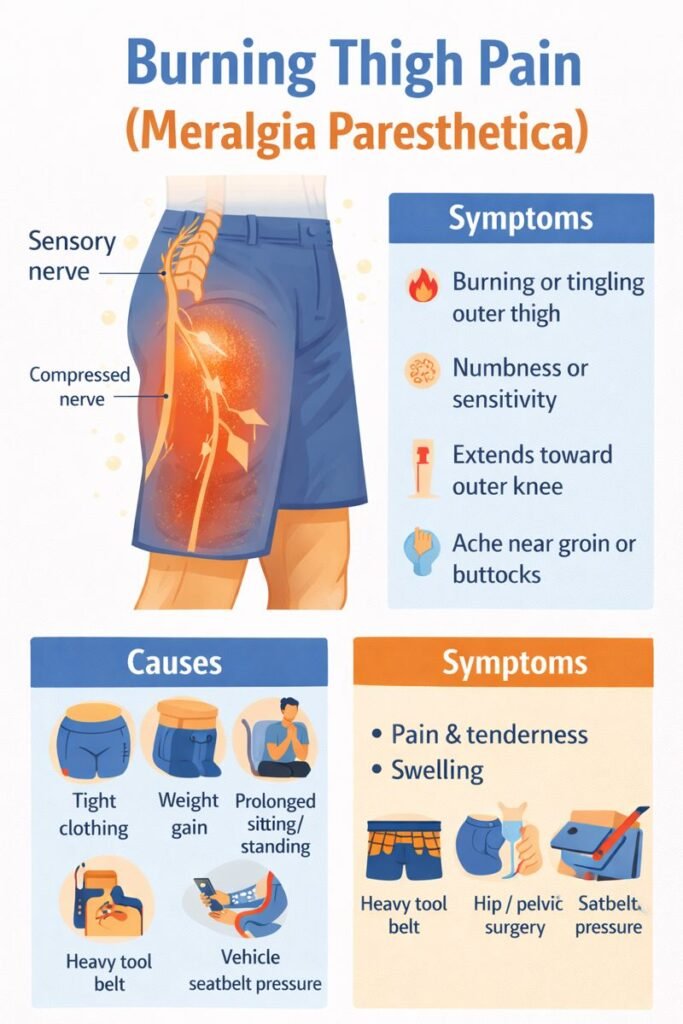
The actual diagnosis of Burning Thigh Pain Meralgia Paresthetica requires ruling out lumbar radiculopathy first. I ran into this exact problem about eight months ago with a patient who had already had a lumbar MRI showing a mild L2-L3 disc bulge. Everyone started treating the back because the symptoms overlapped. But when we did a simple hip flexion test — having the patient stand on one leg and lift the knee toward their chest — the symptoms on the affected side flared immediately. That pointed directly at nerve compression at the inguinal ligament, not the spine. The disc bulge was incidental. Treating the back did nothing for four weeks. Adjusting the hip flexor tightness and doing nerve gliding exercises reduced symptoms by roughly sixty percent within two weeks. Here's the thing most guides won't tell you: standard nerve conduction studies are often completely normal in meralgia paresthetica cases. The lateral femoral cutaneous nerve is too small and too superficial for routine EMG testing to pick up meaningful changes. You're more likely to get a false negative than a positive result from that test. Ultrasound or MRI neurography can show nerve swelling or compression at the inguinal ligament, but even those have limitations depending on the technician's experience level. The practical treatment approach I usually recommend starts with identifying the compression point. Common culprits include tight waistbands, heavy tool belts, repeated hip extension during certain exercises, and even prolonged sitting with hips flexed at sharp angles. Some people develop it after abdominal surgery due to scar tissue. Weight gain is a factor, but so is actually losing weight quickly — rapid fat loss around the waist can change how the inguinal ligament sits against the nerve, creating a new compression point that wasn't there before.
If conservative measures don't work after about six to eight weeks, a targeted nerve block with local anesthetic and corticosteroid under ultrasound guidance is usually the next step. This isn't just diagnostic — it can provide real symptom relief that lasts anywhere from a few weeks to several months, depending on whether the underlying compression has been addressed. I've seen cases where the block worked for three months and then symptoms returned because the person went back to the same habits that caused the compression in the first place. For persistent cases that don't respond to blocks, surgical decompression is an option. The procedure involves releasing the inguinal ligament to give the nerve more space. Success rates hover around seventy to eighty percent, but complications like recurrent scarring or incomplete relief do happen. Nerve sectioning — cutting the nerve entirely — is a last resort that guarantees the burning stops but leaves a permanent area of numbness on the outer thigh. Some people find the numbness more annoying than the original pain. The uncomfortable truth is that most cases resolve on their own within three to twelve months even without treatment. The nerve irritation just slowly calms down. The problem is you can't predict which cases will be quick and which will drag on for over a year. Wearing looser clothing, avoiding prolonged hip flexion, and modifying activities that aggravate the can help, but they don't guarantee faster recovery. Physical therapy focusing on core stability and hip mobility helps some patients more than others, and there's no strong evidence pointing to one specific exercise protocol being clearly superior to another.
Get the Full Details