The Texas Reality for Nurse Practitioners
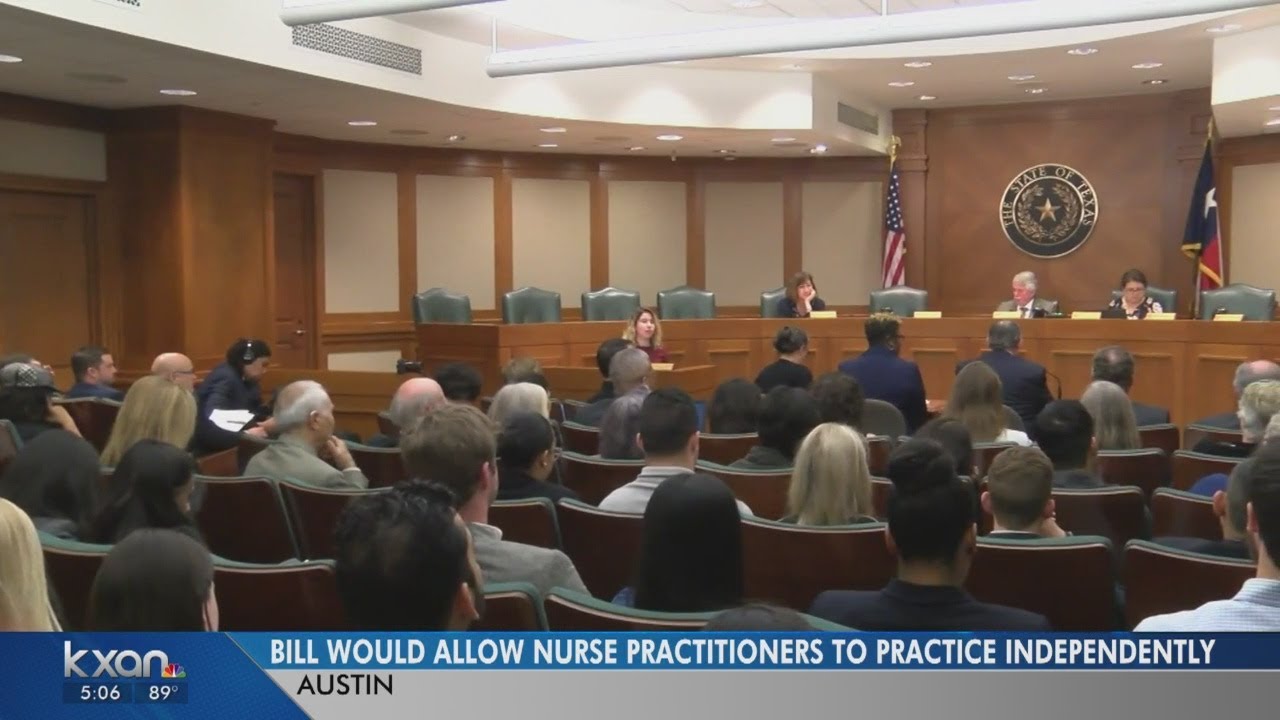
Most nurse practitioners moving into Texas quickly discover that independent practice isn't an option here. The Texas Medical Board and the Board of Nursing maintain a supervisory framework that requires a collaborative agreement with a licensed physician. It is not optional. It is not a formality you can file and forget. The supervising physician must be actively involved in your practice, and the written protocol must be maintained and renewed according to board specifications. No. Texas does not currently grant full practice authority to nurse practitioners. You will need a collaborative agreement with a physician regardless of your specialty, years of experience, or the setting in which you work. There have been multiple legislative attempts to change this over the past decade, and none have passed. The argument from opponents usually centers around patient safety and scope creep. The argument from advocates centers around healthcare access in rural areas and workforce shortages. Both sides have valid points, but neither side has shifted the law enough to change the current requirement. The type of supervision required depends on several factors. If you are practicing in a hospital or health system, the arrangement typically falls under a delegation agreement. Private practice clinics often structure things differently, using what is called a collaborative agreement instead. The distinction matters because it affects who holds clinical responsibility and how billing is structured. I learned this the hard way when I worked a locum tenens position in West Texas. The clinic had the wrong type of agreement on file, and the billing department flagged it before we completed our first week. We spent three days rewriting the entire supervisory document with legal counsel. It cost the clinic roughly eight thousand dollars in legal fees and two weeks of lost revenue while I found alternative coverage.
The written protocol must cover specific elements. It needs to address consultation procedures, referral processes, emergency care arrangements, and prescription authority boundaries. Your supervising physician must be available for consultation, though the board does not require them to be physically present at all times. The exact availability requirement varies depending on your practice setting and whether you are in a medically underserved area. Rural settings sometimes receive more flexibility, but you should verify the current standards directly with the Texas Board of Nursing because these details shift periodically.
What the Supervisory Framework Actually Requires
The Texas Nursing Practice Act outlines the requirements in detail, and the language is less forgiving than many new graduates expect. Your supervising physician must hold an active Texas medical license. They need to have a working relationship with your practice that includes regular chart reviews and quality oversight. The protocol you both sign must be on file with your employer and available for inspection. It also needs to be renewed at least every two years, or more frequently if your scope of practice changes. One thing many people miss is that the supervising physician does not need to specialize in the same area as you. A family nurse practitioner in a rural clinic can have a general practice physician as their collaborator. This creates complications though. A general practitioner may not be comfortable overseeing diabetes management protocols or psychiatric medication management. I encountered this exact issue when a clinic in East Texas tried to use a family medicine physician to supervise an adult-gerontology acute care nurse practitioner. The oversight was superficial at best, chart reviews were perfunctory, and the quality metrics suffered. The clinic eventually brought in a hospitalist as the collaborating physician, and everything improved noticeably within six months. Prescriptive authority is another area where Texas gets particular. You can prescribe controlled substances, but you need a DEA registration and a Texas controlled substance permit. The collaborative agreement must specifically address your prescribing practices. Some physicians include restrictive language in the protocol that limits your Formulary access, which effectively narrows your prescribing range below what Texas law technically allows. I recommend negotiating this explicitly during contract discussions rather than discovering limitations after you have already started working there.
Get the Full Details

Edge Cases and Workarounds That Actually Exist
There are limited scenarios where NPs in Texas operate with reduced supervision requirements. Military treatment facilities follow federal guidelines that differ from state requirements. Federally qualified health centers in rural areas sometimes negotiate modified supervision arrangements through their contracts with state programs. Indian Health Service facilities operate under federal authority. These are exceptions, not the rule, and they require specific qualifications and approvals. The most common workaround I see is the employment model. Large hospital systems in Texas often hire NPs directly and handle the supervisory framework internally. The system designates employed physicians as collaborating physicians, and the NPs fall under the organization's standing orders and protocols. This is functionally closer to independent practice because the administrative burden of maintaining individual physician relationships disappears. However, the hospital system still maintains the legal requirement of physician collaboration. You just do not deal with it day to day. I have seen NPs attempt to practice independently by simply not having a formal agreement in place while relying on verbal arrangements with physicians. This is risky. The Texas Board of Nursing has disciplined practitioners for exactly this scenario. One case I remember involved an NP who had been practicing for five years without updating her collaborative agreement after changing employers. The board cited her not because she was practicing without any agreement, but because the agreement was stale and did not reflect her current practice scope. The fine was relatively small, but the public disciplinary action stayed on her record for years and affected her employment prospects significantly.
Practical Steps If You Want to Practice in Texas
First, confirm your credentials are in order. Texas requires national certification in your population focus, an active RN license, and completion of an accredited NP program. Second, locate a collaborating physician before you accept any job offer. This is critical because some physicians are unwilling to enter into supervisory arrangements, and the pool of willing collaborators in certain regions is small. Rural Texas has more available physicians, ironically, because the healthcare infrastructure is thinner and hospital systems are more flexible. Urban areas with well-established healthcare networks can be harder because experienced physicians have less incentive to take on supervisory responsibility. Third, understand the billing implications. Medicare and most commercial payers in Texas require the supervising physician's information on certain claims when NPs are providing services. This affects how you bill and what reimbursement rates you receive. Medicaid in Texas follows similar rules. The administrative workload for claim preparation increases when physician supervision documentation is required, and billing errors in this area are common among new Texas NP hires. The landscape could change. Legislative sessions in Texas produce new bills every two years, and several have targeted NP scope of practice restrictions. Whether any of them succeed depends on the lobbying power of the Texas Medical Association relative to nursing organizations. The Texas Nurses Association is active on this issue, but the physician lobby has historically been more effective at shaping healthcare legislation in this state. If you are considering a move to Texas, monitor the legislative session outcomes before you commit. A favorable bill could alter the practical requirements within your first year of employment.
What I can say with confidence is that the current system works adequately if you plan for it. The supervision requirement adds administrative steps, it creates potential bottlenecks when your collaborating physician is unavailable, and it limits your ability to set up a solo practice. But it also provides a safety net, and many NPs in Texas find the structured collaboration beneficial, particularly in complex cases where a second clinical opinion is valuable. The friction is real, but manageable if you approach the requirements with realistic expectations rather than frustration born from comparing Texas to states with full practice authority.



