The Real Answer on PMHNP Therapy Billing
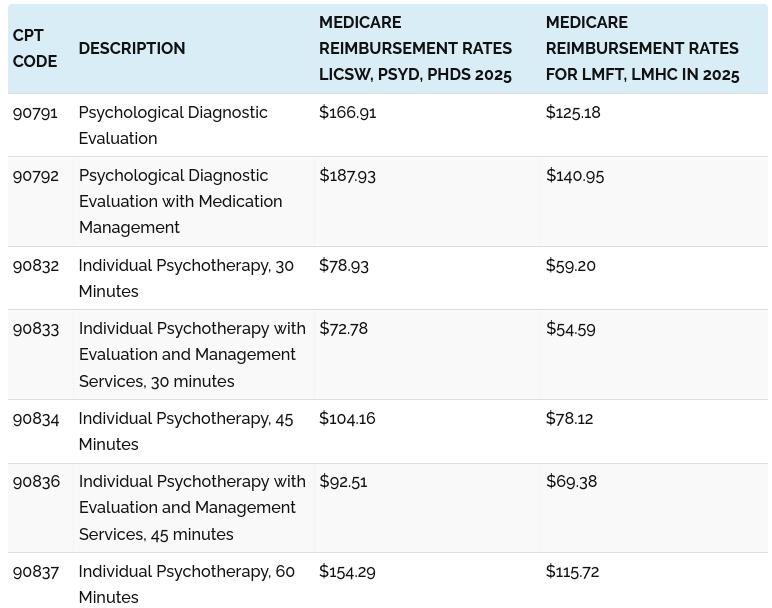
This comes up constantly on forums and the answer is never a simple yes or no, mostly because it depends on which state you're in, which payer you're dealing with, and how your privileges are structured at your facility. I've been through this enough times to know the pain points well. Yes, in most cases you can bill for psychotherapy under your own NPI. The CPT codes you'd typically use are 90832, 90834, 90837 for individual therapy sessions, plus the add-on codes for psychoanalysis when applicable. Your credentials as a PMHNP qualify you as an eligible provider under Medicare and most commercial payers for these services. Here's where it gets messy though. Some states have restrictive scope-of-practice laws that limit what PMHNPs can do independently. In reductionist practice states, you might need a collaborative agreement on file with a physician before you can bill certain services, even therapy. I ran into this back in 2022 when a payer in Alabama denied a claim for 90837 because they had a policy requiring the supervising physician's NPI to be appended to the therapist's claim. The denial came with a message that made no sense at first, but the workaround was straightforward: I called the payer's provider services line, got the denial reference number, and submitted a formal appeal with the state board documentation proving my independent prescriptive authority. Took about three weeks, but it set a precedent for future claims. Never let a single denial stand without appealing if you know your credentials are valid.
Medicare doesn't differentiate between a PMHNP and a psychiatrist when it comes to billing psychotherapy. They treat both as mental health professionals under the same benefit structure. Medicaid is another story entirely, and it varies by state to a frustrating degree. Some states don't reimburse PMHNPs for psychotherapy at all, or they only cover it if it's bundled with medication management visits. One thing people miss is the difference between billable time and billable encounters. You can't bill 90837 for a 25-minute session. The code requires at least 53 minutes of face-to-face psychotherapy. I've seen providers try to stack a 90846 (psychiatric assessment with medication management) on top of a short therapy session to make the math work. Some payers catch this as unbundling and deny both codes. The safer approach is to document separately and bill the appropriate code for each encounter length. If your patient needs therapy that's shorter than 53 minutes, 90832 or 90834 might be more appropriate depending on the exact duration. Another nuance that trips people up is the difference between psychotherapy and psychiatric diagnostic evaluation. A full psychiatric evaluation with psychotherapy is billed under the 90791 or 90792 codes when performed by an NP, but if you're also managing medications during that same session, some payers will flag it as overlapping services. The documentation needs to clearly separate the therapeutic intervention from the medication management component, and they need distinct time stamps in the medical record.
If you're working in a hospital or health system setting, check whether your credentialing through the hospital's provider network automatically covers therapy billing. Sometimes credentialing for psychopharmacology doesn't include psychotherapy privileges, and you'll need a separate application to the medical staff. I learned this the hard way when a health system in Texas didn't have my therapy billing activated for two months after I started, and I ended up billing under a collaborating psychiatrist's NPI temporarily. It wasn't ideal for revenue attribution but it kept patients from falling through the cracks. Private payers like Blue Cross, Aetna, UnitedHealthcare, and Cigna generally recognize PMHNPs for therapy billing, but their provider directories sometimes list you incorrectly as a prescriber-only provider. Always verify your profile directly in each payer's portal before you start seeing patients, because getting caught with an inactive or misclassified provider status mid-course of treatment is the worst scenario. It delays payments and creates compliance headaches. The bottom line is that the ability to bill for therapy exists in almost every jurisdiction, but the administrative burden of confirming it varies widely. Keep your state nursing board license current, maintain documentation that proves your scope allows independent psychotherapy, and verify each payer's policy individually rather than assuming uniformity across the board. Doing the verification upfront saves you from writing off thousands in revenue later.
Get the Full Details