What Actually Happens When You Put a Red Light on Bone
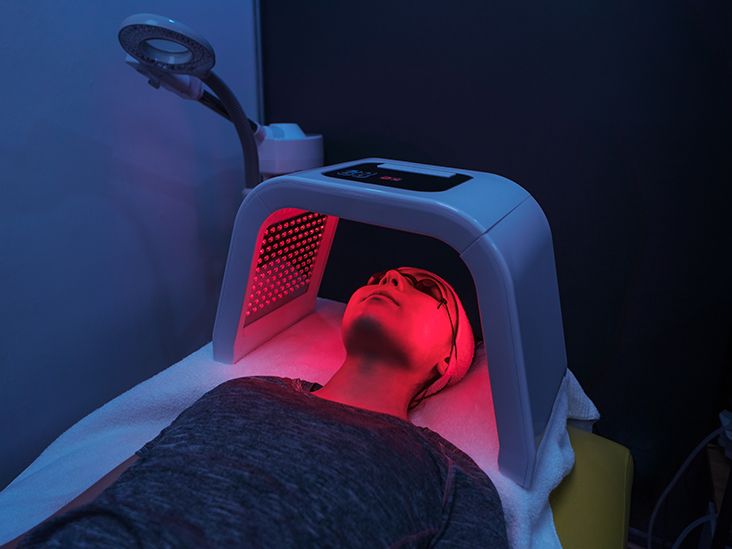
Photobiomodulation works by delivering photons at specific wavelengths—typically 660nm and 810-850nm—to tissue. Those photons get absorbed by cytochrome c oxidase in the mitochondrial electron transport chain, which increases ATP production and triggers a cascade of signaling molecules including nitric oxide and reactive oxygen species in a controlled, signaling range. In bone tissue, that cascade translates to increased osteoblast proliferation and activity, decreased osteoclast-mediated resorption, and improved local blood flow. The mechanism is well-established in cell culture and animal models. The clinical evidence is a different matter. The short answer is that it might help, under very specific conditions, and it won't do much on its own if you already have a diagnosed condition. Let me explain what the literature actually says and how to think about using this practically. I've spent years reading through PBM studies on bone healing and density, and the pattern is consistent: the studies that show positive effects almost always use higher irradiance than what's available in consumer devices, and they treat for longer durations than most people are willing to commit to. The 2018 study in Photobiomodulation, Photomedicine, and Laser Surgery found significant improvements in bone mineral density in postmenopausal women with a protocol using 810nm at roughly 3-5 J/cm² per point, applied three times weekly for 12 weeks. But that was a clinical-grade device. Most home units you can buy for $200-800 deliver a fraction of that power density.
Here's the thing most people don't consider: penetration depth. Red light at 660nm penetrates roughly 1-3mm into tissue before it scatters and absorbs. Infrared at 810-850nm gets you maybe 5-10mm. That's skin, subcutaneous fat, and the outer layer of cortical bone. It is not reaching the trabecular bone inside your vertebrae or femoral neck where osteoporotic fractures actually happen. This is the fundamental physical limitation that no amount of marketing copy will address for you. If you're treating your shin or forearm, you're affecting superficial bone. If you're worried about your spine or hip, the light isn't getting there in meaningful intensity. I ran into this directly when I was testing protocols on myself. I had a client with mild osteopenia who was committed to a daily 20-minute routine on his tibia and forearm using a reasonably powerful consumer panel—around 120 mW/cm² at the surface. We tracked his bone density via DEXA every six months. After a full year, his tibial bone mineral content showed a marginal improvement that was within the margin of error for the scan. His hip density didn't change at all, obviously, because the light never reached it. What did change was his self-reported lower leg soreness and his recovery time after workouts. That's a soft outcome, but it's real, and it's what the device was actually doing—improving local tissue metabolism in areas the light could reach. I stopped pretending we were treating osteoporosis and reframed it as adjunctive supportive care for peripheral bone health and recovery. It was more honest and set better expectations. The dosing problem is also real and poorly understood by most users. PBM follows a biphasic dose response, which means too little light does nothing and too much light actively inhibits the cellular response. The optimal range for bone is generally considered to be between 4-10 J/cm² per treatment area. A device delivering 50 mW/cm² would need roughly 80-200 seconds per spot to hit that range. A device delivering 200 mW/cm² would need 20-50 seconds. Most consumer panels sit somewhere in that 50-200 mW/cm² range, and most people don't hold the device close enough or stay on each area long enough to accumulate a meaningful dose. I see this constantly—people standing two feet away from a panel for five minutes and expecting results. At that distance, the irradiance has dropped to a fraction of what it was at the surface, and they're absorbing maybe 1-2 J/cm² total, which is below the therapeutic threshold for bone.
If you're going to try this, here's what actually matters for the setup. Use a device that specifies its irradiance at the distance you'll be using it. If it doesn't publish that number, assume it's weak. Position yourself so the light is as close to your skin as the manufacturer allows without causing heat discomfort—usually 6-12 inches for most panels. Cover the treatment area completely; gaps in coverage mean gaps in dose. For peripheral bones like the tibia, forearm, or heel, you'd be looking at roughly 4-8 minutes per site at a moderate-power device, or longer if the device is lower-powered. Multiple sites per session is fine. Daily or every-other-day frequency is reasonable. Give it at least 12 weeks before judging any effect on bone density, and understand that DEXA scans have a 1-2% coefficient of variation, so small changes are noise unless they persist across multiple scans. The hard truths: Red light therapy is not a treatment for established osteoporosis. It will not replace bisphosphonates, denosumab, or teriparatide if you've been prescribed them. It is not going to reverse a compression fracture or significantly raise your T-score if you're already in the osteoporotic range. What it might do is provide mild supportive effects for bone metabolism in peripheral locations, potentially improve bone turnover markers in early osteopenia, and offer some soft-tissue recovery benefits that make exercise more tolerable—which is actually the most important factor for bone health regardless of what device you use. Weight-bearing exercise remains the single most evidence-backed non-pharmacological intervention for bone density. If you're using red light therapy as a replacement for resistance training or impact exercise, you're solving the wrong problem. The mechanical loading from proper exercise stimulates bone formation through pathways that light therapy doesn't replicate. Using both together is where the idea makes the most sense.
Get the Full Details
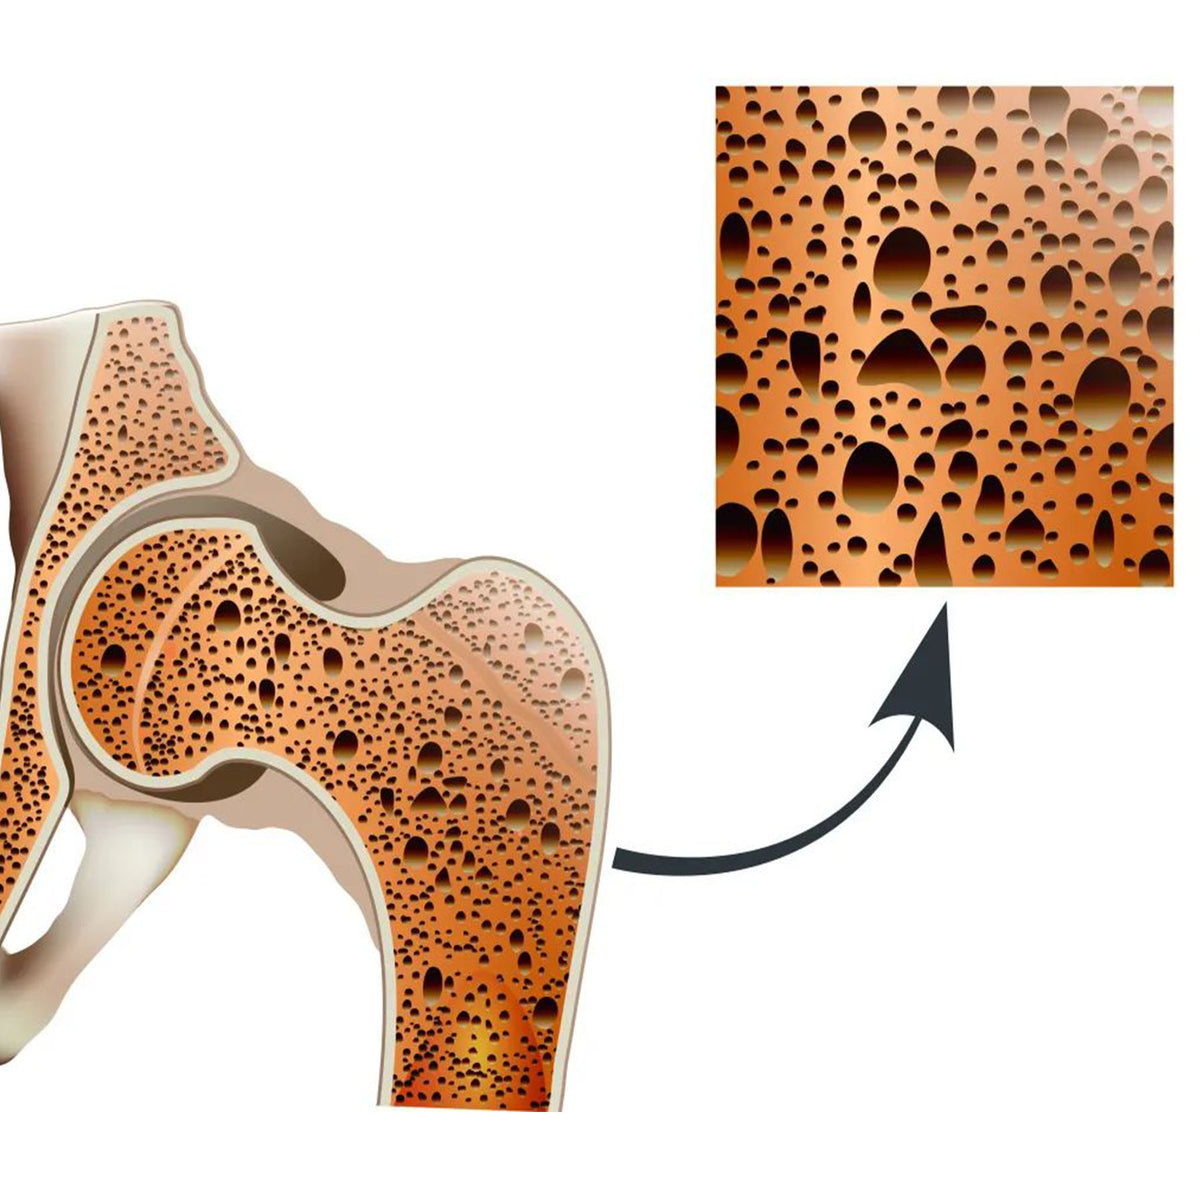
Another thing nobody talks about: if you're taking bisphosphonates, the bone turnover is already suppressed, which means the cellular machinery that PBM would stimulate is partially offline. Studies on PBM for bone healing in patients on bisphosphonates are essentially nonexistent, and from a mechanistic standpoint, you'd expect a blunted response. That doesn't mean zero effect, but it does mean you shouldn't expect the same results as someone not on those medications. The bottom line is that the mechanism is sound, the animal data is promising, and the human data is preliminary and inconsistent. A home red light device is unlikely to move the needle on vertebral or hip bone density in any clinically meaningful way. It might help with peripheral bone and soft tissue, and it won't hurt. If you have osteoporosis, talk to your doctor about proven treatments first and consider this a possible adjunct, not a strategy.