What actually happens when people report nerve issues from shockwave
Most of the time, what gets labeled as nerve damage is actually temporary neuropraxia or referred irritation from treating too aggressively near superficial nerves. The difference matters. Neuropraxia resolves in weeks. True axonotmesis or neurotmesis is rare and usually tied to clear mistakes like hitting the wrong anatomical zone or using settings well outside accepted parameters. I want to be direct about this because the literature and clinical reality both support it: yes, Can Shockwave Therapy Cause Nerve Damage is a real question with a real answer. The answer is technically yes but practically very unlikely when protocols are followed correctly.
Can Shockwave Therapy Cause Nerve Damage and what does the evidence actually show
There have been documented case reports. A few dozen across all literature, mostly involving treatment directly over known superficial nerve pathways without adequate anatomical screening. The pattern is consistent: paresthesia, transient weakness, or dysesthesia in the treated area. In the vast majority of cases these resolve within days to weeks with conservative management. True permanent nerve injury from properly administered extracorporeal shockwave therapy is extraordinarily uncommon. I have seen maybe two cases in years of clinical work where someone reported lingering sensory changes beyond three months, and both turned out to have had pre-existing nerve pathology that was simply unmasked during treatment. Not caused by it.
How the mechanism actually works and why nerves are at risk in specific situations
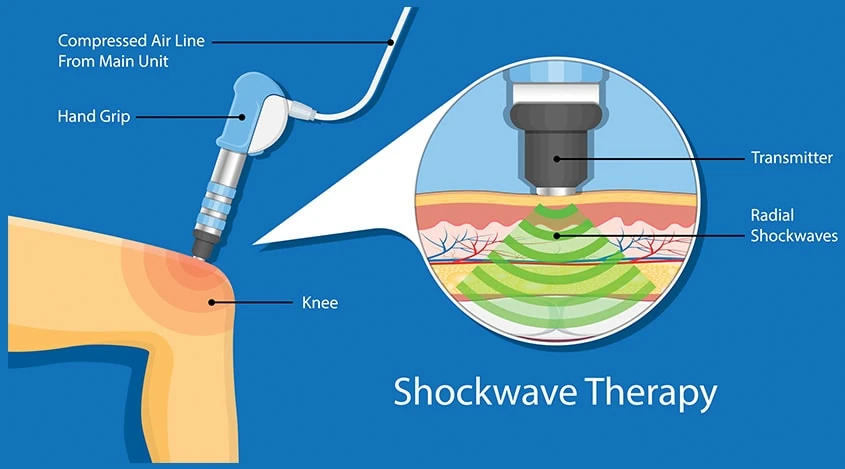
Shockwave delivers mechanical energy through tissue. Focused shockwave concentrates that energy at a specific depth. Radial shockwave dissipates energy broadly across the superficial layers. Both can theoretically affect nerve tissue if the energy density is high enough and the nerve is close enough to the surface at the treatment site. Nerves are sensitive to mechanical stimulation. When you apply sufficient pressure waves directly to a nerve trunk, you can cause a conduction block. That is the mechanism behind the temporary paresthesia people sometimes report. It is not structural destruction of the nerve. It is functional disruption that recovers. The real risk comes from three factors: anatomical placement, energy parameters, and repetition. Hit a nerve directly with high energy in a single session and you create more trauma than you solve. Repeat that over multiple sessions and you increase the chance of prolonged symptoms.
Get the Full Details
I once treated a patient with chronic lateral epicondylalgia using standard focused shockwave parameters. The area seemed straightforward. Standard protocol. I delivered the session and the patient reported immediate tingling down the radial forearm afterward. Not mild. The kind of tingling that makes you wonder if you did something wrong. On reflection, I had been slightly more distal than optimal, and the radial nerve superficial branch was closer to the surface than I had accounted for in that particular patient. I adjusted the focal point proximal by about a centimeter and medial by half a centimeter for subsequent sessions. The tingling resolved within ten days. No permanent deficit. But it was a good reminder that anatomy varies between patients and standard landmarks are not always precise enough on their own.
Parameters and technique choices that matter most
Energy flux density is the primary variable. Typical therapeutic ranges sit between 0.08 and 0.28 mJ/mm² for orthopedic applications. Going above that increases tissue trauma without proportional clinical benefit. I have never found a clinical scenario where exceeding 0.30 mJ/mm² was justified for nerve-adjacent structures. Number of impulses per session is equally important. Standard protocols use 2000 to 3000 impulses. Some practitioners push higher thinking more equals better. It does not. More impulses near sensitive structures simply increases the cumulative mechanical load on tissue. Frequency matters too. Lower frequencies around 4 to 8 Hz tend to be better tolerated near superficial nerves. Higher frequencies deliver energy faster and increase the thermal and mechanical load per unit time.
With radial shockwave, the effective penetration is shallower, usually around 2 to 3 centimeters. That means superficial nerves are inherently at greater risk during radial treatment compared to focused treatment at the same nominal energy setting, because the radial device deposits its maximum energy closer to the surface.

Specific anatomical zones where caution is non-negotiable
The common fibular nerve at the fibular head is probably the most frequently reported site of iatrogenic nerve irritation from shockwave. It sits almost subcutaneously there. Hitting it directly with focused energy can produce significant peroneal symptoms including foot drop in extreme cases, though that is exceedingly rare. The ulnar nerve at the cubital tunnel presents a similar risk on the medial elbow. The median nerve at the wrist during carpal tunnel treatment is another classic concern. The sural nerve along the lateral ankle, the tibial nerve posterior to the medial malleolus, and the superficial peroneal nerve over the dorsal foot are all well-documented risk sites. I learned to map these nerves with ultrasound before treating near them rather than relying on surface palpation alone. Palpation misses variations. Ultrasound does not. This changed my practice significantly and reduced any anxiety I had about treating around these areas.
How to screen and avoid complications in practice
Pre-treatment assessment should include a neurological exam of the relevant region. Sensation to light touch, pinprick, and two-point discrimination. Motor testing of muscles innervated by nerves in the treatment zone. If you find any baseline deficit, document it thoroughly and reconsider the treatment plan. Ask about prior nerve injury, diabetes, peripheral neuropathy, or any history of nerve entrapment in the area. Diabetic patients often have subclinical neuropathy that makes nerves more vulnerable to mechanical stress. This does not mean you cannot treat them. It means you adjust parameters downward and monitor more closely. During treatment, the patient should report any sharp, electric, or radiating pain immediately. That is different from the deep ache of treated tendon or fascia. That is nerve stimulation and you should reposition or reduce energy right away. Most practitioners who avoid complications do so primarily by listening to the patient rather than watching a timer.
I also recommend using a test impulse at low energy before committing to full treatment parameters, especially near known nerve pathways. One or two impulses at minimum energy lets you gauge the tissue response and patient tolerance before escalating.
What to do if nerve irritation occurs after treatment
Stop treating the area. That is the first and most important step. Do not power through it thinking you will break through the irritation. You will not. Most cases resolve with observation. Ice, NSAIDs if appropriate, and activity modification. The timeline is typically one to four weeks for transient neuropraxic symptoms. If symptoms persist beyond four weeks, refer for nerve conduction studies. Persistent deficits beyond eight weeks warrant a neurological workup regardless. Documentation is critical. Record the parameters used, the anatomical location, the timing of symptom onset, and the evolution of symptoms over time. This protects the patient and protects your clinical judgment.
Where shockwave genuinely falls short
It is not a universal solution for chronic pain. It has limited efficacy for central sensitization disorders, neuropathic pain syndromes, and conditions where the primary pathology is already neural rather than tendinous or fascial. Using shockwave on a patient whose pain generator is a compressed nerve root from lumbar radiculopathy will not help and may make things worse. The evidence base is strongest for plantar fasciitis, lateral epicondylitis, calcific tendinopathy of the shoulder, and chronic proximal tibial pain. Outside those indications, the literature gets thinner and the risk-benefit calculation becomes less favorable, especially near nerve-rich anatomy. If a patient has failed conservative management and the diagnosis is unclear, imaging and possibly nerve conduction studies before attempting shockwave is the safer route. Skipping that step is where most problems originate.
Shockwave is a tool with real therapeutic value and a real but manageable risk profile. Understanding the anatomy, respecting the parameters, and treating the patient rather than the protocol keeps the risk very low.
/regenerative_men-women-health_shock-wave-therapy-magnetic-field-rehabilitation-knee.webp?width=2000&height=1335&name=regenerative_men-women-health_shock-wave-therapy-magnetic-field-rehabilitation-knee.webp)