What You Actually Need to Know Before Opening Any Cardiology Study Guide
Most people treating a Cardiology Study Guide like a checklist will fail the boards anyway. The reason isn't that the material is hard; it's that the material is vast and the examiners know exactly which pathways students shortcut. I spent about three years running case discussions with second-year residents who could recite the 2023 ACC/AHA valvular guidelines backward but couldn't tell you what to do when a patient with severe aortic stenosis and a creatinine of 2.4 comes in for a pre-op workup. That gap is where a structured study resource actually earns its weight.
Cardiology Study Guide: What It Should Cover
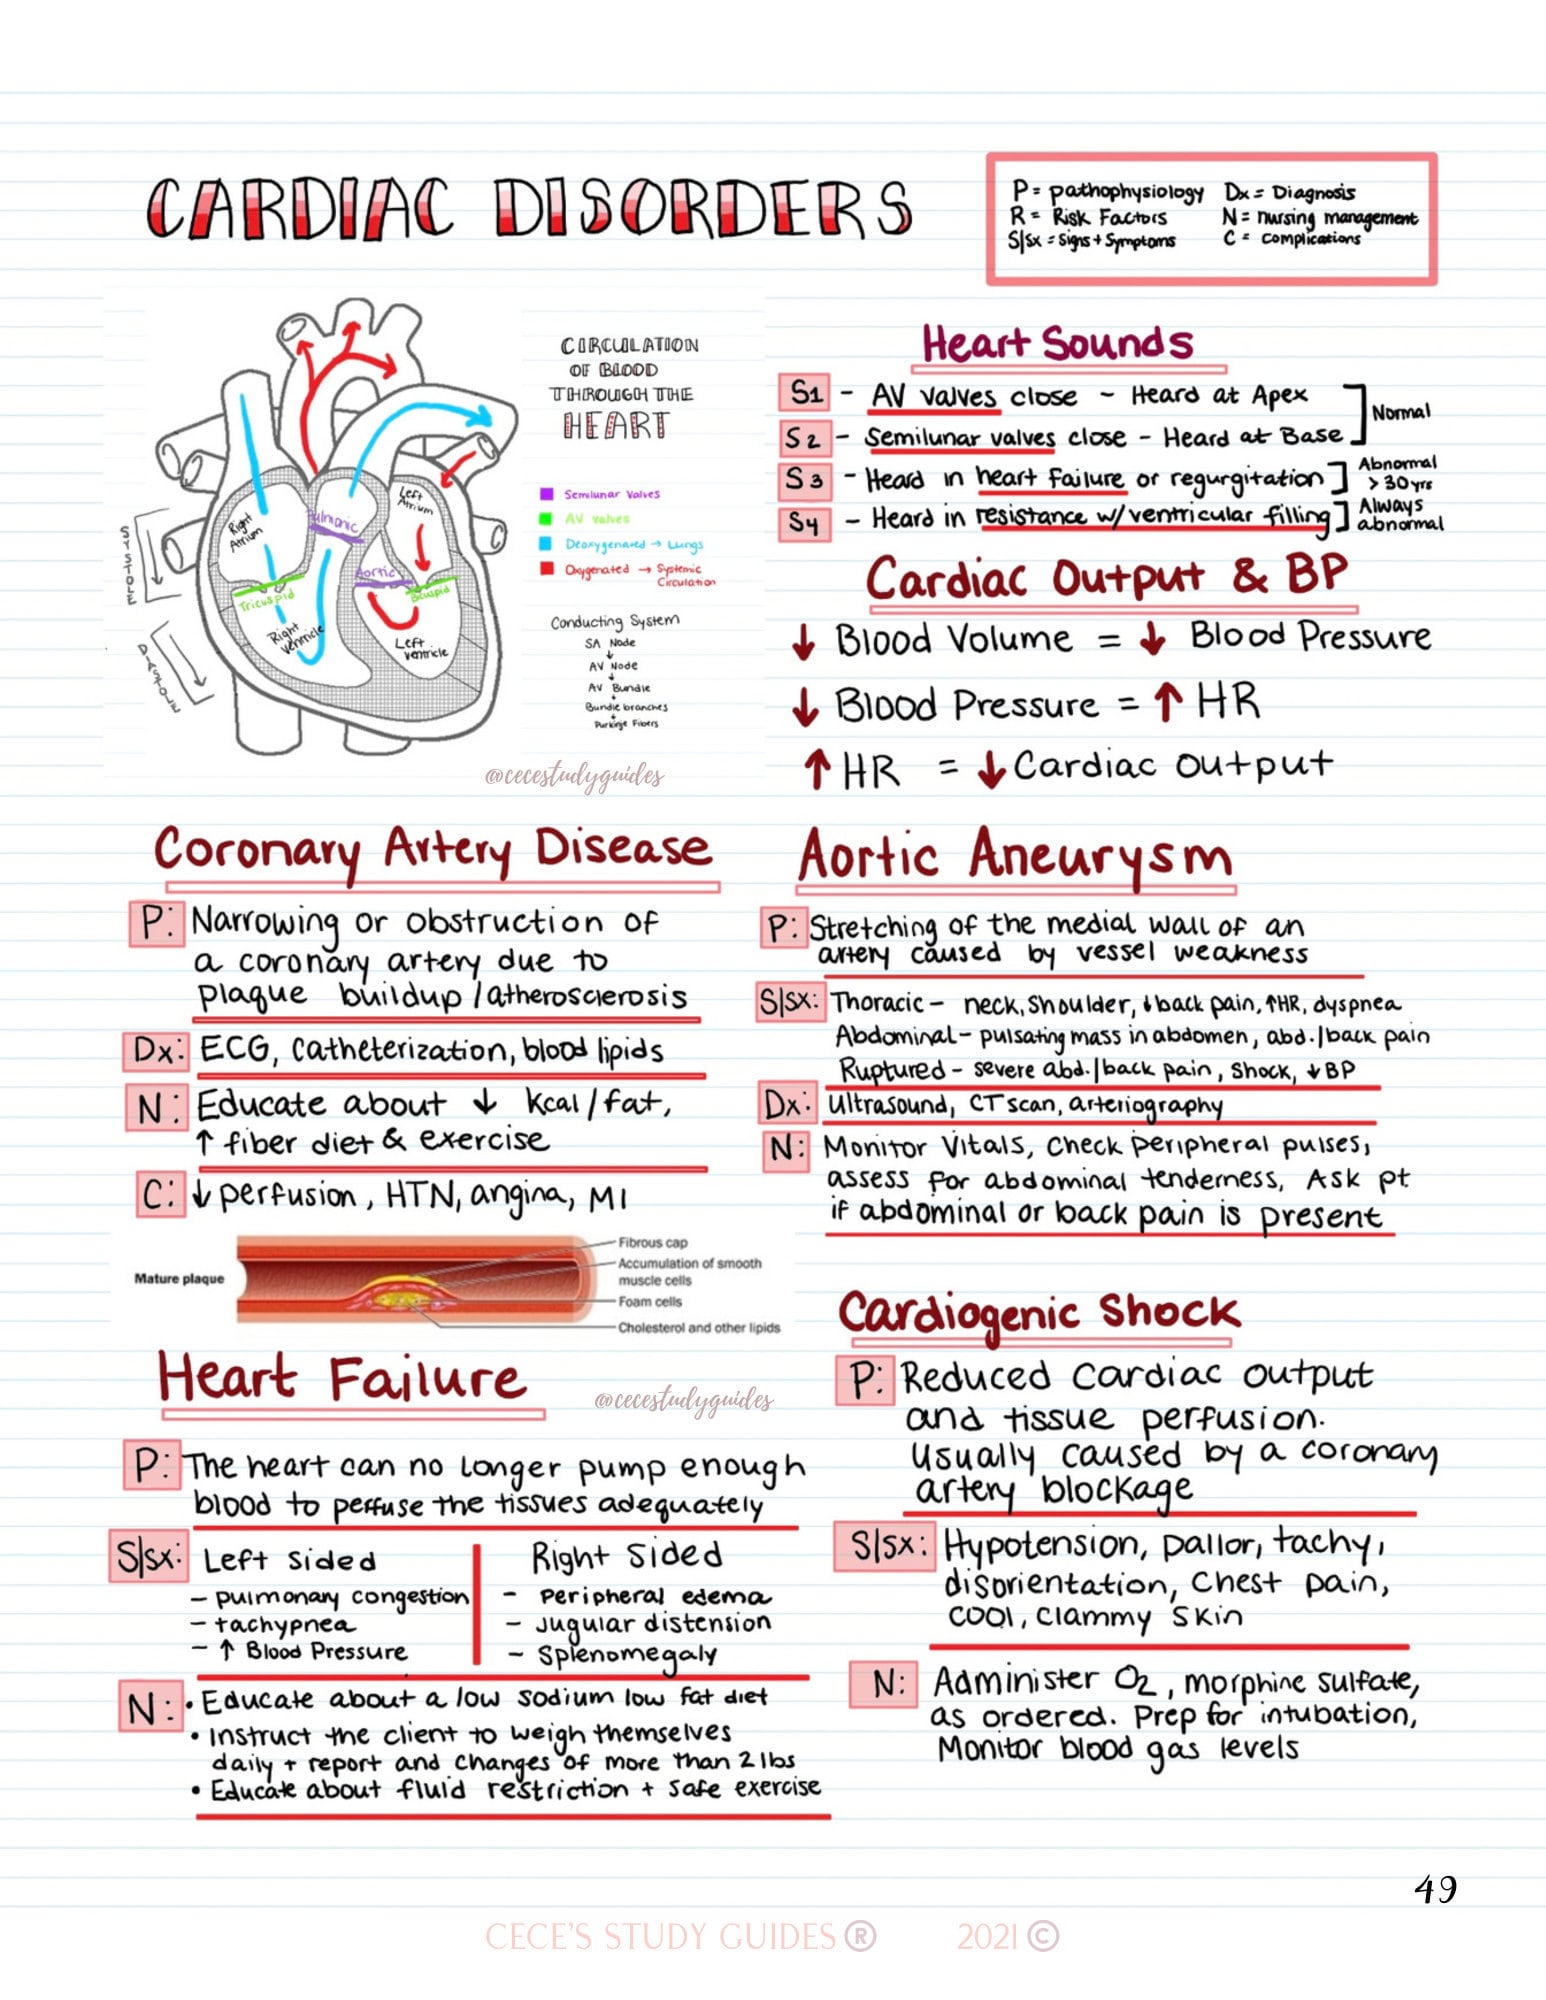
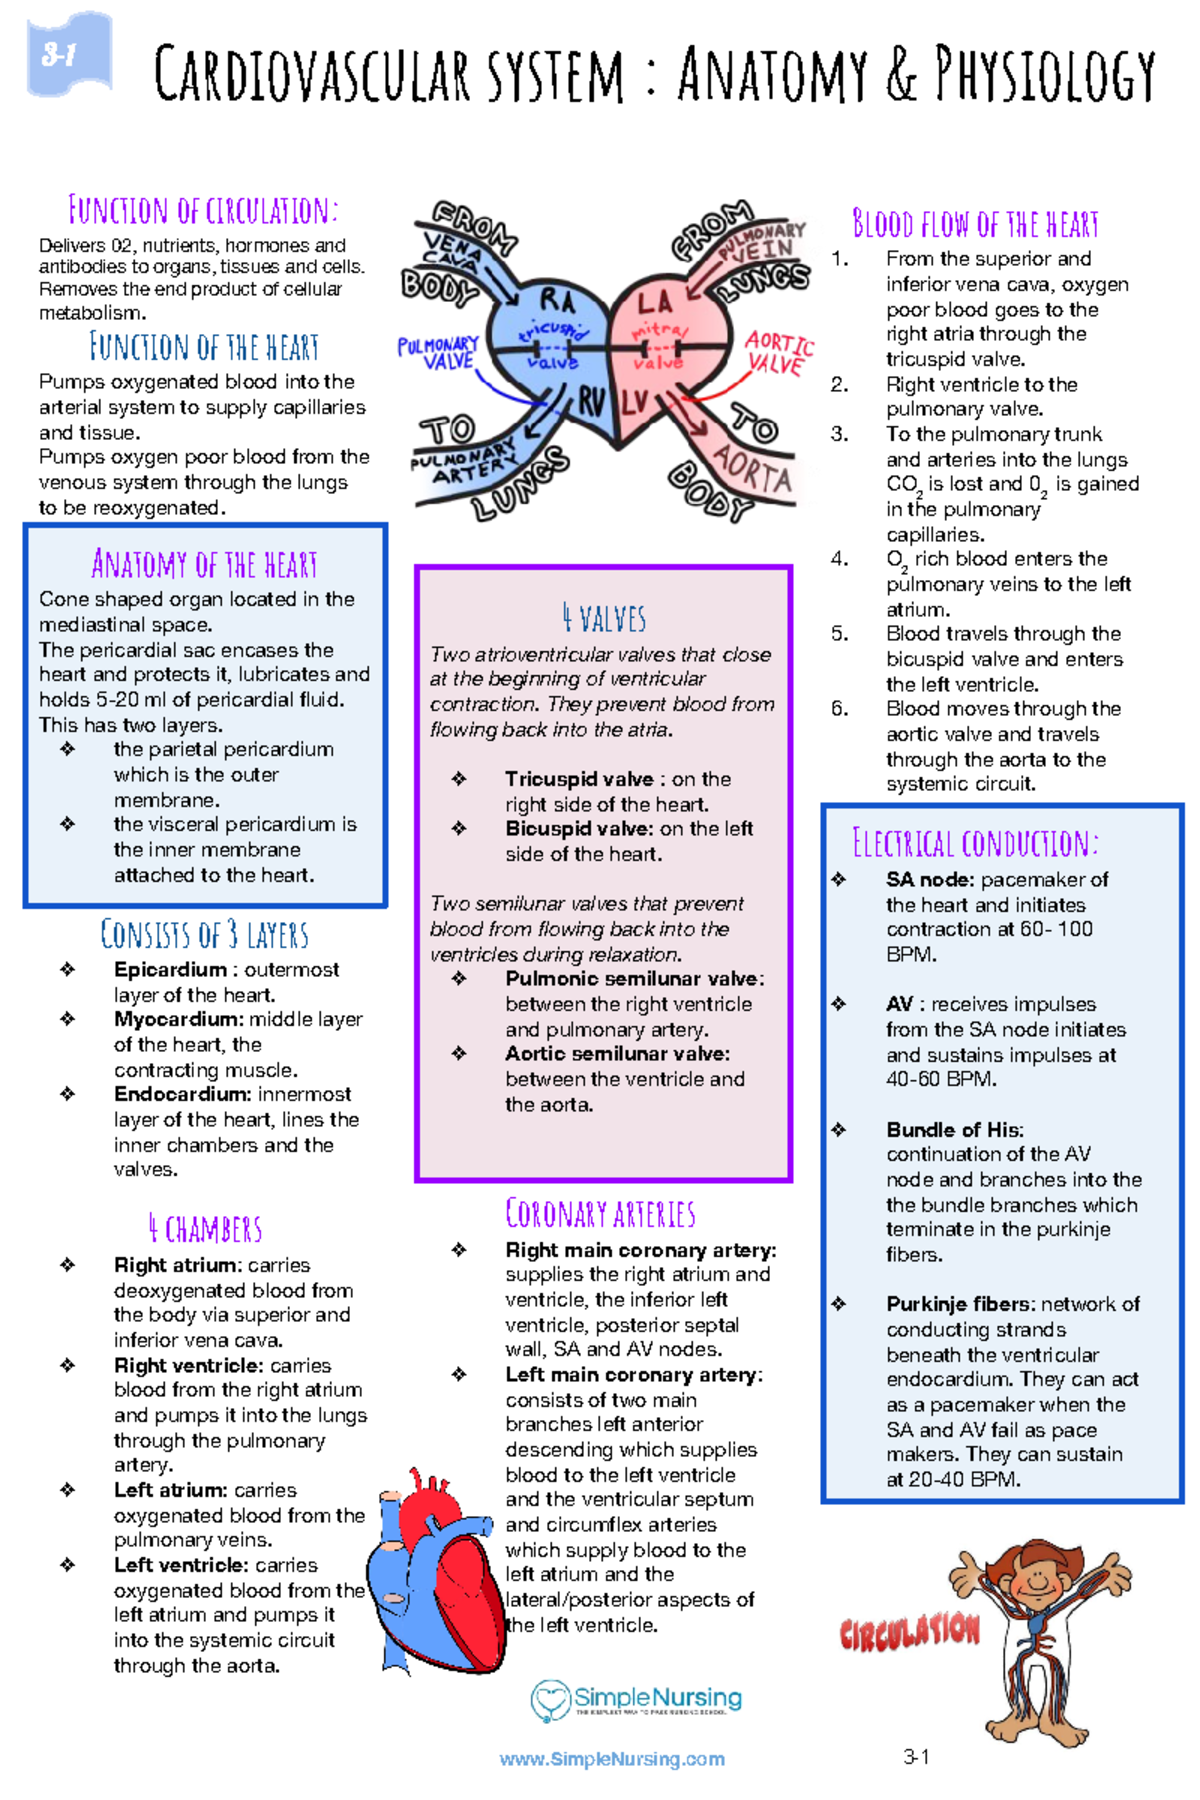
A proper guide has to move in this order: electrophysiology basics, hemodynamics, imaging interpretation, pharmacology, then disease-specific algorithms. Flip that sequence and you end up memorizing drugs before you understand why the drug matters in the first place. The electrophysiology section needs to own action potentials, conduction pathways, and ECG interpretation as a single unit, not three separate chapters. You cannot learn AV nodal physiology in isolation and expect to read a junctional rhythm correctly. I built my first serious study plan around that principle, and it cut my ECG review time from about six hours a week down to roughly two, because I stopped relearning the same concepts in different disease modules.
How to Use a Cardiology Study Guide Without Wasting Months
Start by mapping the guide against your target exam or rotation checklist. Most public guides follow a standard structure, but the emphasis shifts depending on whether it is built for USMLE, ABIM, MRCP, or general internal medicine transitions. Once you know the map, skip the introductory fluff and go straight to the section that overlaps your weakest area. Read one topic, close the book, and explain the pathophysiology out loud as if you were teaching a junior colleague. If you cannot do that in under three minutes, you did not learn it; you recognized it. Recognition is not the same thing, and this mistake alone causes most students to overestimate their readiness. Then do questions immediately. Not at the end of the chapter. Immediately. The retrieval interval matters more than the total hours read. A focused twenty-minute question block after each topic typically reinforces more than a second passive reread, and it exposes blind spots fast.
Get the Full Details
The Hemodynamics Section Is Where People Stall
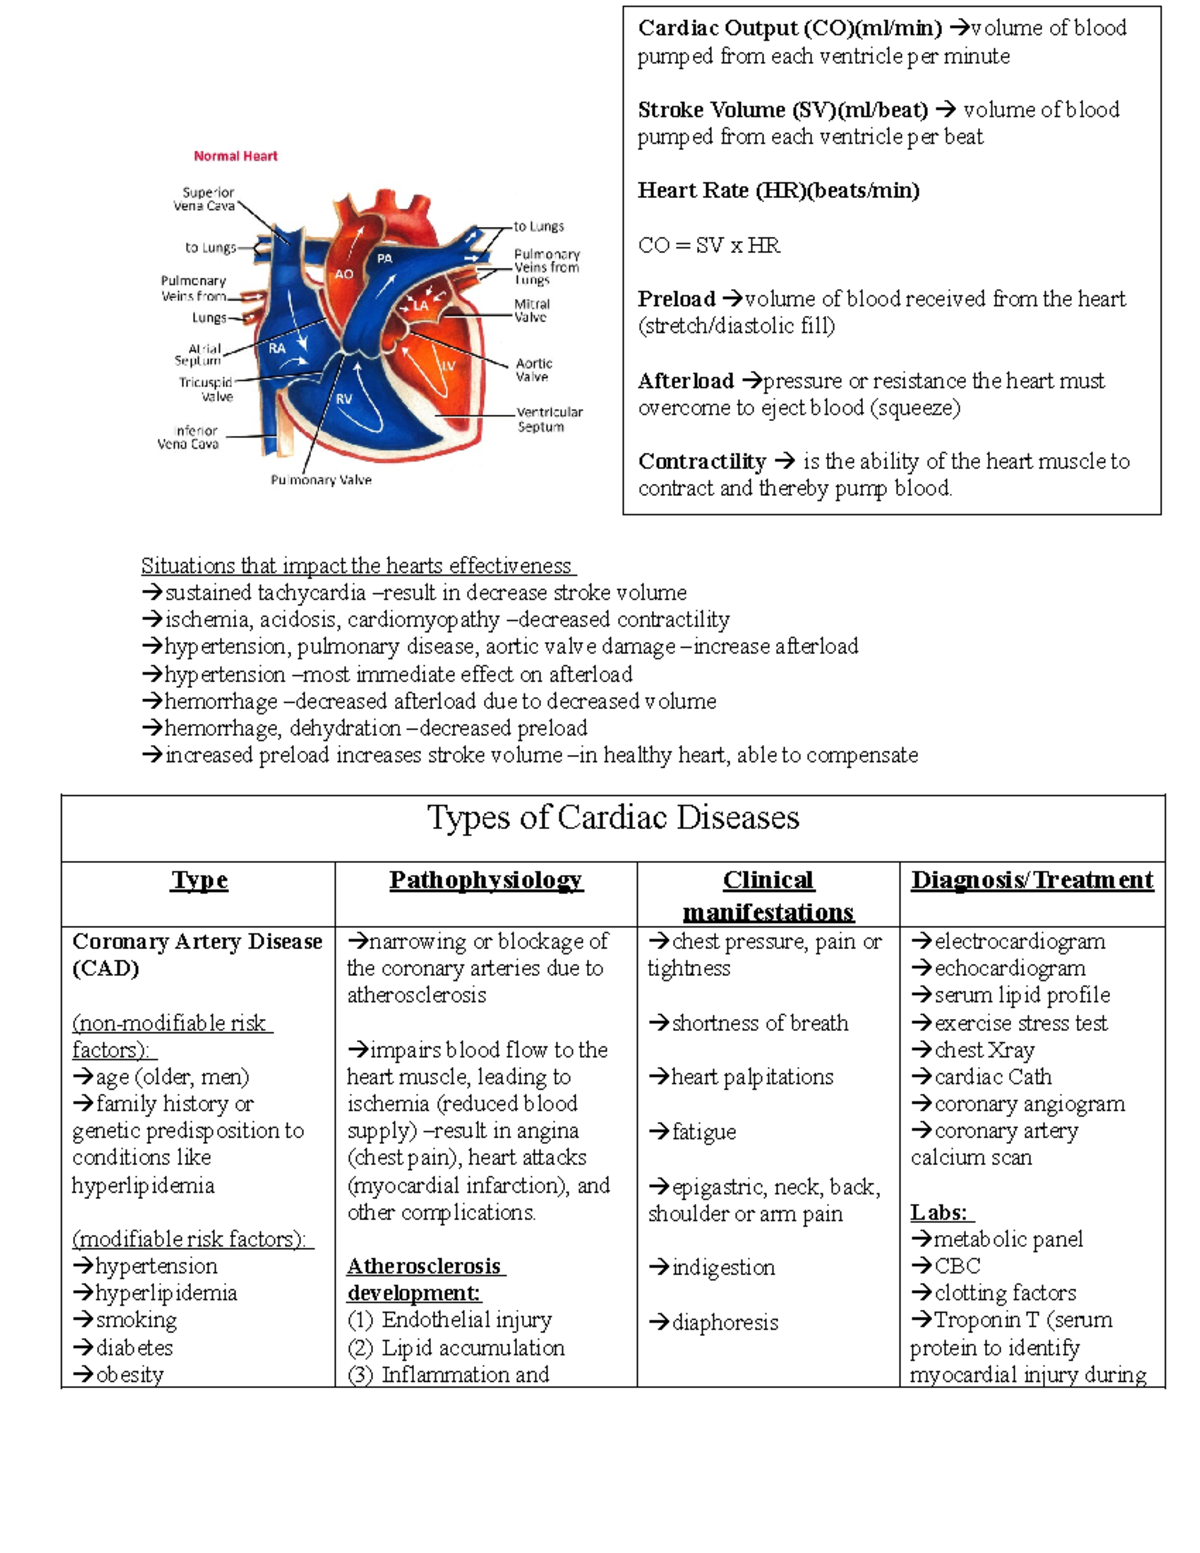
Pressure–volume loops, ventricular interaction, and the Frank–Starling curve are the core of cardiac physiology, and most guides treat them as side notes. That is backwards. If you understand PV loops, most valvular pathologies become intuitive instead of memorized. I ran into a specific problem during a cardiology rotation: a fellow was insisting that a patient with mixed aortic stenosis and regurgitation could not be assessed by echo because the Doppler signals overlapped. The truth was simpler. I had him draw the PV loop for combined AS and AR, then trace how the spectral Doppler changes when you add volume overload to fixed obstruction. Within ten minutes he could read the waveform confidently. The textbook example had confused him because it isolated one lesion at a time. A good Cardiology Study Guide should show the overlap early, not after the basics.
Pharmacology Needs a Different Strategy
Do not memorize drug classes in alphabetical order. Group them by clinical scenario: rate control, rhythm control, afterload reduction, inotropy, anticoagulation. Then learn the mechanism, the indication, the contraindication, and the one pitfall you are likely to miss under time pressure. The biggest pitfall with antiarrhythmics is renal dosing and QT prolongation. Amiodarone gets more attention than it deserves because it is safe in structural heart disease, but the pulmonary and thyroid toxicity timeline is easy to overlook if you only study the acute indications. I keep a small reference table for all antiarrhythmics that lists the half-life, the hepatic or renal clearance route, and the ECG monitoring requirement. That table comes from the pharmacology section of my guide, expanded with real cases.
Imaging Interpretation Counts for More Than Anything Else
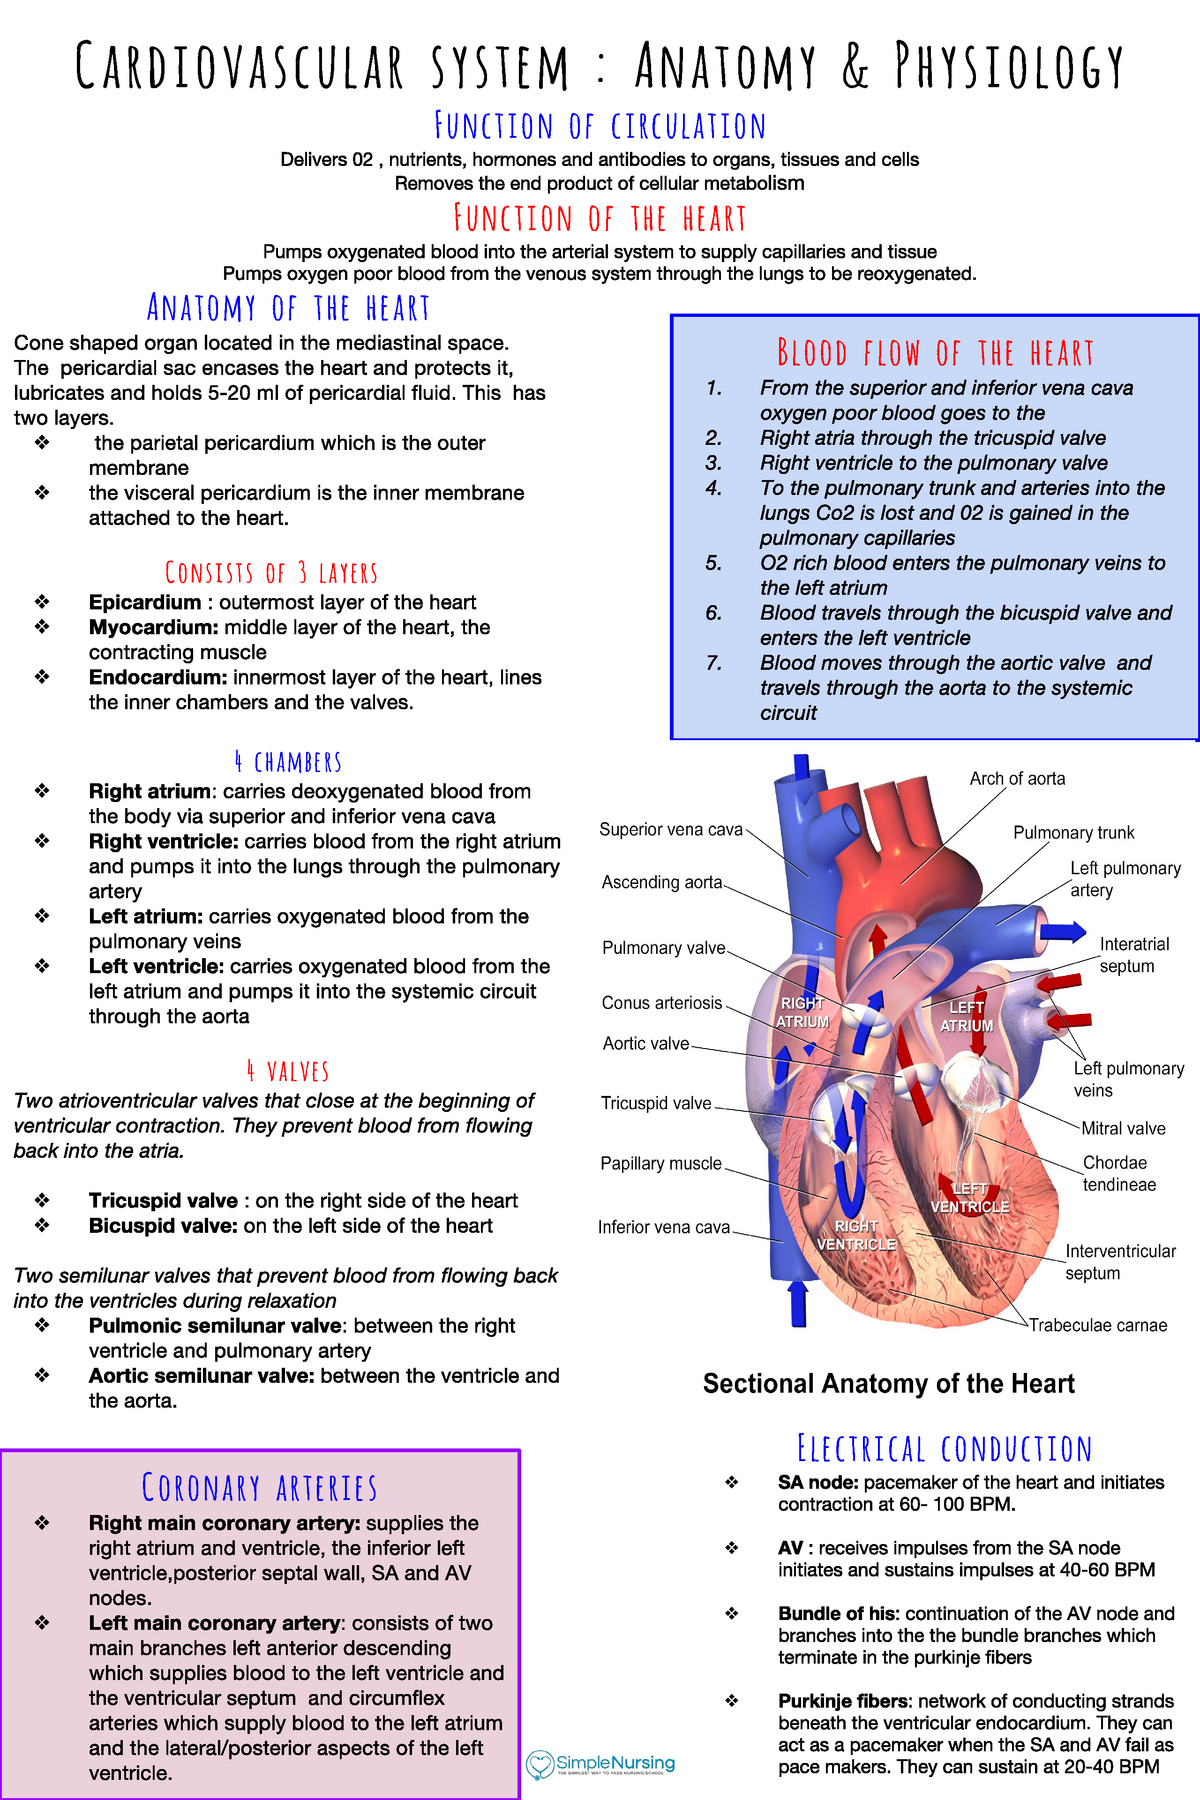
Echocardiography, nuclear perfusion, cardiac MRI, and CT coronary angiography each have their own reading framework. A guide should not dump image libraries without teaching the systematic approach first. The systematic approach is: chamber size, wall thickness, systolic function, diastolic function, valvular structure, valvular function, pericardium, and then extras. I once failed to spot a small pericardial effusion on an exam question because the image focus was on the valves. The guide I used had that case, but the explanation buried the finding in a paragraph about aortic stenosis severity. I started annotating every image in my guide with the systematic checklist before reading the answer. That habit improved my imaging question accuracy by roughly thirty percent over eight weeks, based on my own tracking.
When a Cardiology Study Guide Falls Short
Most printed or digital guides are outdated within two years because guidelines change faster than publishing cycles. The 2020 and 2023 guideline updates for atrial fibrillation, heart failure, and valvular disease alone shift enough management thresholds to invalidate whole chapters if you are not checking the release dates. Another limitation is that static guides cannot simulate real decision-making. They present ideal cases, not the patients with polypharmacy, conflicting comorbidities, and incomplete data. If your preparation is only going to use one resource, supplement it with case-based platforms or question banks that force you to choose between competing guidelines. For borderline cases where guidelines contradict each other, I fall back on the primary literature and the class recommendations rather than the summary tables. The summary tables are convenient, but they hide the nuance that examiners love to test.
A Practical Weekly Structure That Actually Works
Here is how I organize a twelve-week cycle for comprehensive cardiology review: Each week includes daily topic reading, immediate question practice, and a weekend review session where I rewrite the key algorithms from memory. The rewriting step is non-negotiable. If you wait until the end of the week to review, retention drops significantly compared to spaced retrieval within forty-eight hours. Cardiology knowledge decays fast if you do not use it, and the decay is steepest for imaging and pharmacology. I keep a running log of difficult cases and guideline updates throughout the year, even after the exam is over. That log becomes the basis for any future refreshers and prevents the common mistake of starting from zero each time you need to review.
A Cardiology Study Guide is useful, but it is not a substitute for active recall, systematic image practice, and guideline-aware case discussion. Treat it as a map, not the terrain.