
How to Build a Care Needs Assessment Template That Actually Works
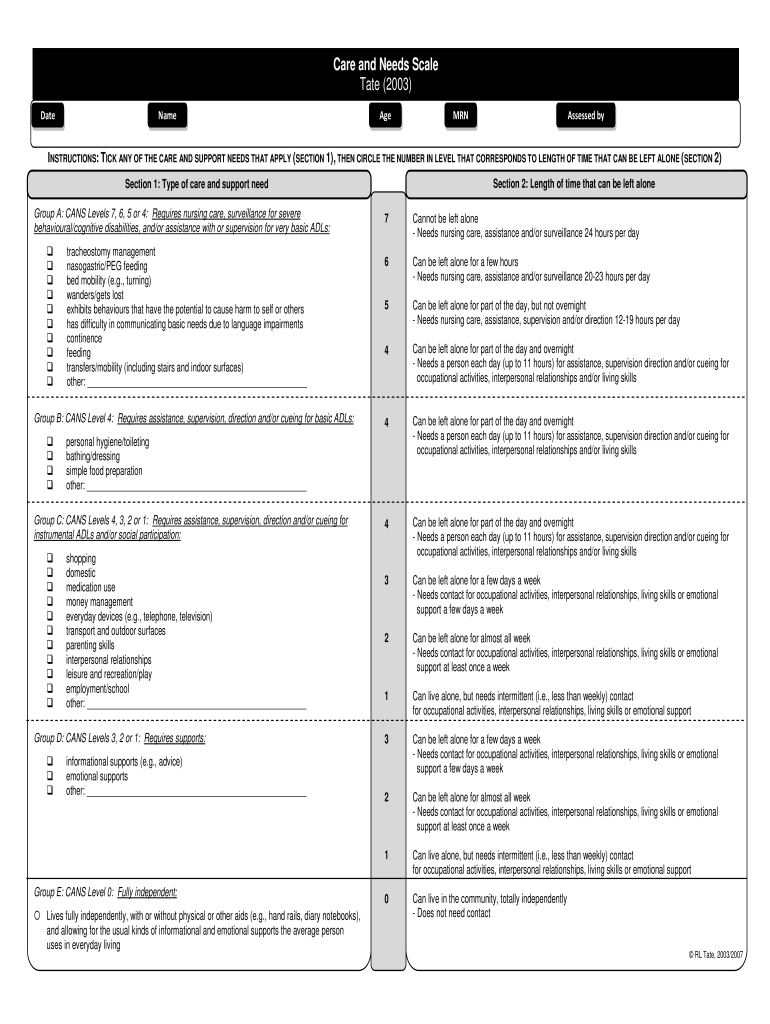
A care needs assessment template is a structured document used by social workers, care coordinators, and care providers to evaluate an individual's physical, cognitive, emotional, and social requirements. It standardizes the information gathering process so assessments are consistent, defensible, and actionable. I built my first version in 2013 using a basic Word form. It took three hours to complete for an average client and about twenty minutes for someone straightforward. The inconsistency was the real problem though. Two different assessors would look at the same person and produce completely different care plans because the template didn't force them to consider certain domains. ADLs would get five minutes of attention while sensory impairment got a single checkbox. That gap is where care plans fall apart later on.
Core Sections of a Care Needs Assessment Template
Every solid template covers these areas, but the trick is in how you structure them: Personal and Demographic Information — Name, date of birth, NHS number or equivalent identifier, primary diagnosis, living situation, and emergency contact. Keep this to one section at the top. People waste time scrolling when this gets buried. Activities of Daily Living (ADLs) — Basic ADLs include bathing, dressing, toileting, transferring, continence, and eating. Instrumental ADLs cover meal preparation, medication management, finances, transportation, and housekeeping. Rate each on a scale from independent to fully dependent, and always include a notes field. A checkbox saying "requires assistance with bathing" means nothing if you don't document whether that means standing by, minimal physical contact, or full two-person assist.
Cognitive and Mental Health Status — Use a validated tool here rather than writing your own questions. The MMSE or MoCA for cognition. GAD-7 and PHQ-9 for depression and anxiety screening. Don't substitute your gut feeling for a scored instrument. I've seen assessors mark someone as "mild cognitive concerns" based on a conversation while the MoCA score came back as 18 out of 30. The written impression and the validated result need to coexist in the template. Risk Assessment — Falls risk, self-neglect, vulnerability to exploitation, medication errors, and safeguarding concerns. Each risk category should have a likelihood and impact rating, plus a mitigation plan. This is the section that protects everyone if things go wrong. Social and Support Network — Who is involved? Family members, friends, carers, community groups. How often do they interact? What support already exists? This section gets rushed and it shouldn't. The difference between a care plan that works for six months and one that collapses in six weeks often comes down to whether you properly mapped the support network before writing it.
Get the Full Details
Goals and Outcomes — Short-term and long-term goals written in measurable terms. "Improved mobility" is not a goal. "Walking from bedroom to kitchen independently three times per day within four weeks" is measurable. Write the goal so you can tell six weeks later whether it was achieved.
The Edge Case That Broke My Template
About two years ago I was assessing a client who had early-stage dementia, significant hearing loss, and a history of paranoid delusions. The standard template treated these as separate domains. Cognitive section got a MoCA score. Sensory section got a hearing aid checkbox. Psychiatric history got a brief note. The resulting care plan recommended a day program with group activities. Three days later the client refused to go, became agitated, and called the police on the support worker. The problem wasn't the template sections themselves. It was that nothing in the template forced me to consider how those conditions interacted. The hearing loss meant the client couldn't follow group conversations, which triggered paranoia, which made the cognitive symptoms appear worse than they were, which then justified a higher care level than actually needed. I ended up creating a cross-condition interaction field at the bottom of every assessment. It's a simple text box but it forces a written analysis of how the domains compound each other. It added about four minutes to each assessment but it caught that interaction immediately on the next similar case and we restructured the care plan entirely.
Building Your Own Template
You have three realistic options depending on your resources: Spreadsheet-based — Excel or Google Sheets works fine for small operations. Each row is a client, each column is an assessment domain. Pros: cheap, flexible, easy to share. Cons: no validation logic, easy to accidentally delete formulas, scales poorly past 50 active assessments. PDF or Word forms — Standard in many healthcare settings. Pros: familiar format, requires no technical setup. Cons: impossible to validate, requires manual data entry later, difficult to analyze trends across cases.

Custom software or electronic health record module — The gold standard if you have the budget. Pros: built-in validation, audit trails, automated scoring, data export for reporting. Cons: cost, implementation time, training requirements. Most organizations I know spend 6 to 8 weeks and between 15,000 and 40,000 dollars to get this right, depending on customisation needs.
Pitfalls That Slow You Down
The most common mistake is overloading the template. I've seen versions with 200+ fields that take 90 minutes to complete. When the assessment itself becomes the bottleneck, people start skipping sections or copying and pasting from previous visits. Neither is acceptable. If a field doesn't directly inform a care decision, remove it. Every checkbox should have a purpose. Another issue is the scoring system. Likert scales from 1 to 5 seem intuitive but they produce unreliable data unless you provide explicit anchors for each point. A score of "3" means something different to different assessors. Define what each number represents in the template itself. I usually put the anchor text right beside the scale: 1 = independent, 2 = supervision, 3 = minimal assist, 4 = substantial assist, 5 = fully dependent. That reduces inter-rater variability significantly. Don't forget accessibility. If your template is only available in a format that requires specific software or a computer, you will miss people who are assessed in the field or at home. A tablet-friendly version or even a well-designed paper backup matters more than you'd think. One of my assessors completed a critical referral using a paper template because the client had no internet access. The digital follow-up took three extra days because the data had to be re-entered manually. Build redundancy in.
What This Won't Fix
A template is a documentation tool, not a diagnostic tool. It won't catch conditions the assessor isn't trained to recognize. It won't replace clinical judgment. And it absolutely will not compensate for rushed or incomplete assessments. I've seen templates filled out in ten minutes for clients who clearly needed a much more thorough evaluation. No amount of template design fixes that problem. That's a training and workload issue, not a template issue. Templates also struggle with people who have complex, changing conditions. A snapshot assessment captures a moment in time. If the person's needs shift week to week, you need a review cadence built into the system, not just the initial template. Monthly reviews for stable clients, biweekly for those transitioning between care levels, and weekly during acute episodes. Write that schedule into the template workflow so it becomes automatic rather than optional.

Where to Find a Starting Point
If you need to build from scratch, start with the NICE guidelines for social care assessment in England, the Adult Social Care Outcome Framework indicators, and your local authority's own assessment criteria. These documents define what must be captured. After that, format it into a working template using whichever platform suits your operation. Don't try to create something original from day one. Use existing regulatory frameworks as your skeleton and layer your own workflow on top. It saves weeks of design work and ensures compliance from the start. I use a modified version of a template originally developed by a local authority consortium. It covers the standard domains, includes the cross-condition interaction field I mentioned, and has built-in validation rules that flag missing high-risk sections before submission. It runs as a Google Form that feeds into a spreadsheet dashboard. Cost: zero beyond my time to set it up. Time to complete an assessment: down from three hours to about twenty-five minutes for a standard case. The reduction came from removing fields that didn't drive decisions and adding structure that forced consistent responses.


