Why Printed CBT Materials Still Matter for Older Adults
Most digital-first CBT platforms collapse when you hand them to someone over seventy. The text is too small. The navigation assumes a motor dexterity that arthritis doesn't allow. You end up spending more time troubleshooting the interface than doing the actual therapeutic work. That's where physical worksheets with clear answer keys become useful. Not as a replacement for a therapist, but as a bridge between sessions. I spent years running group CBT workshops at a community senior center, and the difference between a session that stuck and one that evaporated by Thursday usually came down to whether the materials were actually usable at 8 AM for people who needed their reading glasses to see a menu at a restaurant.
Cbt Therapy For Seniors Worksheets With Answer Key
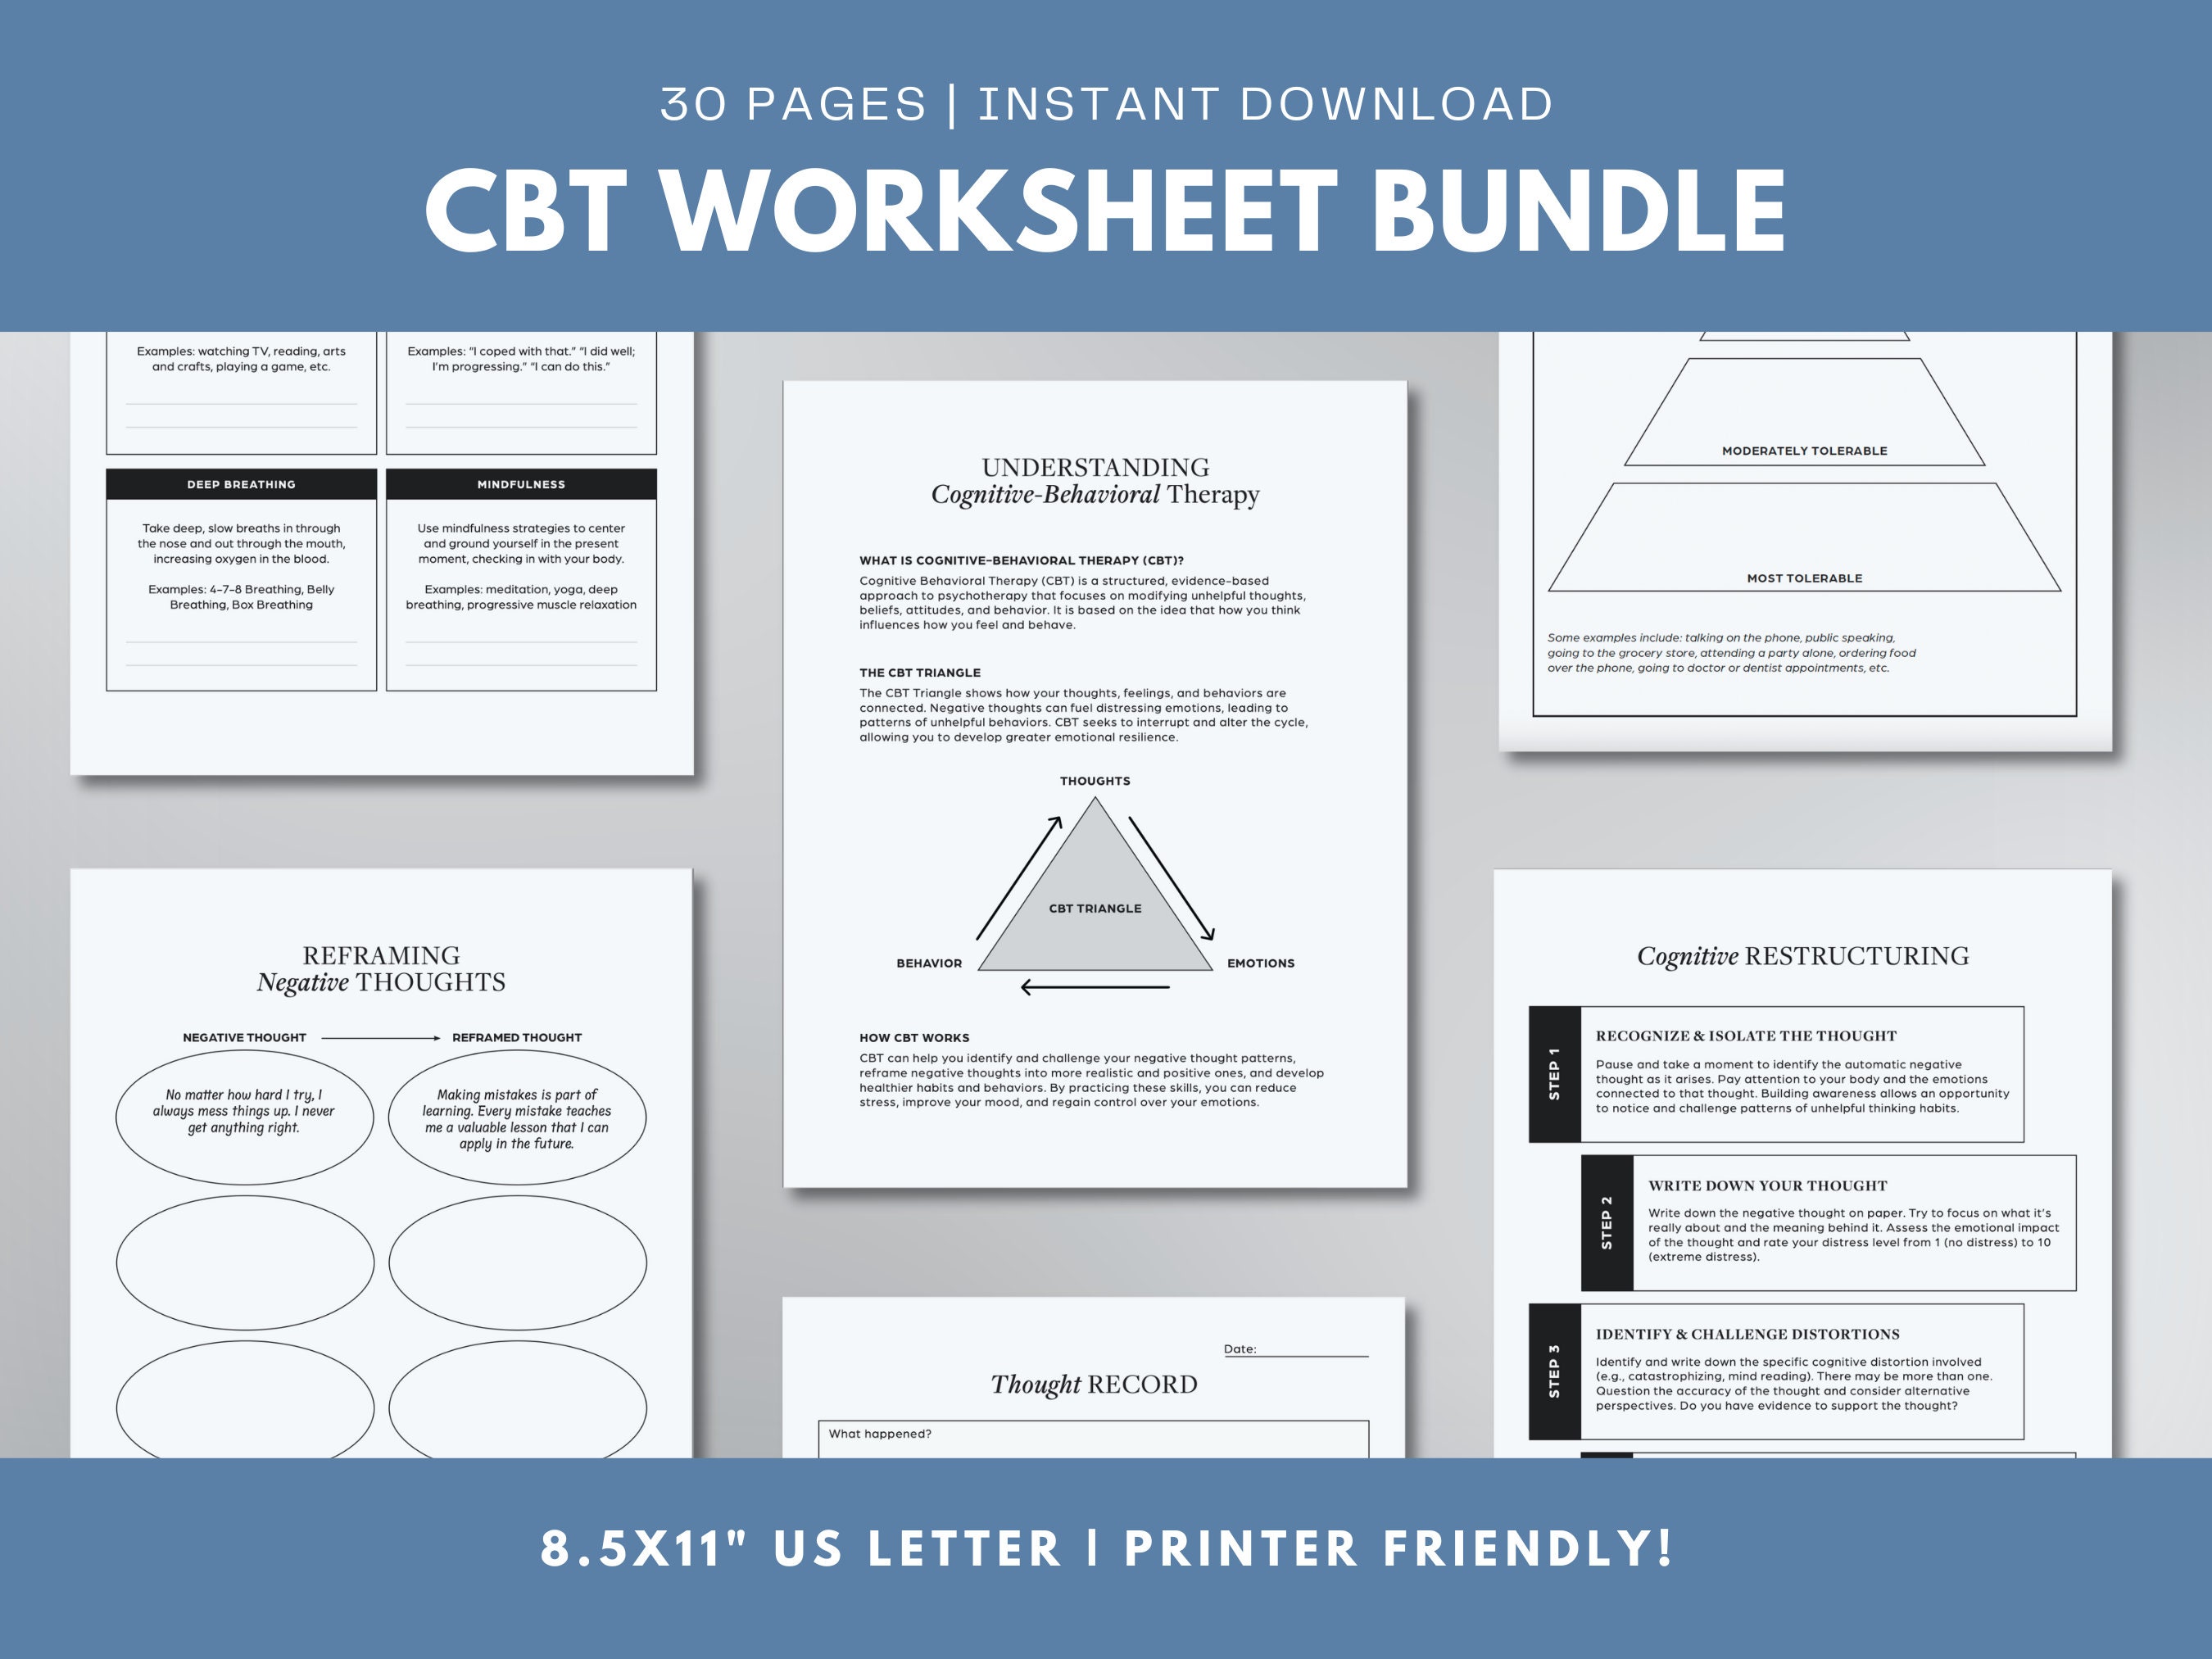
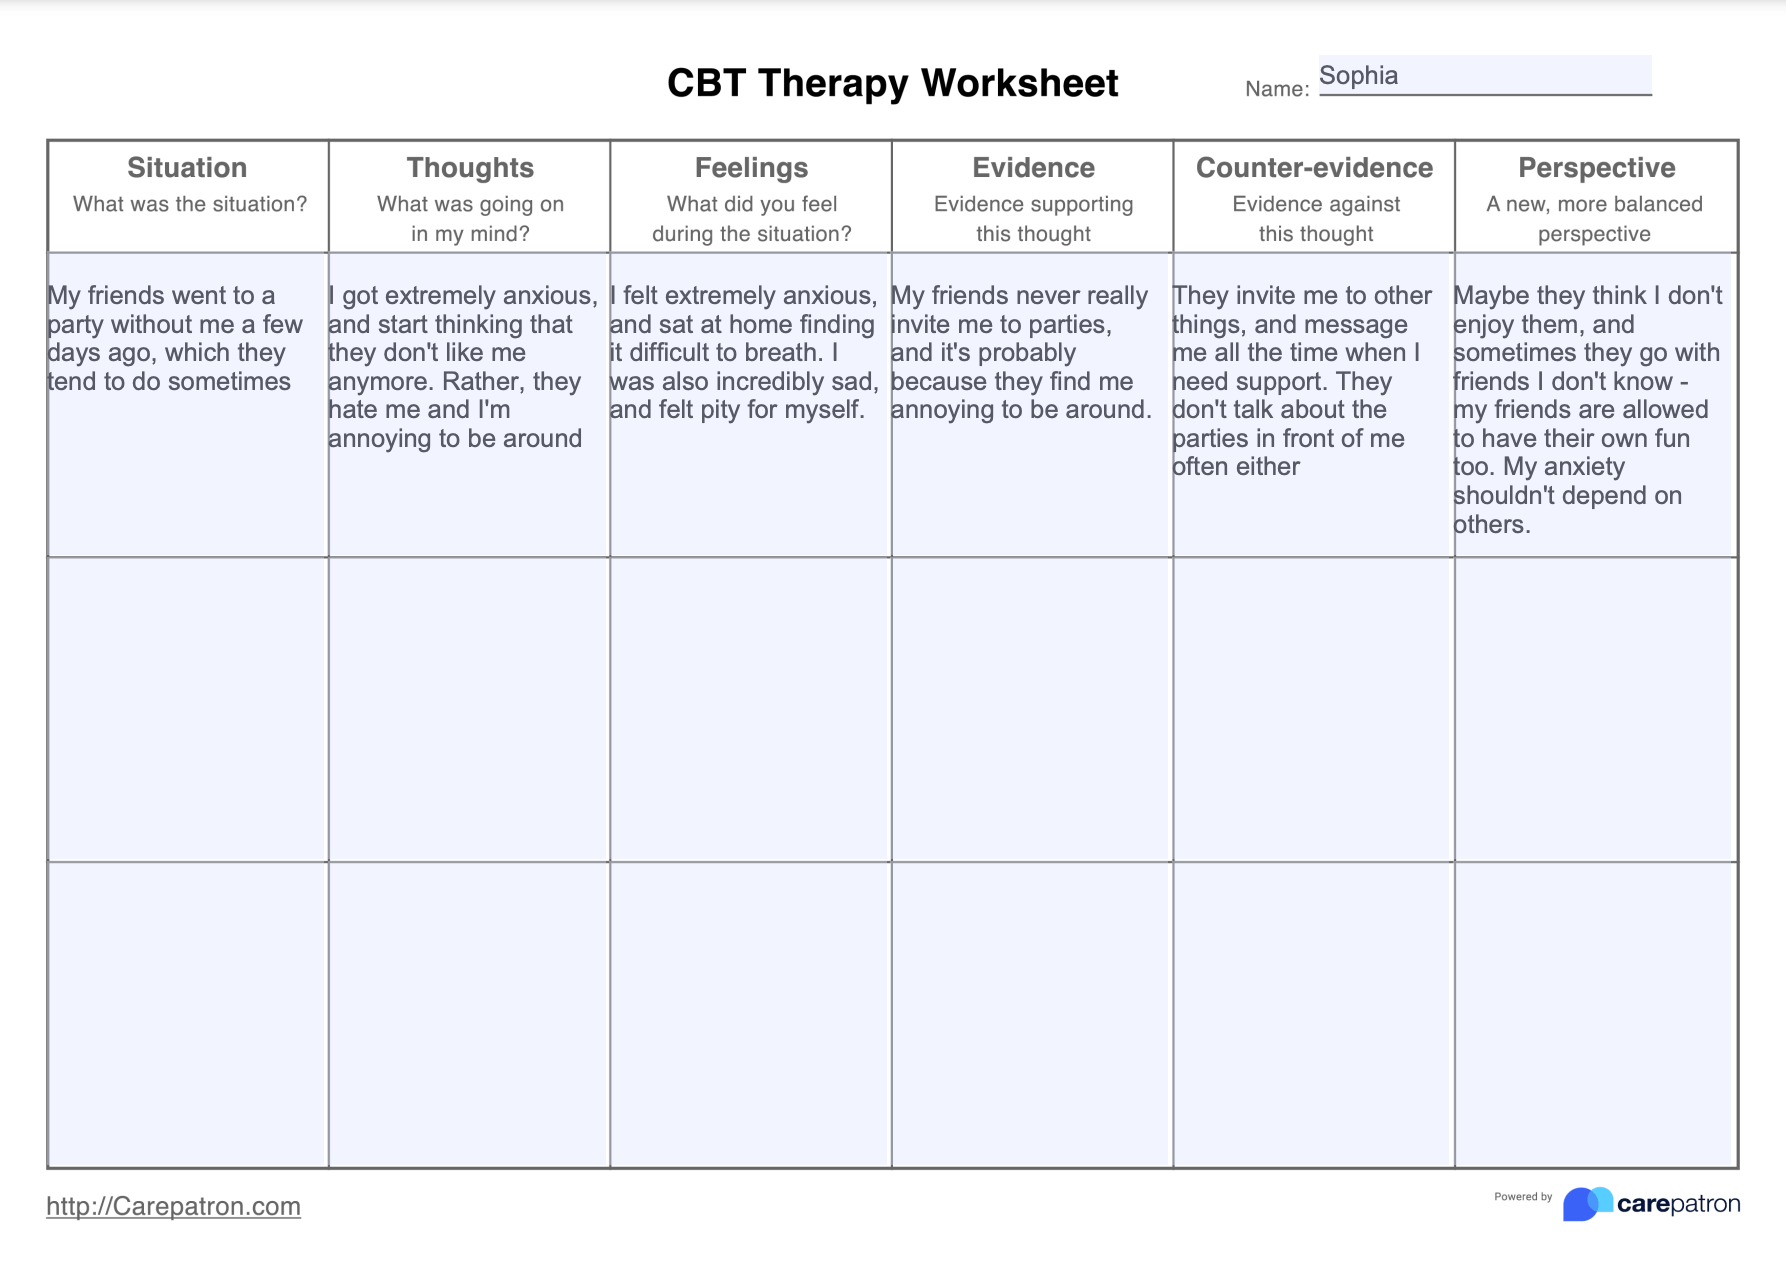
Let me explain what makes a worksheet set actually work for this population, because there's a reason most free PDFs circulating online fail in practice. I've collected over two hundred different versions across my career, and roughly sixty percent are unusable without significant modification. The rest are fine but incomplete—usually heavy on thought records and light on the emotional regulation modules that seniors actually need most. The core format breaks down into a few standard types, and knowing which one you're looking at saves you about twenty minutes of sorting before you even start. Thought records are the most common. They ask the person to identify a distressing situation, note the automatic thought, assign an emotion rating, and then challenge that thought with evidence. For younger clients this works cleanly. For seniors, the automatic thought often involves decades-old cognitive schemas around worthlessness, burdening others, or the belief that recovery is impossible at their age. The worksheet needs to leave enough white space for someone with reduced fine motor control to actually write in it. Half the worksheets I've seen have line spacing designed for a twenty-two-year-old's handwriting speed.
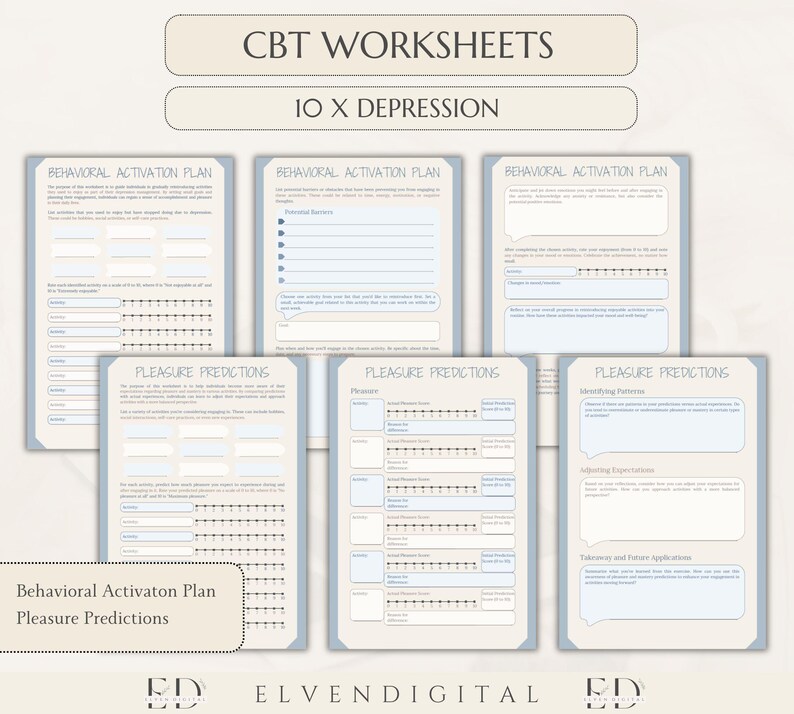
Behavioral activation grids are another staple. These map out activities across a week and rate pleasure and mastery. Seniors respond differently to the mastery component than younger people do. A younger client might feel a genuine boost from completing a moderate task. An older adult with chronic pain or mobility limits often interprets the same scale as evidence they're failing. I learned this the hard way with a client named Margaret, seventy-nine, who'd been scoring her activity completion at four out of ten consistently. I thought she was being overly self-critical. Turns out the worksheet didn't account for the fact that she'd had hip surgery three months prior and was genuinely working within severe physical constraints. She wasn't rating her effort—she was rating her outcome. We switched to a modified version that asked for effort-based scoring instead, and her engagement jumped immediately. Social connection inventories are the third type that actually moves the needle. Loneliness in seniors isn't just an emotional problem—it's a structural one. The worksheet should prompt someone to identify existing weak ties (the postal worker, the pharmacist, the neighbor they nod to) and build from there. Most generic versions skip this entirely and go straight to "call a friend," which isn't helpful when the friend group has shrunk to zero over the past decade. Here's the part nobody mentions in the downloadable descriptions: the answer key matters more than the worksheet itself for this demographic. A senior working through these materials alone or with a caregiver needs to know whether they're on the right track. The answer key shouldn't just show the "correct" response—it should demonstrate the reasoning process. "My daughter called but I felt ignored" paired with "I assumed she was annoyed because she kept checking her phone, but she was actually on speakerphone while cooking dinner" is the kind of example that teaches the skill. A bare answer key that just says "thought distorted: mind reading" teaches nothing.
Get the Full Details
I found this repeatedly with a batch of worksheets from a commercial provider. The answer key was essentially a checklist of cognitive distortions. My group participants couldn't use it because they didn't understand how to apply the labels to their own thinking. I rewrote the keys to show full examples of each distortion in context, and completed a few sample rows myself. That took about forty-five minutes for a twenty-page packet, and it was the single biggest improvement we made to the program. There are also specific pitfalls that make or break these materials: Print size. Anything smaller than twelve-point font becomes a struggle within fifteen minutes of reading. Twelve-point is the bare minimum; fourteen or fifteen is preferable for extended worksheets.
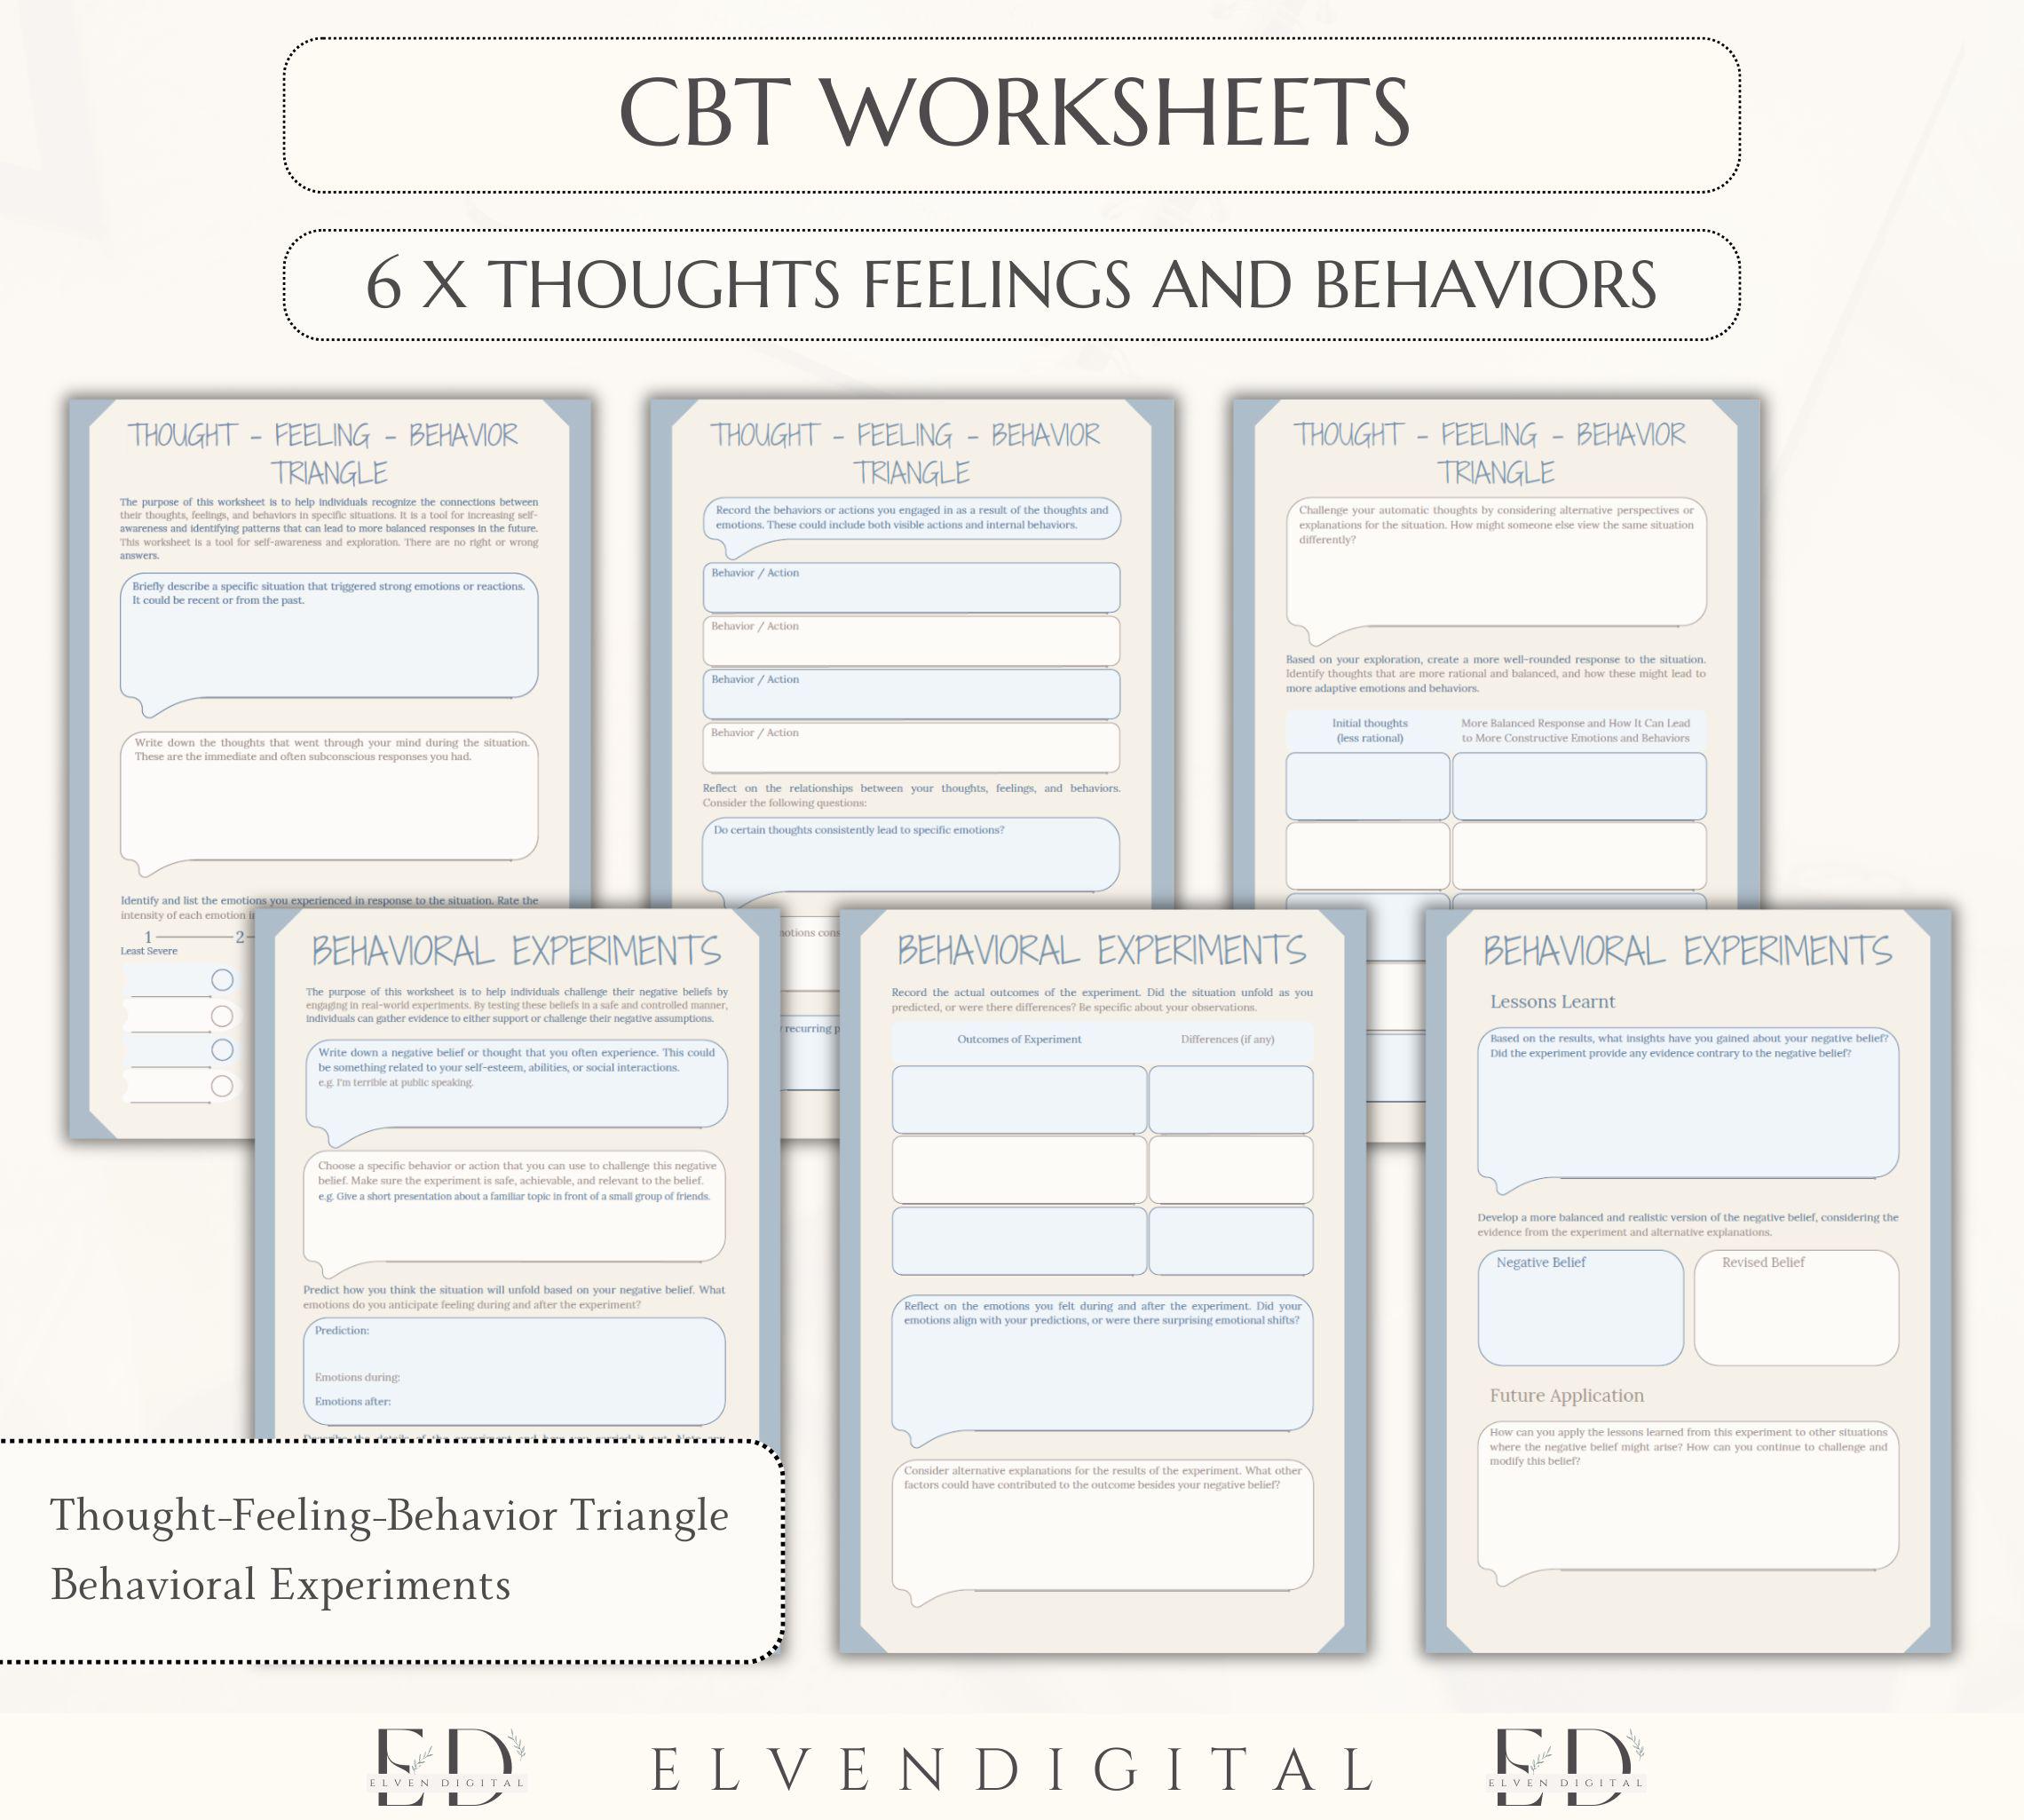
Cognitive load per page. Each worksheet should address one concept. When you pack thought recording, behavioral tracking, and emotion labeling onto the same page, working memory gets overloaded. Seniors with mild cognitive impairment especially can't hold multiple instructions in mind while also processing the emotional content. Assumptions about literacy level. Some worksheets assume college-level reading comprehension. Standardized CBT instruments were often normed on younger, more educated populations. A senior with a GED who's otherwise sharp can still choke on passages written at a ninth-grade level when they're already dealing with depression. Ageist framing. This is the quiet killer. Worksheets that use examples centered on retirement, grandchildren, or "the last chapter of life" assume a narrative that not every senior lives. A seventy-two-year-old who's still working part-time and has no children responds poorly to prompts that frame their situation as inherently sorrowful. I removed every reference to grandchildren from a widely-used packet and replaced it with neutral examples involving daily routines and social interactions. The materials didn't need to be about aging—they needed to be about the cognitive patterns that aging can amplify.
If you're putting together a set or selecting existing materials, here's a practical workflow that's worked for me: Start by identifying the primary presenting issue. Depression, anxiety, grief, chronic pain adjustment—each one pulls different CBT techniques into focus. Don't use a general workbook and hope it covers everything. It won't. Review each worksheet individually against the usability criteria above. Cut anything that feels like filler. I've seen packets that repeat the same thought record format three times with minor wording changes. That's redundant, not thorough.
Write or commission custom answer keys that model the thinking process rather than just labeling responses. The difference between "that's catastrophizing" and a fully worked example showing how to catch a catastrophic prediction and test it against real evidence is the difference between a worksheet that sits unused and one that actually builds skill. Test with at least two people from the target demographic before distributing widely. One person's comfort level with font size and layout might be normal for them and impossible for someone else. I use a rule of thumb: if two out of five test readers struggle with a page, rewrite it. No exceptions. The honest limitation I want to flag is this: worksheets without ongoing therapeutic support have a steep drop-off rate after approximately three to four sessions. A senior will complete the first packet enthusiastically, then stop showing up. The material itself isn't the problem—the isolation that makes consistent independent practice difficult is. If you're distributing these to someone who doesn't have regular contact with a therapist or a trained facilitator, the likelihood of sustained engagement drops significantly. In those cases, pairing worksheets with a weekly check-in call or a caregiver review session makes the difference between completion rates of around seventy percent and twenty percent.
For the best results, look for materials that were specifically normed or piloted with older adult populations, not just rebranded general CBT workbooks. The difference shows up in the examples, the pacing, and the answer key quality. Most commercially available sets that claim to be "senior-friendly" are just larger fonts applied to the same underlying materials. That helps marginally. It doesn't fix the structural issues I described above. I typically recommend starting with a small pilot—five to seven worksheets covering thought records, behavioral activation, and one emotion regulation module—before investing in a full packet. You'll learn more about what actually lands with your specific population in two weeks of trial use than you will from reading any product description. The answer key is where you'll see the most immediate gains. Getting that right transforms a worksheet from a form-filling exercise into an actual teaching tool.