Starting Cdk4 6 Inhibitor Therapy: What Actually Happens
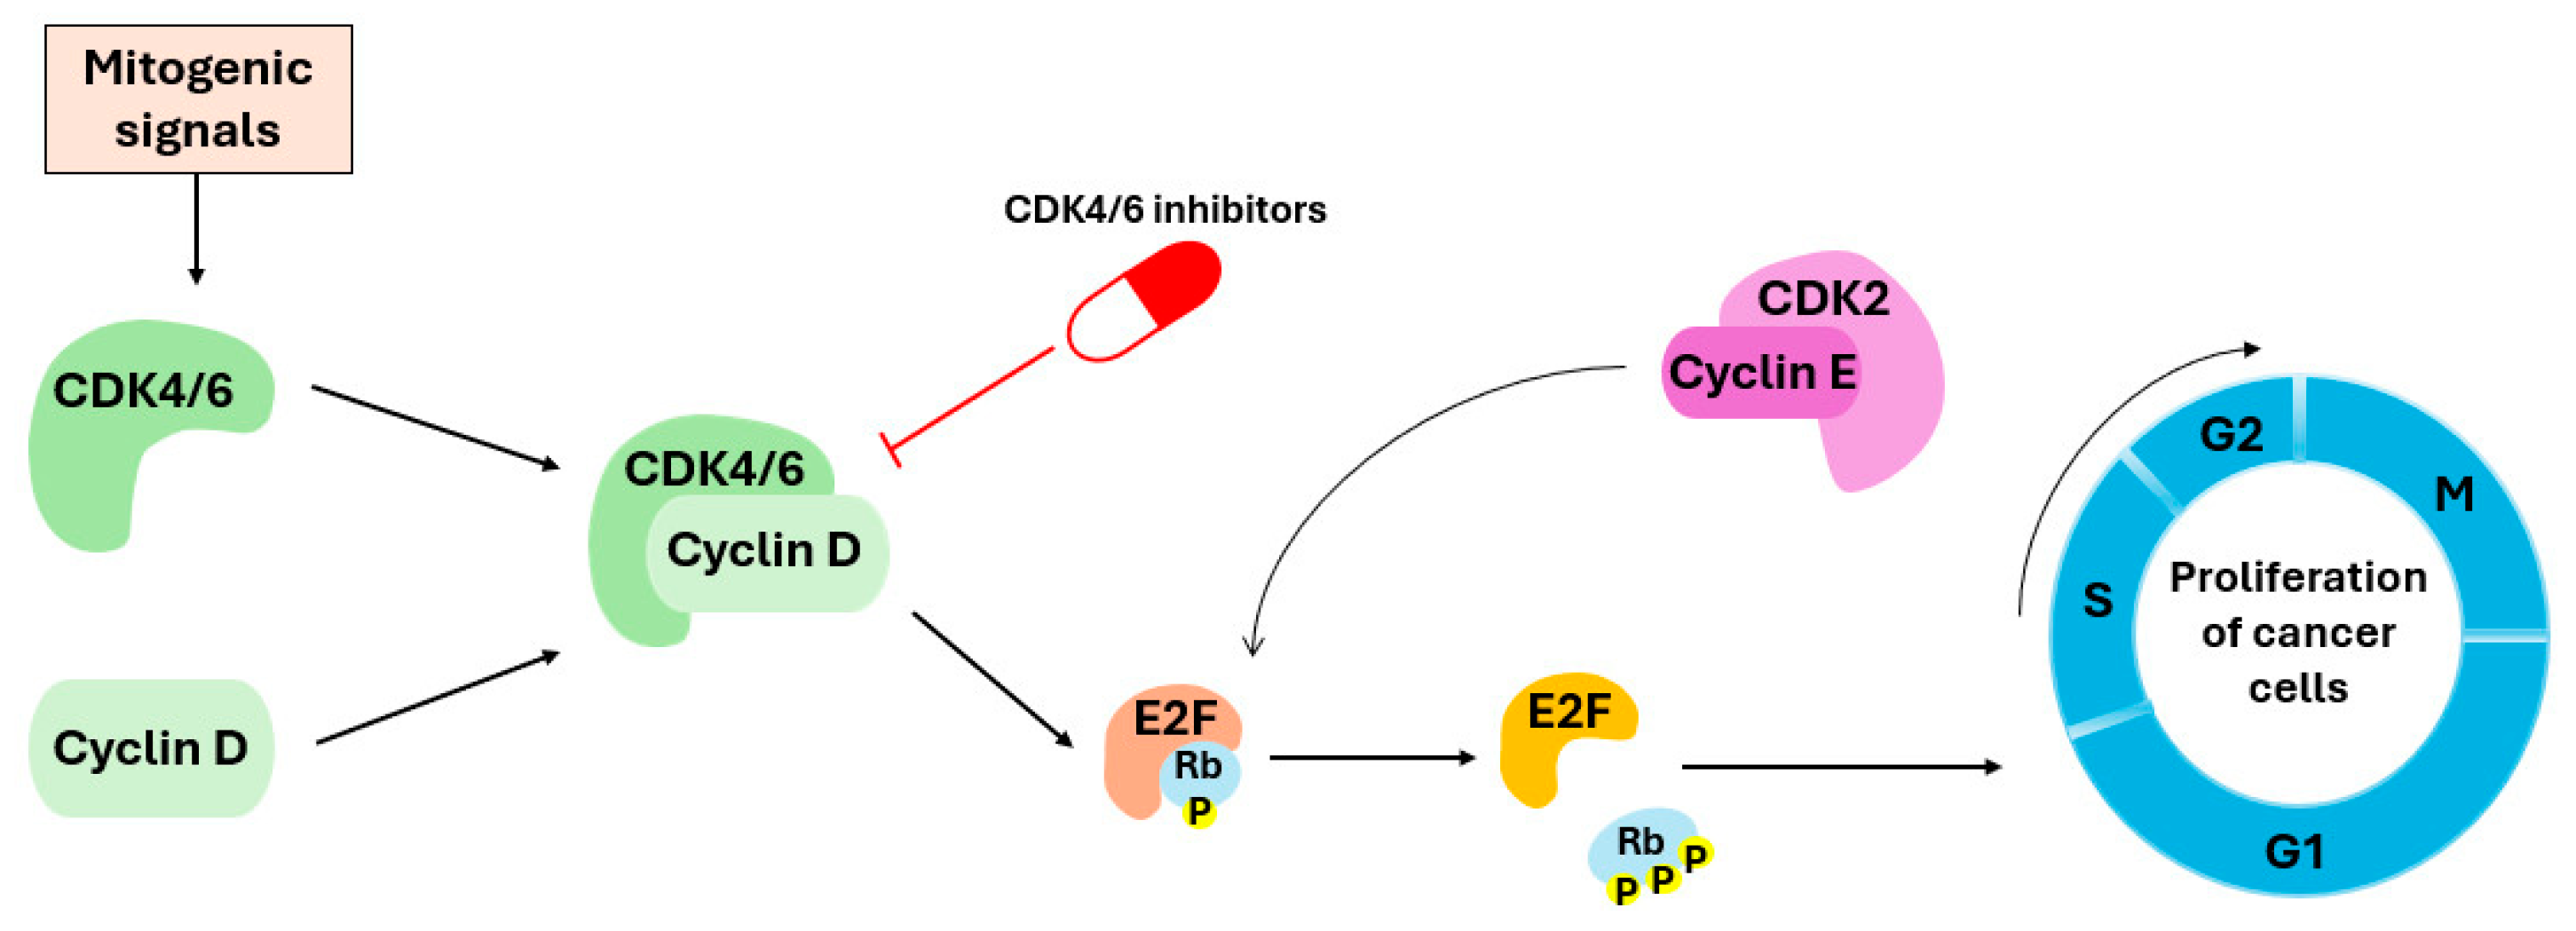
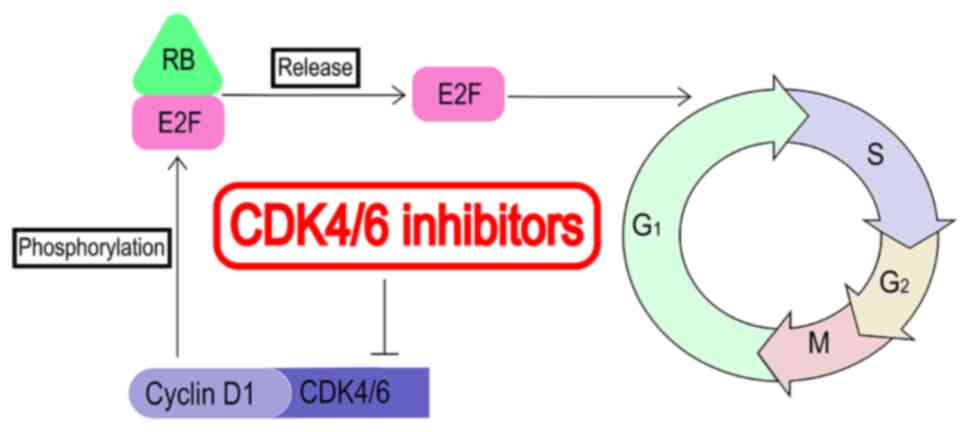
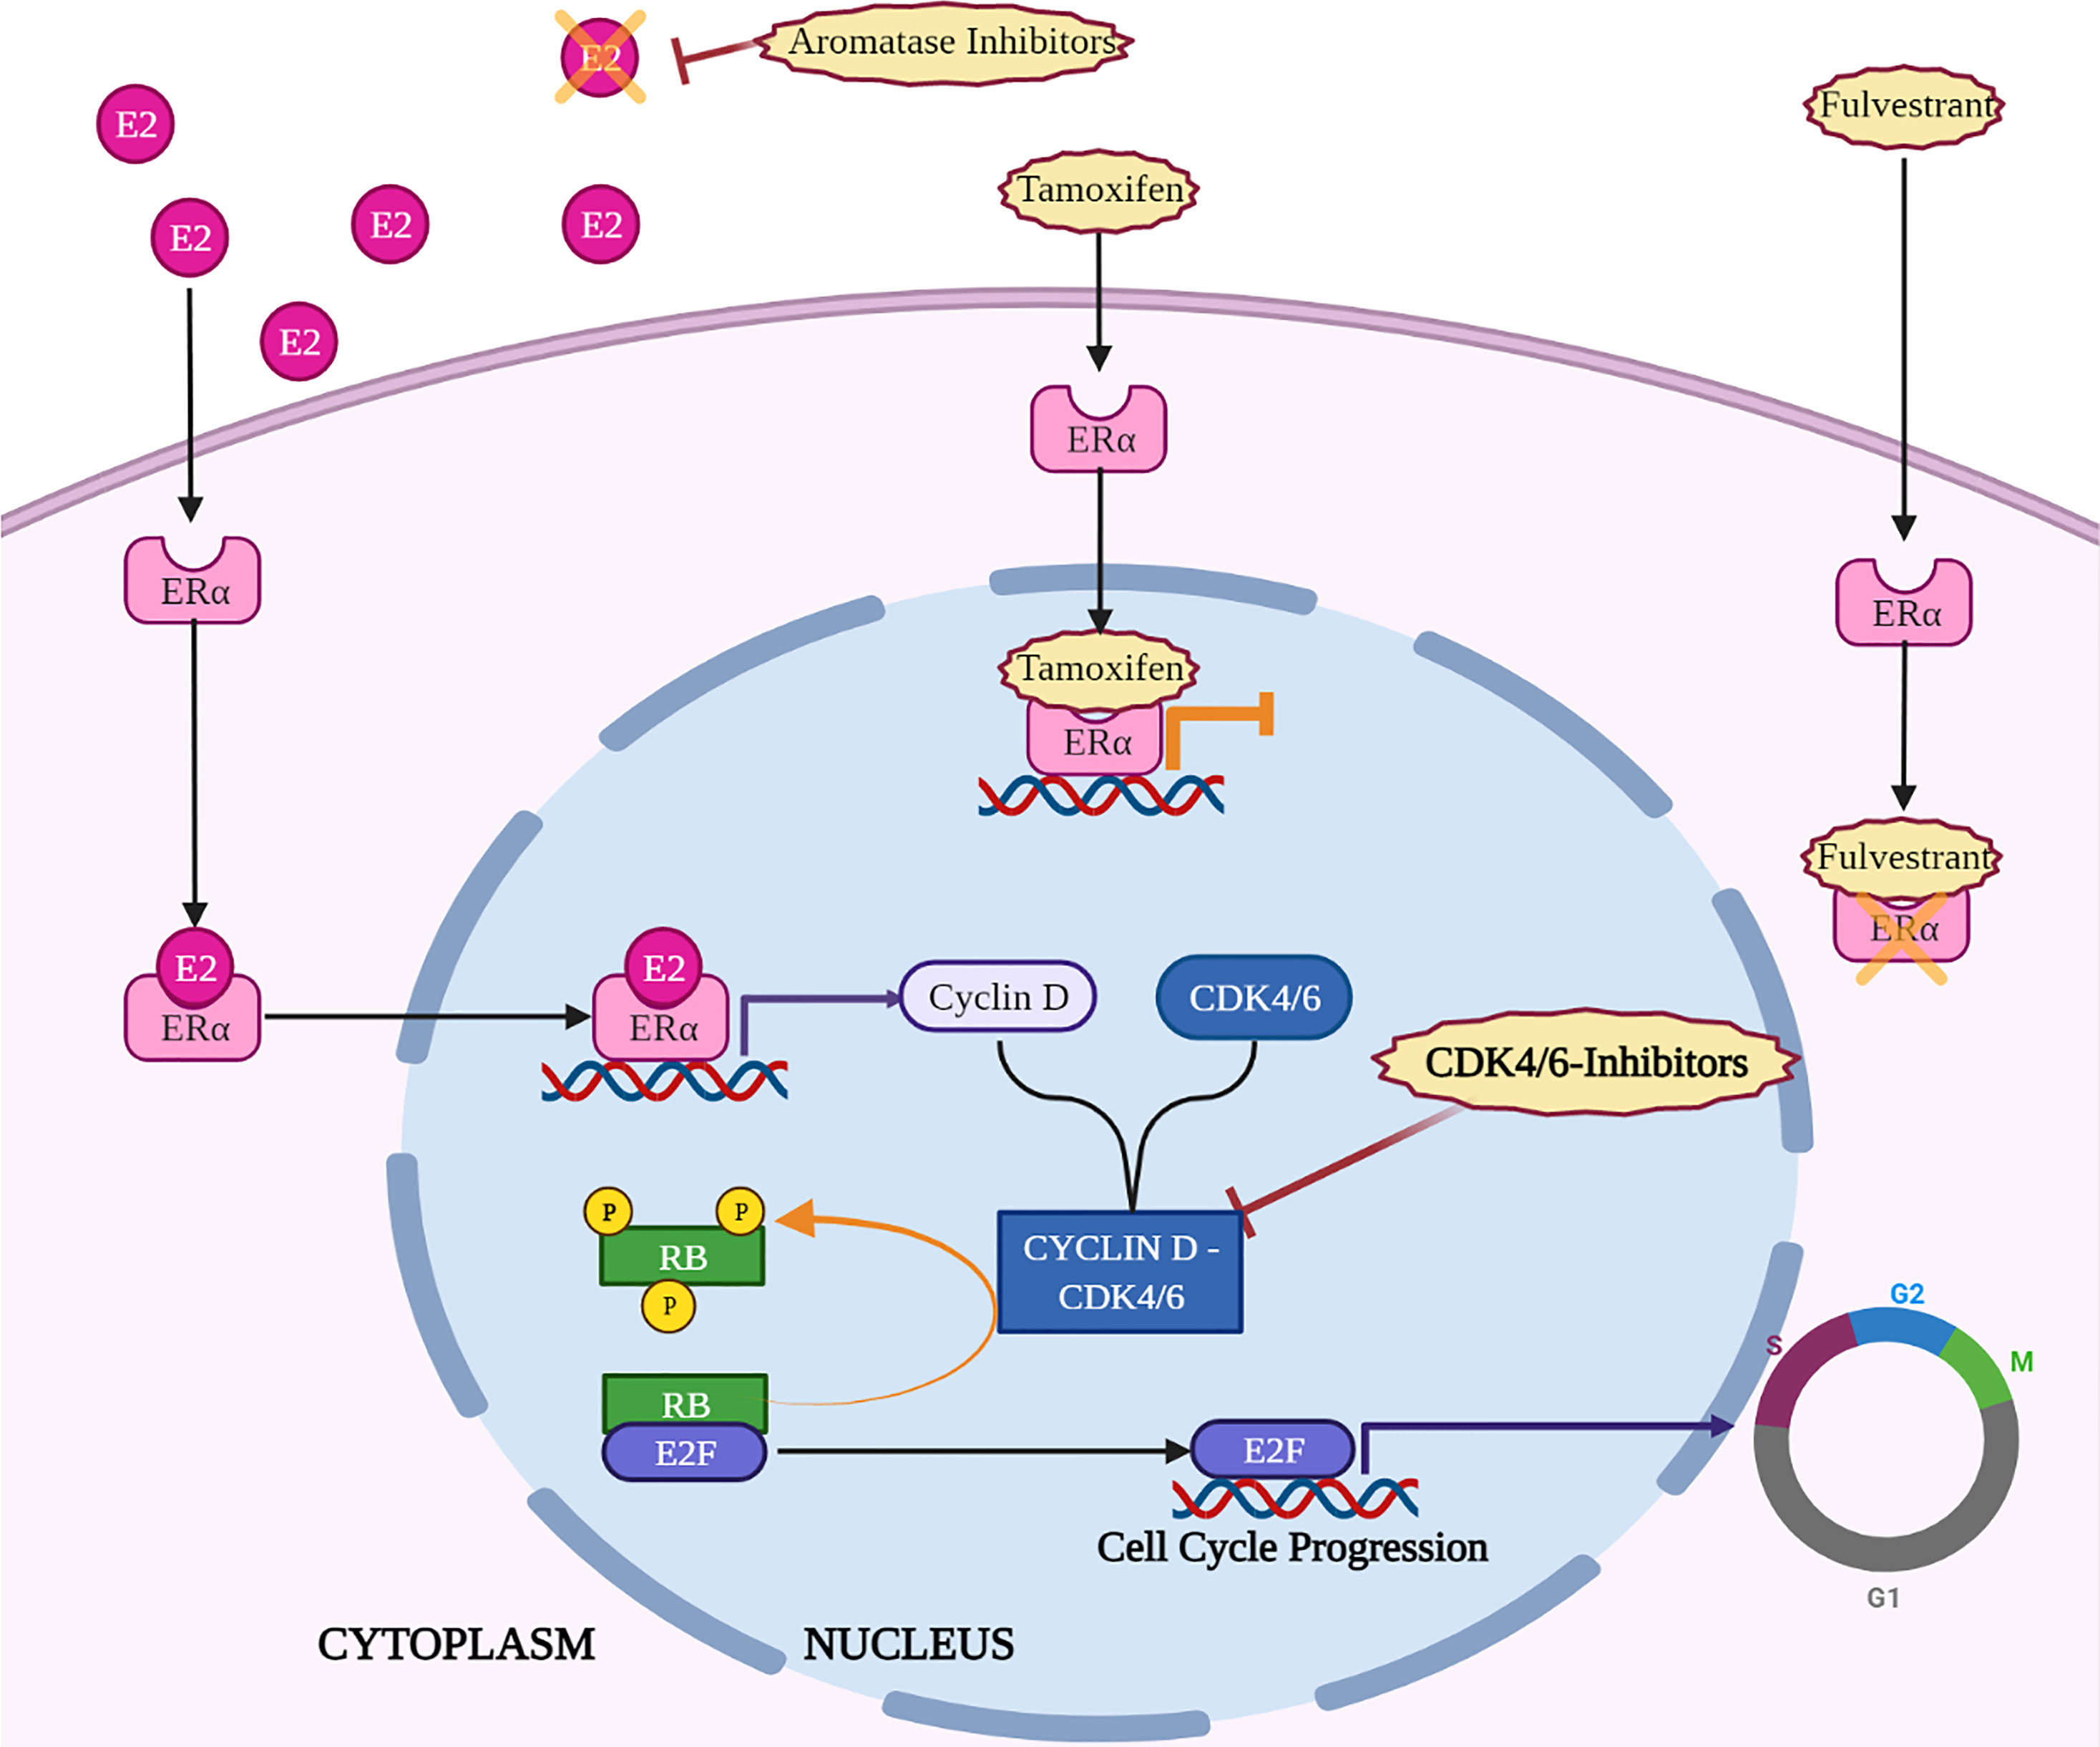
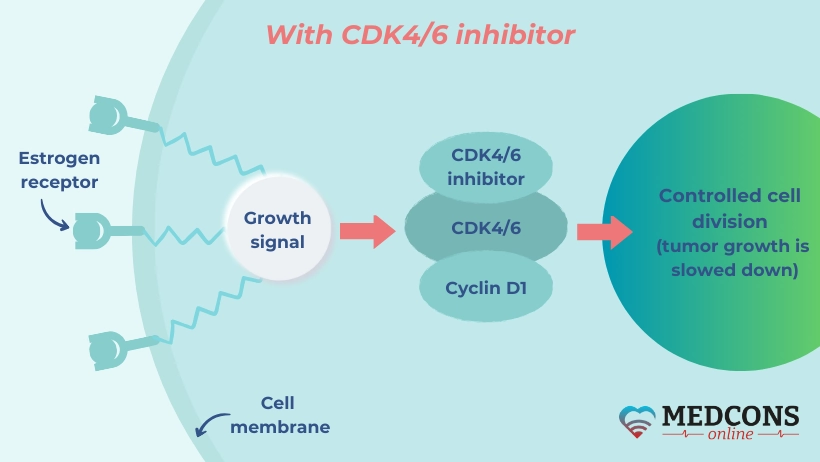
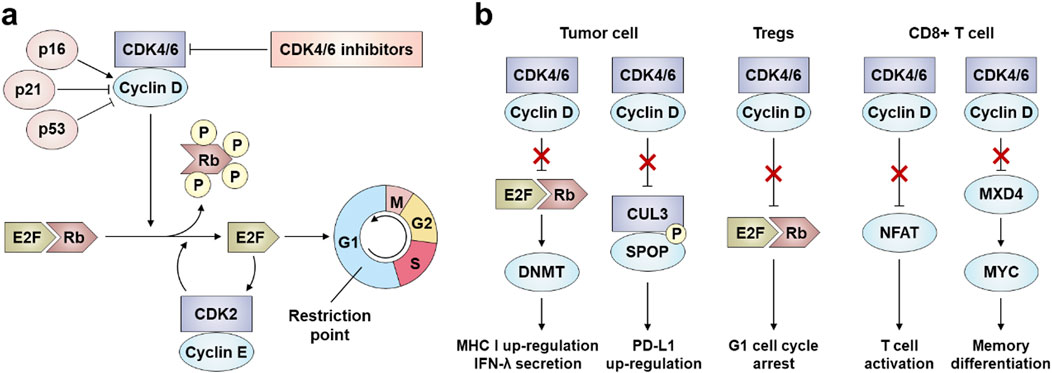
When I first started working with patients on this class of drugs, the biggest misconception was that these are gentle, well-tolerated pills. They are not. Palbociclib, ribociclib, and abemaciclib each have their own personality when it comes to side effects, and if you go in thinking this is simple oral chemotherapy, you will get burned. The mechanism itself is straightforward enough. These drugs block CDK4 and CDK6, which are enzymes that drive the cell cycle from G1 into S phase. In hormone receptor-positive breast cancers that overexpress cyclin D, this pathway is often hyperactive. Block it and you stall proliferation. That is the theory. The reality in clinical practice involves managing neutropenia, figuring out who actually develops QT prolongation versus who just has a benign ECG change, and dealing with the fact that two of these drugs can make your patients miserable if you do not dose-adjust properly.
Choosing Between the Three Cdk4 6 Inhibitor Therapy Options
Not long ago I had a patient on palbociclib who presented with Grade 3 neutropenia at cycle 2. Standard protocol says hold and reduce to 100mg. I did that, but the neutrophils barely recovered before the next cycle started. I switched her to ribociclib instead and monitored her CBCs more aggressively. She tolerated it better at the standard 600mg daily dose for 21 days on, 7 days off. The reason has to do with inter-individual variability in how patients metabolize each drug. Some people clear palbociclib slowly and accumulate it. Others handle ribociclib better. There is no reliable predictive biomarker for this yet, so you end up switching based on toxicity profile rather than pretreatment prediction. Abemaciclib is the outlier in this class. It causes significant diarrhea in roughly 50% of patients, often starting within the first week. I had a patient who lost 8 pounds in ten days on day one because I started at the full 150mg dose instead of doing the recommended dose escalation. That was my mistake. Now I always start at 100mg daily for the first two weeks and titrate up if tolerated. Loperamide is your friend, but prevention through slow titration is better than reaction.
Monitoring That Actually Matters
Blood counts are the obvious one. Baseline CBC with differential before starting any CDK4/6 inhibitor. Then weekly for the first two cycles, then every other week. Neutropenia is almost universal with palbociclib, but it is mostly Grade 1 or 2. Grade 3 and 4 neutropenia happens in about 60-70% of patients on standard doses, yet febrile neutropenia is rare at under 2%. That distinction matters because most clinicians do not need to be as aggressive with G-CSF support as they might be with traditional chemotherapies. With ribociclib, the thing nobody warns about enough is QTc prolongation. The median QTc increase is around 7 milliseconds, but some patients push into dangerous territory. I always check a baseline ECG and repeat it after the first cycle. If QTc goes above 480ms, you stop the drug. The interaction potential is also higher here. Ribociclib is metabolized through CYP3A4, and anything that inhibits or induces that enzyme will change exposure substantially. Strong CYP3A inhibitors like ketoconazole can increase ribociclib exposure by 2-3 fold. Strong inducers like rifampin can drop it by half. I saw a patient whose ribociclib levels became subtherapeutic because her antifungal prophylaxis was switched to something that induced CYP3A4 without checking the interaction first. Liver function tests matter too. Transaminitis occurs, especially with ribociclib, and it is usually reversible on. Abemaciclib is less hepatically toxic but more gastrointestinal toxic. Pick your poison based on your patient's comorbidities.
Get the Full Details
What Nobody Tells You About Long-term Use
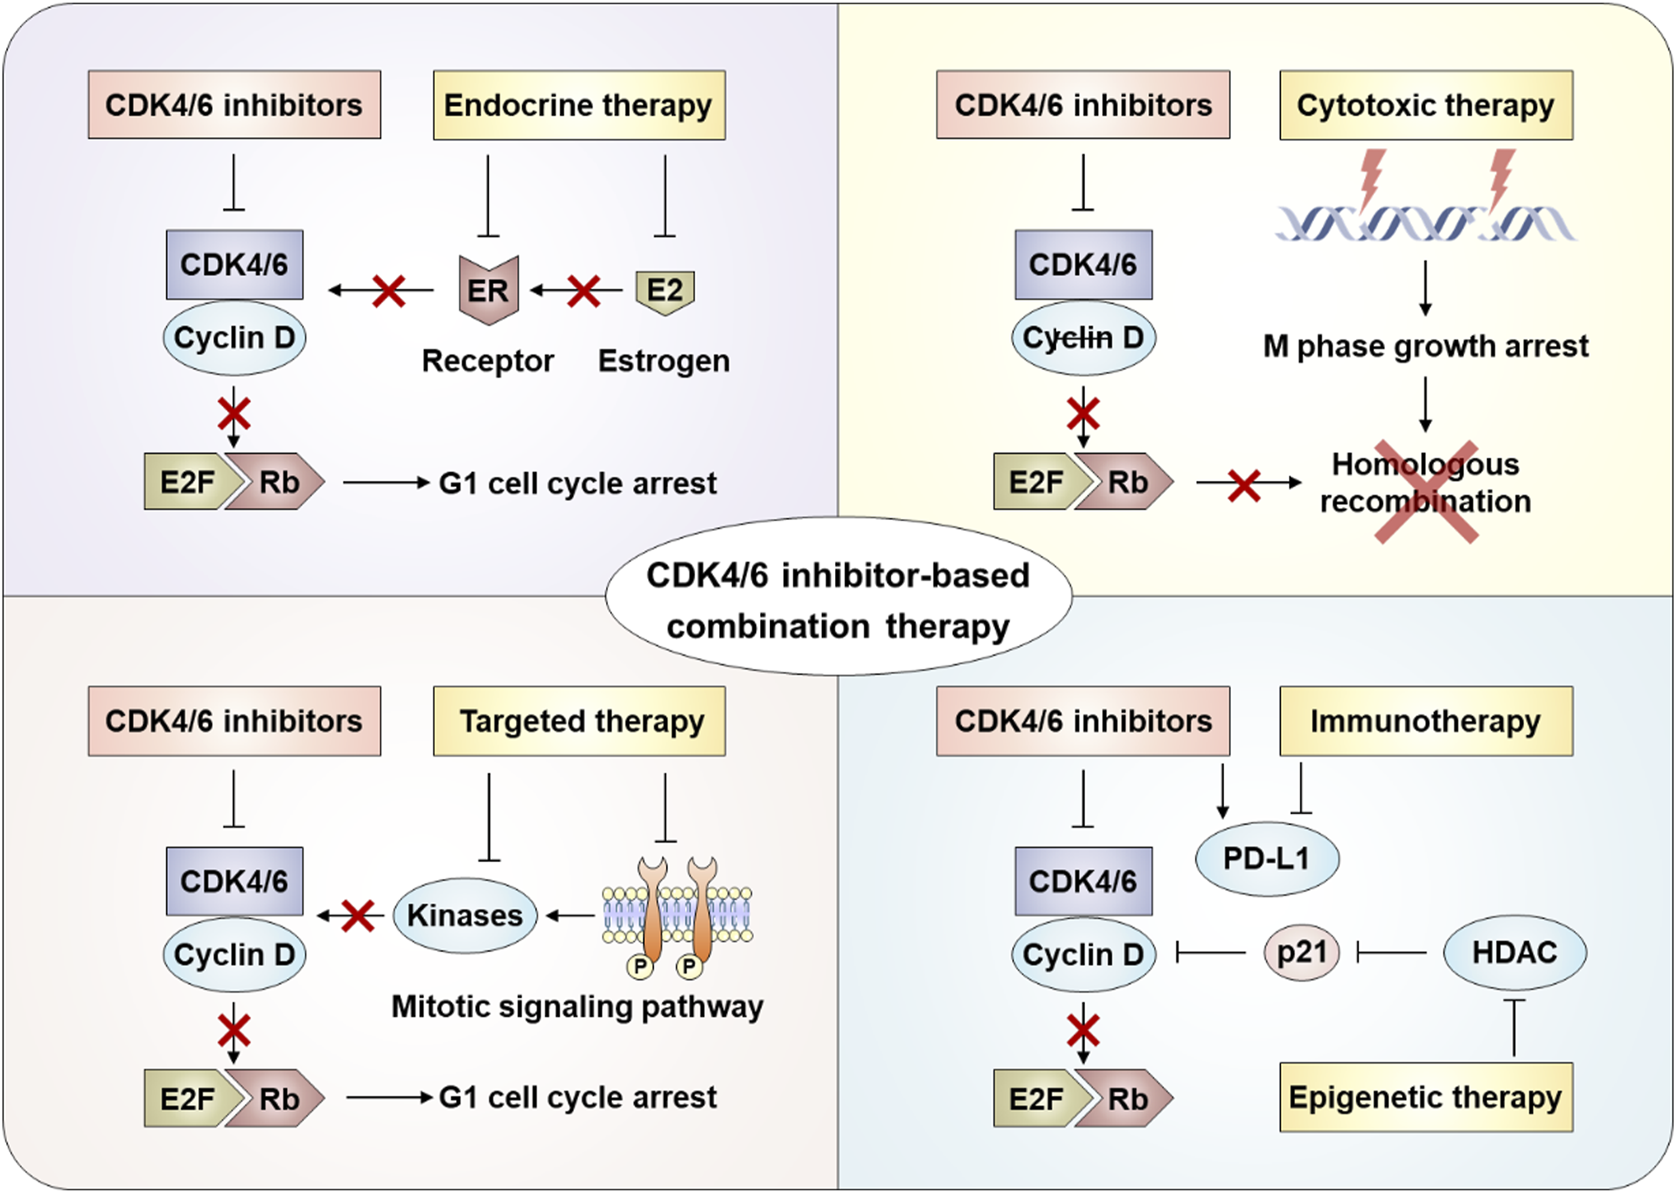
These drugs are generally continued until disease progression or intolerable toxicity. There is no set treatment duration. In practice, many patients stay on them for 1-2 years before either progressing or developing cumulative toxicity that forces a switch. Fatigue accumulates over time, and some patients just feel worse after six months than they did at six weeks. I had one patient who did well on palbociclib for fourteen months and then hit a wall of fatigue that nobody could explain. We reduced the dose, she came back slightly, and eventually we just moved on to a different endocrine combination. The combination partner also matters. Palbociclib with letrozole or anastrozole is the most established regimen. Palbociclib with fulvestrant is the second-line standard. Ribociclib has data both with an aromatase inhibitor and with fulvestrant. Abemaciclib can be used with an aromatase inhibitor or with fulvestrant, and it also has monotherapy data in later lines. The choice of partner drug can influence which CDK4/6 inhibitor you pick. If the patient has cardiac risk factors, avoid ribociclib. If they have a history of diarrhea or IBD, avoid abemaciclib. If they have liver concerns, lean toward abemaciclib or palbociclib over ribociclib.
Dose Modifications That Save Treatment
Here is where experience separates people who quit early from people who complete cycles. Most dose reductions happen because of neutropenia or fatigue. For palbociclib, the reduction steps are 125mg down to 100mg down to 75mg. Each reduction requires holding the drug until neutrophils recover to at least 1500, then restarting at the lower dose. This usually takes 1-2 weeks per hold. I once managed a patient through three dose reductions over eight months and she stayed on therapy for two years total. She never had a single febrile neutropenic event. The key was proactive growth factor support. I started G-CSF prophylaxis at the first sign of persistent Grade 3 neutropenia rather than waiting for it to become febrile. That decision alone prevented two ER visits and kept her on treatment longer than expected. For ribociclib, dose reductions go from 600mg to 400mg to 200mg. The drug holidays between cycles give the bone marrow a chance to recover, but fatigue tends to worsen with each rechallenge at a lower dose. abemaciclib reductions go from 150mg to 100mg to 50mg twice daily, and the diarrhea risk does not necessarily decrease proportionally with dose. That one is frustrating because patients who need dose reductions the most are often the ones whose quality of life degrades the fastest.
When Cdk4 6 Inhibitor Therapy Just Does Not Work
Not every HR+ HER2- patient responds. Primary resistance happens in maybe 20-30% of cases. Risk factors include high Ki-67 at diagnosis, visceral metastases, and certain molecular alterations. I saw a patient recently with an ESR1 mutation who progressed through palbociclib plus letrozole in under four months. That mutation changes the game entirely. The standard approach after that kind of early progression is to switch to a different endocrine backbone, often fulvestrant with a PI3K inhibitor if the patient is PIK3CA mutated, or to consider clinical trial enrollment if available. Hypercalcemia of malignancy is another situation where these drugs can cause problems. CDK4/6 inhibitors can theoretically increase bone resorption markers, and in patients with extensive bone metastases, that can tip into symptomatic hypercalcemia. I monitor calcium every cycle in patients with significant bone disease. It is easy to miss if you are only watching CBCs and LFTs. There is no single answer to managing resistance, and the field is moving faster than the guidelines can keep up. The combinations being tested right now with immunotherapy, with PI3K inhibitors, and with selective estrogen degraders will likely reshape how we sequence these drugs within a few years. Until then, the basic principles still apply: pick the right drug for the right patient, monitor aggressively, and be ready to adjust before a crisis happens.