What Centered Therapy Activities Actually Look Like in Practice
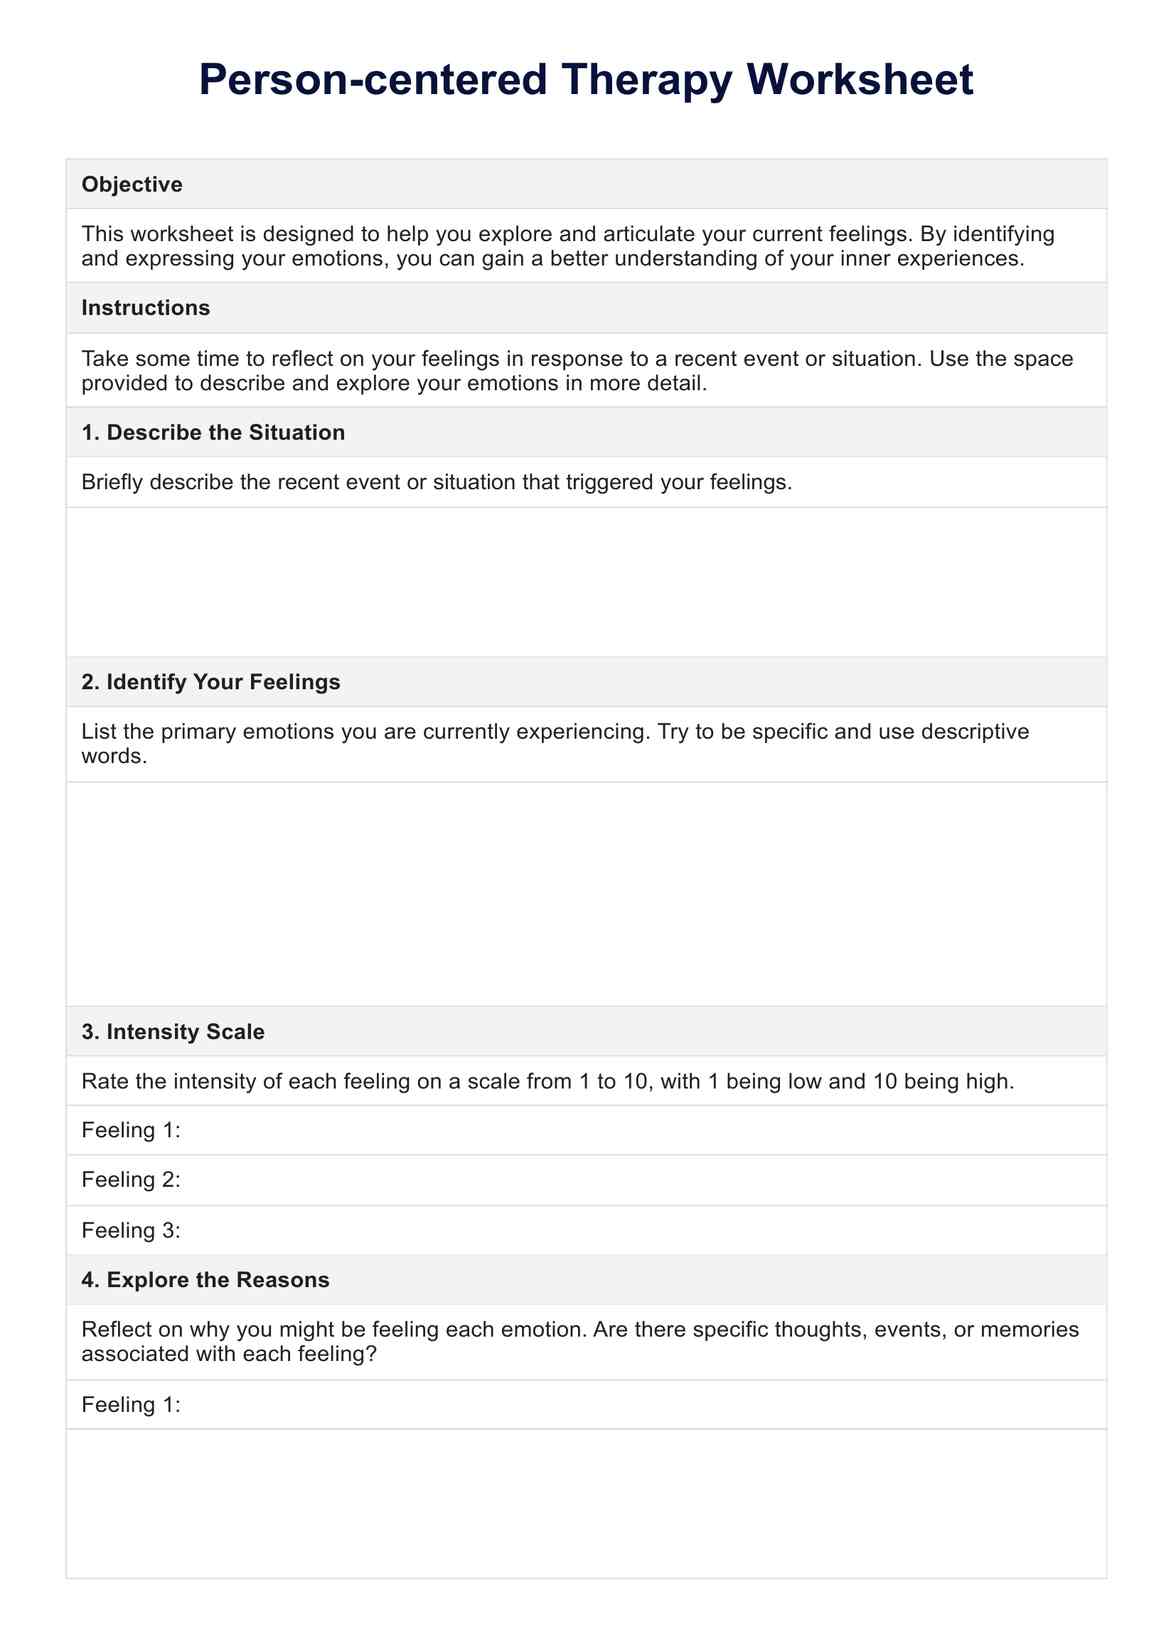
Most people assume centered therapy activities are just free-form conversation exercises, but the reality is messier than that. The core idea comes from person-centered therapy — Rogerian roots, basically — where the therapist creates conditions for growth rather than directing the process. The "activities" are really structured opportunities for clients to explore their own frame of reference without feeling steered. I've run hundreds of these sessions over the years, and the gap between theory and practice is where everything falls apart. The fundamental setup is deceptively simple. You pick an activity that requires some degree of self-reflection or emotional engagement, then you step back and let the client fill in the meaning. Common formats include guided journaling prompts, role reversals where the client plays the therapist, image-based projection exercises, and structured empathy mapping. The trick isn't in choosing the right activity — it's in knowing when to stay quiet and when to gently redirect without imposing your own interpretation.
Centered Therapy Activities
Here's the practical breakdown of how I structure these sessions now. I start by establishing the activity parameters clearly, usually in about two minutes. Then I hand it off completely. During a 50-minute session, I spend roughly 30 to 40 minutes in active silence or minimal prompting. The activities themselves typically fall into three categories: reflective exercises that ask the client to externalize internal states, relational exercises that explore how the client interacts with others, and somatic exercises that draw attention to physical sensation as data. One thing nobody tells you about centered therapy activities is that silence is the primary tool. Beginners keep filling gaps because they feel uncomfortable with it. That discomfort is exactly what needs to stay present. When a client trails off mid-thought, most new therapists jump in with "Can you say more about that?" or "What are you feeling right now?" Both of those are technically fine, but they're also leading questions that pull the client toward whatever the therapist considers valuable. The more skilled move is a slight lean forward, a nod, and waiting. Most clients will produce something more useful in that gap than they would in response to a direct prompt. It took me about two years of supervised practice to stop feeling like I was failing when I sat through 90 seconds of silence. Another thing that catches people off guard is the difference between empathic reflection and paraphrasing. They sound the same on paper. Paraphrasing repeats what the client said in slightly different words. Empathic reflection names the emotion underneath it. If a client says "My boss never listens to me and I feel like I'm going crazy," paraphrasing would be "So you feel your boss doesn't hear you." Empathic reflection would be "It sounds like you're carrying a lot of frustration and maybe some loneliness in that dynamic." The difference matters because centered therapy activities depend on the client feeling genuinely seen, not just repeated back. Get this wrong and the whole exercise collapses into a mechanical Q-and-A session that serves no therapeutic purpose.
I ran into a specific problem a few years ago that changed how I approach these activities entirely. A client kept redirecting every exercise back to intellectual analysis. No matter what centered therapy activities I introduced — journaling, imagery, role reversal — they would articulate the insight perfectly and then immediately detach from the emotional content. It was like watching someone read a map instead of walking the terrain. Standard technique says to gently point out the pattern and explore it in session. I tried that for about six months with diminishing returns. What eventually worked was switching to somatic-centered activities instead of purely cognitive ones. Rather than asking the client to reflect on their feelings, I had them sit with a blank sheet of paper and draw the shape of whatever they were experiencing in their body without trying to make it look like anything recognizable. Then they described the drawing without referencing any life events. The intellectual bypass didn't work when the exercise bypassed language entirely. It felt almost unfair, but it was genuinely the first time that client accessed affective material in a sustained way. Not every client responds to this, but it's worth keeping in your toolkit when the standard reflective approach plateaus. There are real limitations to centered therapy activities that most introductory materials gloss over. The approach depends heavily on the client having a basic capacity for introspection and verbal expression. Clients with significant dissociation, acute psychosis, or severe cognitive impairment often can't engage with these activities effectively, and pushing them can actually cause regressions or increased distress. The therapist also needs genuine competence in holding space without subtly steering. A poorly delivered centered therapy session is worse than having no structure at all because it gives the false impression that the client is making progress when they're actually performing compliance.
Get the Full Details

Time investment is another practical constraint. Centered therapy activities typically require longer sessions than directive approaches because you're waiting for organic emergence rather than extracting predetermined outcomes. A 50-minute slot is usually the minimum viable window. Anything shorter tends to produce superficial material that dissipates before it can be processed. If you're working in a setting with strict time limits — community mental health, EAP models, school counseling — you'll need to adapt significantly or accept that centered therapy activities may not be the right primary modality for your caseload. The evidence base is solid but narrow. Randomized controlled trials support person-centered approaches for anxiety, depression, and relationship issues, but the research mostly examines whole therapeutic approaches rather than specific activities. This means you can't point to a particular exercise and say it has X level of empirical support. The effectiveness lives in the therapeutic relationship itself, which is both the strength and the bottleneck. You can't standardize what works, which makes training and supervision essential. If you want to start practicing these, the foundational reading is still Rogers' On Becoming a Person and Becoming a Person. Those aren't activity manuals — they're philosophical frameworks — but understanding the underlying theory prevents you from turning centered therapy activities into just another technique checklist, which is the most common failure mode I see. For practical activity collections, I'd recommend looking at the work of Bob Taft and Eugene Gendlin on experiential therapy, which gets closer to the actual mechanics of what happens in a room when centered work is done well.
The bottom line is that centered therapy activities are about creating conditions, not applying interventions. The activities are scaffolding. The real work happens in the quality of attention the therapist brings to the space between prompts. That's harder to teach than any specific exercise, and it's what separates practitioners who use centered therapy activities from those who just run reflection worksheets and call it therapy.