Getting Speech Therapy for Cerebral Palsy: What Actually Works
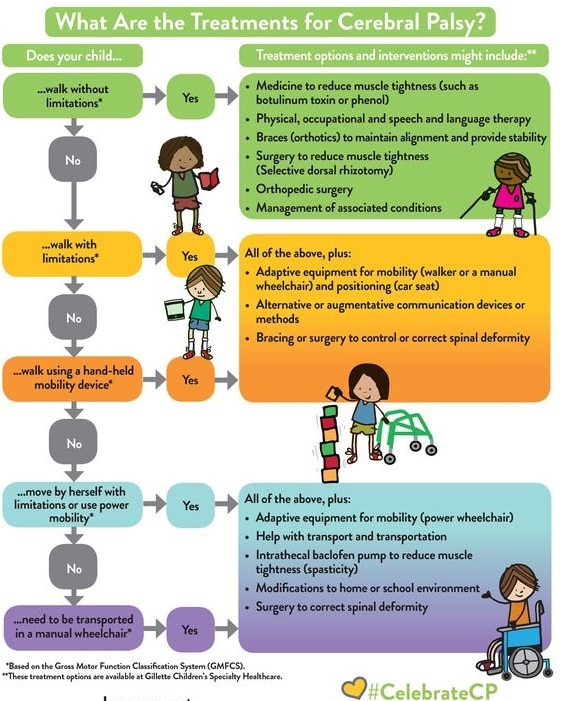
I spent about six years working with pediatric SLPs who specialized in neurogenic communication disorders, and the stuff they do for kids with cerebral palsy is not what most parents expect. The therapy isn't a single protocol. It is a patchwork of approaches that gets tailored based on the individual, and it takes longer than you want it to take. Cerebral palsy affects motor control, and when that involves the muscles used for speech, swallowing, and breathing, communication becomes the bottleneck. Speech-language pathology in this population targets three areas simultaneously: speech production, language comprehension and expression, and alternative communication methods when needed. Not every person with CP has speech difficulties, but roughly 60 to 70 percent do according to clinical literature. The range is enormous because CP is a spectrum. Dysarthria is the most common speech motor disorder seen here, and it presents differently depending on whether the underlying tone issues are spastic, dyskinetic, or ataxic. Spastic dysarthria sounds strained and effortful. Dyskinetic dysarthria produces irregular breakdowns in articulation and prosody. Ataxic dysarthria creates slurred, scanning speech with poor volume control. These distinctions matter because the treatment strategies diverge significantly.
How Sessions Actually Work
A typical session starts with an assessment baseline if it is the first visit, and everything after that is iterative. For children who already have some intelligible speech, the work focuses on increasing clarity through breath support, pacing, and articulatory precision. For those with minimal verbal output, the trajectory runs toward establishing reliable symbolic communication rather than forcing speech that may never become efficient for daily use. AAC, augmentative and alternative communication, comes up earlier than most people anticipate. I once worked with a child whose family resisted any form of alternative communication because they feared it would suppress whatever speech potential remained. That child was four years old and nonverbal. We introduced a picture-based system, and within twelve weeks he began producing consistent vocal approximations of the symbols he was selecting. The AAC did not take away his speech. It provided a scaffold that reduced the cognitive load and actually supported vocal development. That pattern shows up frequently enough that resistance to AAC should be treated as a red flag rather than a reasonable concern. Sessions are usually weekly, sometimes twice weekly for more complex cases. Each one runs forty-five to sixty minutes. Progress metrics include standardized tools like the Kaufman Speech Praxis Test, the Frenchay Dysarthria Assessment, or simply real-world intelligibility measured by caregiver report across different listening conditions. Raw intelligibility scores on standardized tests often overestimate what works in a noisy classroom or a car with the radio on. Factor that into your expectations from day one.
Counter-Intuitive Things to Know
One thing beginners miss is that more articulation drilling does not necessarily improve functional communication for this population. Repetition of isolated syllables can look productive on paper but rarely transfers to conversational speech. Better results come from embedding practice in meaningful, repeated routines where the child has a genuine need to communicate. If the child is practicing consonant-vowel combinations while sitting at a table with no reason to use them, you are wasting session time. Another counter-point involves pacing. Many clinicians default to slowing down speech as the primary intervention. That helps some individuals with spastic dysarthria. It does not help someone with hyperkinetic movements, where slowing the rate actually increases variability and makes the speech worse. For dyskinetic CP, moderate pacing with emphasis on breath group chunking tends to produce better carryover than raw slowdown. Swallowing and speech often share the same neural pathways. If a child has co-occurring dysphagia, neglecting the feeding component while focusing exclusively on articulation leaves a critical piece of the picture untapped. The two are connected enough that improving respiratory support for speech can incidentally improve swallow safety, and vice versa.
Get the Full Details

A Specific Problem I Dealt With
Speech therapy for cerebral palsy has hard limits. Severe hypotonia combined with significant cognitive-communication impairment means that even intensive intervention may only yield marginal gains in intelligibility. Some children with profound motor speech disorders will never achieve conversational-level speech clarity, and pushing them toward that goal is misleading. The honest recommendation in those cases is AAC as the primary communication system, with speech as a secondary supplement rather than the main target. Another limitation is carryover. Skill gains observed in the therapy room frequently drop by half within weeks if home practice is not maintained. Caregiver involvement is not optional. The difference between a child who maintains progress and one who regresses often comes down to whether the family has a realistic, sustainable daily routine that includes ten to fifteen minutes of structured practice. Commercial software programs marketed for home use vary wildly in quality. Some are based on legitimate therapeutic principles. Others are essentially gamified drills with no clinical rationale. Check whether the tool references established frameworks like PROMPT for motor speech, integral stimulation approaches, or AAC best practices before committing to a subscription.
Practical Steps for Families
If you are starting this process, the first step is a comprehensive evaluation by a licensed speech-language pathologist who has demonstrated experience with pediatric motor speech disorders. A generalist SLP can manage mild cases, but moderate to severe dysarthria benefits from someone who has specific training in neuromotor speech conditions. Ask about their caseload composition before you commit. If fewer than thirty percent of their current cases involve neurological motor speech disorders, you may need to look elsewhere. Document baseline intelligibility at home before sessions begin. Record short monologues in different contexts, a quiet room, a busy kitchen, a car. These recordings become your reference points. Standardized testing alone will not show you how communication actually functions across real environments. Expect the first three months to feel slow. Research and clinical observation both suggest that the initial phase often involves establishing engagement and trust more than measuring hard gains. Real measurable improvement typically emerges after six to eight weeks of consistent session attendance. If you see no directional change by week eight, revisit the treatment plan with the clinician rather than waiting blindly.
Technology can fill gaps between sessions. Dedicated AAC devices, tablets with structured communication apps, and simple voice output switches all have roles to play depending on the individual. The key is matching the technology to the person's motor abilities, cognitive level, and communication goals rather than choosing the most feature-rich option available. More buttons does not equal better outcomes. The field moves slowly, but the evidence base is real. Interventions grounded in motor learning principles, meaningful repetition, and appropriately calibrated AAC show consistent results. Approaches built on unvalidated theories about oral motor weakness producing speech problems tend not to produce durable change. Stick with methods that have published outcome data and a clinician who can explain why a specific strategy fits the individual diagnosis.