What Actually Happens in Cervical Myelopathy Physical Therapy
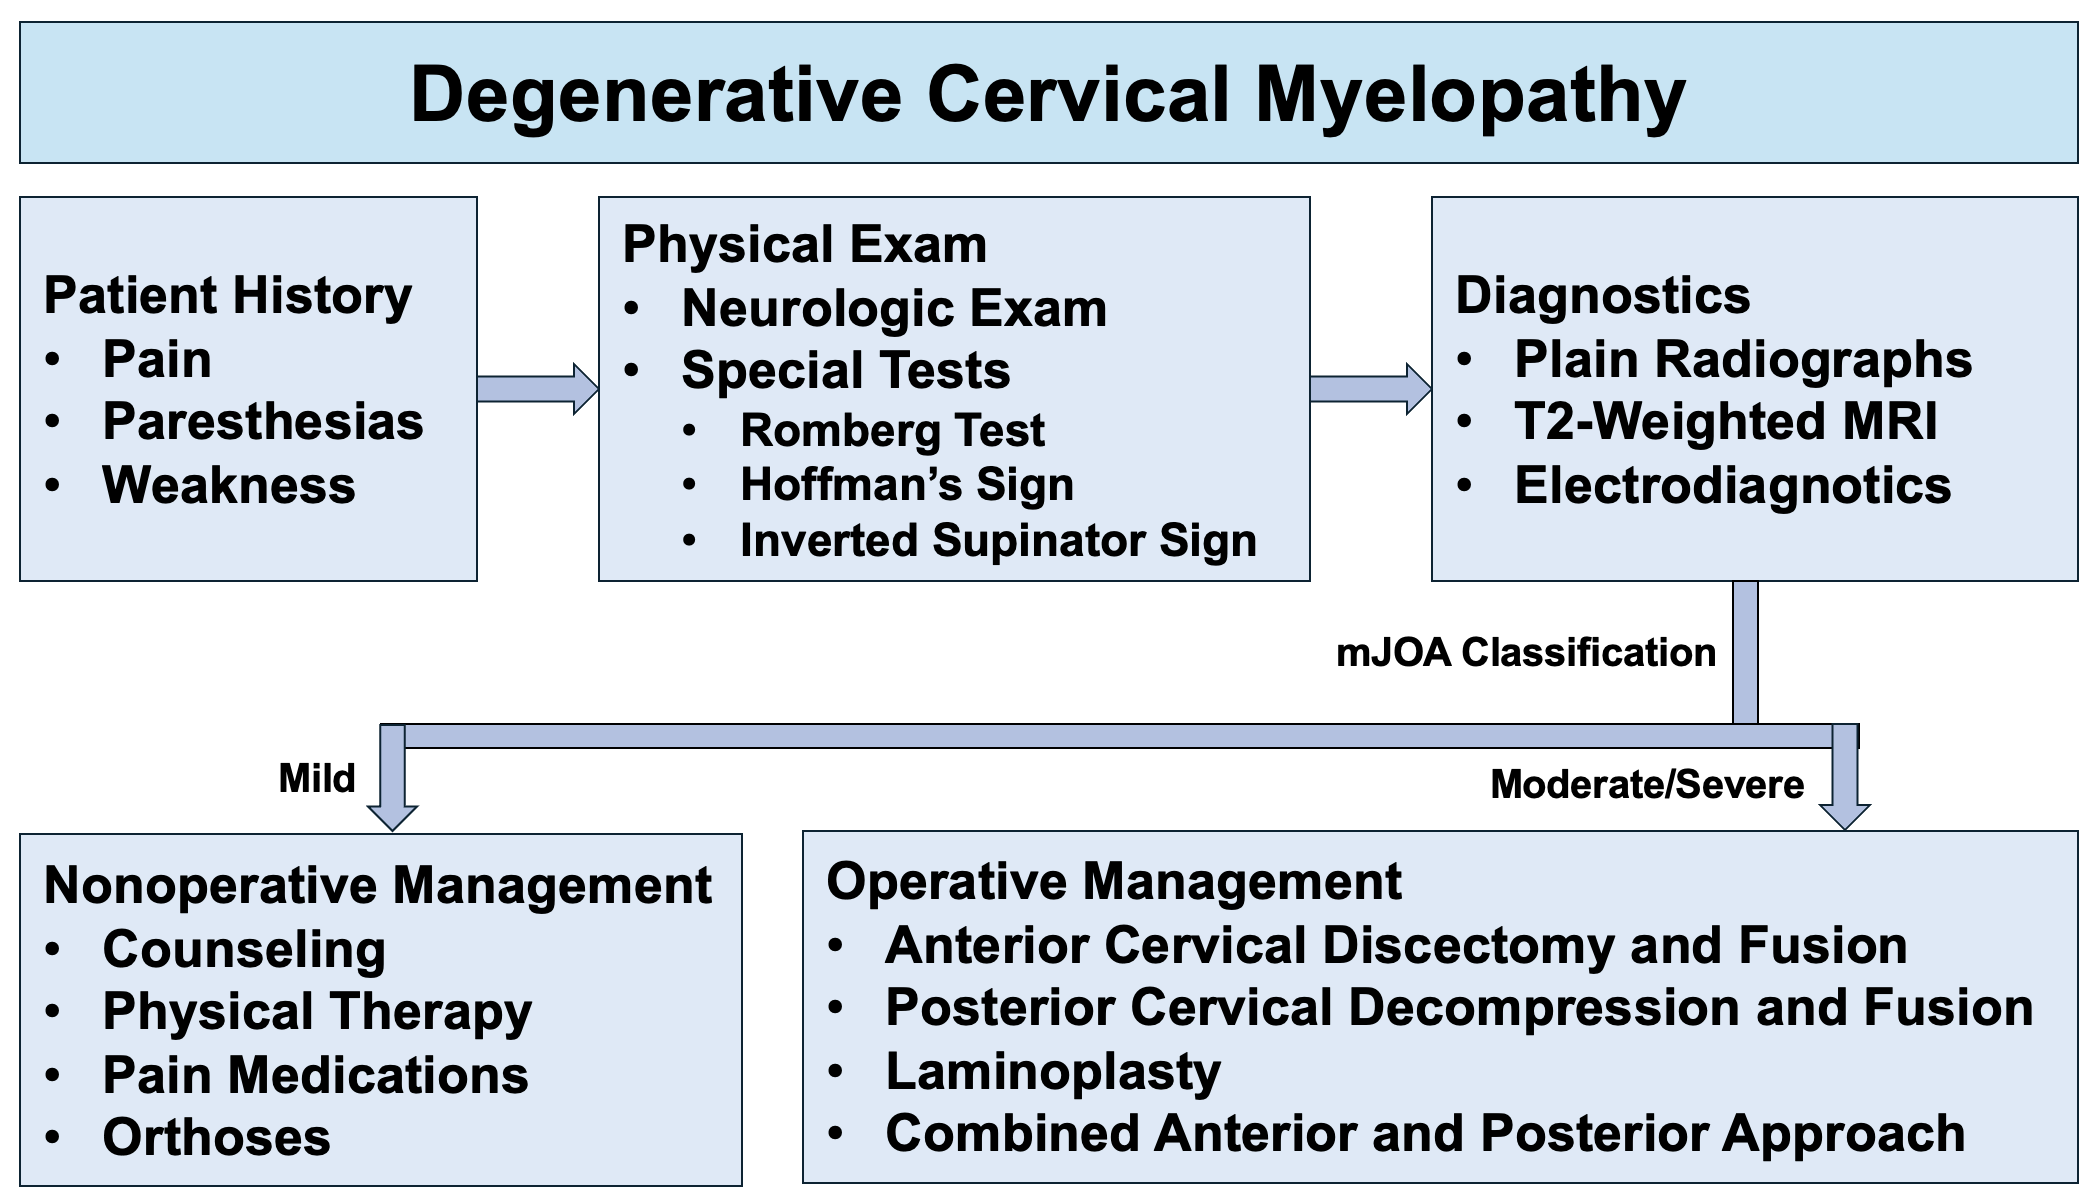
Cervical myelopathy is compression of the spinal cord in the neck, usually from degenerative changes like osteophytes, disc bulging, or ligamentum flavum hypertrophy. Patients present with gait disturbance, hand clumsiness, and upper motor neuron signs. The physical therapy approach isn't about curing the compression — it's about optimizing function and slowing decline while patients decide on or recover from surgery. Most protocols I see are built around proprioceptive retraining, cervical stabilization, and upper extremity coordination. The core idea is that even with persistent cord compression, you can improve how the nervous system navigates around the deficit. This matters because hand dexterity scores and gait speed are the two outcomes most correlated with return to independent function. The protocol I follow has three phases. Phase one covers the acute subacute window after diagnosis — usually six to eight weeks. You're doing gentle range of motion within pain-free arcs, isometric strengthening of the deep neck flexors, and balance work on stable surfaces. Phase two extends from roughly week eight to twelve, adding proprioceptive challenges like foam surfaces and dual-task gait training. Phase three is the maintenance block, typically ongoing for patients who aren't surgical candidates or are waiting for decompression surgery.
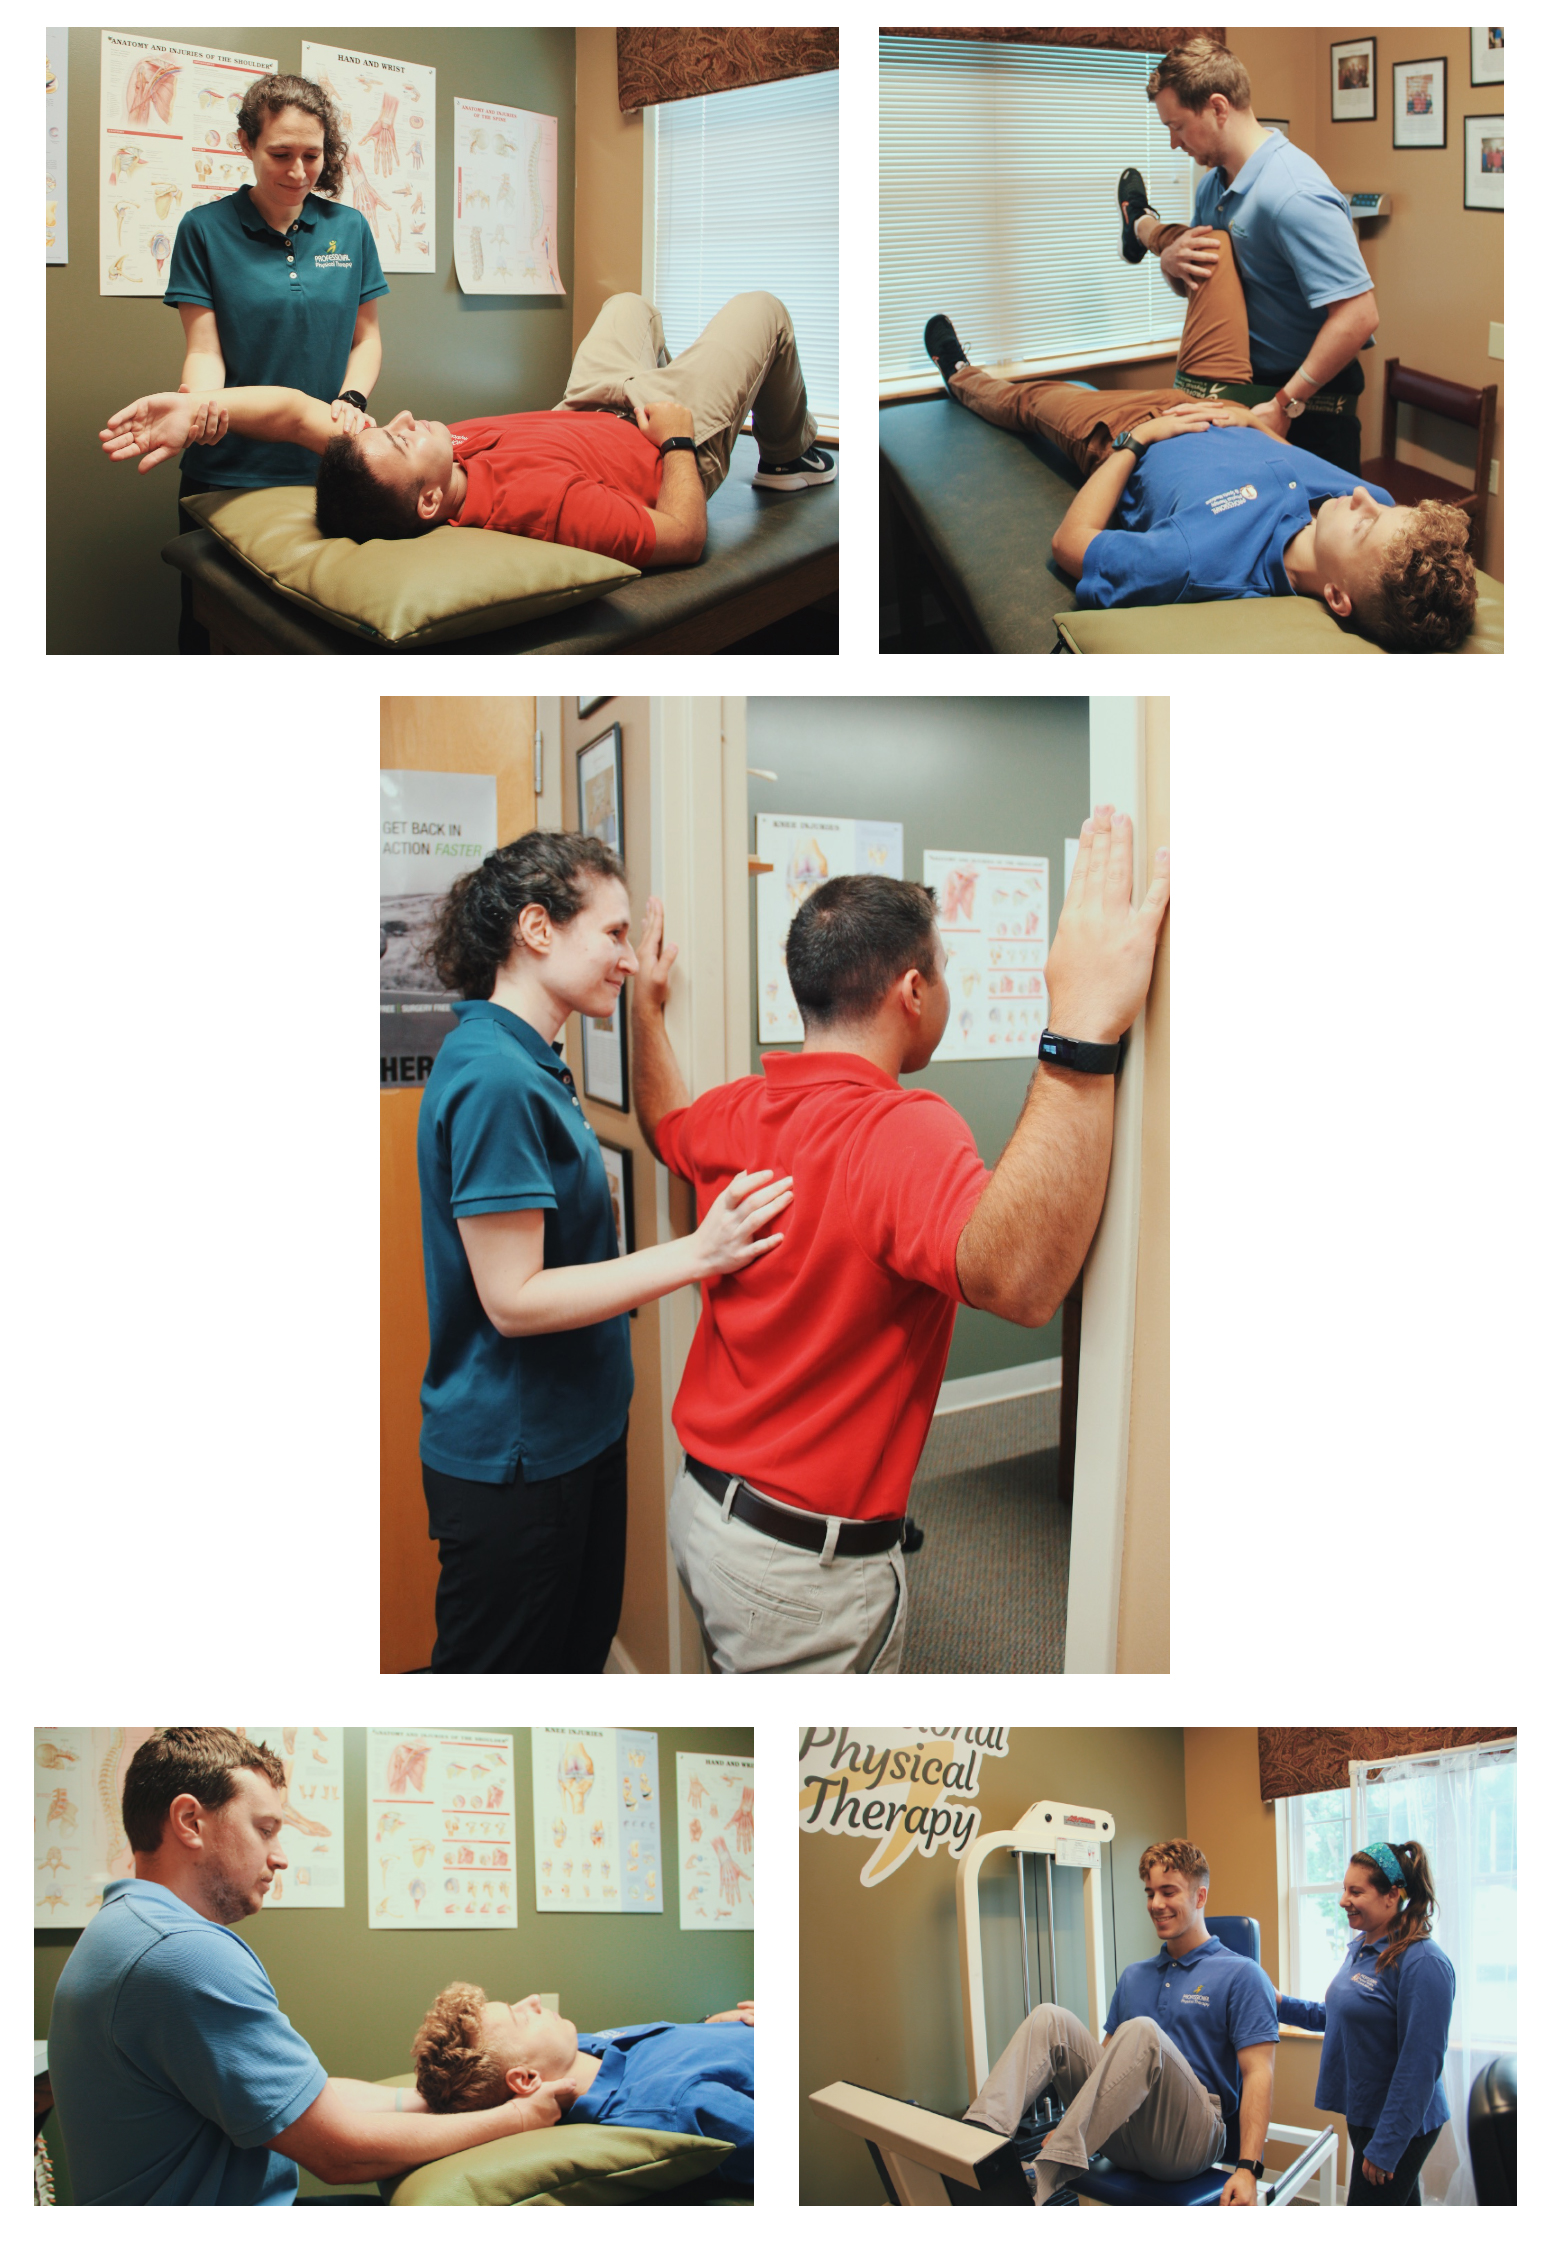
Here's what I actually do in a session. I start with passive cervical ROM assessment. If extension reproduces upper extremity paresthesia or worsens gait, I limit extension to neutral and avoid pushing into symptoms. Then we move to deep neck flexor endurance using the craniocervical flexion test at 20 to 30 mmHg. I hold there for ten seconds per rep, eight reps, three sets. Most myelopathy patients can't sustain this without sympathetic overactivation. We build up slowly. For scapular stabilization, I use prone Y raises with thumb-up positioning at thirty degrees of abduction, two sets of eight. It's low load but it matters for postural control. Patients with cervical myelopathy often compensate with upper trapezius dominance, which increases C5 through C7 facet loading and can worsen symptoms.
The Problem I Keep Running Into
There's one edge case that shows up more often than I'd expect. A patient will have mild myelopathy on MRI — say, signal change but no significant canal compromise — and normal exams initially. They come in, we start treatment, and within two to three weeks their gait becomes noticeably more spastic. The progression isn't explained by structural worsening on imaging. I've seen it happen with patients who have concurrent thoracic outlet involvement or paradoxical cord shift during neck extension. The workaround is straightforward but easy to miss. I stop cervical extension loading entirely and switch to mid-range isometric holds only. I also add a cervical collar for activities outside the clinic if gait deterioration continues. In one case, a 68-year-old male was progressing through a standard protocol when his Tinetti score dropped from 26 to 19 in ten days. We changed the approach, added a soft collar for community ambulation, and referred him for surgical evaluation. He ended up having significant canal stenosis that was underestimated on the initial MRI because he wasn't positioned in extension during imaging. This is the thing nobody emphasizes enough. Cervical myelopathy progression can be non-linear and sometimes silent on routine imaging. Standard flexion-extension X-rays won't catch dynamic cord compression. If a patient's neurological status is deteriorating despite conservative management, repeat imaging in extension or consider MRI with neuroform positioning to evaluate dynamic elements.
Get the Full Details
What Most Protocols Get Wrong
Rotational manipulation is contraindicated and still shows up in some clinic protocols. High-velocity low-amplitude thrusts at C2 through C5 carry stroke risk in patients with myelopathy because the vertebral arteries can be compromised by osteophytic changes or spondylotic deformity. This isn't theoretical. I had a referral come in from a practitioner who included cervical manipulation in a myelopathy protocol and the patient developed transient ischemic symptoms within forty-eight hours. Another common mistake is overloading the upper trapezius and levator scapulae in strengthening programs. These muscles become hypertonic in cervical myelopathy as compensatory stabilizers. Adding resistance to already overactive muscles doesn't improve function and increases segmental compression forces. The priority should always be weakening the incorrect compensations before strengthening the correct ones.
What Actually Moves the Needle
Aerobic conditioning with cervical neutral positioning improves functional outcomes more than isolated strengthening. Stationary recumbent cycling keeps the cervical spine in neutral while providing cardiovascular load. I prescribe fifteen to twenty minutes at sixty-five to seventy-five percent maximum heart rate, three times weekly. The mechanism isn't directly related to the cord compression — it's about systemic neuroplasticity and improved mitochondrial efficiency in underperforming neural tissue. Balance training on unstable surfaces needs to be progression-based. Start with eyes open on firm ground, then eyes closed on firm ground, then eyes open on foam, then eyes closed on foam. Most myelopathy patients fail at step four quickly because vestibular compensation is degraded. I track progress using the Berg Balance Scale and aim for a two-point improvement per month in the conservative management group. Hand dexterity work should include pegboard tasks, coin rotation, and button practice. These aren't filler exercises. Fine motor coordination scores correlate strongly with quality of life measures in myelopathy patients. I use the Nine-Hole Peg Test as a baseline and reassessment tool. The average improvement I see with consistent home exercise is two to four seconds per hand over eight weeks.
When Conservative Management Fails
Cervical myelopathy physical therapy has clear boundaries. If a patient shows progressive myelopathic gait, new bowel or bladder dysfunction, or rapid hand function decline over two to four weeks, conservative management isn't appropriate and surgical referral is urgent. Physical therapy can optimize function but cannot reverse significant structural cord compression. The outcome data is mixed for long-term conservative management. Studies show roughly forty percent of patients remain stable on non-operative protocols over twelve months, another thirty percent progress to surgical indication, and the remaining thirty percent decline regardless of intervention. The key predictors of progression are baseline gait impairment, presence of myeloma hand, and evidence of cord signal change on MRI. For patients who aren't surgical candidates due to comorbidities, the protocol shifts toward symptom management and fall prevention. Gait training with assistive devices, home modification assessment, and energy conservation strategies become the primary interventions. The goal changes from functional improvement to functional preservation.

Practical Notes for Clinicians
Documentation should include baseline neurological assessment with manual muscle testing at C5 through T1, sensory mapping, reflex grading, and gait analysis. Reassess every two weeks initially, then monthly once stable. Track changes in the modified Japanese Orthopaedic Association score if available — it's the most validated outcome measure for cervical myelopathy. Home exercise compliance is typically around sixty percent in this population, largely because hand clumsiness makes self-management difficult. Simplify the program to three exercises maximum and provide visual guides or video demonstrations. Patients who can perform their home program correctly have significantly better outcomes than those who attempt complex routines incorrectly. Coordinate with neurology and neurosurgery early. If a patient is being evaluated for surgery, physical therapy should support prehabilitation — improving cardiovascular baseline and strengthening non-affected muscle groups to reduce postoperative complications. Prehabilitation typically lasts two to four weeks before surgical intervention.