Getting Through Chapter 13 of Anatomy and Physiology
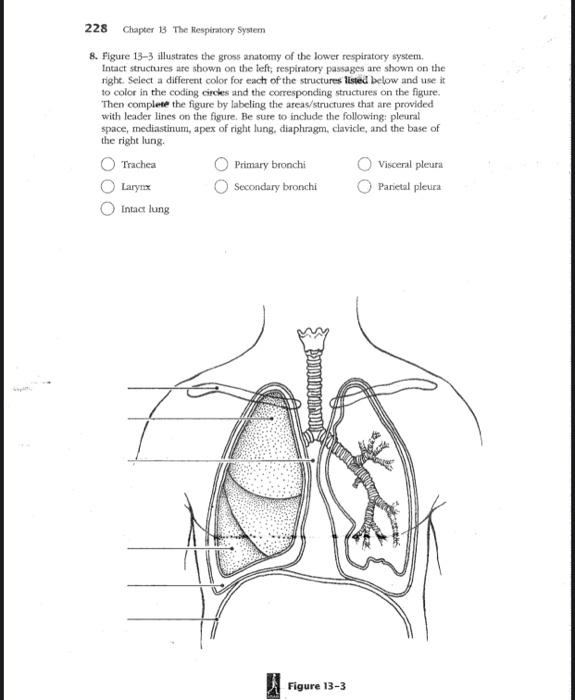
Chapter 13 covers the respiratory system, and most students hit a wall around the gas exchange section. I've been grading these for years and the answer key is usually where people end up when they've already spent four hours staring at a diagram of alveoli trying to remember which partial pressure goes where. The standard answer key for Chapter 13 Respiratory System typically follows the textbook structure: anatomy of the upper and lower respiratory tract, the mechanics of ventilation, gas exchange at the alveolar-capillary membrane, transport of oxygen and carbon dioxide, and regulation of breathing. The problems students actually struggle with aren't the identification questions—they're the ones asking you to walk through the pressure changes during a full respiratory cycle or calculate alveolar ventilation rates.
Where the Chapter 13 The Respiratory System Answer Key Actually Helps
I keep a copy of the answer key open while I work through practice problems, not to check my final answer but to trace my steps mid-problem. When I'm stuck on a ventilation calculation, I look at how the key sets up the equation, not just what it says the answer is. That distinction matters because most keys show the work in a condensed format that skips the intermediate algebra unless you know what line you're looking for. Here's a specific edge case that always catches people off guard. The key sometimes lists pulmonary ventilation rate and alveolar ventilation rate as interchangeable in simplified problem sets, but they are not the same thing. Pulmonary ventilation is the total volume of air moved in and out per minute, while alveolar ventilation subtracts the anatomical dead space. I once spent twenty minutes confused on a homework question because the answer key used the wrong term in the setup. The workaround was checking whether the problem included a dead space value—if it did, the key was using alveolar ventilation, and I needed to adjust my answer accordingly. Just multiply the anatomical dead space (usually 150 mL) by the respiratory rate and subtract that from the total minute ventilation. That gives you the real alveolar ventilation number the question is after. The harder part of this chapter isn't memorizing terms. It's understanding how the partial pressures of oxygen and carbon dioxide drive diffusion across the respiratory membrane. The answer key will give you numbers like 104 mmHg for alveolar oxygen and 40 mmHg for venous blood oxygen, but it rarely explains why those numbers exist or what happens when they shift. That's where the actual learning happens.
Common mistakes I see in student work center on the Bohr and Haldane effects. Students treat oxygen binding and carbon dioxide transport as separate processes when they're linked. The answer key typically handles this by separating the questions into discrete sections, but the underlying physiology doesn't work that way. Hemoglobin's affinity for oxygen drops when carbon dioxide and hydrogen ion concentrations rise, which is exactly what happens in metabolically active tissue. If you can only explain one without the other, you're not really answering the question. Another counter-intuitive point that textbooks don't stress enough: the majority of carbon dioxide in the blood is transported as bicarbonate ions, not bound to hemoglobin or dissolved in plasma. About 70 percent becomes bicarbonate, roughly 23 percent binds to hemoglobin as carbaminohemoglobin, and only about 7 percent stays dissolved. The answer key questions on CO2 transport often trip students up because they expect the hemoglobin-bound fraction to be larger. It's not. The bicarbonate conversion happens inside red blood cells via carbonic anhydrase, and the chloride shift that follows is what maintains electrochemical balance. If a question asks about the chloride shift and you haven't reviewed it alongside CO2 transport, you'll miss the point entirely. The regulation of breathing section is where the answer key tends to be most sparse. Central chemoreceptors in the medulla respond primarily to changes in cerebrospinal fluid pH, which reflects arterial PCO2 levels. Peripheral chemoreceptors in the carotid and aortic bodies respond to changes in PO2, PCO2, and pH, but they're mainly sensitive to drops in oxygen when levels fall below 60 mmHg. That threshold matters because it means mild hypoxemia doesn't trigger the chemoreflex—you have to be significantly low before breathing rate increases based on oxygen alone. Most students gloss over this detail and lose points on exam questions that hinge on it.
Get the Full Details

If you're using the Chapter 13 The Respiratory System Answer Key to study, work through the problems in order and cover the answers until you've attempted each one. The key is useful for confirming your setup, not for filling in gaps in your understanding. When your answer matches the key but your reasoning was different, that's usually a sign you got lucky, not that you know the material. Pay attention to those mismatches more than the ones that line up. The chapter also includes questions on respiratory volumes and capacities—tidal volume, inspiratory reserve volume, expiratory reserve volume, and residual volume. The spirometry diagrams in the key can be misleading if you don't realize that residual volume cannot be measured directly by spirometry. You need body plethysmography or gas dilution techniques for that. Any question asking you to calculate vital capacity from total lung capacity should account for residual volume, and if the key skips that step, double-check your own work. One more practical note: the answer key for this chapter often groups questions by section but doesn't always match the numbering in your specific textbook edition. Pearson, McGraw-Hill, and Cengage all use slightly different chapter structures. Make sure you're cross-referencing question numbers against your actual assignment sheet rather than assuming the key aligns perfectly. I've had students waste time looking for a question that didn't exist in their version because they were using a slightly different edition of the key.
If you need the actual document, it's usually available through your course portal or the publisher's companion website. Look for the instructor resources section if the student version doesn't include the detailed explanations. The student keys tend to be lighter on reasoning, which is fine for quick checks but less useful for actual studying. The instructor version walks through the physiology more thoroughly and tends to catch the edge cases I mentioned above.