What Actually Matters in This Chapter
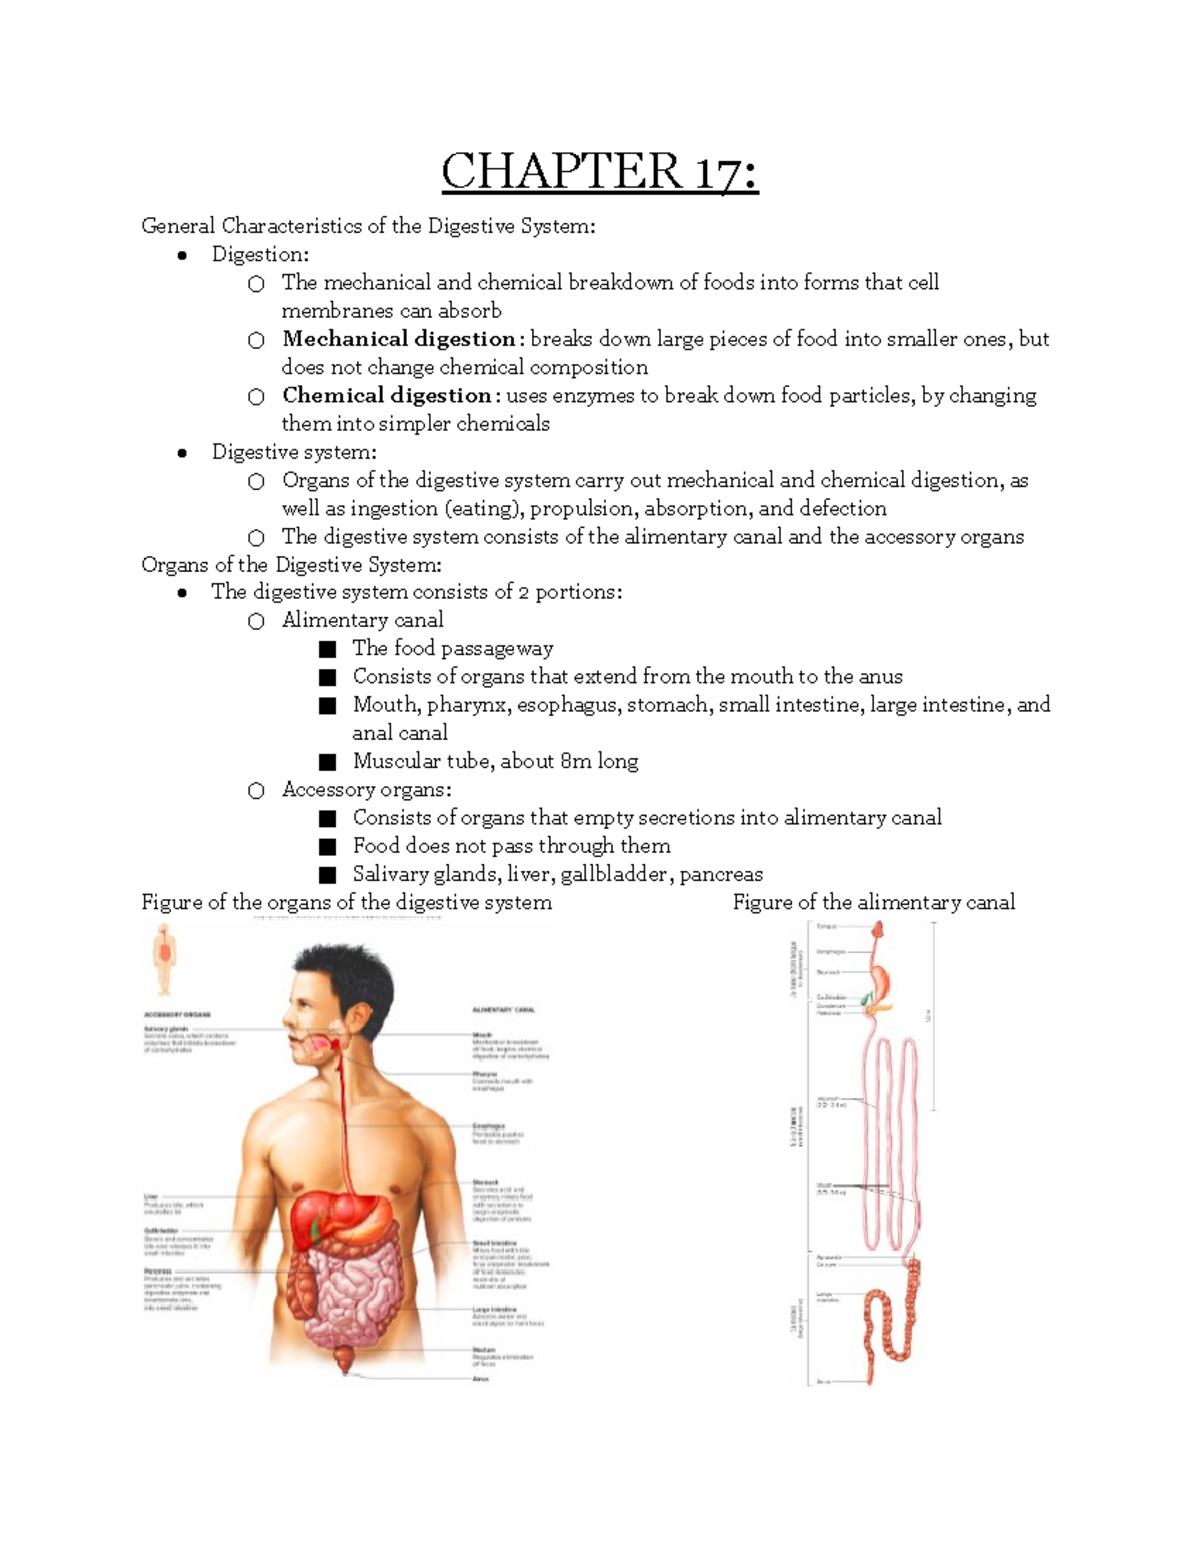
Most students breeze through the first half of the digestive system chapter because it's descriptive. Ingest, chew, swallow, move along. The real trouble starts when you try to tie the endocrine pieces, the neural controls, and the enzymatic pathways together. That's where the exam questions live.The digestive system isn't just a tube with glands. It's a tightly regulated network where hormonal signals, autonomic input, and local reflexes constantly negotiate with each other. If you memorize the list of organs without understanding the cross-talk, you'll hit a wall pretty quickly. Here's what I did wrong the first time I covered this material. I treated the phases of gastric secretion as separate topics. Cephalic phase, gastric phase, intestinal phase — I flash-carded them individually and moved on. Then the test asked me to describe what happens when chyme enters the duodenum and how that feedback loop actually slows gastric emptying. I blanked. I hadn't connected the dots between the phases. The workaround was drawing the entire GI tract on a large piece of paper and using different colored pens for neural pathways, hormones, and enzymatic actions. You force yourself to see the connections when you're trying to draw a single coherent diagram. Takes about 45 minutes the first time. After that, the system just clicks into place.
The Layers You Actually Need to Know Cold
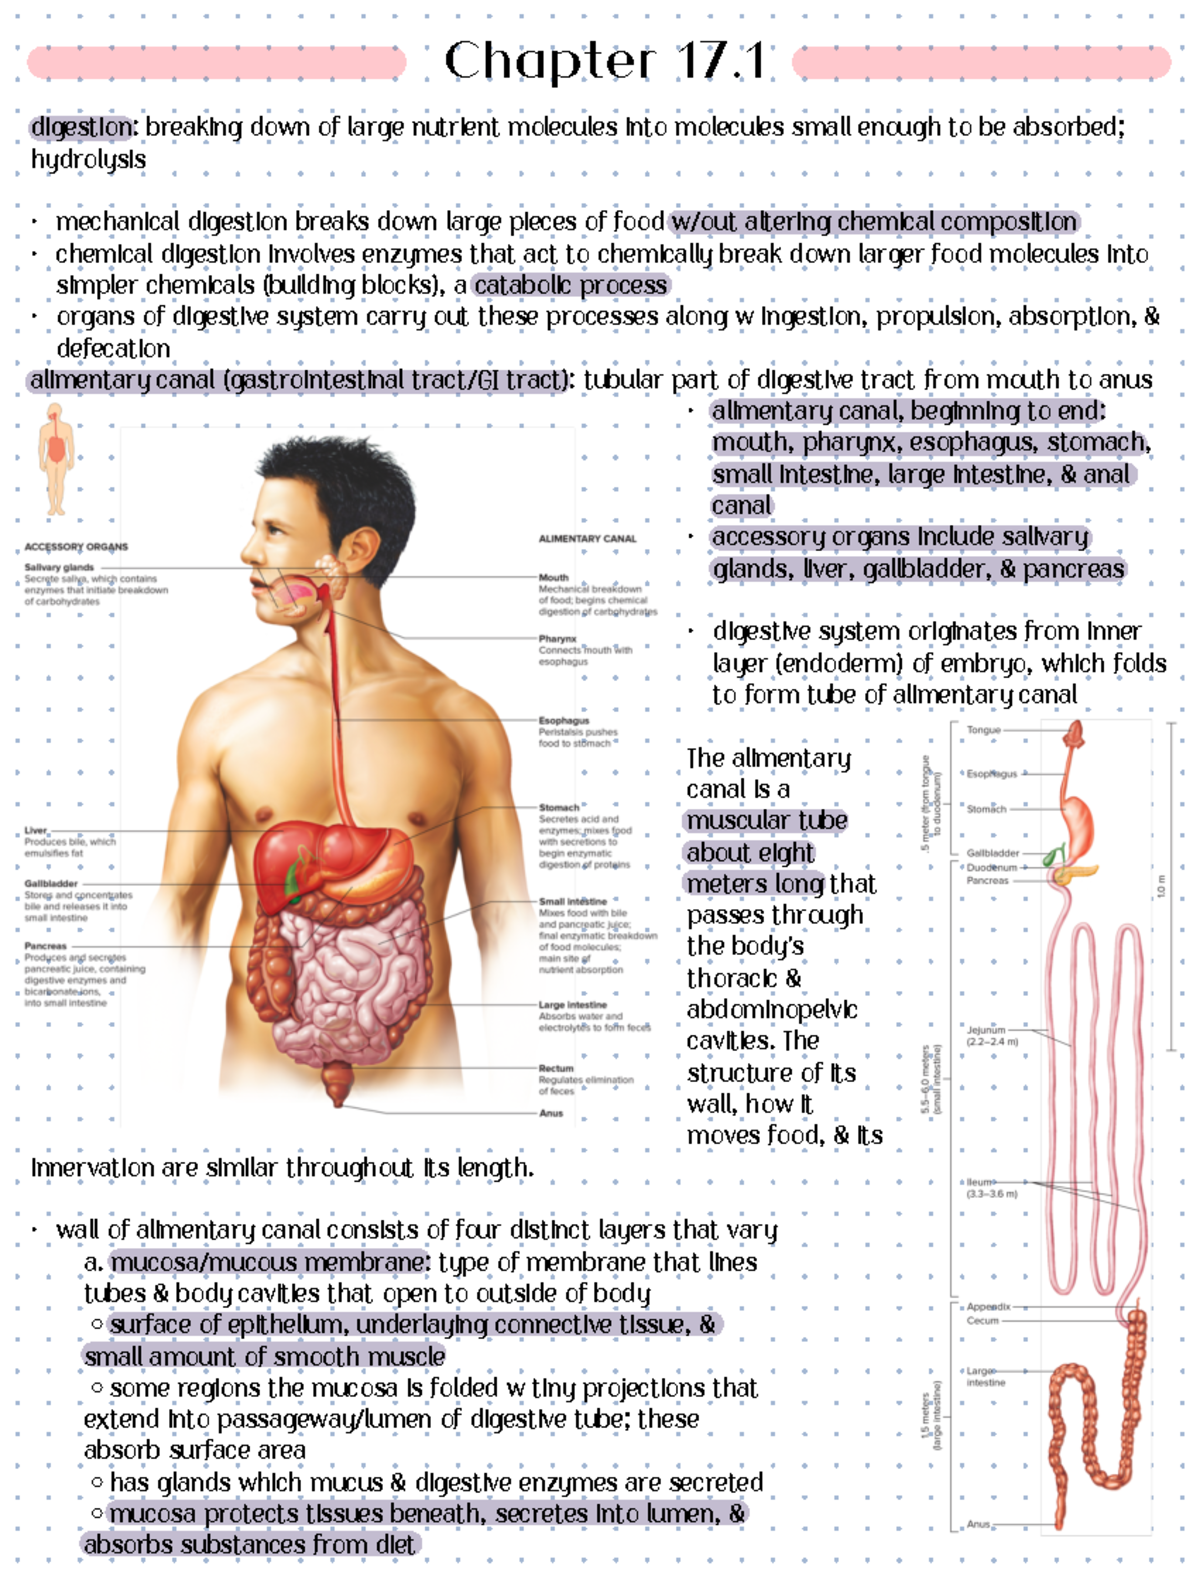
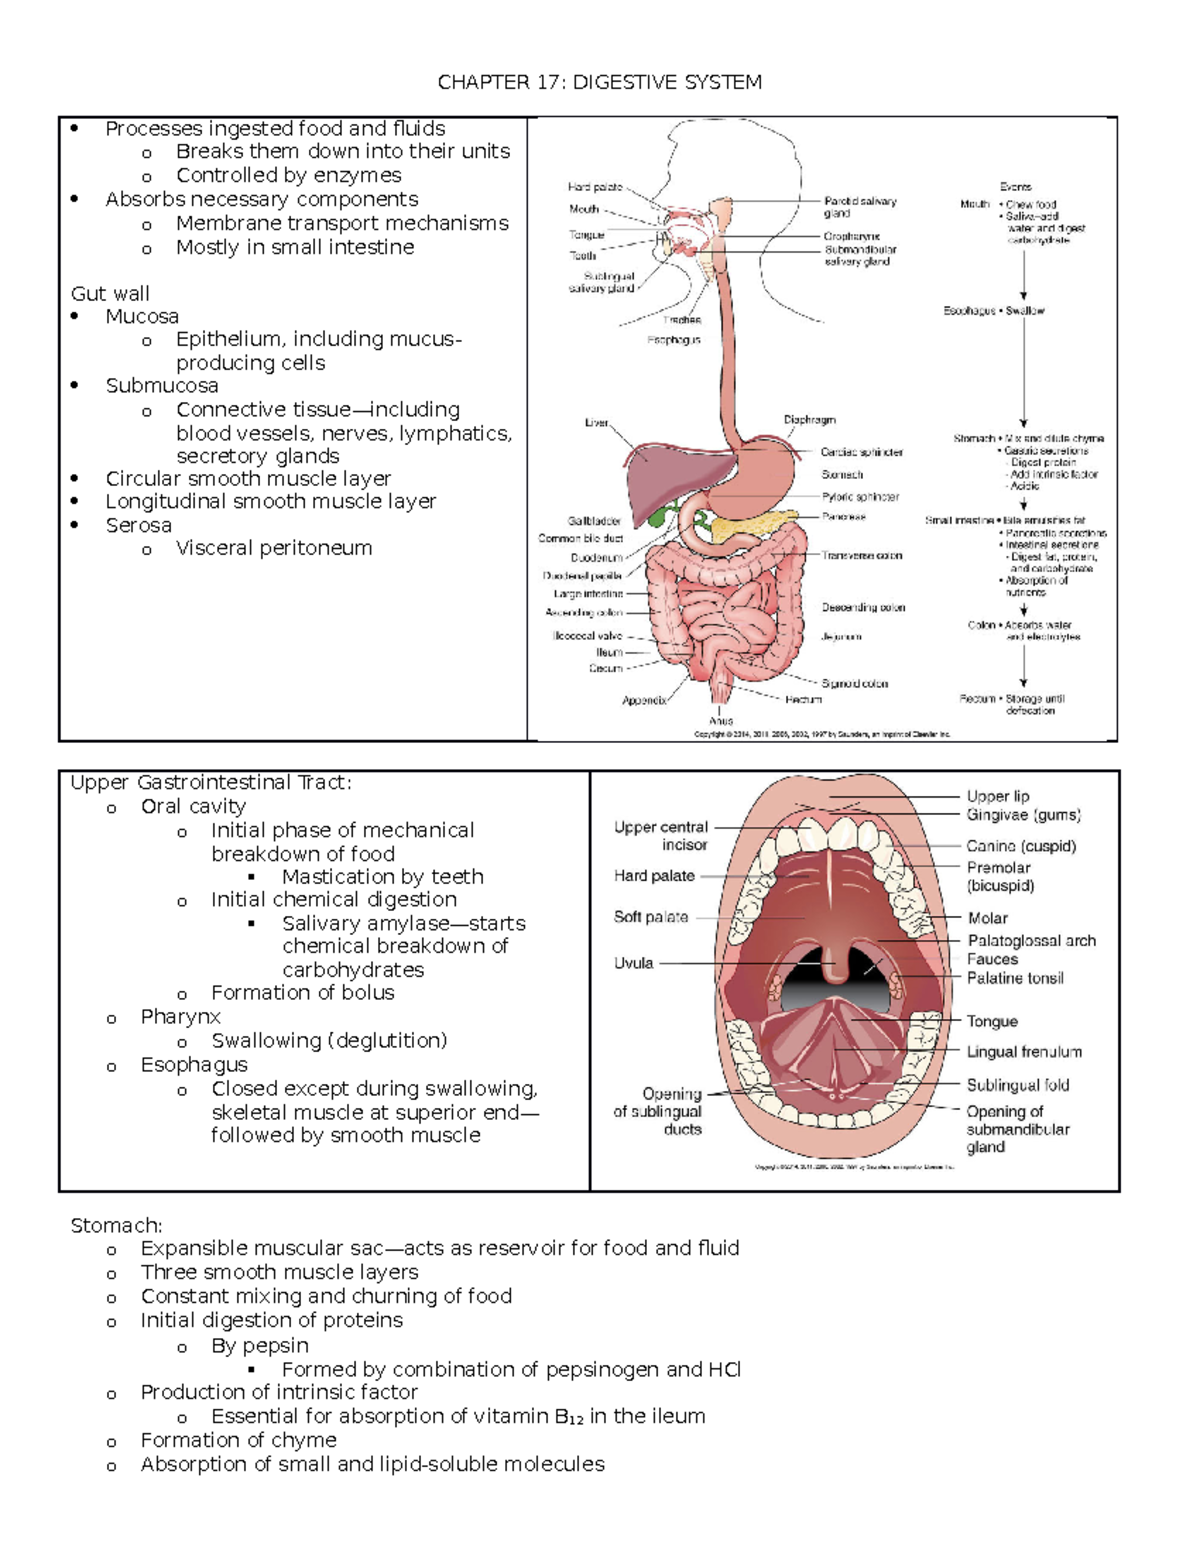
Mucosa, submucosa, muscularis externa, serosa. That's the basic wall structure and it repeats from esophagus to anus with modifications. Don't just memorize the names. Know what each layer contributes functionally. The mucosa handles secretion and absorption. The submucosa has the submucosal (Meissner's) plexus and blood supply. The muscularis externa has the myenteric (Auerbach's) plexus between the circular and longitudinal muscle layers. The serosa is the outer covering. A detail most people skip: the muscularis mucosae. It's a thin layer of smooth muscle within the mucosa itself that creates local folding and increases surface area for absorption. It's easy to forget because it's small, but it shows up in histology questions more often than you'd expect.
Hormonal Control Is Where Students Lose Points
Gastrin, secretin, cholecystokinin, gastric inhibitory peptide, motilin — that's the core cast. You need to know which cell type secretes each one, where it acts, and what it does. But the deeper understanding comes from knowing the feedback logic. Secretin gets released when acidic chyme hits the duodenum. It tells the pancreas to dump bicarbonate. It also tells the stomach to slow down. CCK gets released when fats and proteins hit the duodenum. It tells the gallbladder to contract and the pancreas to release digestive enzymes. It also slows gastric emptying. Both of these hormones are essentially doing the same job from different angles: protect the small intestine from being overwhelmed. The counter-intuitive part most textbooks don't emphasize enough: the enterogastric reflex. This is the neural component that works alongside the hormonal one. When the duodenum senses distension or acidity, vagal and enteric reflexes send signals back to the stomach to reduce motility and secretion. It's not just hormones doing the work. The nervous system is right there participating. I've seen students answer questions correctly by naming the hormones but missing the reflex arc entirely. That's a half-answer.
Get the Full Details
Enzymes and Where They Come From
Salivary amylase starts carbohydrate digestion in the mouth. It keeps working in the stomach until the acid denatures it. Pancreatic amylase finishes the job in the small intestine. That's two waves of the same enzyme class, and the transition point matters for understanding why you need pancreatic output to be adequate. Proteases are trickier because of the zymogen issue. Pepsinogen becomes pepsin in acidic conditions. Trypsinogen becomes trypsin in the duodenum via enterokinase. Then trypsin activates the rest of the pancreatic proteases. This cascade is one of those topics that feels like trivia until you understand what happens clinically. If trypsinogen gets activated too early — inside the pancreas instead of the intestine — you get autodigestion. That's acute pancreatitis. The mechanism explains the pathology directly. Lipase is another one people undersell. Pancreatic lipase does the heavy lifting on fat digestion, but it needs bile salts for emulsification to work efficiently. Without bile, lipase can still act on large fat globules at a much slower rate. The surface area argument is the key insight here.
The Enteric Nervous System Is Not a Nice-to-Know
You need to understand that the gut has its own nervous system capable of operating independently of the brain and spinal cord. The myenteric plexus controls motility. The submucosal plexus controls secretion and blood flow. Together they're called the enteric nervous system, sometimes referred to as the "second brain" in pop science, but that nickname is useless to you on an exam. What matters is that the ENS can coordinate peristalsis, segmentation, and reflex responses without any input from the CNS. The vagus nerve and sympathetic chains modulate it, but they don't initiate the basic rhythmic activity. That comes from interstitial cells of Cajal acting as pacemakers. Knowing that detail separates students who understand the system from students who memorized a diagram.
Absorption Realities That Textbooks Gloss Over
Most nutrients cross the intestinal epithelium into capillaries that drain into the hepatic portal vein. That's standard. But fat absorption is different. Chylomicrons enter the lacteals — the lymphatic capillaries in the villi — and eventually reach the bloodstream through the thoracic duct. This bypasses the liver initially. It's a critical distinction because it explains why certain lipid-soluble substances and drugs have different pharmacokinetics compared to water-soluble ones. Vitamin B12 absorption requires intrinsic factor from gastric parietal cells. Without intrinsic factor, you can eat all the B12 you want and you still won't absorb it. This is pernicious anemia. The connection between the stomach and the small intestine's absorptive capacity is one of those integrated concepts that appears in case-study questions.

Common Pitfalls on Exams
One mistake I see constantly: confusing the functions of the large intestine versus the small intestine. The small intestine is where the vast majority of nutrient absorption happens. The large intestine absorbs water, electrolytes, and some vitamin K produced by bacteria. It does not absorb significant nutrients. If a question describes massive nutrient absorption, the answer is small intestine, period. Another one: assuming the stomach's main job is chemical digestion. Mechanically, it churns and mixes. Chemically, it starts protein breakdown with pepsin. But its role in controlled delivery of chyme to the duodenum is just as important. Gastric emptying rate is a regulated process, not a passive one. The bile question trips people up too. The liver produces bile. The gallbladder stores and concentrates it. The cystic duct connects the gallbladder to the common bile duct. The sphincter of Oddi controls entry into the duodenum. Trace the anatomical path and the functional sequence together and you won't mix them up under pressure.
How to Study This Chapter Efficiently
Don't read it passively. Close the book and redraw the GI tract from memory, labeling every structure, every plexus, every hormone, every enzyme. Then open the book and fill in what you missed in a different color. The gap-filling is where actual learning happens. This process takes roughly 90 minutes for a first pass but will save you hours during review sessions later. Prioritize the regulatory mechanisms over the descriptive anatomy. The organ locations and basic histology are straightforward. The control systems — neural, hormonal, paracrine — are where the difficulty lives and where the grading emphasis usually sits. Spend roughly 60 percent of your study time on regulation and 40 percent on structure and function. Teach it to someone else or explain it out loud to an empty room. If you can't articulate why secretin slows gastric emptying without looking at your notes, you don't understand it yet. That self-test is brutally honest and usually reveals exactly where your gaps are before you sit down for the actual exam.