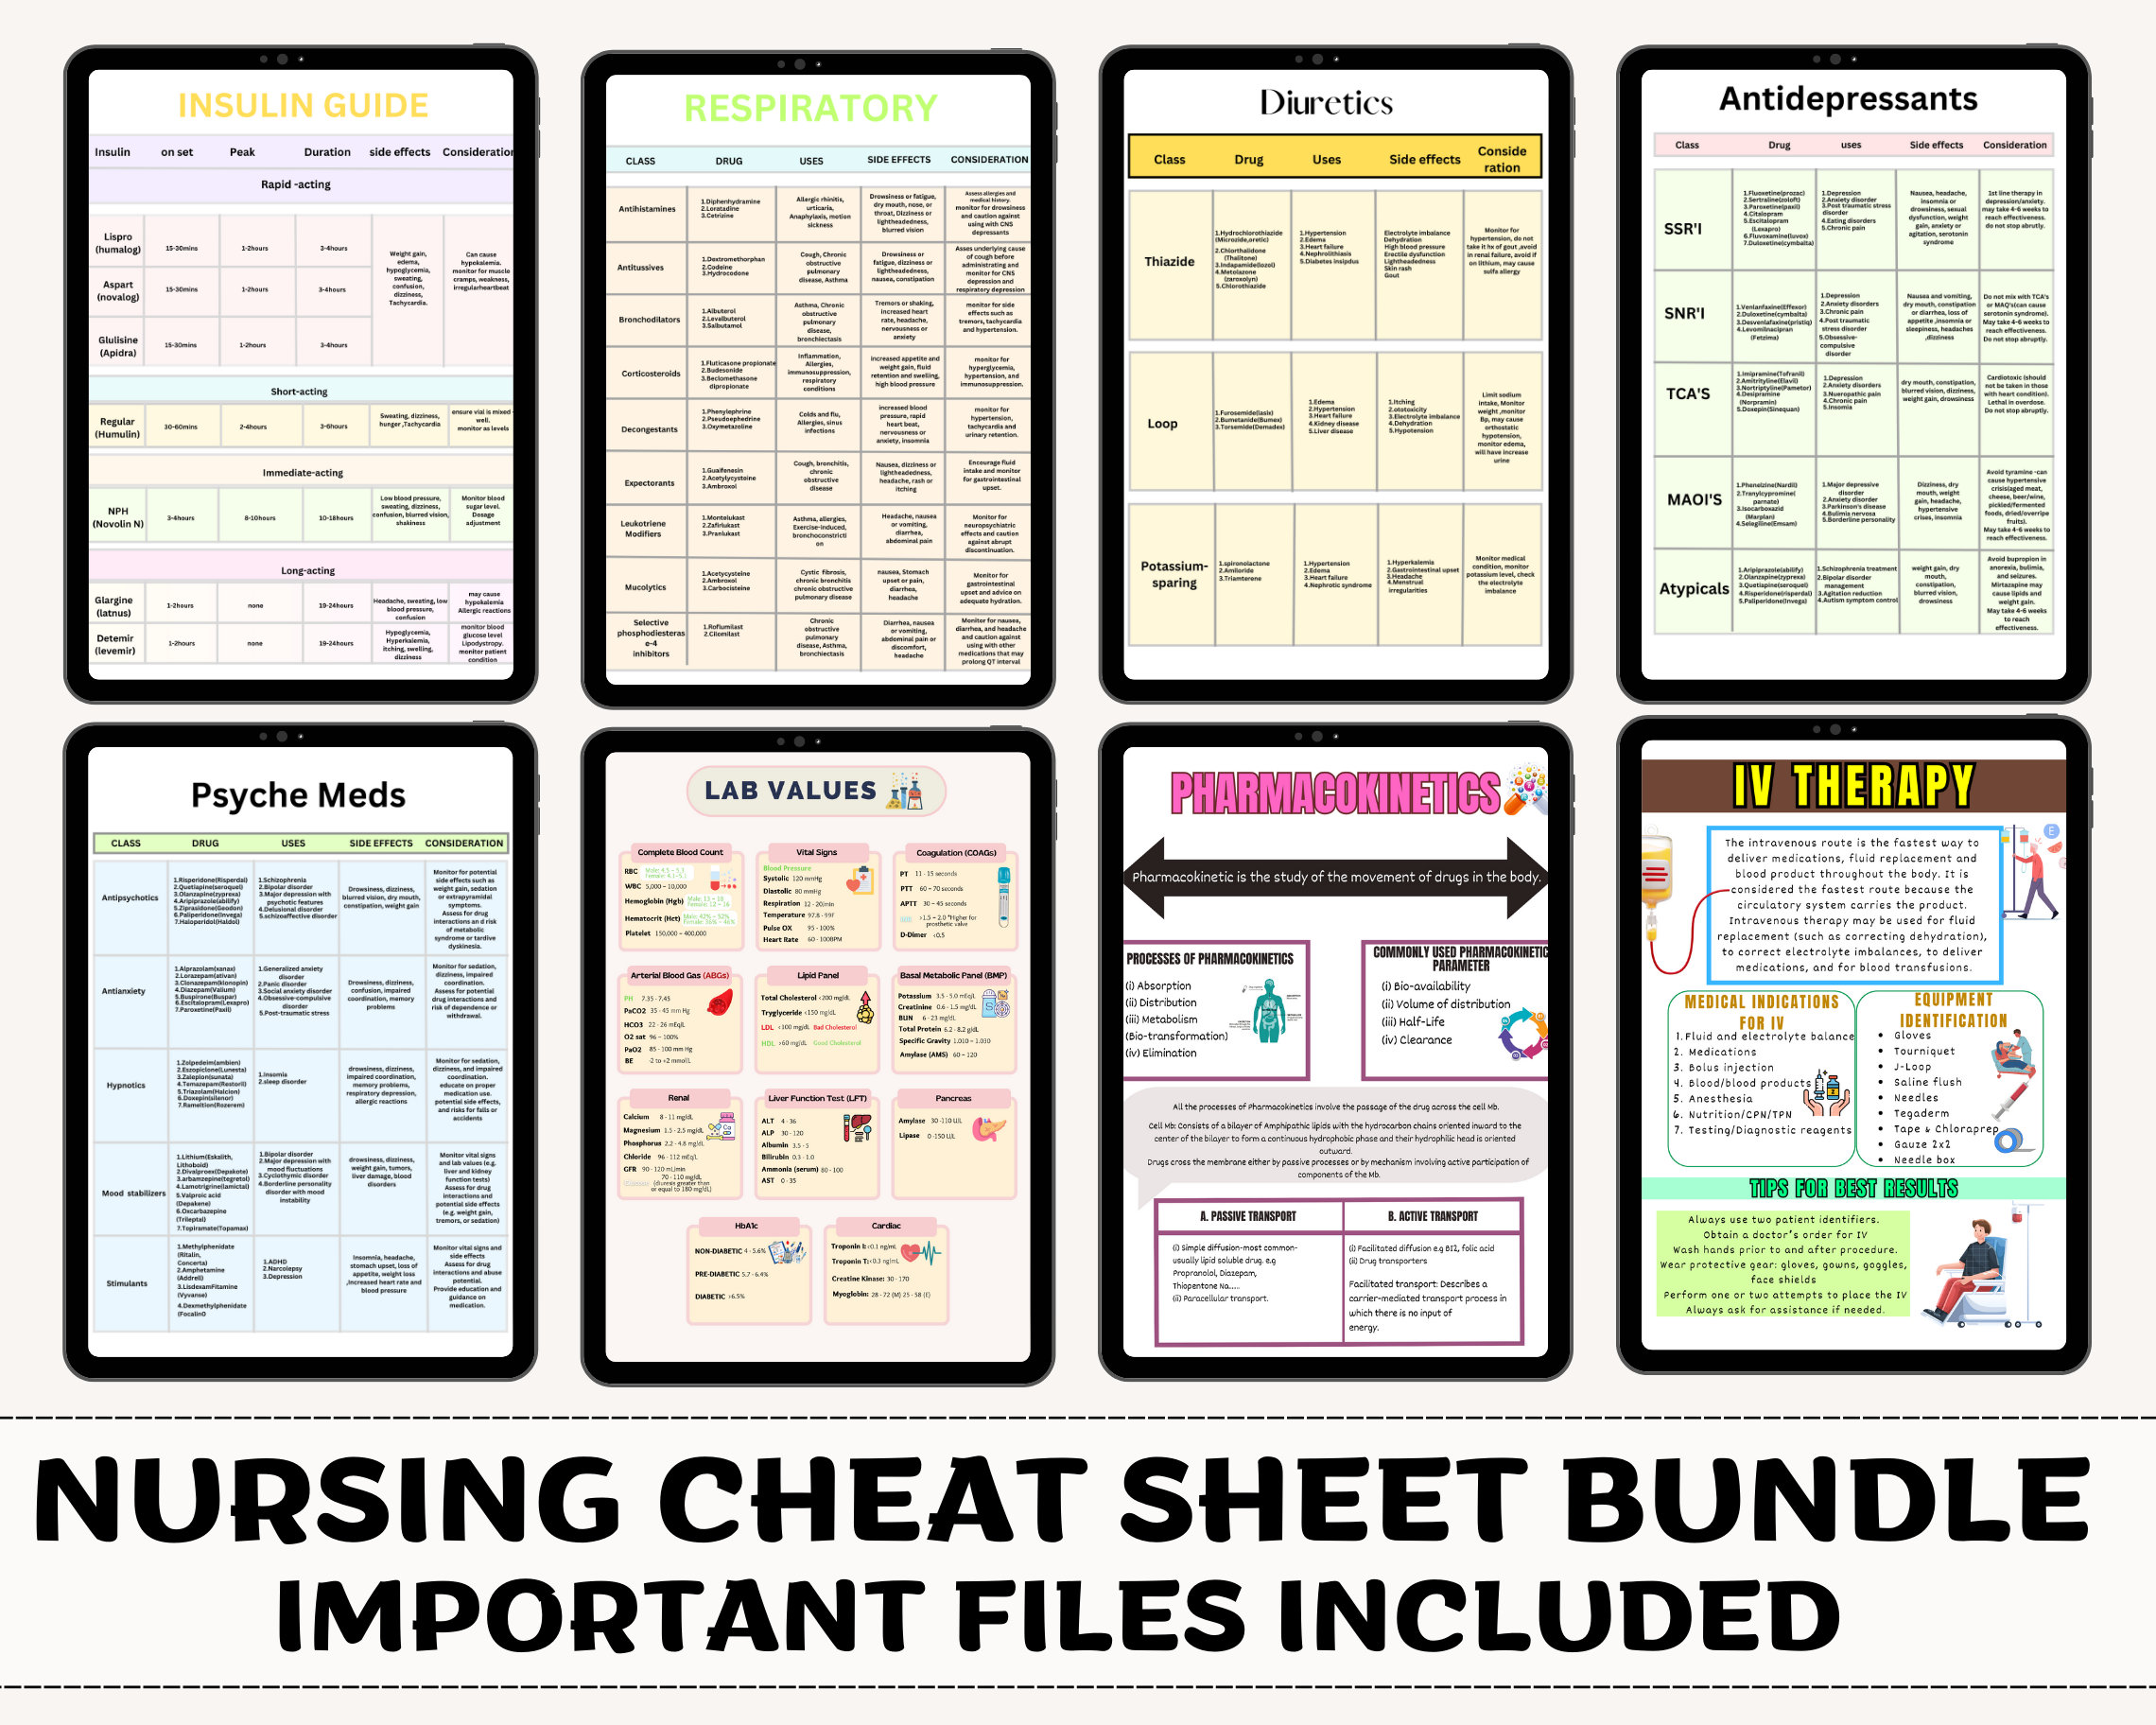
What actually makes a nursing cheat sheet useful versus just another piece of clutter
A nursing cheat sheet is a condensed reference tool that compresses critical dosing calculations, conversion factors, drug ratios, and quick-decision algorithms onto a single page or a small set of pages. I have spent years watching nurses either carry laminated sheets around their necks like a badge or forget they even exist until a code blue hits. The difference between those two outcomes usually comes down to whether the sheet was designed for actual rapid lookup under stress, or whether it was made by someone who had never had to turn pages with sweaty gloves on. The first thing you need to understand is that most people build these things wrong. They put too much information on one page, use font sizes smaller than 8 point, and organize content alphabetically instead of by clinical urgency. Here is the basic structure I have been using since 2008, and the reason it works for my team. Page one: IV and dose calculations. This should contain the formula for flow rate, mg/kg dosing, concentration conversions, and the standard drip factor reference. Everything else gets pushed to page two. When someone needs to run a dopamine drip at 5 mcg/kg/min on a 90kg male patient and their brain is already working through the hemodynamics, they should not have to flip a page to find the multiplication factor.
I ran into a specific problem last year that completely changed how I design these sheets. A resident on my floor was administering a heparin bolus and misread the unit conversion between IU and mg on our printed chart. He caught it before delivery, but it took us twenty minutes to trace exactly where the error crept in. The issue was that the sheet listed the conversion factor at the bottom in gray text, near the footers, buried under three other reference tables. After that incident, I moved all unit conversion factors to the top margin in bold. You should do the same. This single change reduces calculation errors significantly because the most error-prone step becomes the first thing a reader sees. Page two: Drug reference tables. List the most commonly used medications by class, not alphabetically. Include route, onset, peak, and duration columns. Keep it to maybe fifteen to twenty drugs per class, prioritizing what your unit actually uses. If your ICU rarely sees vancomycin, do not waste space on it. If your med-surg floor goes through Lasix like water, put it front and center. One thing most people miss here: include the narrow therapeutic index drugs in a separate highlighted box. Lithium, phenytoin, digoxin, warfarin. These are the drugs where a rounding error can land a patient in the ICU. I put mine in a red-bordered box at the top right of page two. It is not fancy. It works.
Page three: Lab value quick references. Normal ranges for electrolytes, renal function markers, coagulation panels, and arterial blood gas values. Keep this section in a table format with two columns: parameter and normal range. Add a third column for critical values. Some people ask why you need critical values on a cheat sheet. The answer is simple. When a nurse picks up a phone at 3 AM to call a doctor about a potassium of 6.8, she needs to know immediately that this is critical without cross-referencing three different textbooks. Critical value thresholds are universal enough that they belong on the sheet.
Get the Full Details

Why most cheat sheets fail under real conditions
There are structural problems that make many published nursing cheat sheets nearly useless in practice. I want to address the ones I see most often, because recognizing them will save you time you cannot afford to waste. First, the font size issue. Many commercial and free downloadable sheets use 9-point font as standard. On a gurney at midnight, with fluorescent lighting and tired eyes, 9-point is essentially illegible for most people. I always print my sheets at 11-point minimum. This forces you to be more selective about what goes on the page, which is actually a good thing. Less is more here. Second, there is the over-reliance on memorization rather than calculation. A good cheat sheet shows the method, not just the answer. When I print a drug calculation formula, I include the full equation with placeholders so the user can see the structure. Just writing "dose equals weight times concentration" is not helpful. Writing "D = W × C ÷ T" with a worked example below it tells the nurse exactly what to do when the numbers change.
Third, and this is something I have seen cause real harm, is the failure to account for route differences. A dose of acetaminophen IV is not the same as oral. A dose of morphine subcutaneous is different from epidural. I have seen nurses look up a drug on a sheet and assume the numbers apply across routes. This is dangerous. Every drug entry on your sheet should specify the route. If a drug has multiple routes, list them separately. Another limitation that most cheat sheets ignore completely: they do not account for insurance or formulary restrictions. A drug might be on your reference sheet, but if your hospital does not stock it, that information is worthless. I add a small notation column next to each drug entry indicating whether it is formulary on our floor. It took me two months to fill this in properly after comparing the sheet against our pharmacy formulary. But once done, it prevents a specific type of error where a nurse prepares a medication that then has to be returned because it was not ordered or not available. There is also the problem of outdated reference ranges. Normal lab values shift over time as laboratories update their methodologies. I review my cheat sheet every six months against our lab's current reference ranges. Some of the values on my original sheet were off by several standard deviations. A sodium range that says 135 to 148 is no longer correct in our lab; it is now 136 to 145. These changes matter when you are interpreting results at midnight.
Cheat Sheet For Nursing Top 10: Core Content Priority Order
If you are building one from scratch and you only have space for ten items, here is the order I use based on frequency of use and risk of error. This is not theoretical. This comes from tracking which sections my team actually references during a shift. One is IV flow rate calculation. Two is weight-based dosing. Three is concentration-to-dose conversion. Four is common drug drip calculations. Five is electrolyte replacement dosing. Six is pediatric dose adjustment. Seven is renal dosing adjustments. Eight is ABG interpretation. Nine is vital sign thresholds for notification. Ten is emergency drug dosing like epinephrine and atropine. The ordering matters because five through ten get less attention but carry higher risk when wrong. Renal dosing adjustments alone are responsible for more adverse drug events than any other calculation category on the sheet. Put them on the page. Do not skip them because they seem complicated.

I keep my current version laminated and carry it in my left pocket at all times during my shift. I replace it every six months. I have learned from experience that the versions I made five years ago have errors that accumulated over time without me noticing. The only way to catch them is to rebuild from scratch annually and compare the new version against current guidelines. It takes about forty-five minutes of focused work. Worth it. When you download or build your own version, test it under conditions that resemble actual use. Set a timer for two minutes, write out a heparin drip calculation from scratch, and see how long it takes you to find each number on the sheet. If it takes longer than ninety seconds for any single lookup, the layout needs to change. The best sheets I have seen allow any single lookup in under thirty seconds. That is the standard to aim for.