Pharmacology Checklists Are Barely Useful Unless You Use Them Right
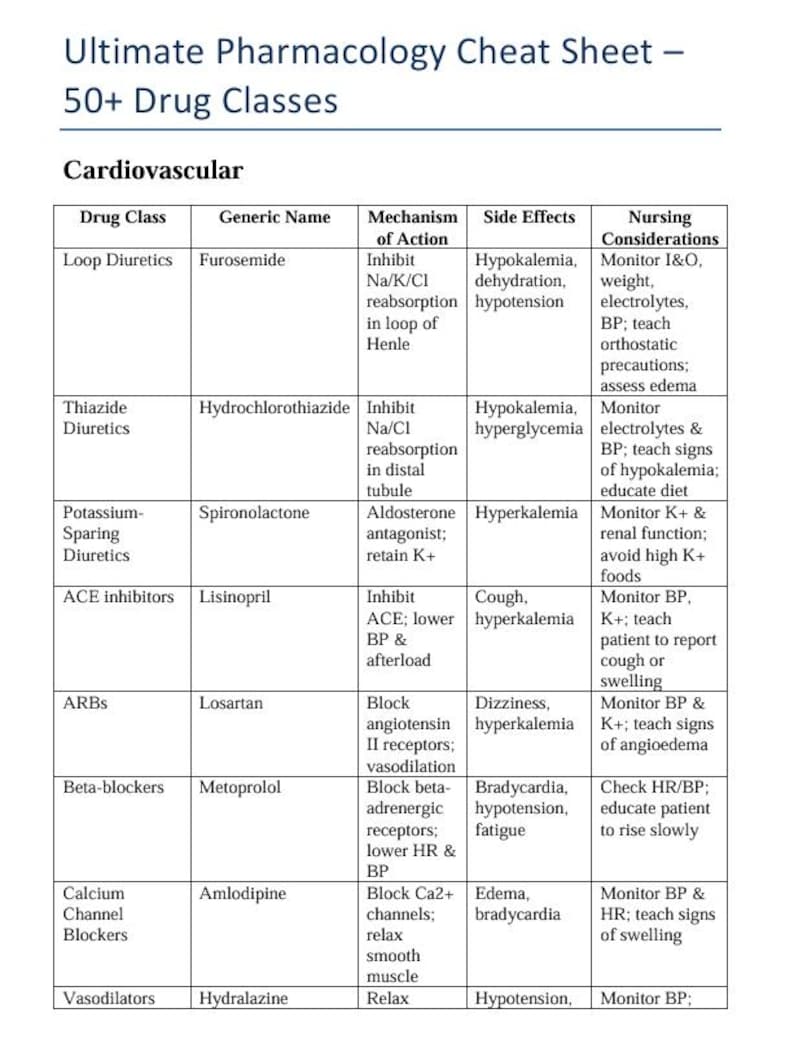
I spent three years building out a pharmacology study system that actually survives clinical rotations, and the core of it is what I call the Checklist For Pharmacology Ultimate. It isn't a branded product from some edtech company. It's a structured list I put together myself after watching too many students fail because they studied drugs in isolation instead of in categories with clear distinguishing features. The checklist covers drug classes, mechanisms of action, adverse effects, contraindications, and key clinical pearls. The format is deliberately sparse. Each entry gets one line for mechanism, one line for major side effects, and one line for the thing you absolutely cannot forget about that drug class. That's it. Anything more and students just skip ahead to the next one anyway.
How to actually use the Checklist For Pharmacology Ultimate
Download a blank version or grab an existing template, then go through each drug class you need to know and fill in the three lines yourself. The act of filling it in is where the memory happens. Copying someone else's completed version rarely works because you aren't forced to retrieve the information. Active recall matters more than passive reading. I've seen students swear they "knew" a drug class until the exam question asked for something specific like CYP450 interactions or pregnancy category, and they froze because they never actually pulled the fact out of their head during study. Here is the practical workflow I recommend: start with the drug class headers in the order your curriculum uses, fill in mechanisms first across all classes before moving to side effects. Do not jump around. Pattern recognition works best when you see similarities side by side. Beta blockers versus calcium channel blockers become almost obvious when their adverse effect profiles sit next to each other in a table rather than scattered across three different chapters. I once had a student who completed her checklist for ace inhibitors and wrote "cough" under side effects but missed that the cough was specifically a bradykinin-mediated dry cough. The question on the exam distinguished between ACE inhibitor cough and other causes of chronic cough, and she lost points because she hadn't thought through the mechanism behind the side effect. After that, every entry on the checklist includes the mechanism even for adverse effects. It adds maybe twenty minutes per class but it prevents exactly that kind of mistake.
What most checklists get wrong about pharmacology
Most students treat pharmacology like a memorization task. It is not. Pharmacology is applied physiology with a drug label slapped on top. If you understand the underlying physiology, the drug mechanisms stick naturally and you spend far less time cramming. The checklist should reflect that. Each entry needs a short physiology anchor, not just drug facts. For example, studying digoxin without reviewing the sodium-potassium ATPase pump and how cardiac glycosides affect intracellular calcium is pointless. The drug will feel arbitrary. Once you understand the physiology, digoxin becomes predictable: more intracellular calcium means stronger contraction, which explains both the therapeutic effect and the toxicity pattern. Nausea, vomiting, and yellow vision are not random side effects. They are signs of toxicity at the cellular level. Another common mistake is including too many drugs per class. A checklist for antihypertensives should not list every ACE inhibitor ever made. It should list the prototype, note the class exceptions, and move on. Ramipril and lisinopril and enalapril share the same core profile. You do not need separate entries for each one. Focus on differences that matter clinically. Fenoldopam versus labetalol in hypertensive emergencies is the kind of distinction that actually shows up on boards and in practice.
Get the Full Details

Specific edge cases the checklist must cover
Therapeutic indexes are one area students consistently mishandle. A narrow therapeutic index drug like warfarin or lithium requires monitoring and dose adjustments that most checklists completely skip. I added a separate column to my version specifically for drugs with a narrow therapeutic window, including the monitoring parameter and the general target range. This took about fifteen extra minutes to populate but it catches questions that otherwise feel like trivia. Drug-drug interactions represent another blind spot. Most checklists either ignore interactions entirely or list them randomly. I built a small secondary section that maps the major CYP450 inhibitors and inducers to the drug classes they most commonly affect. The pattern repeats across classes. Macrolides inhibit CYP3A4, fluconazole inhibits CYP2C9 and 3A4, rifampin induces almost everything. Learning these patterns lets you predict interactions instead of memorizing a separate list. Pregnancy categories deserve attention too. The old A, B, C, D, X system is being replaced by the PLLR format, but many exam questions still use the letter system. I kept both formats on the checklist with a note indicating which drugs have known teratogenic risk versus which ones carry warnings based on animal studies. The difference matters for clinical decisions and for test questions that ask you to choose the safest option in pregnancy.
Where the checklist approach breaks down
This method does not work for everything. Pharmacology kinetics and pharmacodynamics require problem-solving practice, not checklist review. You need to calculate clearances and half-lives and understand volume of distribution. A checklist cannot teach you to solve those problems. I recommend pairing the checklist with a separate workbook for kinetic calculations. The two approaches complement each other but they serve different purposes. Another limitation is that checklists become outdated quickly. New drugs get approved, guidelines shift, and dosing recommendations change. The version I use gets revised every six months and I cross-reference it with the latest clinical guidelines. If you are using a static PDF you found online, verify the information against a current source before relying on it for exam prep or clinical work. Finally, checklists encourage surface-level review if you let them. The temptation is to glance at your completed list and think you know the material. You do not. The real test is whether you can explain why a drug works, what happens when it fails, and what to do when a patient has an adverse reaction. Use the checklist as a starting point, not as proof of mastery.
A practical resource
If you want a starting template, I put together a comprehensive version that covers the major drug classes with the physiology anchors, narrow therapeutic index notes, CYP interaction summaries, and pregnancy category columns I described. You can download it and customize it for your own curriculum. The format is designed to be printed double-sided and used as a reference while you do active recall practice, not as something to read cover to cover before an exam. The file is available at the standard study resource links for this material. I keep the page updated when drug guidelines change, and I include a revision log so you can see what has been modified. Pharmacology moves fast enough that an outdated checklist can do more harm than no checklist at all.

What comes after the checklist
Once you have filled in your version and reviewed it through active recall, the next step is practice questions. A lot of them. The checklist prepares you to recognize patterns. Practice questions teach you how those patterns show up in different contexts. I recommend doing at least two hundred practice questions per major drug class after your checklist work is done. This usually cuts exam preparation time from several weeks down to about ten to fourteen days depending on your baseline knowledge and how many classes you need to cover. Group practice questions by drug class rather than mixing everything together. Spaced repetition across different classes comes later, once you have built familiarity with each category individually. The order matters for retention. Pharmacology is one of those subjects where looking busy and actually learning are two different things. The checklist reduces the volume of information you need to track and forces you to organize it meaningfully. It does not replace practice, and it does not replace understanding the physiology. But used correctly, it removes a significant amount of noise and lets you focus on what actually gets tested. That is generally worth the effort it takes to set it up properly.