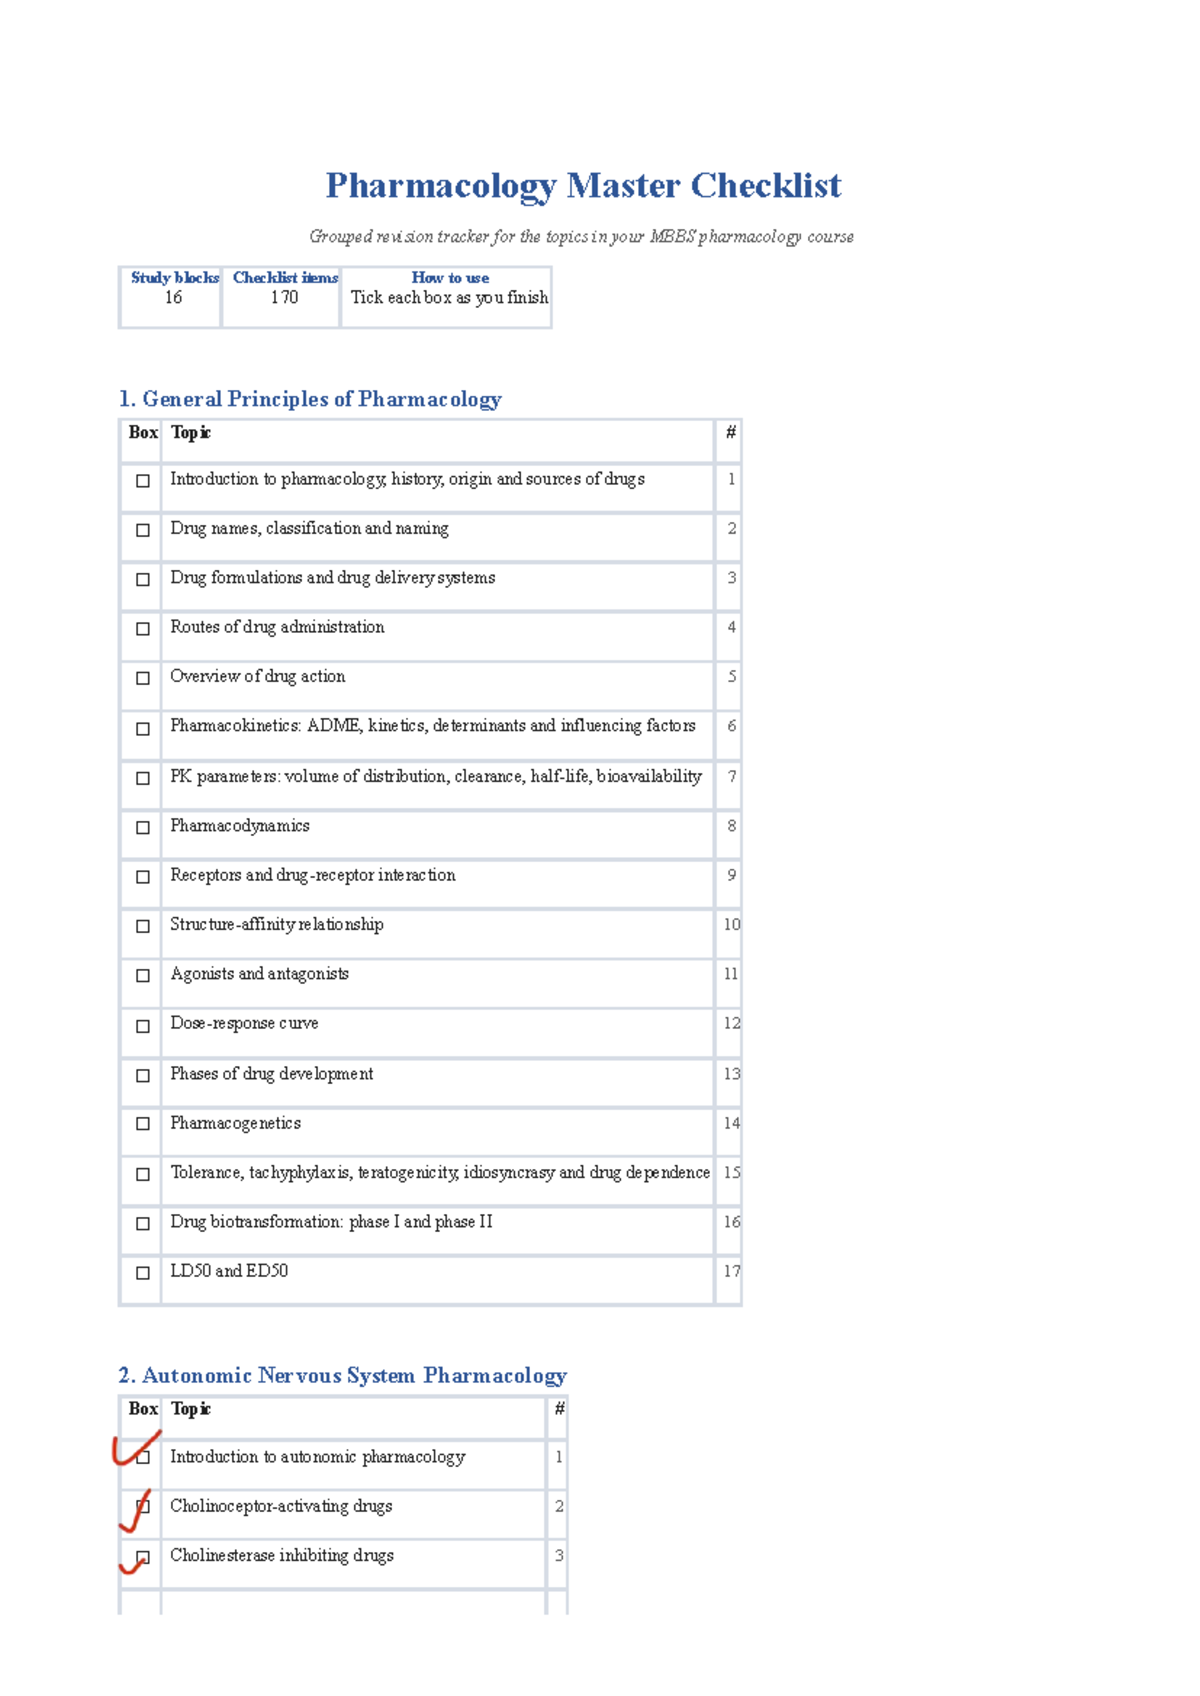
Pharmacology Yearly Review Checklists
Most people who end up making a "checklist for pharmacology yearly" don't realize they're reinventing something that already exists in fragmented form across multiple resources. The truth is, pharmacology revision isn't a single unified subject. It's about eight to ten overlapping domains — drug classifications, mechanism of action pathways, pharmacokinetics and pharmacodynamics, adverse effect profiling, therapeutic indications, drug interactions, dosing adjustments, and then the clinical application layer on top of all of that. A properly structured yearly checklist has to account for each of these without letting any one category dominate your study time disproportionately. I built my first one during second year because my university's pharmacology curriculum covered maybe two dozen major drug classes per semester, but the final exams pulled from everything simultaneously. The old method of re-reading textbooks chapter by chapter was burning out six to eight hours per week and barely moving the needle. What actually worked was shifting to a structured checklist approach that forced active recall instead of passive review. The checklist became a tracking tool as much as a study guide.
Using a Checklist For Pharmacology Yearly
The core idea is straightforward. Create a master list of every topic you need to cover across the full academic year, then break it into smaller sub-items under each category. Here's how I structured mine and how it held up over three years of use: Drug Classification Domains: Beta-blockers, ACE inhibitors, statins, PPIs, SSRIs, SNRIs, antipsychotics, benzodiazepines, opioids, NSAIDs, anticoagulants, antiplatelets, corticosteroids, insulin and oral hypoglycemics, antiepileptics, antibiotics across all major classes, antifungals, antivirals, antihelmintics, antimalarials, chemotherapeutic agents, biologic response modifiers. That's roughly 35 to 40 drug classes depending on how granular you get. Each one needs its own row in the checklist with the sub-items listed below. Sub-items per drug class: Mechanism of action, receptors or enzymes targeted, primary indication, secondary indications, pharmacokinetics — absorption, distribution, metabolism, excretion specifics, half-life, bioavailability, active metabolites, dosing ranges for adults, pediatric dosing notes, geriatric considerations, hepatic impairment adjustments, renal impairment adjustments, major adverse effects, idiosyncratic reactions, black box warnings, key drug-drug interactions, antidotes where applicable, monitoring parameters, contraindications, pregnancy category, and at least five representative prototype drugs you can use as reference points for the entire class. That's 17 sub-items per drug class. Multiply that by 35 and you're looking at roughly 600 discrete review points for a full yearly coverage cycle.
The practical workflow: Each week, pick two drug classes. For each class, cover all 17 sub-items using active recall. Close the textbook and write down everything you remember from memory, then check what you missed. Mark each sub-item as green for confident recall, yellow for partial, or red for doesn't exist in your brain yet. Red items get revisited within 48 hours. Yellow items get revisited within four days. Green items enter a spaced repetition schedule of seven, fourteen, and thirty-day reviews. This system typically cuts total study time per drug class from around four hours of passive reading down to about ninety minutes of active work, though that varies based on how much foundation you already have. A real problem I ran into: About midway through third year, I discovered my checklist had a blind spot. I was studying drug classes in isolation — beta-blockers here, ACE inhibitors there — but the exam questions were increasingly asking about combined therapy. A patient with heart failure and COPD. A diabetic patient starting an SSRI. These combo scenarios weren't covered by any single class entry in my checklist. I spent roughly two weeks building an entirely separate cross-reference section that mapped out at least forty common comorbidity combinations with their pharmacological implications. That single addition changed my exam performance noticeably because the question patterns shifted that semester toward clinical vignettes rather than pure recall. Common mistakes that waste time: The most frequent error I see is making the checklist too broad and never actually using it. A checklist with three hundred items and no time allocation will sit on your desk unused. The second mistake is treating all sub-items equally. Not every drug class needs the full 17 sub-items covered at the same depth. High-yield drugs used in emergency settings or frequently tested topics like anticoagulants, insulin protocols, and antibiotic stewardship deserve more granular breakdowns than say, some of the less commonly prescribed dermatological agents. Allocate your checklist rows proportionally to clinical relevance and exam frequency.
Get the Full Details

The pharmacokinetics and pharmacodynamics catch: Beginners often treat PK and PD as separate memorization tasks. They're not. Understanding first-pass metabolism changes everything when you're comparing oral versus intravenous dosing for the same drug. Knowing about CYP450 enzyme induction and inhibition is the difference between spotting a dangerous interaction and missing it entirely. I learned this the hard way when I could recite half-lives and clearance rates but couldn't explain why fluconazole required a dose reduction in a patient on warfarin. Once I started linking every PK concept to a clinical consequence in my checklist notes, the retention improved dramatically. What this system doesn't handle well: The checklist approach assumes you already have access to quality source material. If your primary resource is outdated or contains inaccuracies, the checklist will just track your mistakes more efficiently. Also, this method is weak on pattern recognition and clinical reasoning development. It's excellent for covering breadth and ensuring nothing falls through the cracks, but it won't make you better at interpreting lab values, adjusting doses in real time, or explaining rationale to a patient. For those skills you need separate clinical case studies and practice questions. The checklist keeps you informed. Practice cases make you competent. Resource recommendations: Goodman and Gilman is the reference standard but it's impractical for checklist-based studying due to its length. Katzung is more concise and better suited for this approach. First Aid for the USMLE Step 1 has a pharmacology section that works well as a checklist backbone. Anki decks built from your own checklist items will reinforce spaced repetition far better than pre-made cards because they force you to process the material during creation. Lippincott's Illustrated Reviews Pharmacology is useful for visual learners who need mechanism diagrams alongside their checklist items.
Digital vs. paper: A digital spreadsheet gives you filtering and progress tracking capabilities. You can sort by topic, difficulty level, or date last reviewed. Paper checklists have one advantage — no screen distraction and the physical act of writing reinforces memory. I used both simultaneously. Spreadsheet for tracking and paper for the actual review sessions. The compromise costs more organizational effort but the split system kept the data organized while preserving the memory benefit of handwriting. If you're starting this process fresh, don't try to build the perfect checklist upfront. Start with a minimum viable version covering the ten highest-yield drug classes first. Test it for two weeks. Refine the format based on what actually gets used and what gets ignored. Then expand. The checklist that sits on your desk incomplete but actively used is worth more than the comprehensive one that never gets opened.