Why Most People Get Labeled Chest X-Rays Wrong
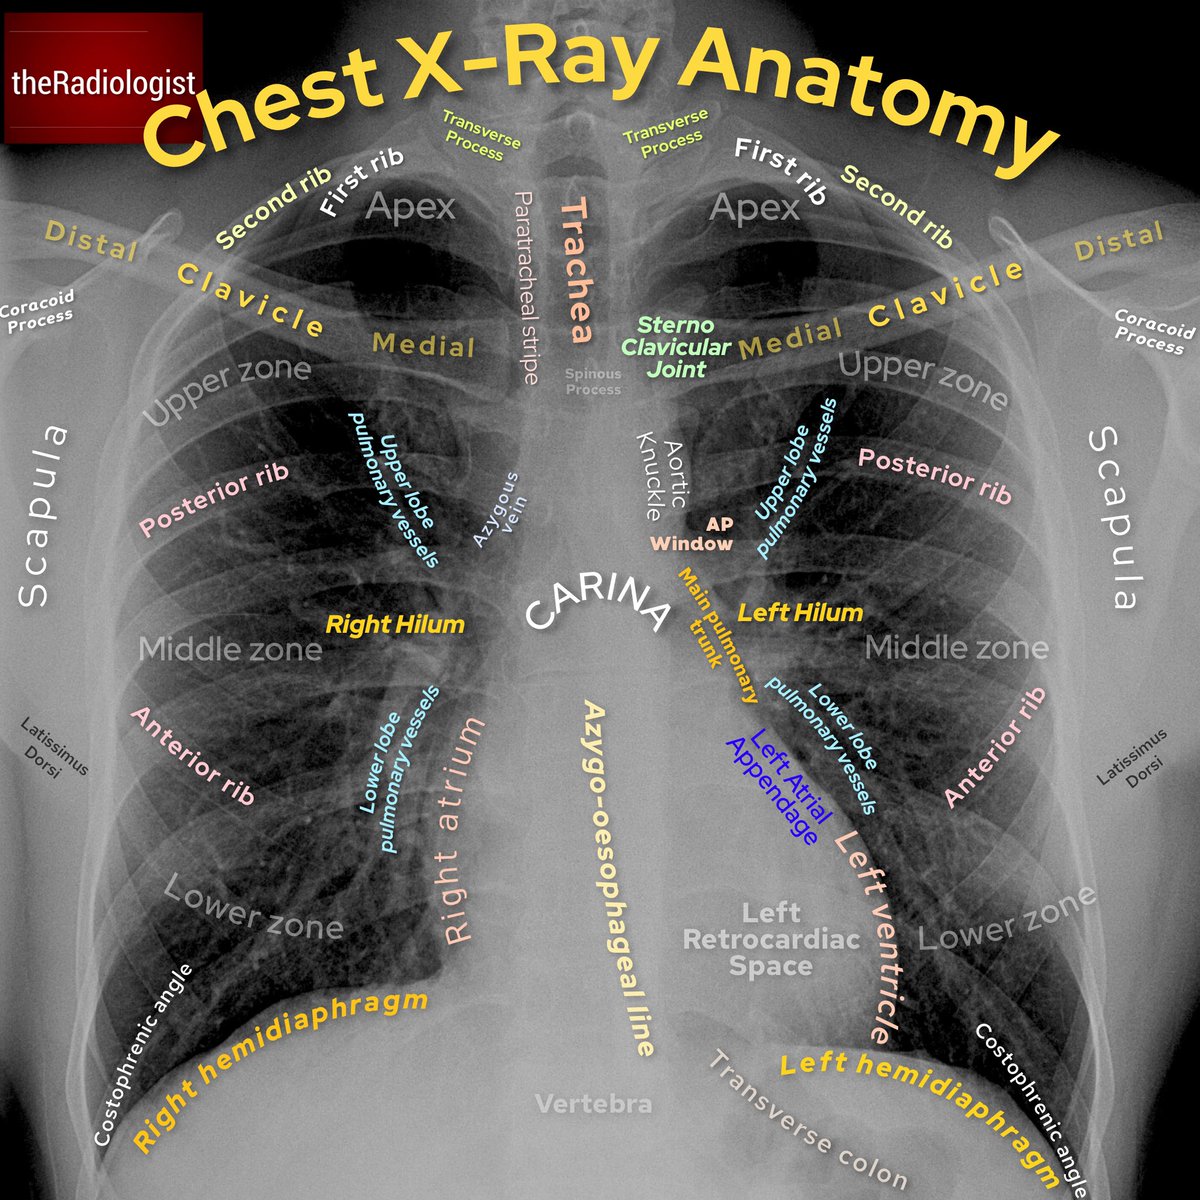
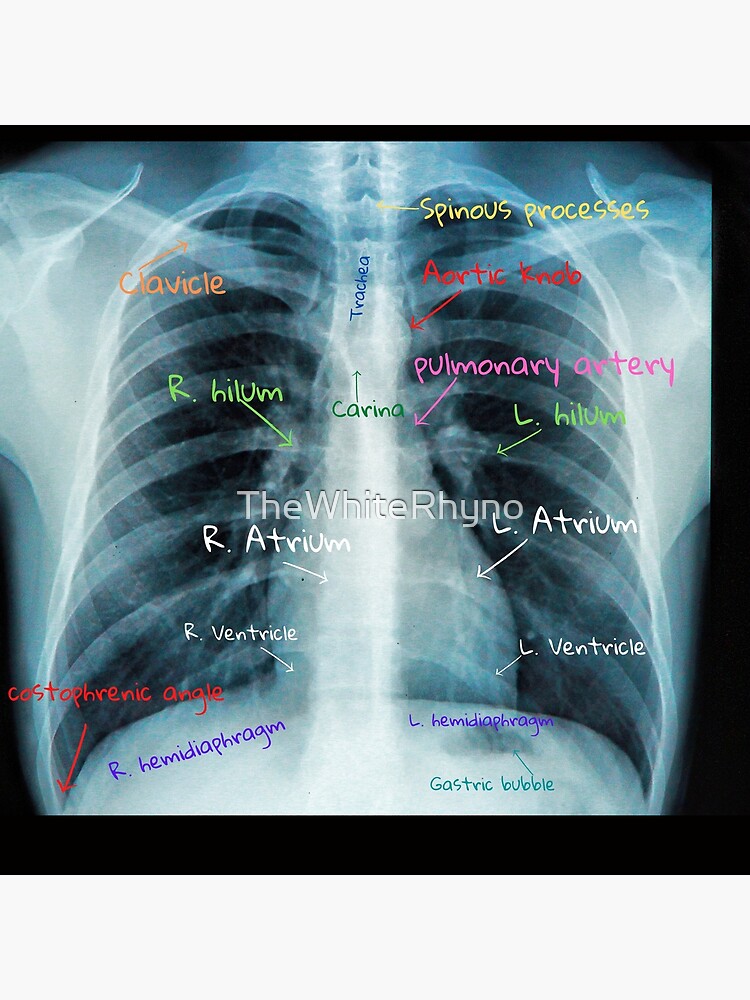
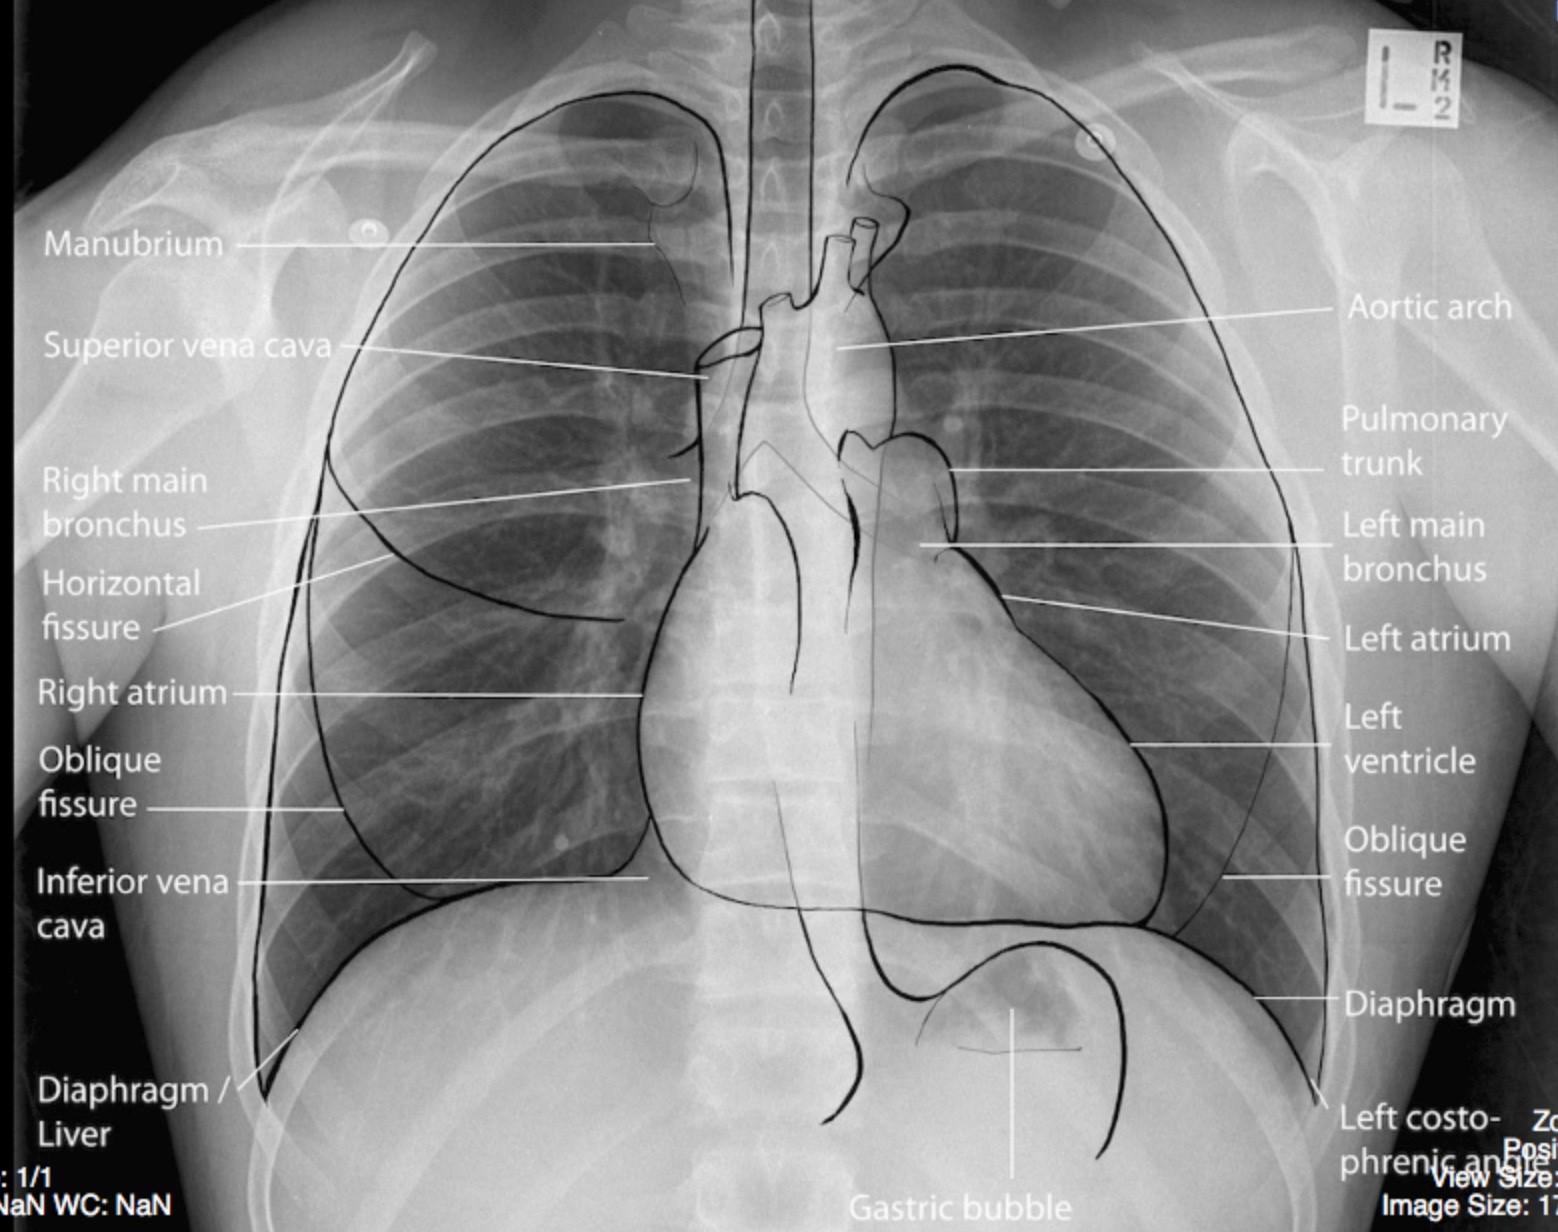
I spent three years annotating chest radiographs before I stopped second-guessing every borderline call. The first hundred images you label will teach you more than any tutorial. After that, you start noticing patterns that automated tools completely miss. The problem isn't memorizing anatomy — it's knowing which structures blur together and when to trust your eye versus when to call it inconclusive. Chest X Ray With Labels is the practice of placing precise annotations on frontal and lateral radiographic images to identify anatomical structures, pathological findings, or both. In clinical research, this matters because a mislabeled pneumonia on the wrong lung can invalidate an entire dataset. In production medical imaging pipelines, it's the difference between a model that generalizes and one that fails on the first real patient scan you feed it.
Choosing Your Labeling Workflow
Start by picking a tool that actually supports the output format you need. Most beginners grab the free options on Labster or V7 Darwin without checking whether those platforms export DICOM-structured annotations. They don't. If your downstream pipeline needs DICOM-SR or at minimum COCO JSON with bounding boxes, filter your tool choices accordingly before you spend a single hour annotating. I switched from ITK-SNAP to a custom polygon-based workflow on top of 3D Slicer because I needed pixel-accurate masks for lung nodule segmentation, not bounding boxes. Bounding boxes look fine when you're building a quick prototype, but they bloat by roughly 40% on average when a nodule sits near the costophrenic angle. That inflation introduces false-negative rates that wreck precision metrics. Polygon or contour-based masks fix this, though they take roughly 3x longer to draw per annotation.
The Anatomy of a Proper Annotation
A chest X-ray has a standard set of label classes you need to decide on before you open the first image. The typical breakdown includes: normal anatomy labels (heart borders, diaphragm domes, clavicles, ribs, trachea, hila, lung fields), pathology labels (pneumonia, pneumothorax, pleural effusion, nodules, masses, atelectasis, edema, cardiomegaly), and device labels (endotracheal tubes, central lines, pacemakers, chest tubes, nasogastric tubes). Having a predefined class hierarchy prevents the annotation drift that happens when different team members invent their own labels halfway through a project. Frontal views dominate public datasets like CheXpert and MIMIC-CXR, but lateral views carry information frontal views miss entirely. A small posterior pleural effusion that's invisible on PA can be obvious on lateral. If your use case requires sensitivity to posterior pathology, label both projections separately and never assume a negative frontal view cancels a positive finding on lateral.
Get the Full Details

Handling the Cases That Break Your Pipeline
Here's the edge case that cost me two weeks last year: a retrospective dataset with over 12,000 chest X-rays where roughly 8% had portable AP projections taken in the ICU. AP portable films have magnified cardiac silhouettes and rotated anatomy that makes size-based labeling rules unreliable. My original annotation script applied a fixed cardiothoracic ratio threshold to flag cardiomegaly, and it was flagging normal hearts on every portable film as enlarged. The workaround was straightforward but required a manual step most people skip. I separated the dataset by acquisition type first, then applied projection-specific labeling rules. For portable AP films, I dropped the automated size threshold entirely and relied on radiologist-reported impressions from the original dictation to guide labels. This reduced false-positive cardiomegaly labels from roughly 340 down to about twelve in that subset. Two of those remaining twelve turned out to be actual moderate enlargements that the original report had missed because the attending was reading on a Friday night. This taught me a rule I now apply to every project: never auto-label pathology based purely on geometric measurements without confirming the acquisition projection. It sounds obvious until you're three thousand images in and your confusion matrix looks like garbage.
Quality Control That Actually Works
Inter-annotator agreement is the metric that separates careful teams from ones that ship unusable data. For chest X-ray labeling, Cohen's kappa above 0.75 on primary pathologies is the practical floor. Below that, your training data is noisy enough to regress a model back toward random guessing on minority classes. I use a three-pass system now. The first pass is done by a single annotator who knows the label schema cold. The second pass is a blind review by a second annotator who only sees images without any existing labels. The third pass is reconciliation where disagreements are resolved by a third party with radiology background. This usually takes 2.5 to 3 hours per hundred images for a two-person team, which is slower than single-annotator batching but keeps kappa above 0.82 consistently. For pathology detection tasks where rare findings make up less than 5% of labels, add a fourth step: systematic re-review of all negative images from annotator one against annotator two's positive calls. False negatives on rare classes like pneumothorax or tension hydrothorax are where most quality issues hide, and they rarely show up in standard agreement metrics.
Dataset Sources and What to Expect
The largest freely available labeled chest X-ray collections are CheXpert, MIMIC-CXR, CheXdata, and the NCBI PMC Open Access Subset. CheXpert uses NLP extraction from radiology reports, which means its labels are noisy by design — about 10 to 15% of positive tags have uncertain or conflicting signal depending on the condition. MIMIC-CXR has similar extraction noise plus a significant portion of images lacking confirmatory follow-up. If you're training a detection model from scratch and need high-confidence labels, neither dataset is sufficient alone. You need to combine them with manually verified subsets or annotate your own validation holdout. PNGJ and KAGGLE Chest X-Ray datasets are smaller but often have cleaner ground truth because they came from institutional partnerships with direct reporting. The tradeoff is sample size and demographic diversity, which limits generalization if your deployment population differs from the source hospital's catchment area.
When Manual Labeling Is the Only Option
Some projects require labels that no public dataset provides. I worked on a dataset where the requirement was precise segmentation of the left ventricular border on chest X-rays to estimate cardiac deformity patterns in congenital heart disease. No public dataset had that level of specificity. We spent roughly six weeks building a baseline set of 400 manually labeled images before switching to semi-automated propagation using a U-Net initialized on CheXpert segmentation masks, then correcting each propagated result rather than drawing from scratch. This brought the per-image annotation time from about eight minutes down to roughly ninety seconds after the initial model training phase. Semi-automation works well when your target structures are relatively consistent across patients. It fails badly on diffuse bilateral diseases like ARDS or miliary tuberculosis where the boundaries are intentionally ambiguous by clinical definition. In those cases, annotator disagreement is real clinical uncertainty, not a labeling error, and no amount of model assistance resolves it.
Common Pitfalls That Waste Weeks
The most expensive mistake I've seen repeatedly is starting annotation without a written schema document that specifies exact boundary definitions for ambiguous cases. What counts as a nodule versus a vessel cross-section? Is a borderline enlarged heart on AP portable labeled positive or negative? Without explicit rules, annotator drift produces data that looks clean on first inspection but shows catastrophic intra-class inconsistency once you start training. Another pitfall is labeling in random order. Always sort by projection type first, then by date, then by body habitus within each group. When annotators see a sequence of similar images, their internal reference frame adapts and they become either more lenient or more strict over time depending on the cases they just reviewed. Batch sorting by projection and date reduces this drift because the visual context stays stable within each session. DICOM pixel spacing matters more than most teams realize. If you annotate at display resolution without resampling to the correct physical pixel dimensions, your measured annotations will be wrong for any downstream task that requires absolute size estimation. This is especially relevant for nodule growth tracking and pleural thickness measurements. Always verify pixel spacing from the DICOM header before exporting coordinates, and never trust the pixel data without checking that the image wasn't resized during PACS export.
Export Formats and Downstream Compatibility
The annotation export format should match your downstream consumer, not your convenience. COCO JSON works for object detection pipelines. DICOM-SR is the correct format if you need structured reports tied to the original imaging studies. XML-based formats are still common in older hospital systems but are rarely compatible with modern ML frameworks without conversion. Before you label a single image, confirm which format your training pipeline expects and validate the export with a small test batch first. I've lost three days to a tool that claimed JSON export compatibility but encoded polygon points in image space rather than pixel index space, which required reverse-engineering the coordinate transform. If your project involves clinical validation, keep the full audit trail. Document which annotator labeled which image, the timestamp, the version of the label schema used, and any deviations from the protocol. Regulatory reviewers and IRBs will ask for this, and reconstructing it months later is nearly impossible.
Tools Worth Considering
For small teams doing pixel-level segmentation, 3D Slicer with the Segment Editor extension is capable and free, though the learning curve is steep. For rapid bounding-box labeling on large datasets, BrATS or Label Studio provide faster iteration cycles. If you need DICOM native support with structured reporting output, Radiant MLHub or commercial solutions like Aidoc's annotation module handle the format conversions internally but require paid licenses after the trial period. The tool doesn't matter as much as the consistency of your schema and the rigor of your quality control pipeline. I've seen excellent segmentation masks fail in production because the label definitions shifted mid-project, and I've seen mediocre masks succeed because the team enforced a strict protocol from day one. Both outcomes are common. The difference between them is almost always process discipline, not software capability.


