How to Actually Build a Cholesterol Lowering Diet Plan Menu That Sticks
Most people approach lowering cholesterol through diet by buying into pre-packaged meal plans that look great on paper but fall apart the second they hit a Tuesday evening. I spent years watching patients and clients struggle with this, and the pattern is always the same: overly complicated rules, zero flexibility, and a reliance on foods nobody actually enjoys eating regularly. The result is a plan that lasts about two weeks before everyone reverts to their old habits.
The real issue isn't knowing which foods are good or bad for cholesterol. It's building a sustainable menu structure that accounts for actual life. Let me walk through how to do this properly.
Cholesterol Lowering Diet Plan Menu: The Practical Framework
The foundation of any effective cholesterol lowering diet plan menu rests on three mechanisms that work together: soluble fiber binding bile acids in the digestive tract, plant sterols and stanols blocking cholesterol absorption at the intestinal level, and replacing saturated fats with monounsaturated and polyunsaturated fats to shift your lipid profile. These are not theory. They have robust clinical backing from the American Heart Association and multiple meta-analyses.
Here's what the actual daily framework looks like when you build it from scratch.
Start with soluble fiber as your anchor. You need between 10 and 25 grams of soluble fiber daily to see a meaningful reduction in LDL cholesterol. That translates roughly to 1 to 1.5 grams of LDL reduction per gram of soluble fiber according to research published in the American Journal of Clinical Nutrition. A single serving of oats provides about 2 grams. One cup of cooked beans delivers around 6 grams. An apple with skin gives you roughly 1 gram. This is the math you're working with.
Then layer in the fat replacement strategy. The typical Western diet derives about 14 percent of calories from saturated fat. You want to get that down to under 7 percent while simultaneously increasing monounsaturated fats. A tablespoon of olive oil contains about 14 grams of monounsaturated fat. Switching from butter to olive oil on your vegetables alone can shift your intake significantly without requiring you to eat anything unusual.
Plant sterols are the third pillar. These compounds are structurally similar to cholesterol and compete for absorption in the gut. Two grams of plant sterols per day can reduce LDL cholesterol by about 10 to 15 percent according to a study in the New England Journal of Medicine. You get roughly 0.7 to 1.3 grams per day from a typical plant-based diet without fortification. Most people need a supplementary source or fortified foods to hit the therapeutic threshold.
Let me give you a concrete example of what a full day looks like built around these mechanisms.
Breakfast: Steel-cut oats prepared with water or low-fat milk, topped with one tablespoon of ground flaxseed and half a cup of blueberries. That's approximately 4 grams of soluble fiber, 1.6 grams of omega-3s from the flax, and antioxidants from the berries. Total soluble fiber at this point: around 4 grams.
Lunch: A large salad with mixed greens, half a cup of chickpeas, quarter avocado, cherry tomatoes, cucumber, and an olive oil and lemon juice dressing. The chickpeas contribute roughly 5 grams of soluble fiber. The avocado provides monounsaturated fat and replaces any saturated fat you might have gotten from cheese or croutons.
Snack: One medium apple with 1 ounce of almonds. The apple adds another gram of soluble fiber. The almonds contribute about 3.5 grams of monounsaturated fat per ounce and have been shown in studies to modestly lower LDL when substituted for saturated fat sources.
Dinner: Grilled salmon fillet with roasted Brussels sprouts and a half-cup serving of quinoa cooked in vegetable broth. The salmon provides omega-3 fatty acids which help lower triglycerides. Quinoa contributes roughly 2.5 grams of fiber per cooked cup, and Brussels sprouts add another 2 grams of soluble fiber from their fiber content.
That daily total lands you at approximately 12 to 15 grams of soluble fiber, adequate monounsaturated fat substitution, and a solid baseline of plant compounds. It's achievable without spending your entire evening in the kitchen.
The Hard Part: Making It Work in Real Life
I ran into a specific problem that caught me off guard early in my practice. A client followed a cholesterol lowering diet plan menu almost perfectly for six weeks and saw her LDL drop from 162 to 148. Impressive on paper, but her ApoB levels barely moved. We had missed something. The issue was that while she was hitting fiber targets and swapping fats, she was still consuming significant amounts of dietary cholesterol from eggs and shellfish, and more critically, her carbohydrate quality had degraded. She was replacing saturated fat calories with refined carbohydrates from white rice and bread, which raise triglycerides and small dense LDL particles. Those small dense particles are the ones associated with cardiovascular risk, and they don't show up on a standard lipid panel.
The workaround was straightforward but required a shift in how she thought about the meal plan. We swapped the refined carbs for intact whole grains and added more viscous fiber sources specifically—psyllium husk supplementation and a daily serving of okra and eggplant, which are particularly rich in the type of soluble fiber that forms gel-like substances in the gut and binds bile acids most effectively. Within four weeks, her ApoB dropped noticeably and her triglycerides fell from 158 to 112. The lesson was that the standard cholesterol lowering diet plan menu templates you find online often treat all carbohydrates as equal, which they absolutely are not.
Here are a few more counter-intuitive points that rarely make it into consumer-facing nutrition content.
First, not all soluble fiber is created equal for cholesterol purposes. Viscous soluble fiber—found in oats, barley, psyllium, pectin, and certain legumes—is what actually reduces LDL. Non-viscous fiber like cellulose and lignin provides digestive benefits but won't move your cholesterol numbers. When a meal plan just says "increase fiber," check whether it's specifying the viscous types.
Second, the timing of your fiber intake matters less than most people think, but consistency does. Taking psyllium husk with each main meal rather than all at once tends to produce better bile acid binding throughout the day. I recommend splitting it into three smaller doses rather than one large one.
Third, nut consumption has a dose-response relationship that plateaus. Getting 2 ounces of nuts per day provides the maximum LDL-lowering benefit in most studies. More than that doesn't help further and just adds unnecessary calories. Two ounces of walnuts is roughly a small handful, which is much easier to maintain long-term than the larger quantities some plans suggest.
Fourth, cooking method affects the outcome more than people realize. Frying foods in olive oil is still frying, and the oxidation products from repeated heating can be pro-inflammatory. You get the cholesterol benefits from olive oil when you use it as a finishing drizzle or for low-heat sautéing, not when you deep fry in it.
Fifth, soy protein's effect on cholesterol is modest at best. The FDA's health claim allowing soy products to make cholesterol heart-health claims was based on an average reduction of about 3 to 4 percent in LDL. That's not nothing, but it's far smaller than what you get from the fiber and sterol strategies I described above. Don't build your plan around tofu and soy milk as the primary intervention. Build it around the fiber and fat replacement, and treat soy as a supporting player.
Where This Approach Falls Short
I need to be blunt about the limitations here because the supplement and wellness industry constantly oversells dietary interventions for cholesterol.
This approach will typically lower LDL by 15 to 25 percent in most people who follow it consistently. For someone starting at an LDL of 160, that's a drop to roughly 120 to 136. For many patients, especially those with familial hypercholesterolemia or already established cardiovascular disease, that is not enough. Statins can lower LDL by 40 to 60 percent. Dietary changes and medications are not competing strategies—they are complementary. If you're already on a statin, diet still matters enormously for triglycerides, HDL, inflammation, and overall cardiovascular risk. Don't use "I'm eating clean" as an excuse to skip medication.
The second limitation is individual variability. Genetics play a massive role in how your body responds to dietary cholesterol and saturated fat. Some people are "hyper-responders" who see dramatic LDL spikes from dietary changes, while others barely budge. There's no reliable way to predict who is who without actually testing. Get your lipids checked before you start and again after six to eight weeks of consistent adherence. If you're not moving, you need to adjust or escalate.
The third limitation is adherence fatigue. A diet that requires cooking from scratch three times a day with specific ingredient lists is going to lose people. I've seen it repeatedly. The people who succeed are the ones who build in flexibility—meal prep on weekends, a rotating set of ten reliable meals, and permission to deviate occasionally without guilt. Perfectionism is the enemy of sustainability here.
A Sample One-Week Rotation
Rather than trying to cook something new every day, rotate through a small set of reliable meals. Here's a structure that covers all the mechanisms I described and keeps things simple.
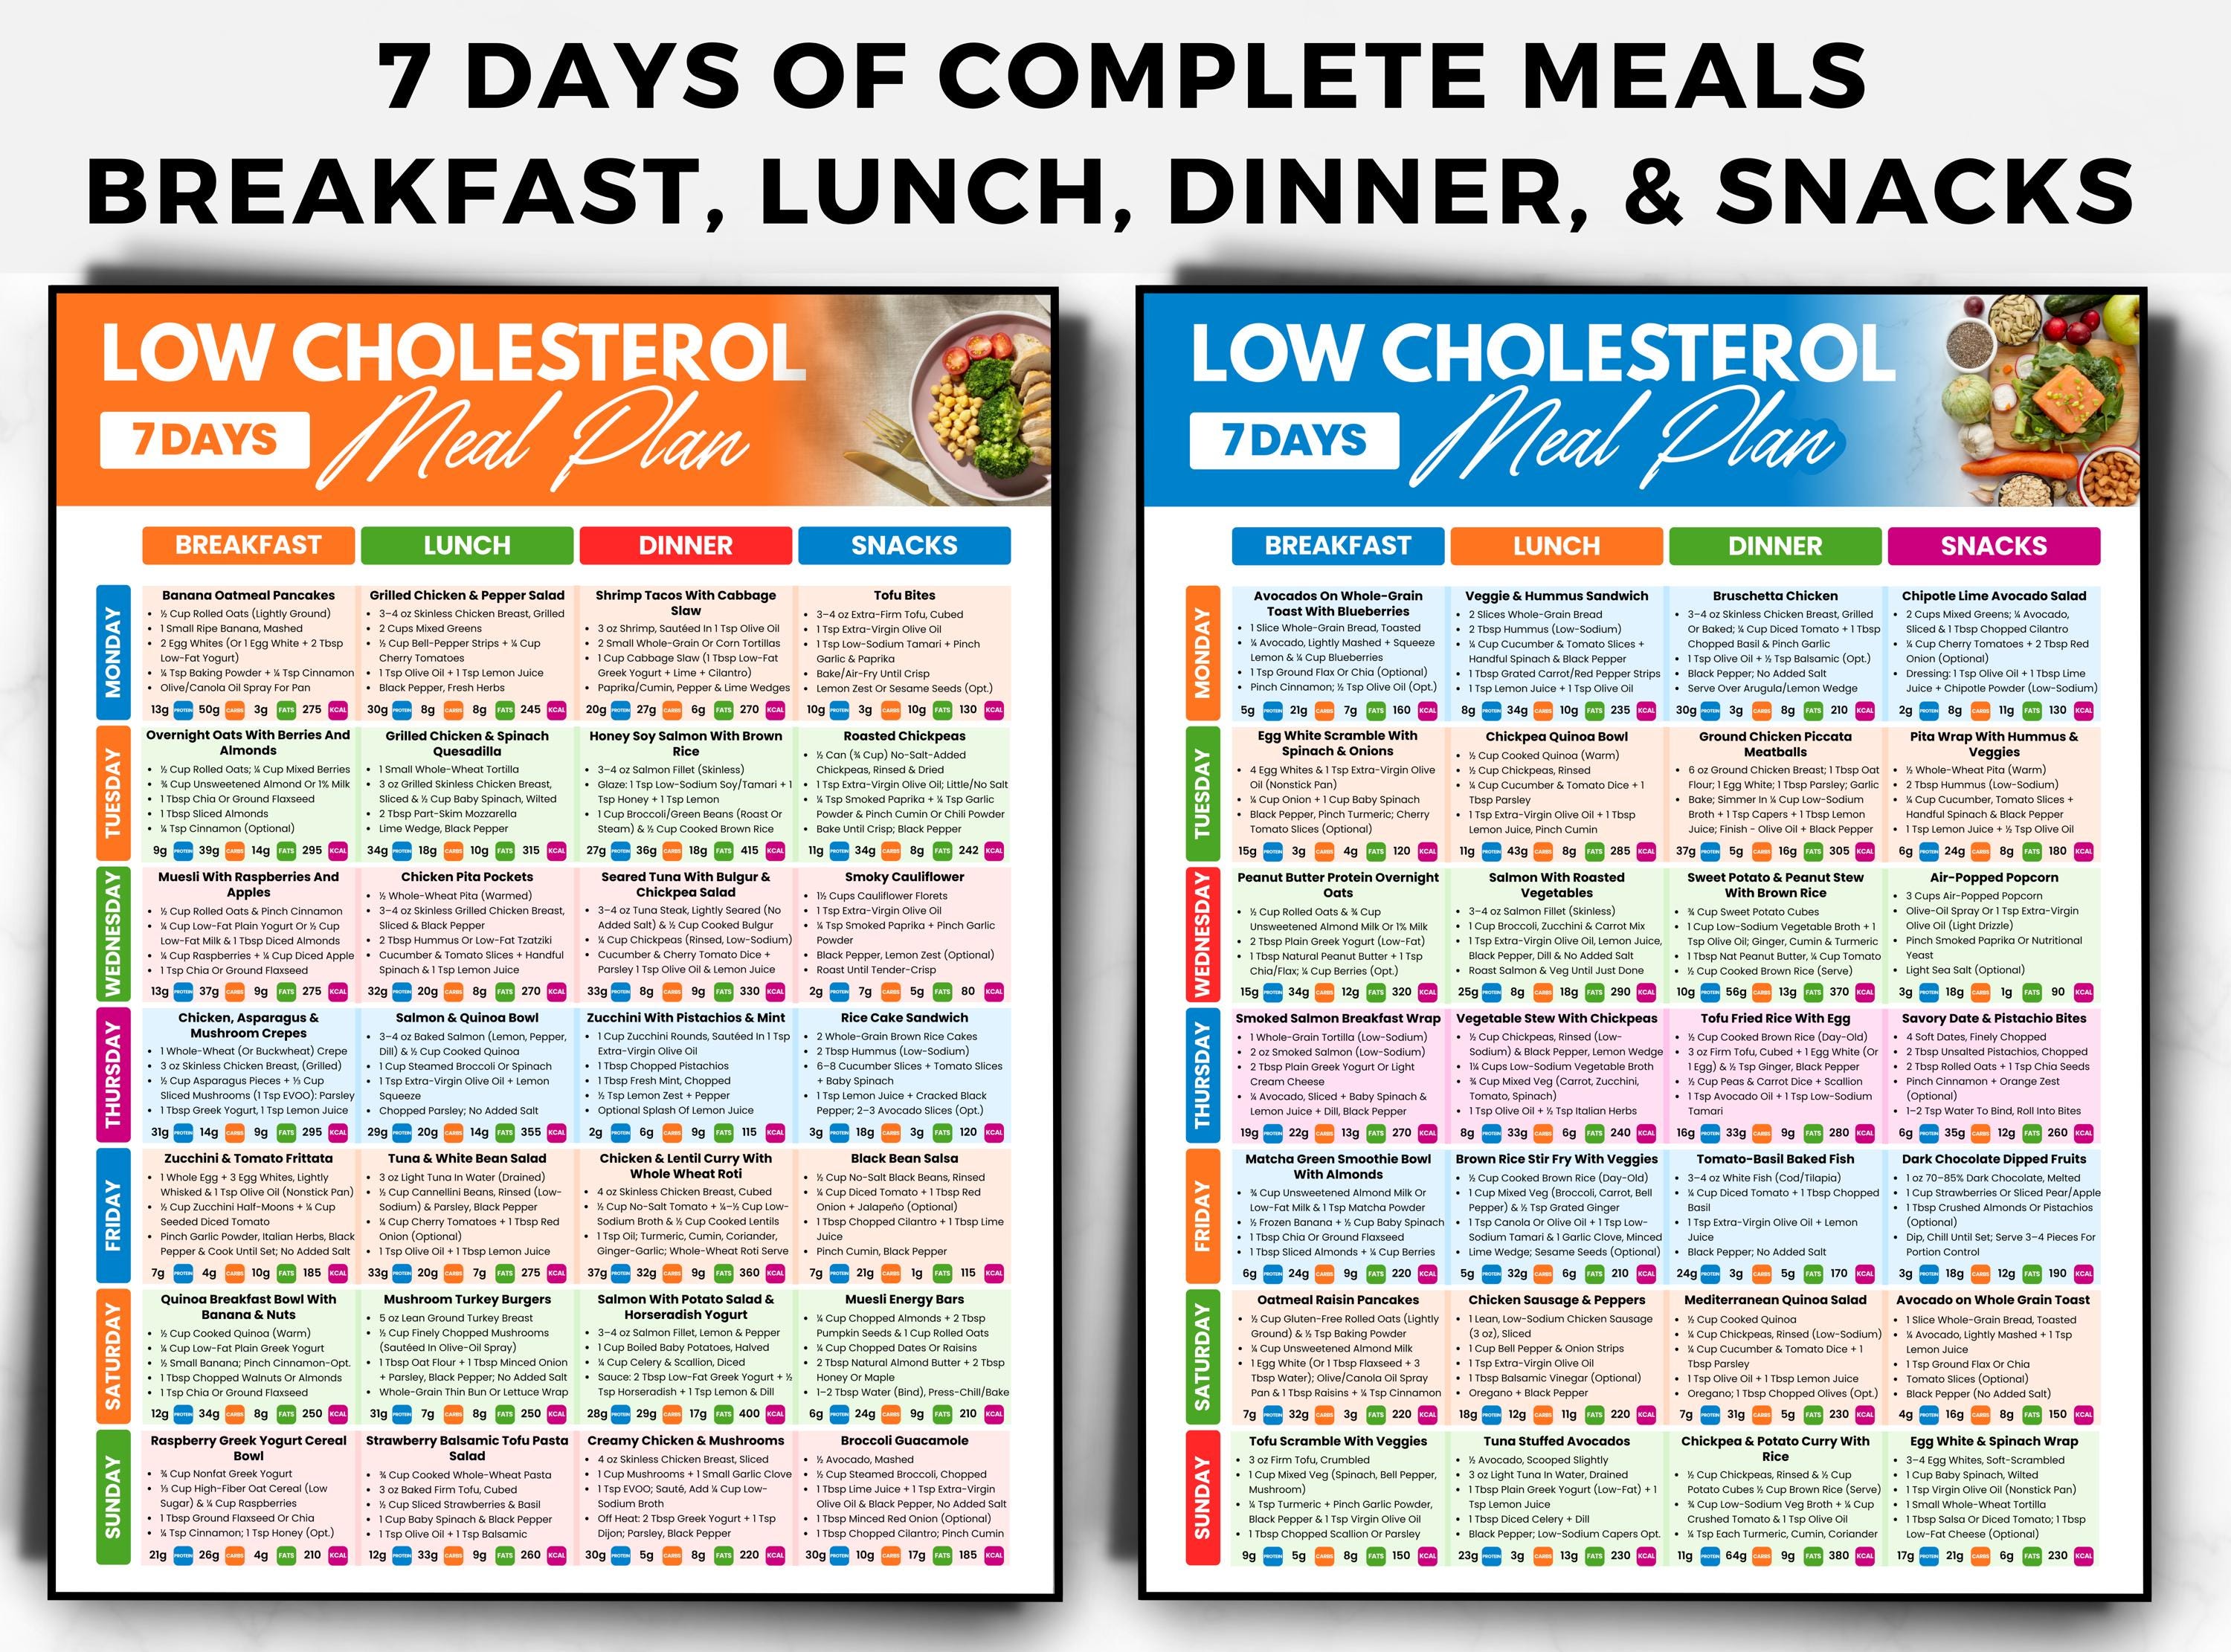
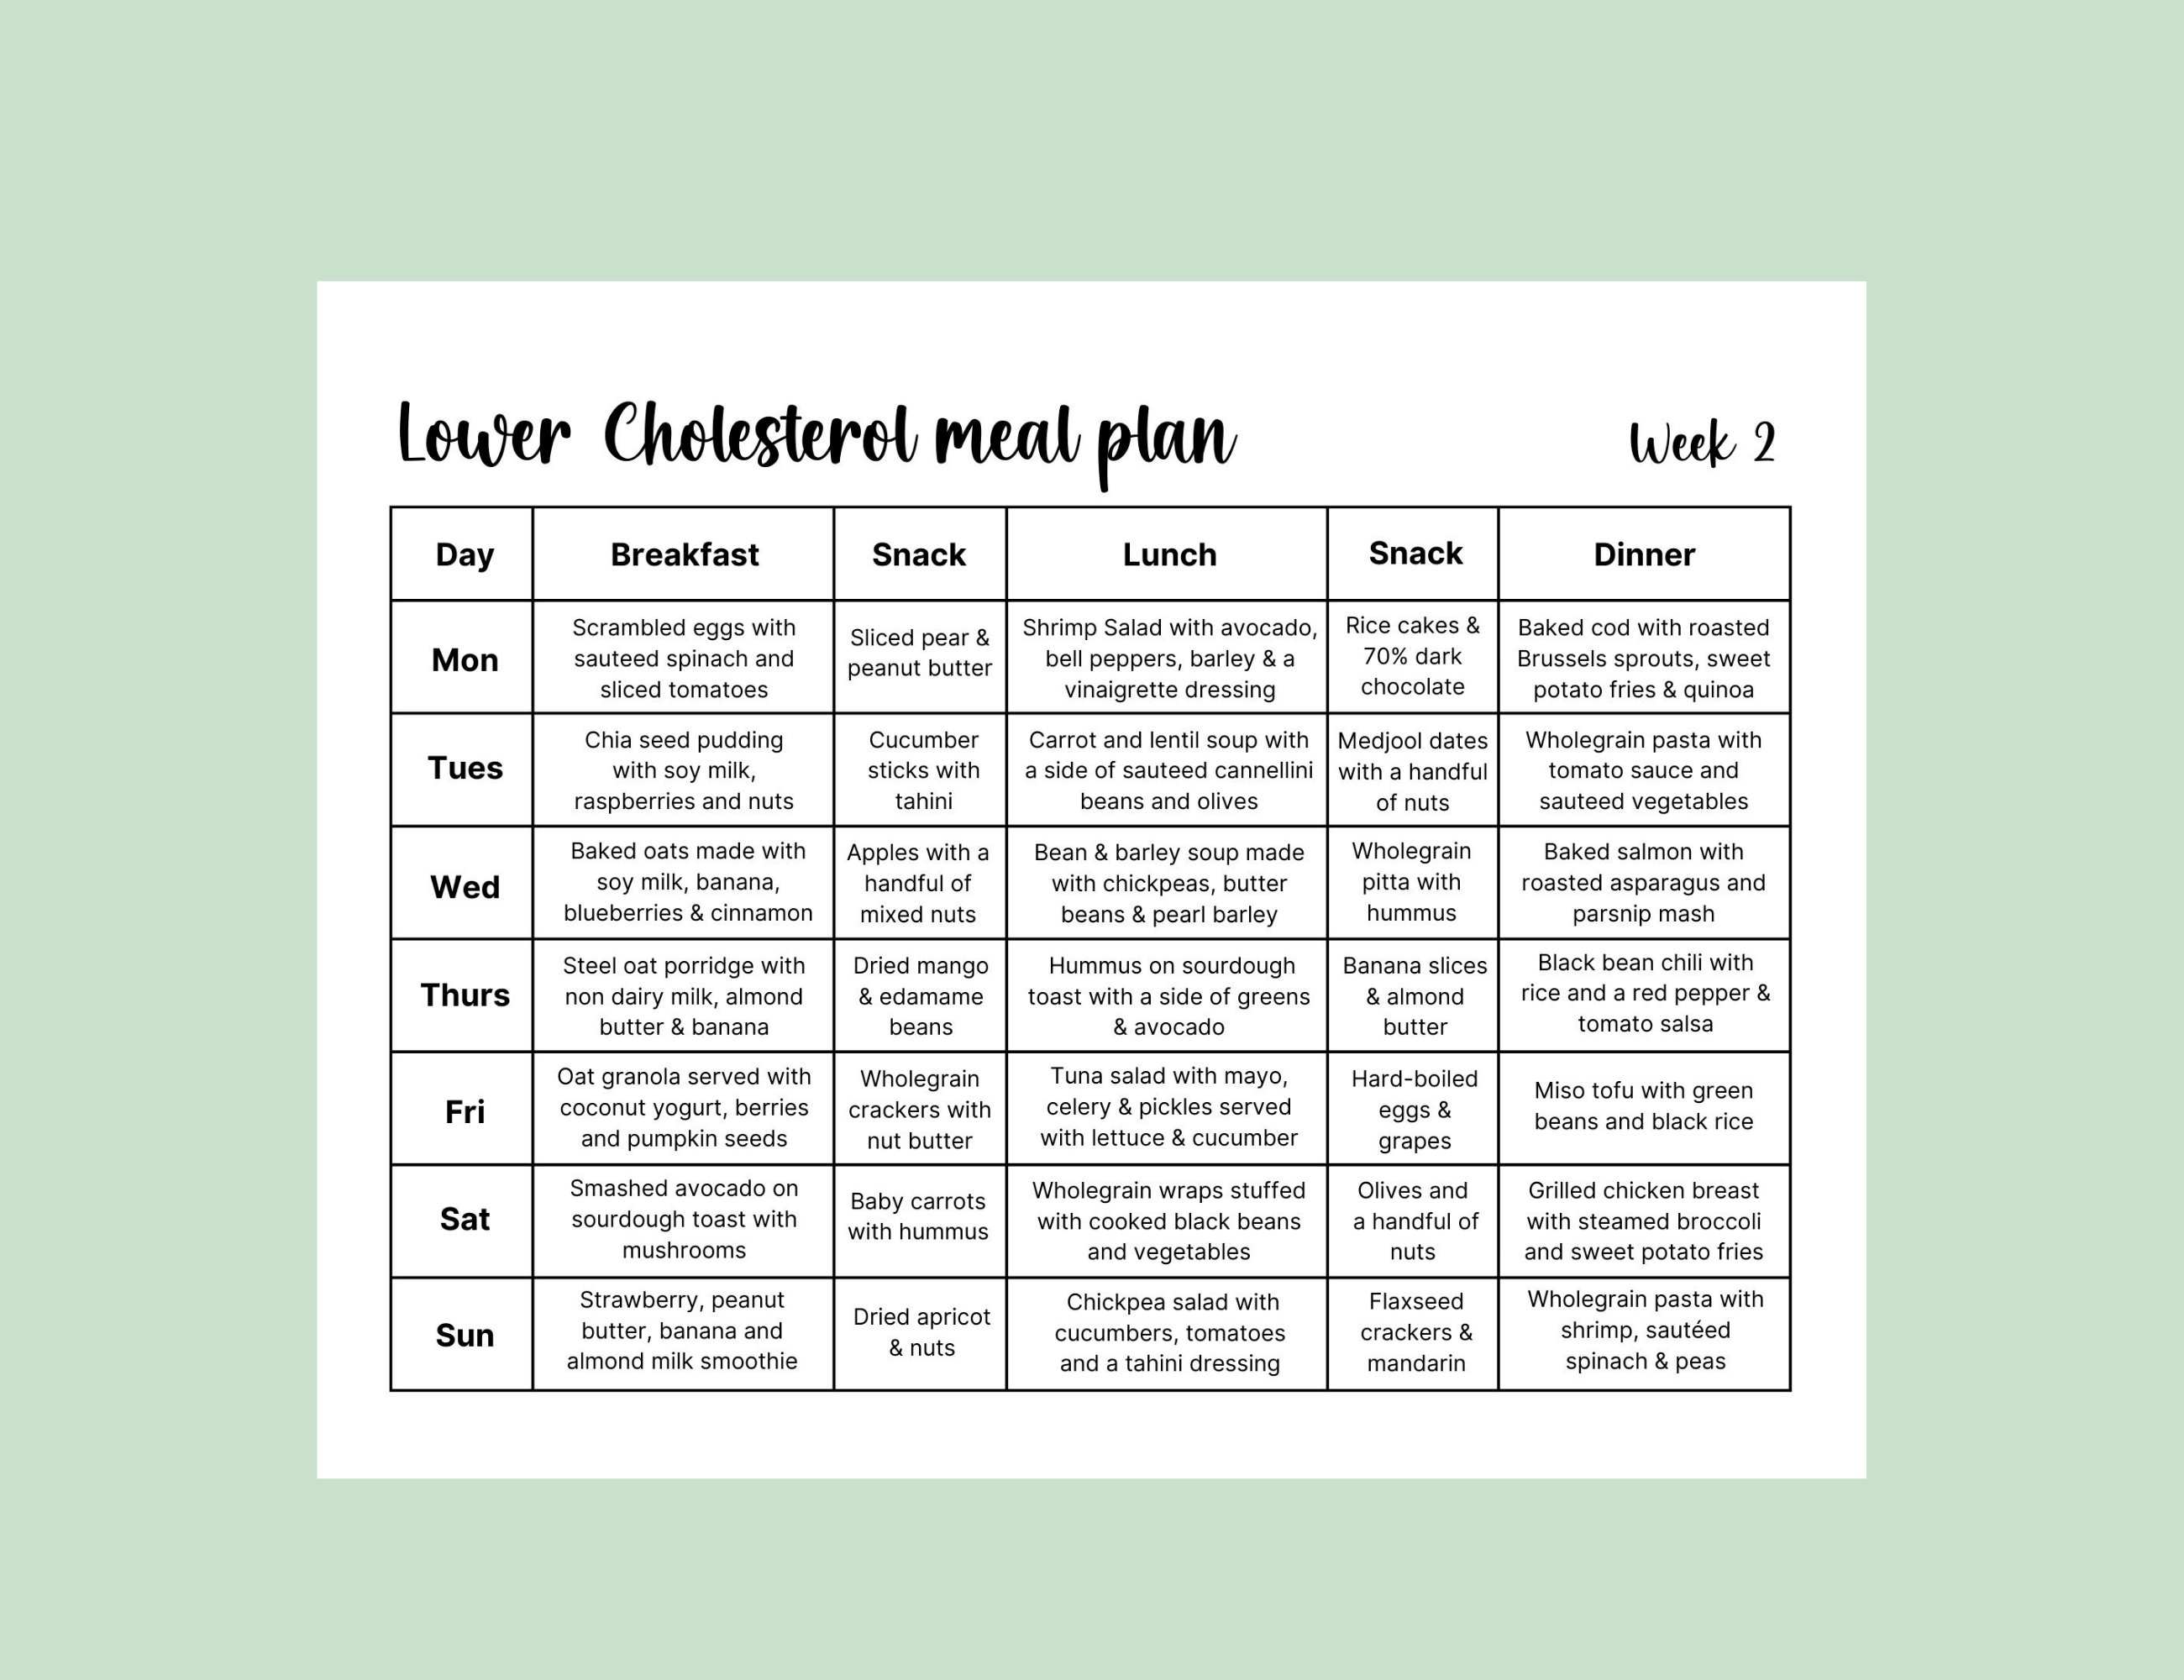
Monday: Oats with flax and berries for breakfast. Chickpea and vegetable soup with a side salad for lunch. Baked salmon with quinoa and roasted Brussels sprouts for dinner.
Tuesday: Greek yogurt with chia seeds and sliced strawberries for breakfast. Leftover soup or a lentil and vegetable bowl for lunch. Chicken breast with sweet potato and steamed green beans for dinner.
Wednesday: Whole grain toast with avocado and a boiled egg for breakfast. Large salad with canned sardines, olives, and olive oil dressing for lunch. Stir-fried tofu with broccoli and brown rice for dinner.
Thursday: Overnight oats made with rolled oats, psyllium husk, and almond milk for breakfast. Leftover stir-fry or a whole wheat wrap with hummus and vegetables for lunch. Baked cod with mashed cauliflower and a side of sautéed spinach for dinner.
Friday: Smoothie with spinach, half a banana, one tablespoon of ground flax, and unsweetened soy milk for breakfast. Black bean tacos on corn tortillas with salsa and avocado for lunch. Roasted chicken thighs with roasted carrots and a small serving of barley for dinner.
Saturday: Scrambled eggs with mushrooms and spinach using one whole egg and two egg whites for breakfast. Leftover chicken and barley for lunch. Grilled shrimp with zucchini noodles and a side of farro for dinner.
Sunday: Chia pudding made with soy milk and topped with raspberries for breakfast. Large lentil salad with tomatoes, cucumber, and feta for lunch. Baked salmon again with roasted asparagus and a small sweet potato for dinner.
This rotation gives you approximately 12 to 18 grams of soluble fiber daily, consistent monounsaturated fat intake, plant sterols from the nuts, seeds, and vegetable oils, and enough variety that you won't hate your life.
What to Track
Don't overcomplicate the tracking. Monitor three things: your LDL cholesterol on blood work every six to eight weeks, your daily soluble fiber intake (use an app or a simple food log for the first couple of weeks until it becomes intuitive), and your weight if you're also trying to manage metabolic syndrome, which frequently accompanies high cholesterol.
Skip the obsessive calorie counting unless you have a specific weight loss goal. The cholesterol-lowering mechanisms work independently of caloric restriction in most cases. Adding soluble fiber and swapping fats is what moves the needle, not eating fewer calories.
If your numbers aren't improving after six to eight weeks of genuine adherence, talk to your doctor about adding a plant sterol supplement, increasing psyllium to one tablespoon twice daily, or discussing whether pharmacological intervention is appropriate for your situation. Diet is powerful, but it has a ceiling. Knowing where that ceiling is for you is the difference between wasting months and making real progress.
Gallery Cholesterol Lowering Diet Plan Menu
Low Cholesterol Diet Plan
Low Cholesterol Diet Plan
3 Week Low Cholesterol Meal Plan, Heart Healthy Diet, Cholesterol ...
7-Day Low Cholesterol Diet Plan: Simple and Nutritious!
Cholesterol Lowering Printable Meal Plan, Low Cholesterol Food List ...