What Actually Happens When You Run a Co-Oximetry Sample
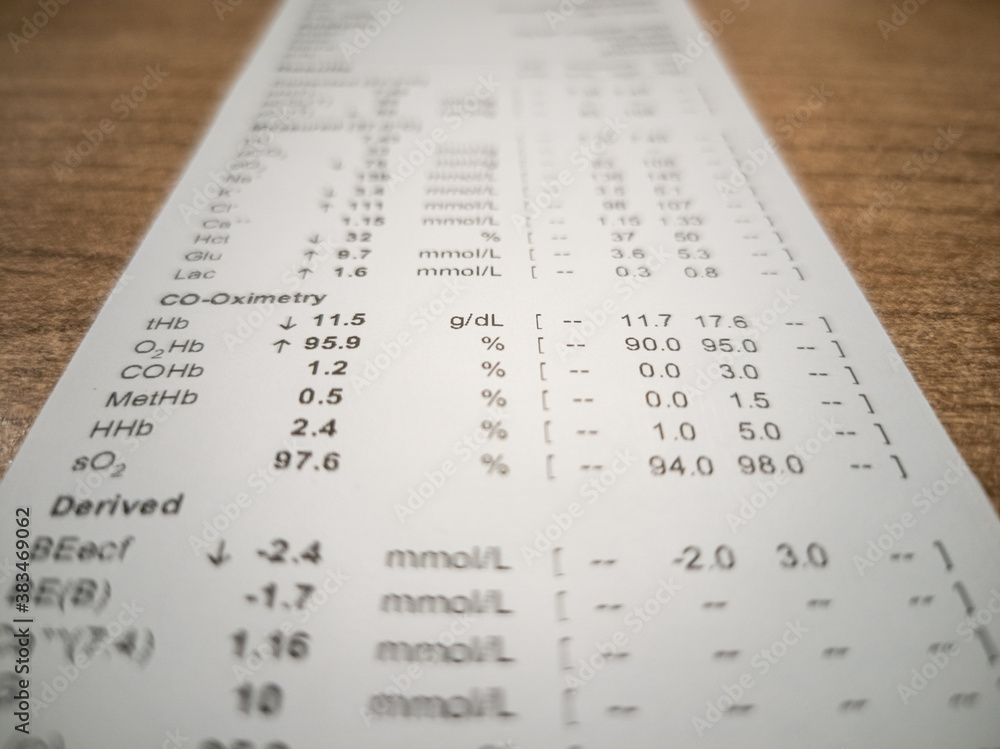
You put the tube in the analyzer, press start, and twelve seconds later you have pH, pCO2, pO2, electrolytes, and a full hemoglobin breakdown including O2Hb, HHb, COHb, and metHb. That is the surface-level picture. The mechanics underneath are straightforward spectrophotometry, but the way the instrument applies it is where most people get tripped up. A Co-oximeter pulls light through a tiny flow cell at multiple specific wavelengths, usually six or more, spanning roughly 500 to 660 nanometers. Each hemoglobin species absorbs light differently at each wavelength. The instrument measures absorbance at every wavelength, runs it through a set of predetermined extinction coefficients, and solves the Beer-Lambert equation system to calculate the fractional percentage of each species. It is not guessing. It is solving a matrix.
Co Oximetry Blood Gas Analysis in Practice
The term itself is slightly redundant because almost nobody runs Co-oximetry as a standalone bench instrument anymore. Modern blood gas analyzers from Radiometer, Siemens, Abbott, and others have Co-oximetry built into the cartridge or cuvette system. You draw a heparinized arterial sample, prime the line, and the same run gives you everything. If your lab still uses a separate Co-oximeter, you are already behind on workflow and should probably look at upgrading, but that is a separate conversation. The standard output gives you four fractions expressed as percentages of total hemoglobin. O2Hb is the oxygenated fraction. HHb is deoxygenated hemoglobin. COHb is carboxyhemoglobin. MetHb is methemoglobin. Some analyzers report O2Content as well, calculated from the O2Hb percentage, total hemoglobin, and dissolved oxygen. Everything is derived from those four measured values.
Why Pulse Oximetry and Co-Oximetry Are Not the Same Thing
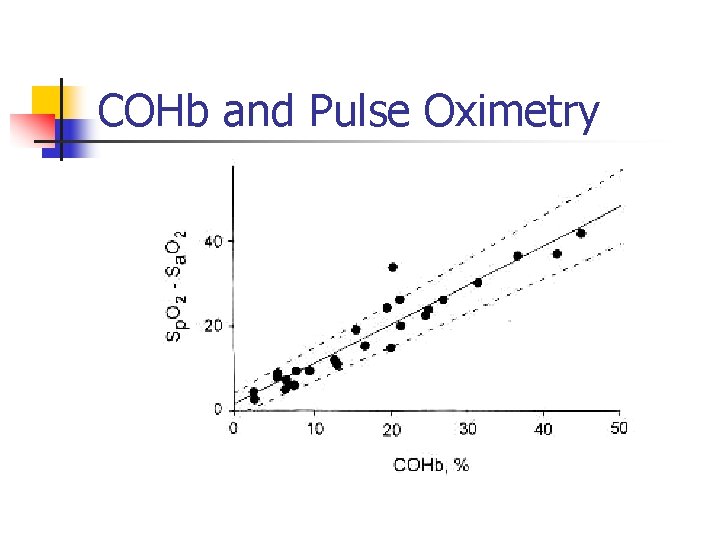
This is the most common mistake I see when residents or even attending physicians interpret these numbers. A pulse oximeter uses two wavelengths, red and infrared, and assumes only two chromophores are present: oxygenated and deoxygenated hemoglobin. It calculates SpO2 from that assumption. If anything else is absorbing light at those two wavelengths, the reading goes sideways with no warning. Carboxyhemoglobin absorbs light nearly identically to O2Hb at the two pulse ox wavelengths. So a patient with significant CO exposure, maybe 25% COHb, can present with a SpO2 of 95% while their actual functional oxygen-carrying capacity is severely compromised. Co-oximetry catches this because it sees the extra absorbance at the longer wavelengths. Methemoglobin similarly skews pulse ox readings toward 85% regardless of the true saturation. You will see this on midnight calls regularly. I had a case last year where a patient came in from a house fire. Their pulse ox was 96% on room air. The ABG with integrated Co-oximetry showed COHb at 31%, O2Hb at 62%, and metHb at 3%. The pulse ox was completely misleading because it could not distinguish COHb from O2Hb. We started hyperbaric evaluation based on the Co-oximetry result alone. If I had relied on the pulse ox, we would have missed the severity entirely. This happens more often than you would think, especially with smokers whose baseline COHb is already 5 to 10%.
Get the Full Details
Pre-Analytical Issues That Ruin Results Before You Even Start
The sample has to be collected correctly. Arterial blood goes into a heparinized syringe, expel all air bubbles, cap it immediately, and roll it between your palms to mix. Do not let it sit at room temperature. Analyze within thirty minutes, ideally sooner. If you are sending it to a central lab, put it on ice. Glycolysis continues in the sample after collection, which drops pH and raises pCO2 progressively. Every minute counts, and the hemoglobin fractions stay stable, so the Co-oximetry part is less time-sensitive than the gas parameters. Venous samples can be used for Co-oximetry fractions without major issue, since those are concentration-based and not dependent on oxygen tension. You cannot derive pO2 or O2 saturation from a venous sample in the same way, but the COHb and metHb values remain valid. I routinely accept venous draws for the Co-oximetry portion when an arterial stick is not feasible, and I flag the sample clearly so the reporting reflects that limitation. Air bubbles in the syringe will alter pCO2 and pO2 significantly. They do not affect the Co-oximetry fractions because those are ratios of hemoglobin species, not partial pressures. A bubble-heavy sample will give you garbage pH and pCO2 but perfectly fine COHb and metHb. I have seen attendings get confused by this exact scenario and question the entire run. It is not a bad run. The spectrophotometry is independent of the gas measurement.
Interference Patterns You Need to Know About
Lipemia causes light scattering across all wavelengths. The instrument tries to compensate, but severe triglyceride elevation, usually above 400 mg/dL, can depress all hemoglobin fractions slightly and artificially elevate the sum. If your O2Hb plus HHb plus COHb plus metHb adds up to more than 100%, something is interfering. Lipids are the usual suspect. I reject those samples and ask for a non-fasting draw to be repeated, or I note the interference on the report. Dyes are another source of error. Methylene blue, indigo carmine, and even IV contrast at high doses can absorb light in the visible spectrum and throw off the fractions. Methylene blue specifically reduces metHb artificially, giving a falsely low metHb reading while the true value is higher. This is relevant in patients being treated for methemoglobinemia, where you administer methylene blue and then immediately draw blood. Wait at least fifteen minutes after administration before drawing, or interpret the metHb with extreme caution. Bilirubin at very high levels, typically above 20 mg/dL, can interfere with the metHb measurement because bilirubin absorbs light near 579 nm, which overlaps with one of the metHb detection wavelengths. The effect is small but measurable. I cross-reference the bilirubin value from the chemistry panel with the metHb result. If metHb is marginally elevated and the bilirubin is massive, the metHb is likely partially artifact.
Understanding the Numbers When Everything Looks Wrong
The oxygen saturation gap is your fastest diagnostic shortcut. Calculate it by subtracting the pulse ox SpO2 from the Co-oximetry O2Hb percentage. A gap greater than five percentage points signals an abnormal hemoglobin species is present. In a smoker, the gap might be two or three points from a chronically elevated COHb. In a CO poisoning case, the gap can be twenty points or more. In methemoglobinemia, the SpO2 plateaus near 85% while the Co-ox O2Hb reads much lower or higher depending on the true state. Total hemoglobin on a blood gas analyzer is measured spectrophotometrically, usually at a single wavelength after lysing the red cells. It is not the same as the cyanmethemoglobin method used on hematology analyzers. The values can differ by 0.5 to 1.0 g/dL routinely, and the BG measured value tends to run slightly higher. Do not try to reconcile them perfectly. Use the BG total hemoglobin when calculating oxygen content from the blood gas, and use the hematology value for everything else. Mixing them deliberately introduces error into your O2Content calculation.
Limitations Nobody Talks About Enough
Standard Co-oximetry cannot reliably detect sulfhemoglobin. It does not appear as a distinct peak in the absorbance spectrum, and most instruments will simply misallocate it into the metHb fraction or leave it unreported. If a patient has true sulfhemoglobinemia, your metHb will be falsely elevated and there will be no warning label on the report. This is rare but clinically important, and the only way to confirm is send-out spectroscopy or special staining. Hemoglobin variants like HbS, HbC, and HbE have subtly different absorbance spectra. Most modern Co-oximeters account for common variants in their algorithms, but uncommon ones can produce fraction errors. A patient with sickle cell trait or disease will have accurate O2Hb and COHb values typically, but the metHb may drift slightly. The clinical impact is usually negligible unless you are monitoring methemoglobinemia treatment in a hemoglobinopathy patient, in which case you need to know the baseline metHb before starting therapy. Instrument-to-instrument variation is real. Radiometer, Siemens, and Abbott use different wavelength sets and different calibration curves. A COHb of 8% on one platform might read 7% or 9% on another. This matters when you are tracking trends in a CO poisoning patient over hours. Stick to one analyzer for serial measurements if possible, or at least be aware that small shifts between draws on different machines may reflect instrument variability rather than true physiological change.
When to Escalate and When to Repeat
If you get a metHb above 5% in a patient with no history of oxidant drug exposure, no nitrate ingestion, and no congenital condition, repeat the sample before panicking. Specimen artifact from prolonged tourniquet time, venous draw mixed with tissue fluid, or delay in analysis can produce spurious elevations. I repeat any unexpected metHb above 3% in an asymptomatic patient. For COHb above 5% in a non-smoker, repeat immediately and consider true CO exposure until proven otherwise. When the fractions do not add up to approximately 100%, something is wrong with the sample or the measurement. The normal range for the sum is 98 to 102%. Outside that range, check for lipemia, dye contamination, or a bubble artifact in the gas measurement portion. If the sample looks visually normal and there is no known interference, rerun it. Most modern analyzers will flag the sum automatically, but the flag does not tell you what caused it. You have to figure that out.