
What Actually Happens During a Cognitive Assessment For Adhd
A lot of people treat a cognitive assessment as if it's a diagnostic test that will definitively confirm or rule out ADHD. That is not how it works. The assessment measures attention, processing speed, working memory, and executive functioning under controlled conditions. It generates a profile of your cognitive strengths and weaknesses. Whether that profile aligns with ADHD is another conversation entirely. I've sat through dozens of these assessments myself, both as someone who requested one and later as a consultant who helps people interpret results. The most common mistake I see is treating the output as a binary diagnosis tool. It isn't. It's a map of how your brain performs on specific tasks. The map is useful. It is not a verdict.
The Cognitive Assessment For Adhd Process Explained
The standard approach involves a battery of individually administered subtests. The WAIS-IV and WISC-V from Pearson are the most widely used. The CPT-3 and TOVA are continuous performance tests you'll encounter frequently. These are not self-report questionnaires. They're timed tasks where you respond to visual or auditory stimuli, keep numbers in mind while solving problems, cancel specific symbols, and match patterns under pressure. Here's what most guides don't tell you: the environment matters more than you think. I once worked with a client who scored in the average range across the board during his first session. He'd slept five hours, consumed caffeine on an empty stomach, and was anxious because the evaluator was a stranger in a white coat. Second session, after a proper night's sleep and a routine morning dose of prescribed medication, his processing speed composite jumped twelve points. His attention scores improved by roughly eight. The raw data changed because his baseline state changed. This is why retesting at least once, under conditions that reflect your typical functioning, is non-negotiable if you want results that actually reflect you. The typical assessment runs between two and four hours. It's usually split across two visits. Some providers offer shorter versions, but those tend to skip the subtests that reveal the most about executive dysfunction. The ones they cut are often the digit span backward, the coding subtest, and the symbol search. Those three are where ADHD-related patterns most clearly emerge. Skipping them makes the assessment cheaper but also shallower.
Key subtests and what they actually measure: Digit Span (forward, backward, sequencing) tests working memory capacity and mental flexibility. A person with ADHD might perform adequately on forward digit span but crumble on backward. That gap between subtests is more informative than any single score. Coding and Symbol Search measure processing speed under time pressure. These are where fatigue and distractibility show up fastest. People with ADHD often score significantly lower here than on verbal comprehension, and the discrepancy itself carries diagnostic weight.
Get the Full Details

Block Design and Matrix Reasoning assess visual-spatial reasoning and fluid intelligence. These are generally less affected by attentional issues, which makes them useful as a baseline for comparing against the processing speed scores.
Where Standard Assessments Fall Short
I need to be straightforward about the limitations because most providers won't highlight them. Standard cognitive assessments have real blind spots when it comes to ADHD, particularly the inattentive presentation. The biggest issue is that these tests measure performance in a highly structured, low-distraction environment. ADHD brains often perform quite differently in natural settings where distractions are constant and self-regulation has to be sustained over hours rather than minutes. A person can score within the average range on a two-hour assessment and still struggle profoundly to finish a workday. This is why ecological validity is such a persistent problem. Another limitation is the Medication Effect. Stimulant medications can normalize certain scores temporarily. If you take medication before testing, the assessment may underrepresent your actual difficulties in unmedicated states. I recommend bringing your medication history to the session and asking the evaluator to note whether scores were obtained medicated or unmedicated. Ideally, you get assessed in both states. Not every provider offers this, and insurance rarely covers it, but it's the only way to get a complete picture.
There's also the anxiety factor. Many people with ADHD develop significant test anxiety from years of performing below their actual capability in structured settings. Anxiety inflates effort inconsistency, which can produce irregular response patterns that look like inattention but are actually performance artifacts. I've seen this repeatedly. The workaround is straightforward: build in breaks, allow short movement periods between subtests, and explicitly tell the evaluator about your anxiety. A good examiner will adjust pacing accordingly. A rushed one will record the scores and move on regardless.
What the Results Actually Mean
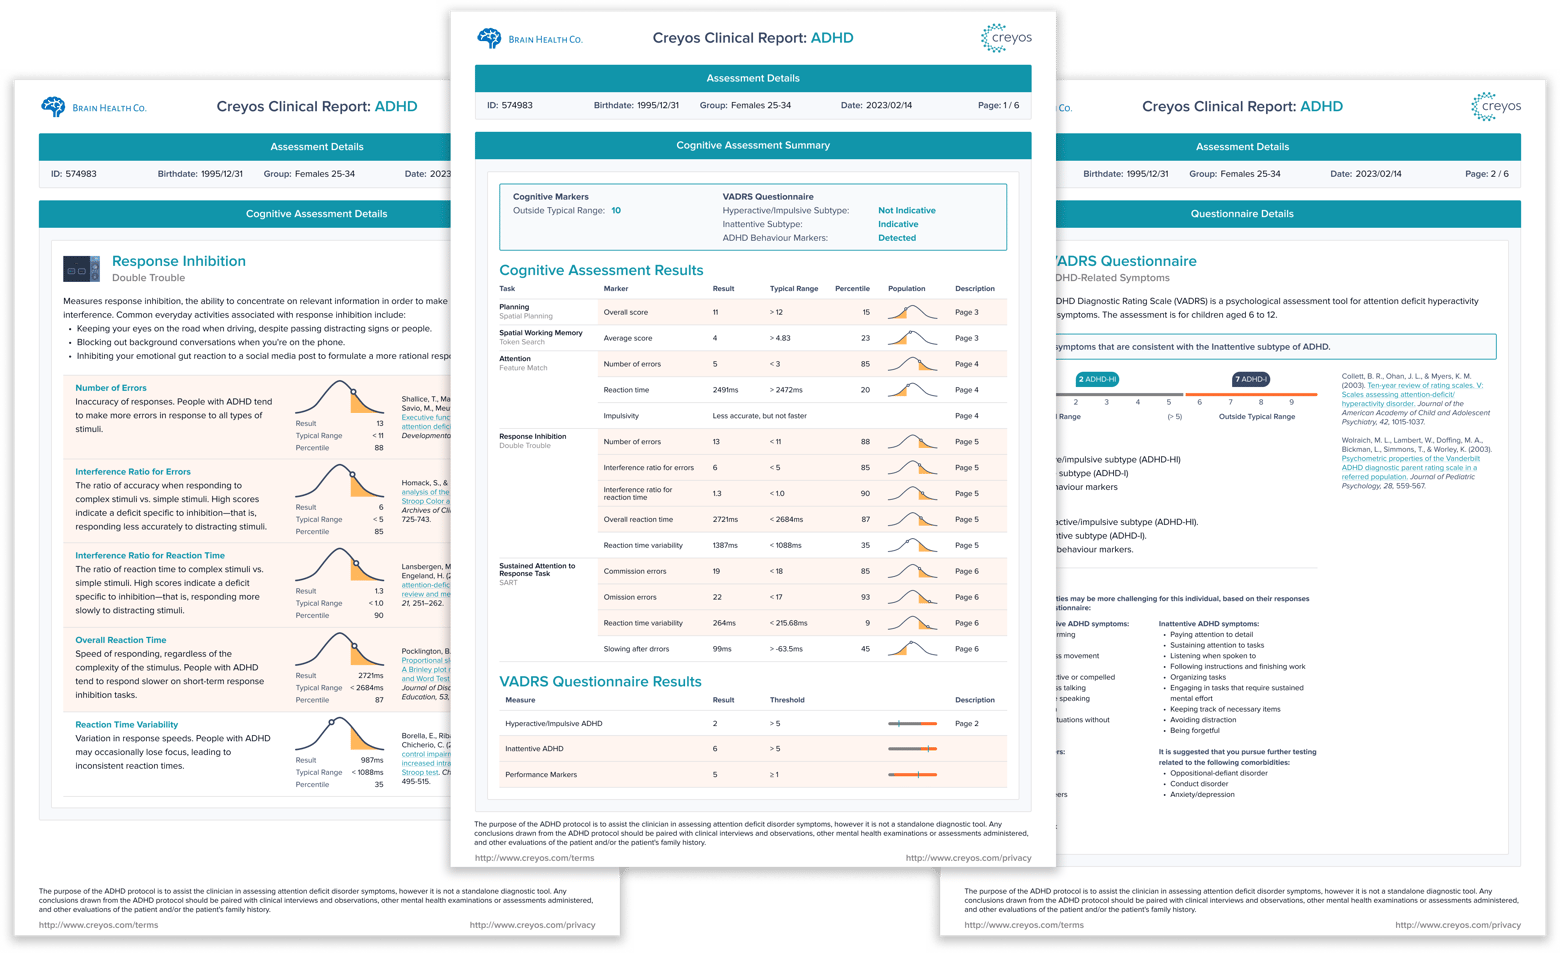
Your report will come with scaled scores, index composites, and percentile ranks. Scaled scores range from 1 to 19 with a mean of 10. Index composites cluster multiple subtests into categories like Processing Speed Index or Working Memory Index. Percentile ranks tell you how you performed relative to the normative sample for your age group. A percentile rank of 50 means you scored higher than 50% of people in the same age group. A rank of 14 is considered below average. A rank above 91 is above average. The clinical cutoffs typically used are: average (25th to 75th percentile), low average (16th to 24th), borderline (9th to 15th), and extremely low (below 9th). What clinicians look for is not a single low score but a pattern. A significant discrepancy between your verbal comprehension and processing speed, for example, is one of the more reliable indicators. Research consistently shows this pattern appears in approximately 70 to 80 percent of adults with ADHD. But the remaining 20 to 30 percent do not show it, which is why this assessment alone can never confirm a diagnosis.
Here's something most people don't understand about the data: IQ estimates derived from cognitive assessments are often inflated in people with ADHD who have learned compensatory strategies. If you've spent years developing verbal reasoning skills as a workaround for working memory deficits, your verbal comprehension score will reflect that adaptation. Your full-scale IQ may appear solid while your working memory index tells a different story. The discrepancy between the two is where the clinically relevant information lives.
How to Prepare Without Sabotaging Your Results
Do not try to game the assessment. I've seen people practice cognitive training apps for weeks before testing, hoping to boost their scores. This produces inflated results that don't reflect your typical functioning and will mislead anyone using the assessment for accommodation purposes. The point of the assessment is to measure how your brain actually works, not how it performs at its best. What you should do is ensure your baseline conditions are optimized. Sleep eight hours the night before. Take any prescribed medication at your usual time. Eat a normal meal before arriving. Arrive ten minutes early so you're not rushed. Bring a list of your current medications and any relevant medical history. These steps prevent avoidable variability in your scores. If you're being assessed for workplace or academic accommodations, bring documentation of your current challenges. Accommodation reviewers care more about functional impairment than raw scores. A person with average-range processing speed who reports severe difficulties completing tasks on time carries more weight than someone with clinically low scores but no reported functional impact.

The assessment itself is not a diagnostic endpoint. It is one data point among many. A comprehensive ADHD evaluation includes clinical interviews, symptom checklists completed by multiple informants, review of developmental history, and ruling out of alternative explanations like anxiety disorders, sleep apnea, thyroid dysfunction, and learning disabilities. If a provider offers only a computerized assessment and calls it a diagnosis, that is not a thorough evaluation regardless of how polished the report looks.
Obtaining Your Results and Using Them
You have a legal right to your assessment results. Under HIPAA in the United States, you can request a copy of the full report including raw scores and stimulus books. Some providers will give you a summary rather than the complete document. Push back on this. The summary is written for other professionals. The full report with percentiles, standard scores, and subtest breakdowns is what you need to understand what the numbers actually mean. When you receive the report, focus on the index composites first. These aggregate scores give you the broadest picture. Then look at the subtest scatter within each index. High variability within a single index often signals attentional inconsistency rather than a genuine ability deficit. A person with a working memory index of 95 whose digit span forward scores 12 and digit span backward scores 7 is showing the kind of pattern that suggests attentional regulation problems more than a general working memory weakness. If you're using the assessment for accommodations, make sure the report explicitly connects the cognitive findings to functional limitations. Vague statements about "areas of difficulty" are insufficient for disability services offices and HR departments. They need specific language linking your scores to real-world impact. This is worth discussing with your evaluator before the report is finalized rather than trying to fix gaps afterward.
Some newer tools are entering the space, like the QbTest and the BrainCheck platform, which combine computerized attention testing with motion tracking. These can supplement traditional assessments but should not replace them. They measure different things and have different limitations. The gold standard remains the individually administered WAIS or WISC with a qualified psychologist interpreting the results in context. The bottom line is that a Cognitive Assessment For Adhd is a useful but imperfect instrument. It reveals patterns. It does not deliver answers on its own. The quality of the assessment depends heavily on who administers it, how they interpret the data, and whether they account for the variables that make ADHD testing notoriously tricky. Choose your provider carefully and go in with realistic expectations about what the numbers can and cannot tell you.


