What CBT Actually Looks Like on the AP Exam
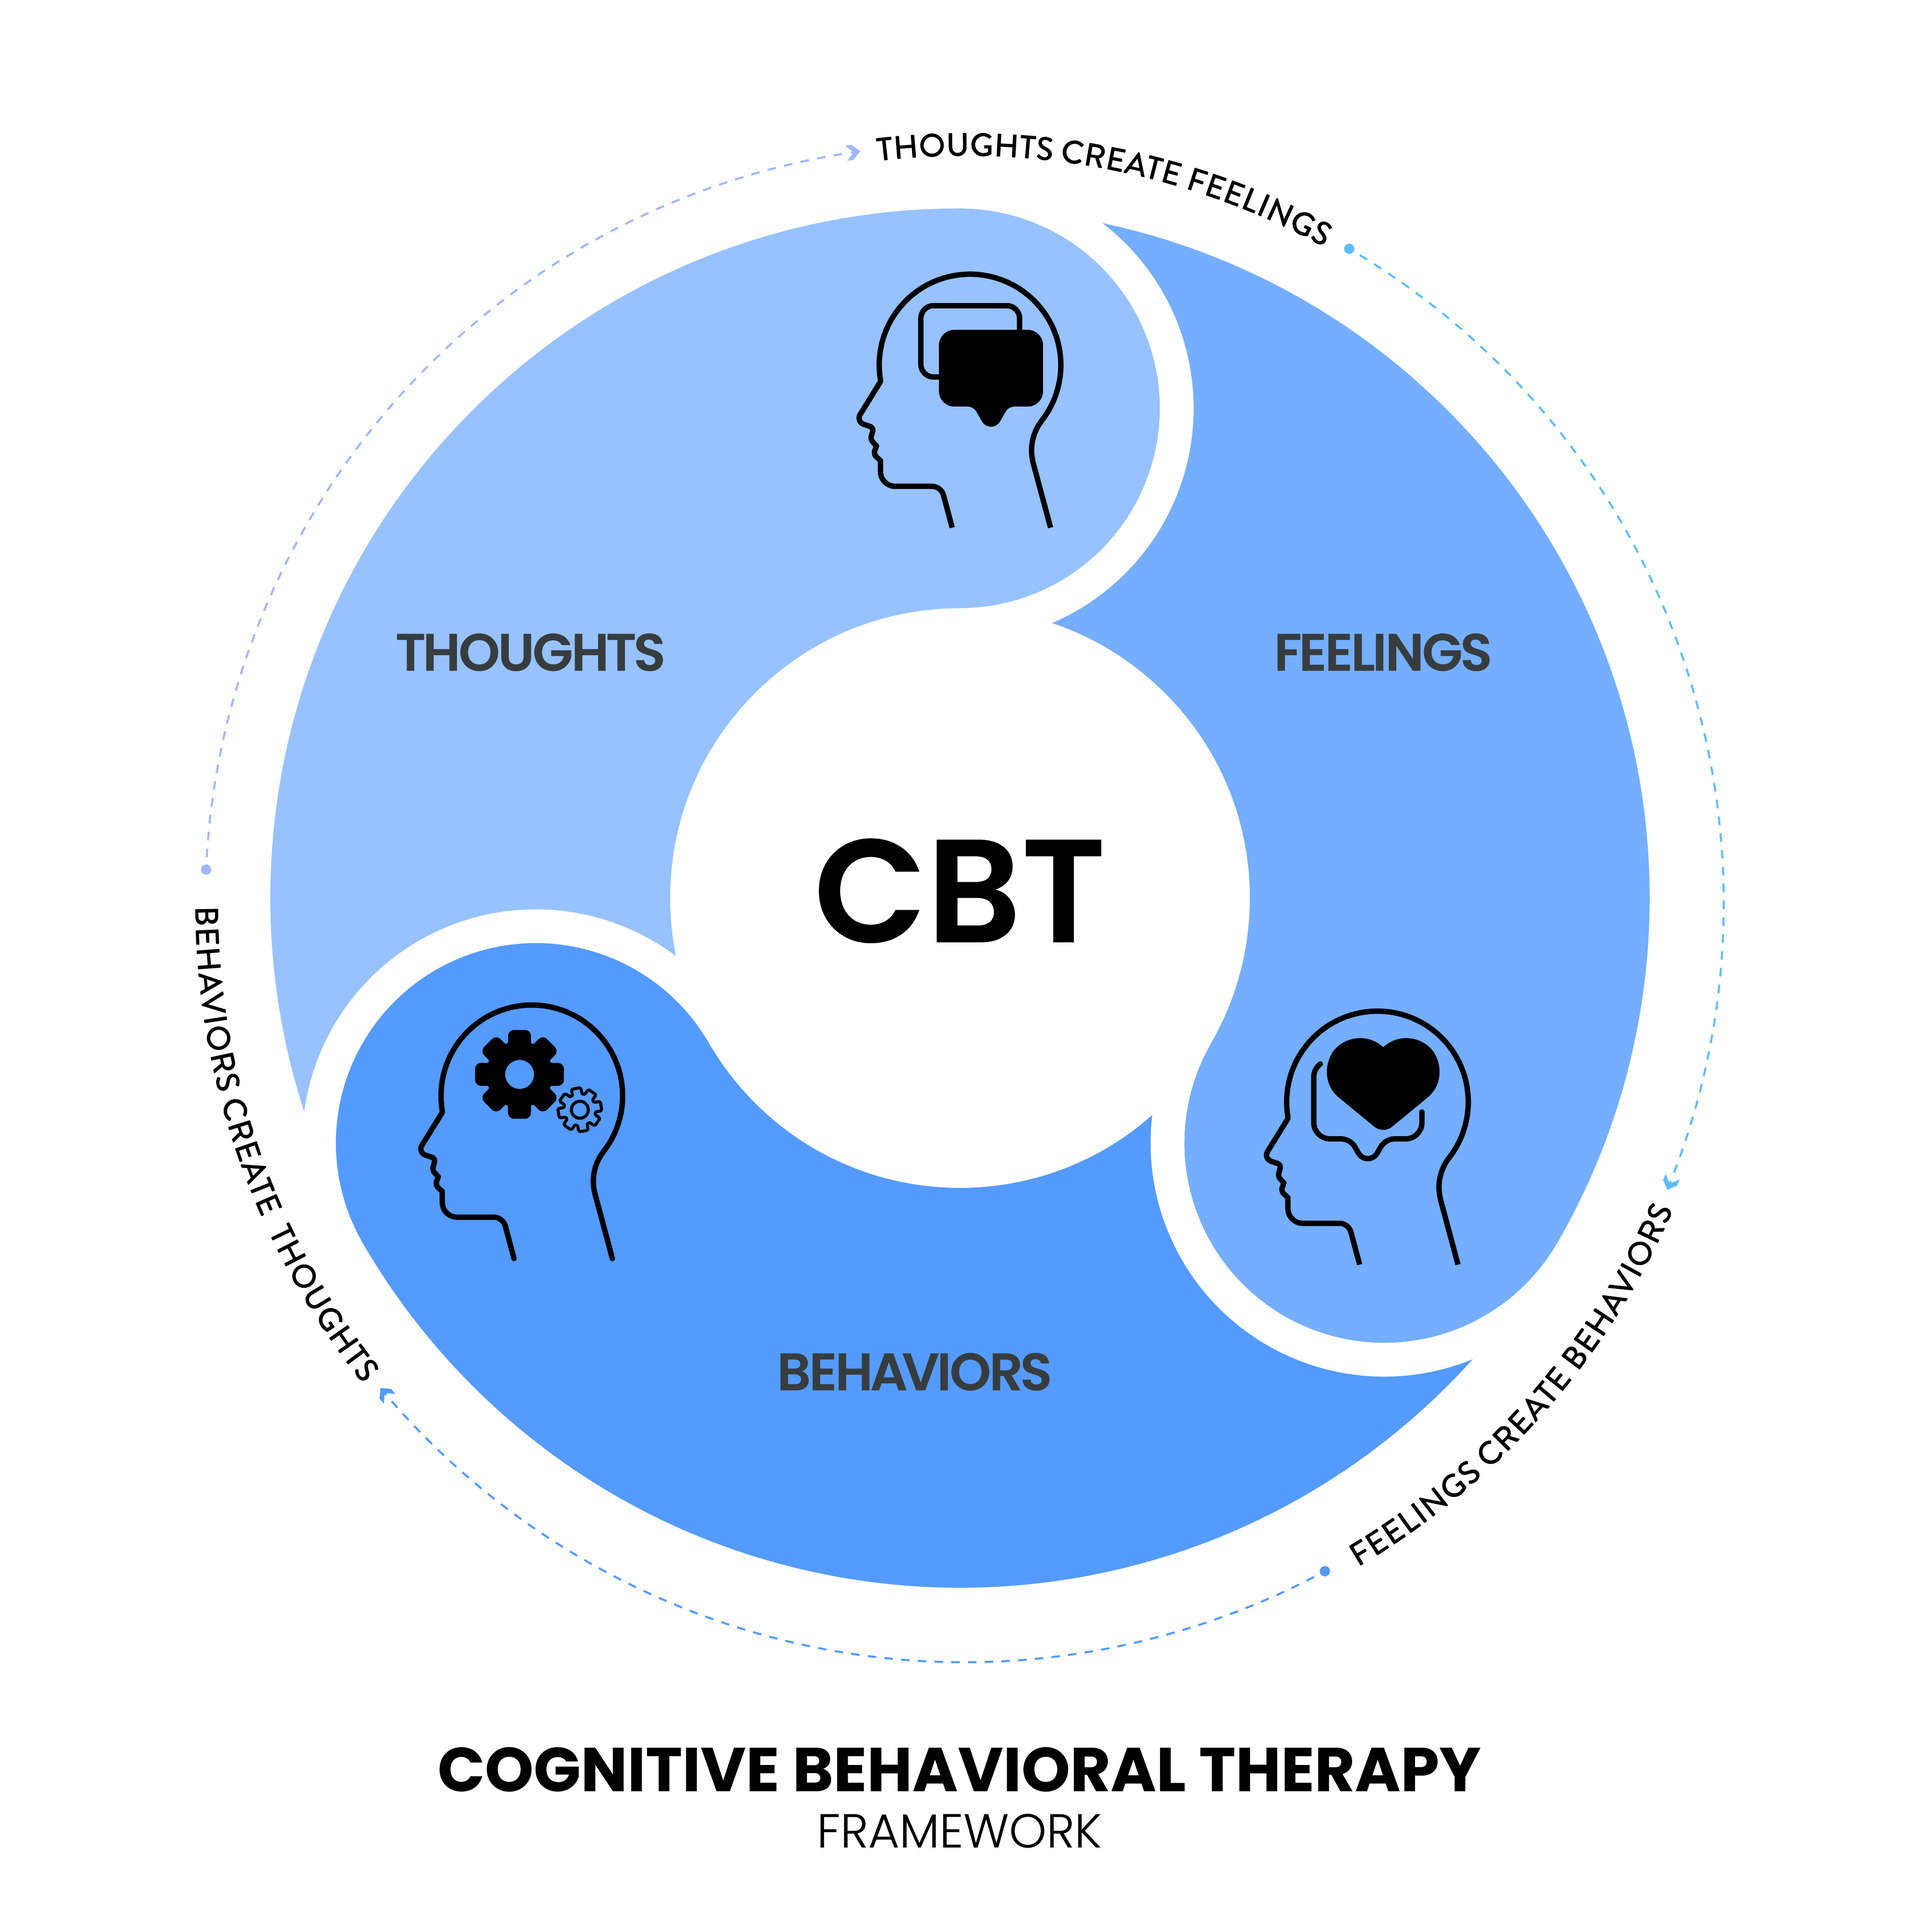
Most students treat CBT like another term to memorize from a list. It is more practical than that. When you understand how the therapy works, you can answer application questions even if you have never seen them before. The AP Psych exam loves scenario-based items, so knowing the mechanics matters more than the definition. CBT combines two approaches. The cognitive piece targets the thoughts people have. The behavioral piece targets what they actually do. Together, the therapist helps the client identify distorted thinking patterns and then replace them with more realistic interpretations while also changing behaviors that reinforce those thoughts. Depression and anxiety are the two most common targets. Phobias, OCD, and eating disorders respond to it as well. Here is the part textbooks do not stress enough. CBT is structured and time-limited by design. Sessions follow an agenda. The therapist assigns homework between meetings. It is not free association or exploring childhood trauma the way psychodynamic therapy does. That distinction shows up constantly on the exam in questions asking you to identify the therapeutic approach based on the description.
I remember grading practice exams where a student selected psychodynamic therapy for a passage that explicitly mentioned "challenging irrational beliefs." The client was asked to track their negative automatic thoughts and test whether those thoughts held up under evidence. That is pure CBT. Students miss that because they latch onto keywords like "understanding" or "insight" and assume depth therapy. The trick is to look at the mechanism, not the goal. Insight is the outcome in many therapies. The specific mechanism in CBT is identifying and restructuring cognition through behavioral experiments. The core technique is called cognitive restructuring. You take a distorted thought, label the type of distortion, and then generate a balanced alternative. Common distortions the AP course covers include catastrophizing, all-or-nothing thinking, overgeneralization, and mind reading. When a question describes someone who believes "one failure means I will always fail," the answer involves overgeneralization. The therapist would have the client examine actual evidence from their life that contradicts that absolute statement. Behavioral activation is the other half. Depression often leads to withdrawal. Withdrawal reinforces the depression. The therapist interrupts that cycle by scheduling rewarding activities even before the client feels motivated. It sounds backwards, but the data supports it. Motivation follows action in depression, not the other way around.
Exposure therapy falls under the behavioral umbrella within CBT. Systematic desensitization pairs gradual exposure with relaxation techniques. It is frequently tested when a scenario involves a phobia. A student might see a passage about someone afraid of elevators and the treatment described involves creating a fear hierarchy. The answer is systematic desensitization, not flooding, because flooding involves immediate full exposure without the gradual steps. Here is a counter-intuitive point most students skip. CBT does not require the client to believe the new thoughts immediately. The therapist is testing hypotheses, not selling positive thinking. The language matters. Instead of saying "you should think positively," a CBT therapist says "let us test whether this thought is accurate." That framing reduces resistance and keeps the client engaged. On the exam, any option that sounds like the therapist is giving advice or moralizing is wrong. CBT therapists are collaborative empiricists, not life coaches. Another frequent pitfall involves confusing CBT with behavior modification. Behavior modification relies primarily on reinforcement and punishment without addressing cognition. If a passage mentions token economies, contingency management, or operant conditioning principles alone, that is behavior modification, not CBT. The cognitive component is what separates them. Look for the thought record, the Socratic questioning, or the emphasis on appraisal.
Get the Full Details

Effectiveness is well-established but has limits. CBT works best for depression, anxiety disorders, and phobias. It is less effective for personality disorders without significant adaptation, and it is not appropriate during acute psychosis when reality testing is compromised. In those cases, medication management and supportive therapy come first. The exam sometimes includes a scenario where a client is experiencing hallucinations or severe dissociation, and CBT would be the wrong answer. Recognition of contraindications is a higher-level skill that separates students who score above a three from those who do not. If you are studying for the exam, work through at least ten scenario-based questions that ask you to identify the therapy type. Write out why each wrong answer is wrong. That habit forces you to distinguish between similar approaches like humanistic therapy, which emphasizes unconditional positive regard and empathy, versus CBT, which emphasizes skill-building and cognitive change. Both are present-focused. Both are active. The difference is structural and technique-driven. Remember that the AP exam rarely asks for a definition in isolation. It wraps everything in a vignette. A typical question might describe a therapist who has a client keep a thought diary, challenge evidence for negative predictions, and gradually approach avoided situations. All of that points to CBT. If the same passage mentioned the therapist reflecting feelings and providing a nonjudgmental space without challenging thoughts, the answer shifts to person-centered therapy. The content of the therapist's interventions determines the category, not the therapist's attitude.
For your own review, focus on linking each therapy to its founder when possible. CBT traces back to Aaron Beck for the cognitive side and Albert Ellis for the rational emotive behavior therapy variant. Knowing those names can help eliminate distractors. Beck developed the cognitive model of depression with its focus on the negative triad: negative views of the self, the world, and the future. Ellis focused more on demandingness and musturbation language, though the AP exam usually just calls it rational emotive behavior therapy. The real-world application outside the test is straightforward but not simple. CBT requires effort from the client between sessions. Homework completion predicts outcomes. A therapist can be skilled, but if the client does not practice cognitive restructuring outside of sessions, progress stalls. This is also why it is not a quick fix, despite being shorter-term than other approaches. Twelve to twenty sessions is typical for uncomplicated depression, though some protocols run longer. When you see a question about CBT on the exam, pause and map the passage onto three things: What cognition is being targeted? What behavior is being changed? Is there a structured homework component? If all three are present, you are likely looking at CBT. If only behavior is mentioned without any cognitive element, it is behavior therapy. If only insight or emotion is mentioned without restructuring or behavioral change, it is likely a different modality entirely.
One last practical note. Some older AP resources still conflate CBT and Rational Emotive Behavior Therapy as separate answers when they are closely related. The College Board treats them as distinct on the exam, but they share the same theoretical foundation. If a question offers both CBT and REBT as options for the same scenario, look for language about irrational beliefs and the ABC model. That points to REBT. General cognitive restructuring without that specific points to CBT.