.jpg)
The actual mechanics of cognitive restructuring
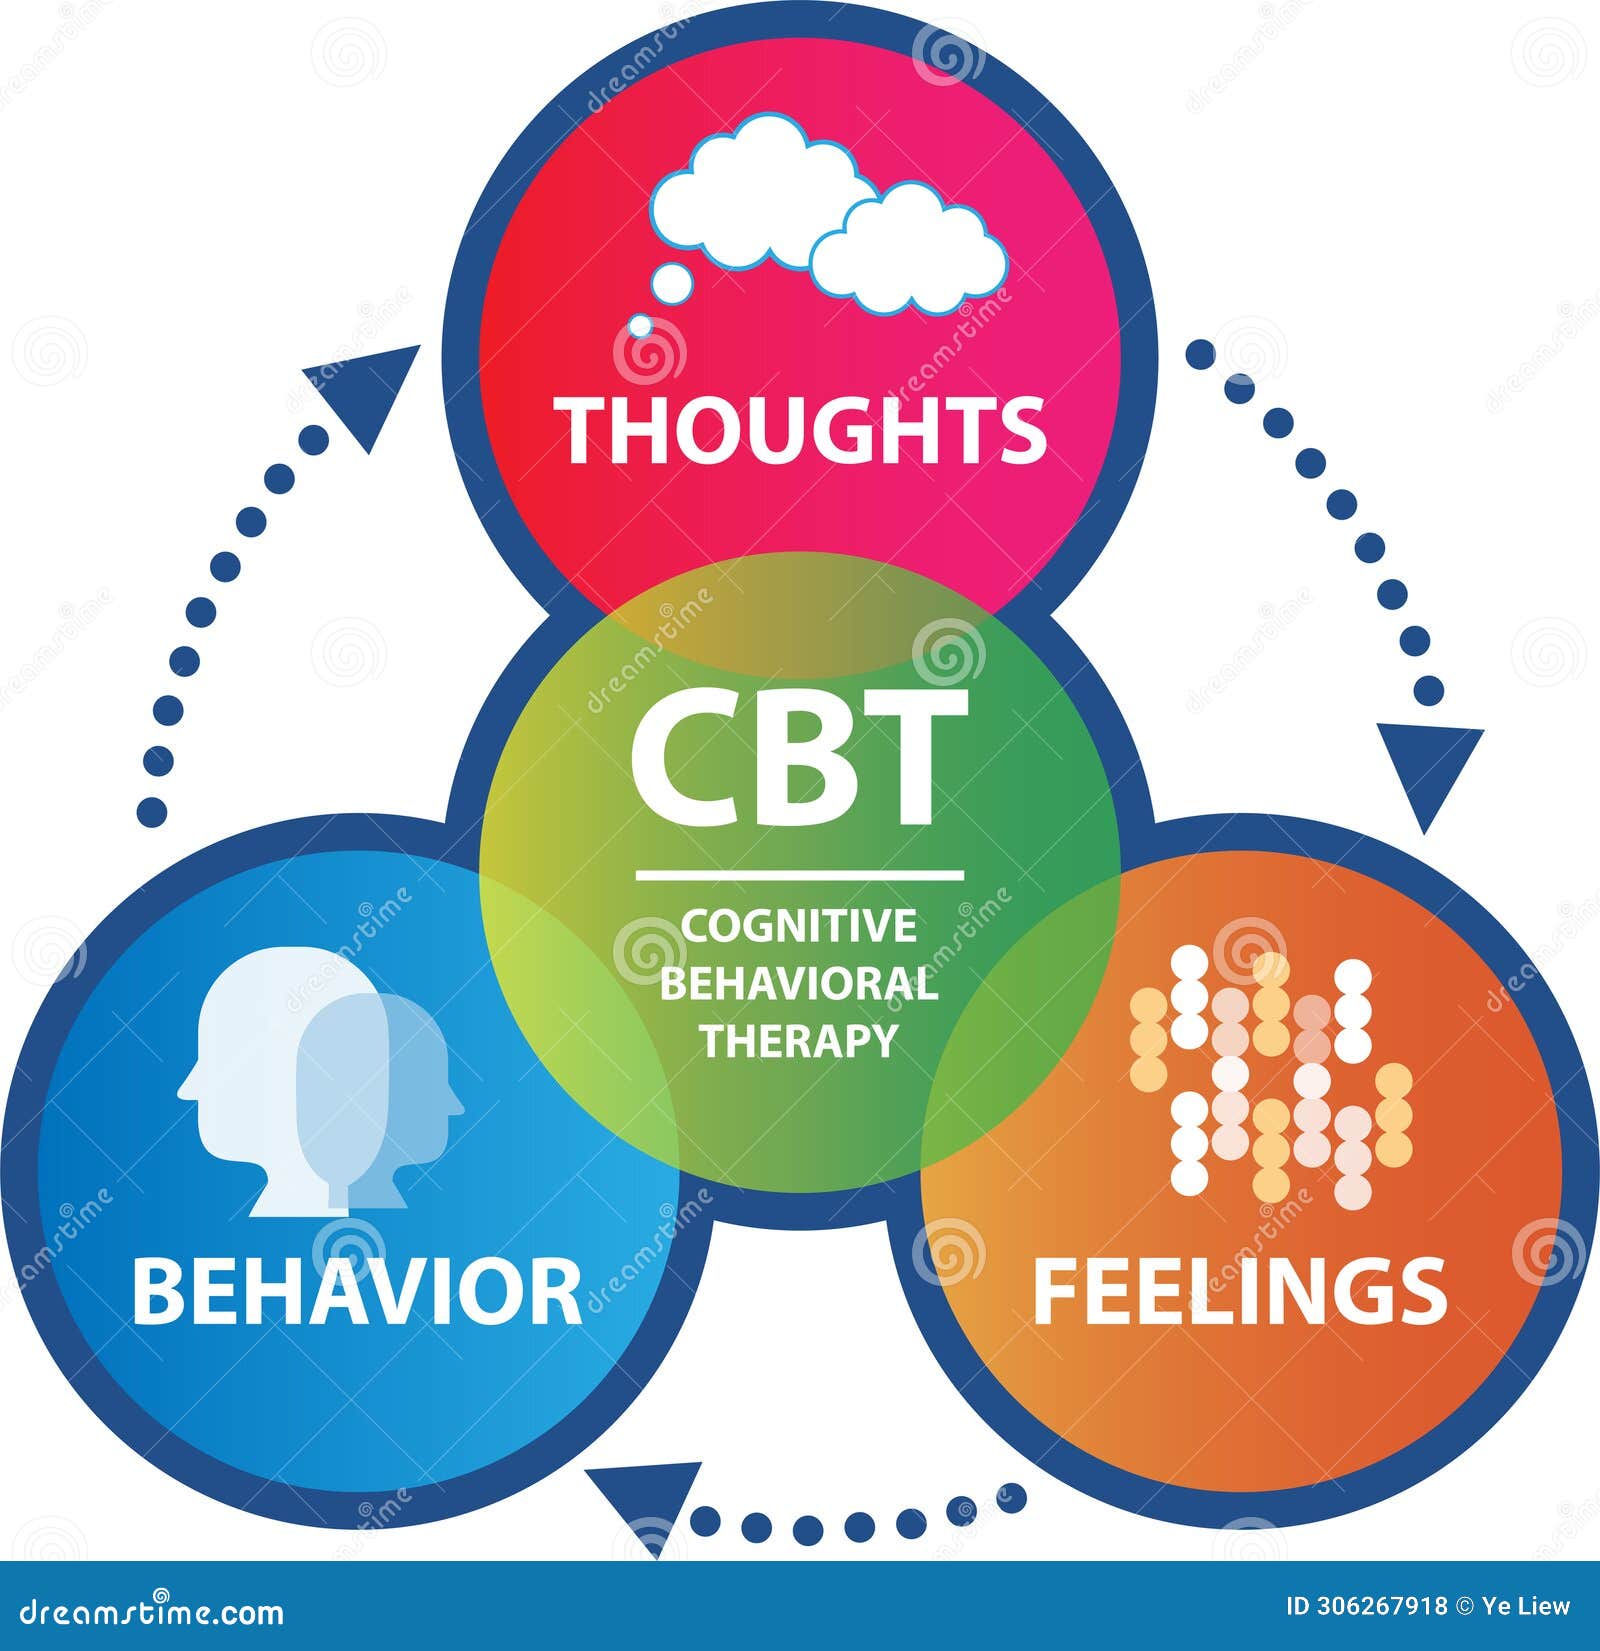
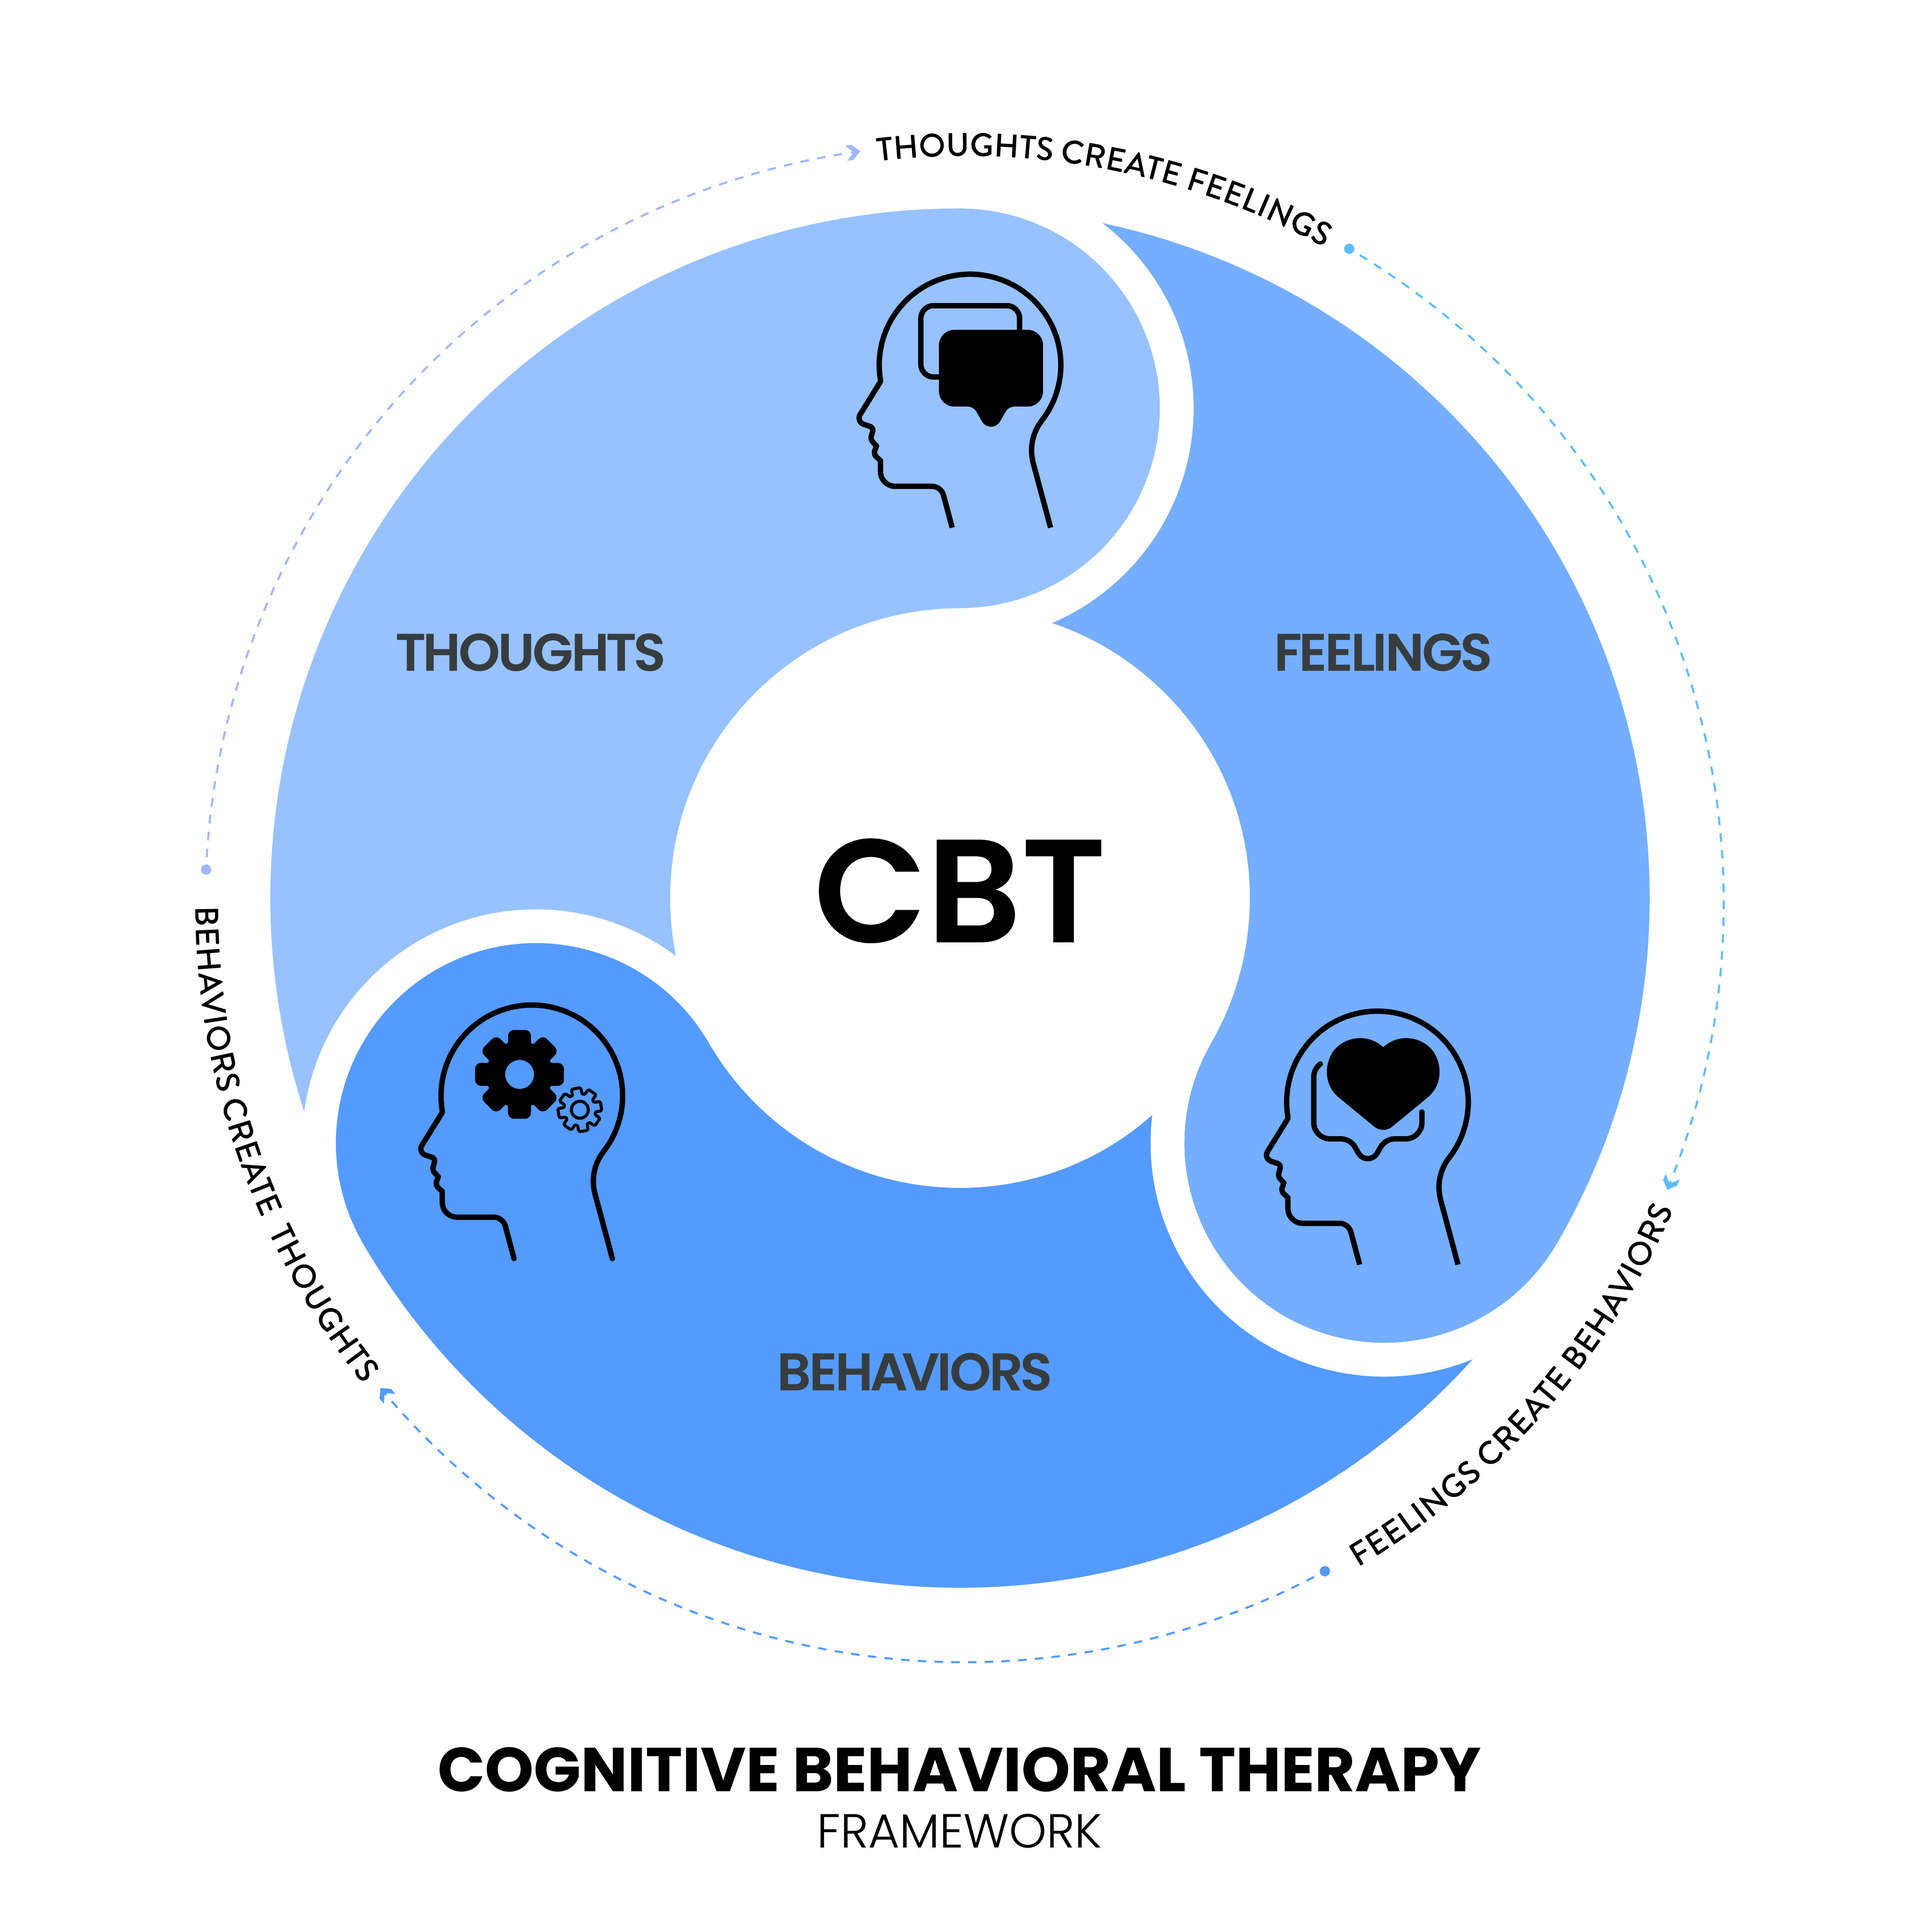
CBT is not just identifying negative thoughts and replacing them. The mechanism is more specific than most people describe it. When a patient presents with panic attacks, for example, the automatic thought isn't always obvious. I've sat across from people who genuinely believed they were having heart attacks, and the cognitive distortion wasn't about "negative thinking" in the generic sense. It was catastrophic misinterpretation of bodily sensations. The work involves teaching the person to separate the physical symptom from the narrative they attach to it. That's where the actual change happens. Not in debating the thought. In building tolerance for uncertainty while the nervous system recalibrates. The standard ten-session protocol usually follows a particular shape. Sessions one through three are assessment and psychoeducation. You spend time mapping the problem, establishing the cognitive model, and introducing the concept of thought records. Sessions four through seven move into active skill-building. This is where behavioral activation, cognitive restructuring, and exposure work happen simultaneously. Sessions eight through ten focus on consolidation and relapse prevention. Most people think the change happens during the middle sessions. It doesn't. The consolidation period is where the skills actually become available under stress. That's the difference between knowing a technique in session and using it when your cortisol spikes at 2pm on a Tuesday.Cognitive Behavioural Therapy In Mental Health Care
The reason CBT dominates mental health care in most public and private systems isn't because it's the best therapy for every condition. It's because it's the most tractable one to train, supervise, and measure outcomes for. That's an institutional reality, not a clinical endorsement. What actually makes CBT difficult in practice is that the homework component is where most treatment failures accumulate. A patient can do excellent work in session and still not improve because they're not completing thought records or exposure exercises outside of it. The research shows a strong correlation between homework completion and outcome. But no one talks about how much of that "homework" is actually just the patient feeling guilty about not doing it, which becomes another cognitive distortion feeding the problem. I once worked with a client who had severe health anxiety and spent forty-five minutes each day filling out thought records perfectly. Technique-wise, she had it down. She could identify cognitive distortions, generate balanced alternatives, rate her belief in the original thought before and after. She was doing everything right. She also wasn't improving. The issue was that the thought record had become a ritual, not a tool. She was using it to gain certainty about her health, which is the exact thing health anxiety resists. The workaround was to stop the thought records entirely and replace them with response prevention. When she caught herself filling one out, she had to close the notebook and do something else for thirty minutes instead. The anxiety peaked higher than it ever had before. Then it dropped faster. That's the part that always surprises people coming into this field. Sometimes the intervention is removing the intervention.
Where the common approaches break down
Most training programs teach cognitive restructuring as a three-step process: identify the automatic thought, examine the evidence, generate an alternative. This works for mild to moderate depression and anxiety. It falls apart in several scenarios that aren't discussed enough. The first problem is what I call "intellectual insight without emotional shift." A patient can articulate a balanced thought perfectly and still feel exactly the same. This happens when the therapist treats the thought record as a logical exercise. The patient isn't trying to convince themselves rationally. They're trying to reduce distress. The pathway from cognition to emotion isn't through reasoning. It's through experiential learning. Behavioral experiments produce stronger emotional change than cognitive restructuring alone because they create new data the brain has to process. When someone with social anxiety speaks up in a meeting and nobody reacts negatively, that experience rewires something that three pages of a thought record never will. The second problem is the assumption that all patients can access their automatic thoughts. Patients with higher functioning autism, chronic trauma histories, or certain personality structures often report difficulty identifying thoughts in the moment. They describe their experience somatically or emotionally without a clear cognitive layer. Forcing these patients through standard thought record protocols usually results in frustration and dropout. A modification that works better is starting with body sensations and emotions first, then tracing backward to any thoughts that accompanied them. This reverses the standard sequence and respects the patient's actual experience rather than imposing a model that doesn't fit.
Another issue that comes up frequently is comorbid substance use. CBT protocols were largely developed and tested on patients without active substance dependence. When someone is using alcohol or opioids to self-medicate anxiety or depression, the cognitive distortions and the substance use are functionally linked. Treating the thoughts without addressing the substance use pattern usually fails. The substance becomes the coping mechanism that prevents the CBT work from taking hold. The evidence supports integrated treatment models in these cases, not sequential ones.
Get the Full Details
The protocols that actually get used
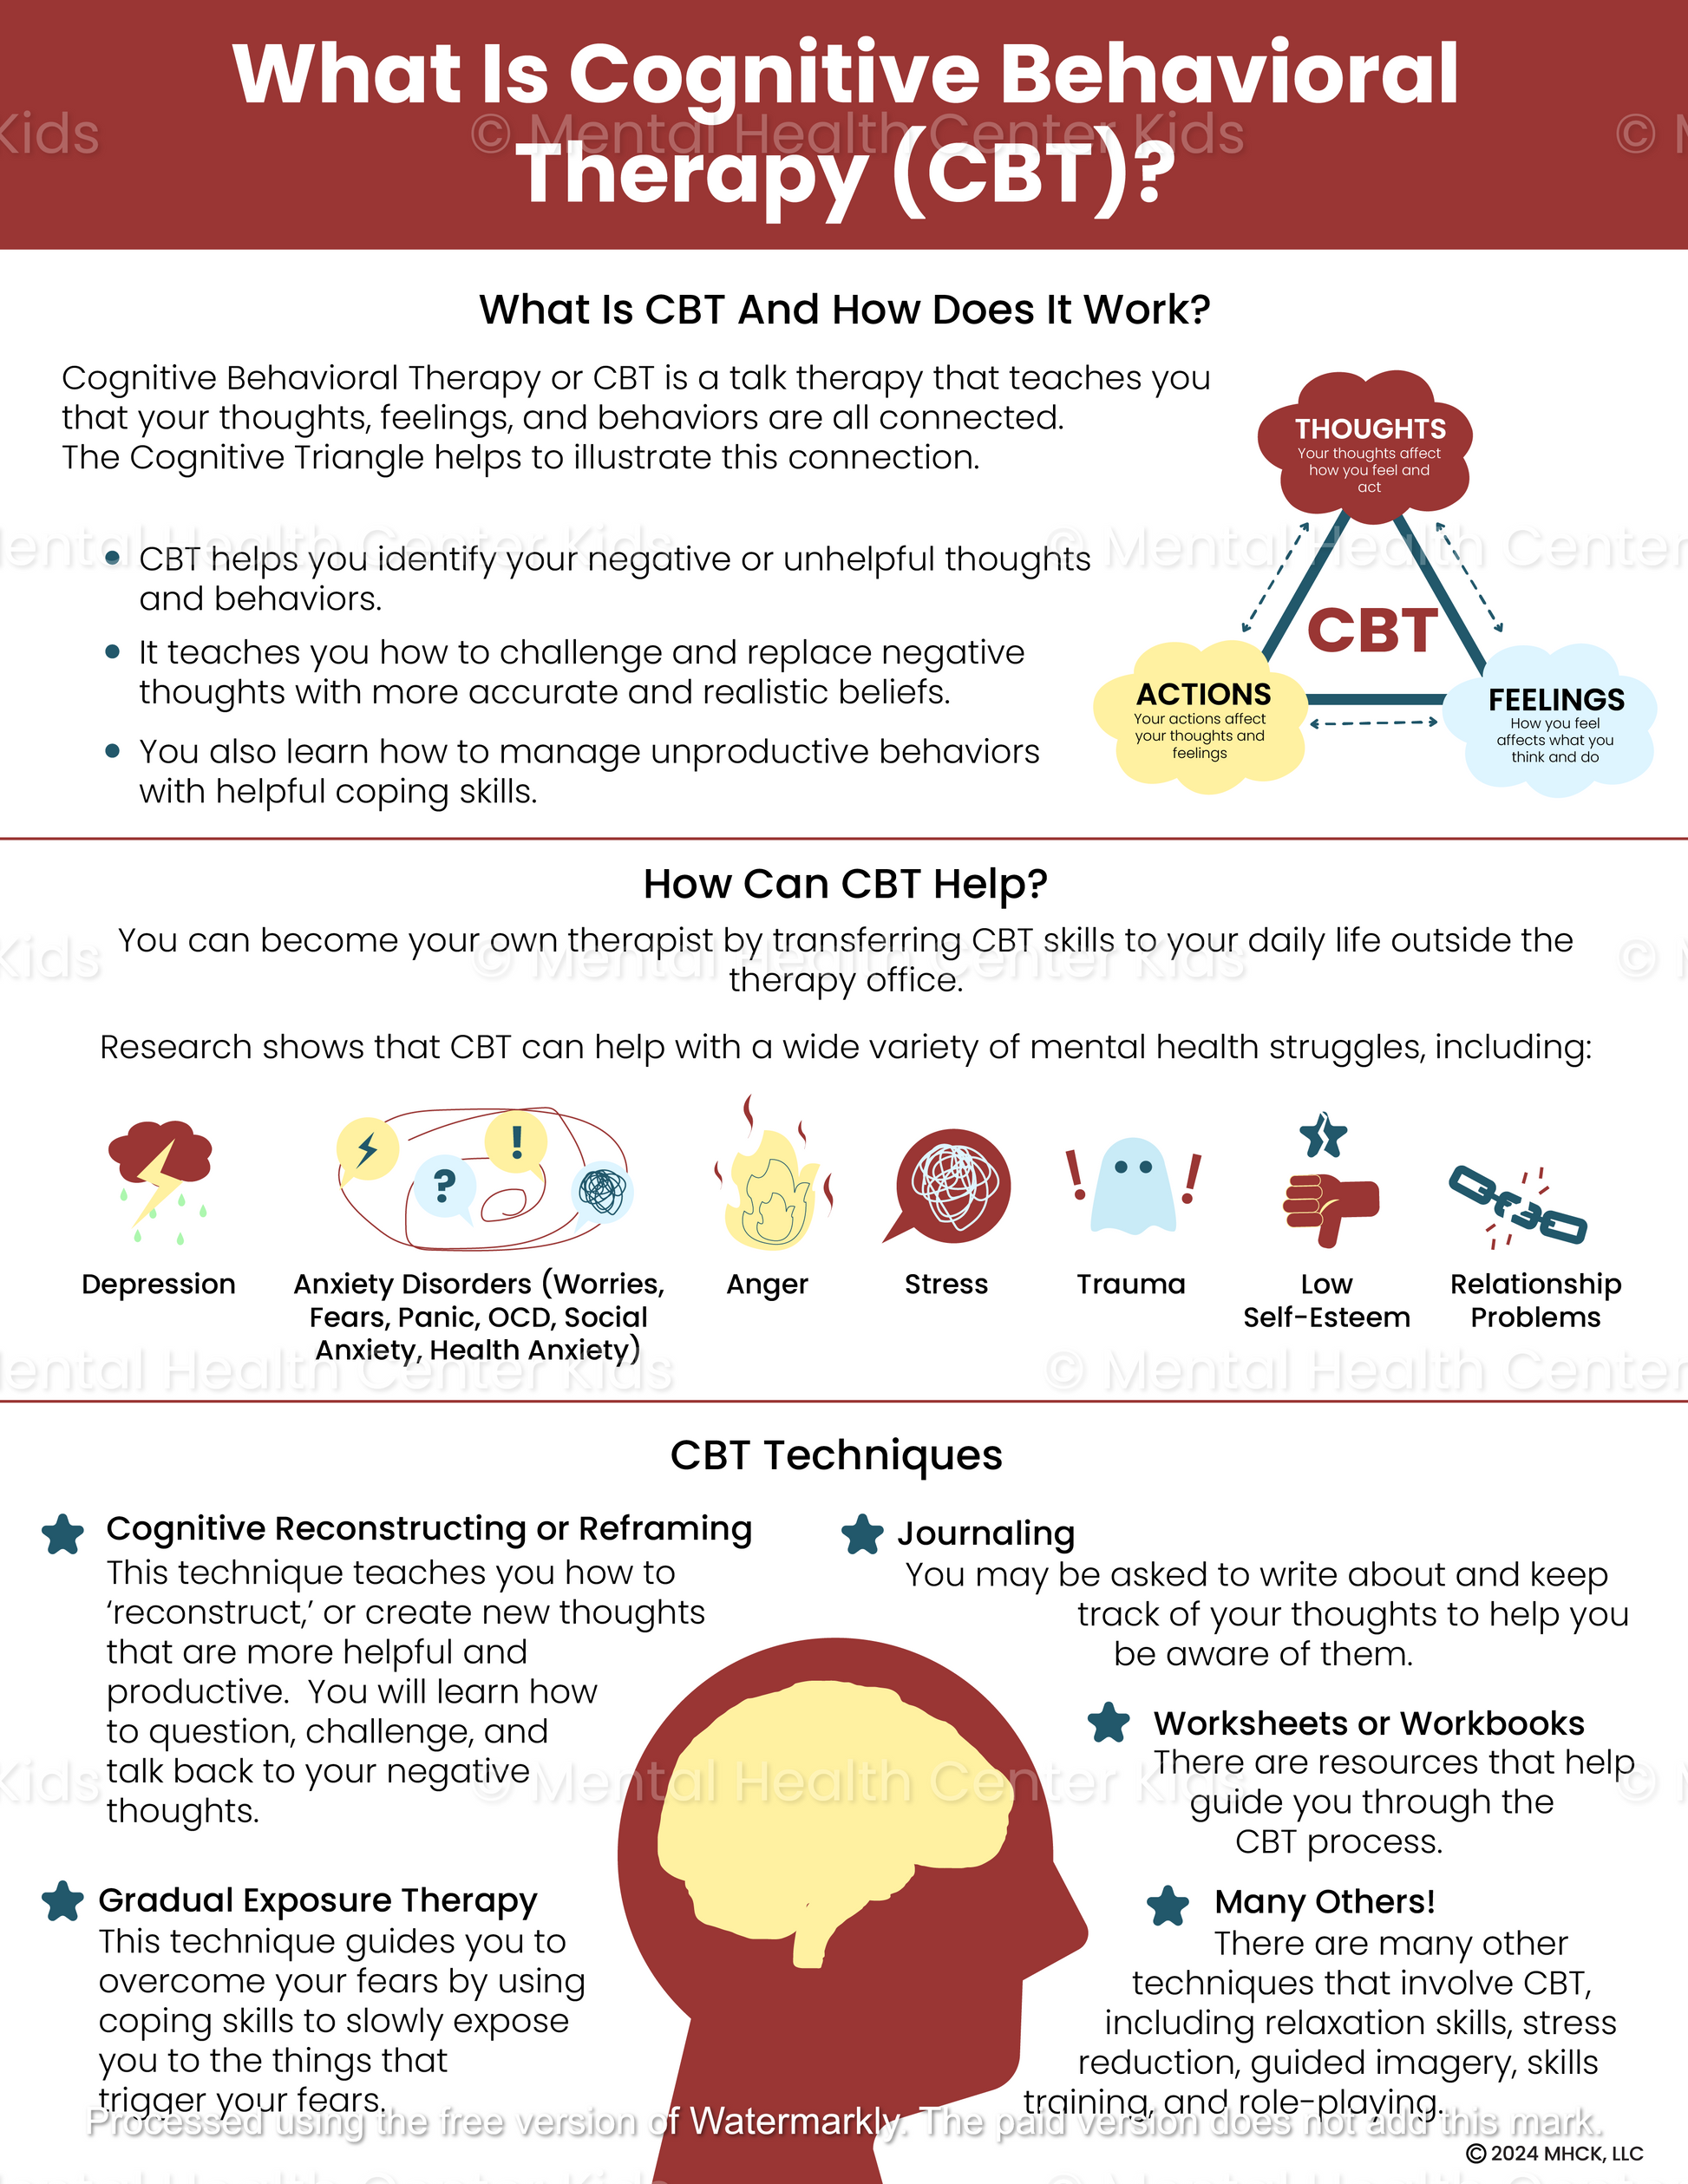
Let me walk through what a typical CBT session structure looks like in a busy clinic setting where you're seeing multiple patients per day and don't have the luxury of spending an hour on each one. Every session starts with a brief check-in and agenda setting. This takes five to ten minutes. You ask about the week since last session, review any worksheets, and collaboratively set the focus for today. Skipping this step is one of the most common mistakes new therapists make. Without an agenda, sessions drift into open-ended exploration, which feels therapeutic but produces weaker outcomes in CBT frameworks. The agenda keeps the session structured and ensures you're actually working on the treatment plan rather than whatever is loudest that day. The main intervention block runs for thirty to forty minutes. This is where you pick between cognitive restructuring, behavioral activation, or exposure work depending on the presenting problem and where the patient is in treatment. Cognitive restructuring involves reviewing a specific situation, identifying the automatic thought, examining cognitive distortions, and developing a balanced response. Behavioral activation targets depression by scheduling rewarding and mastery activities that counteract withdrawal and avoidance. Exposure work targets anxiety disorders by systematically confronting feared situations or internal sensations while preventing the usual safety behaviors.
The session ends with a summary and homework assignment. Five to ten minutes. You review what was accomplished, assign a specific worksheet or behavioral task for the week, and identify any barriers to completion. This closing is critical. It's easy to skip because the middle of the session is more interesting and the time runs short. But the summary and homework assignment are what translate session content into lasting change. Without it, the patient leaves with insights that fade within hours. A specific detail that matters more than most people realize is how you assign homework. Saying "try to complete the thought record" is ineffective. The assignment needs to be specific enough that the patient knows exactly what to do and when. "Write down one automatic thought from today between 3pm and 5pm using the three-column format we reviewed, then bring it to our next session" is dramatically more effective than the vague version. Concrete assignments increase completion rates significantly.
What the evidence actually says and where it falls short
CBT has the strongest evidence base of any psychotherapy for depression, generalized anxiety disorder, panic disorder, and PTSD. Meta-analyses consistently show moderate to large effect sizes compared to waitlist controls and small to moderate advantages over other active treatments. This is why it's the first-line recommendation in most clinical guidelines worldwide. But the evidence has important caveats that get lost in promotional material. The effect sizes shrink considerably when you look at real-world effectiveness trials rather than randomized controlled trials. RCTs exclude comorbid conditions, medication users, and patients with poor adherence. Real-world clinics treat all of those people. The difference between efficacy and effectiveness is substantial. A study published in the British Journal of Psychiatry found that the real-world effectiveness of CBT for depression was roughly half the effect size shown in RCTs. Another underreported finding is the relapse rate. CBT teaches skills that should theoretically protect against relapse better than medication. But the data is mixed. Some studies show a modest relapse advantage. Others show no significant difference between CBT and medication maintenance in preventing return of symptoms. The skills-based advantage exists in principle. In practice, most patients stop using the skills within months of ending treatment, which erases whatever protective benefit they might have provided.
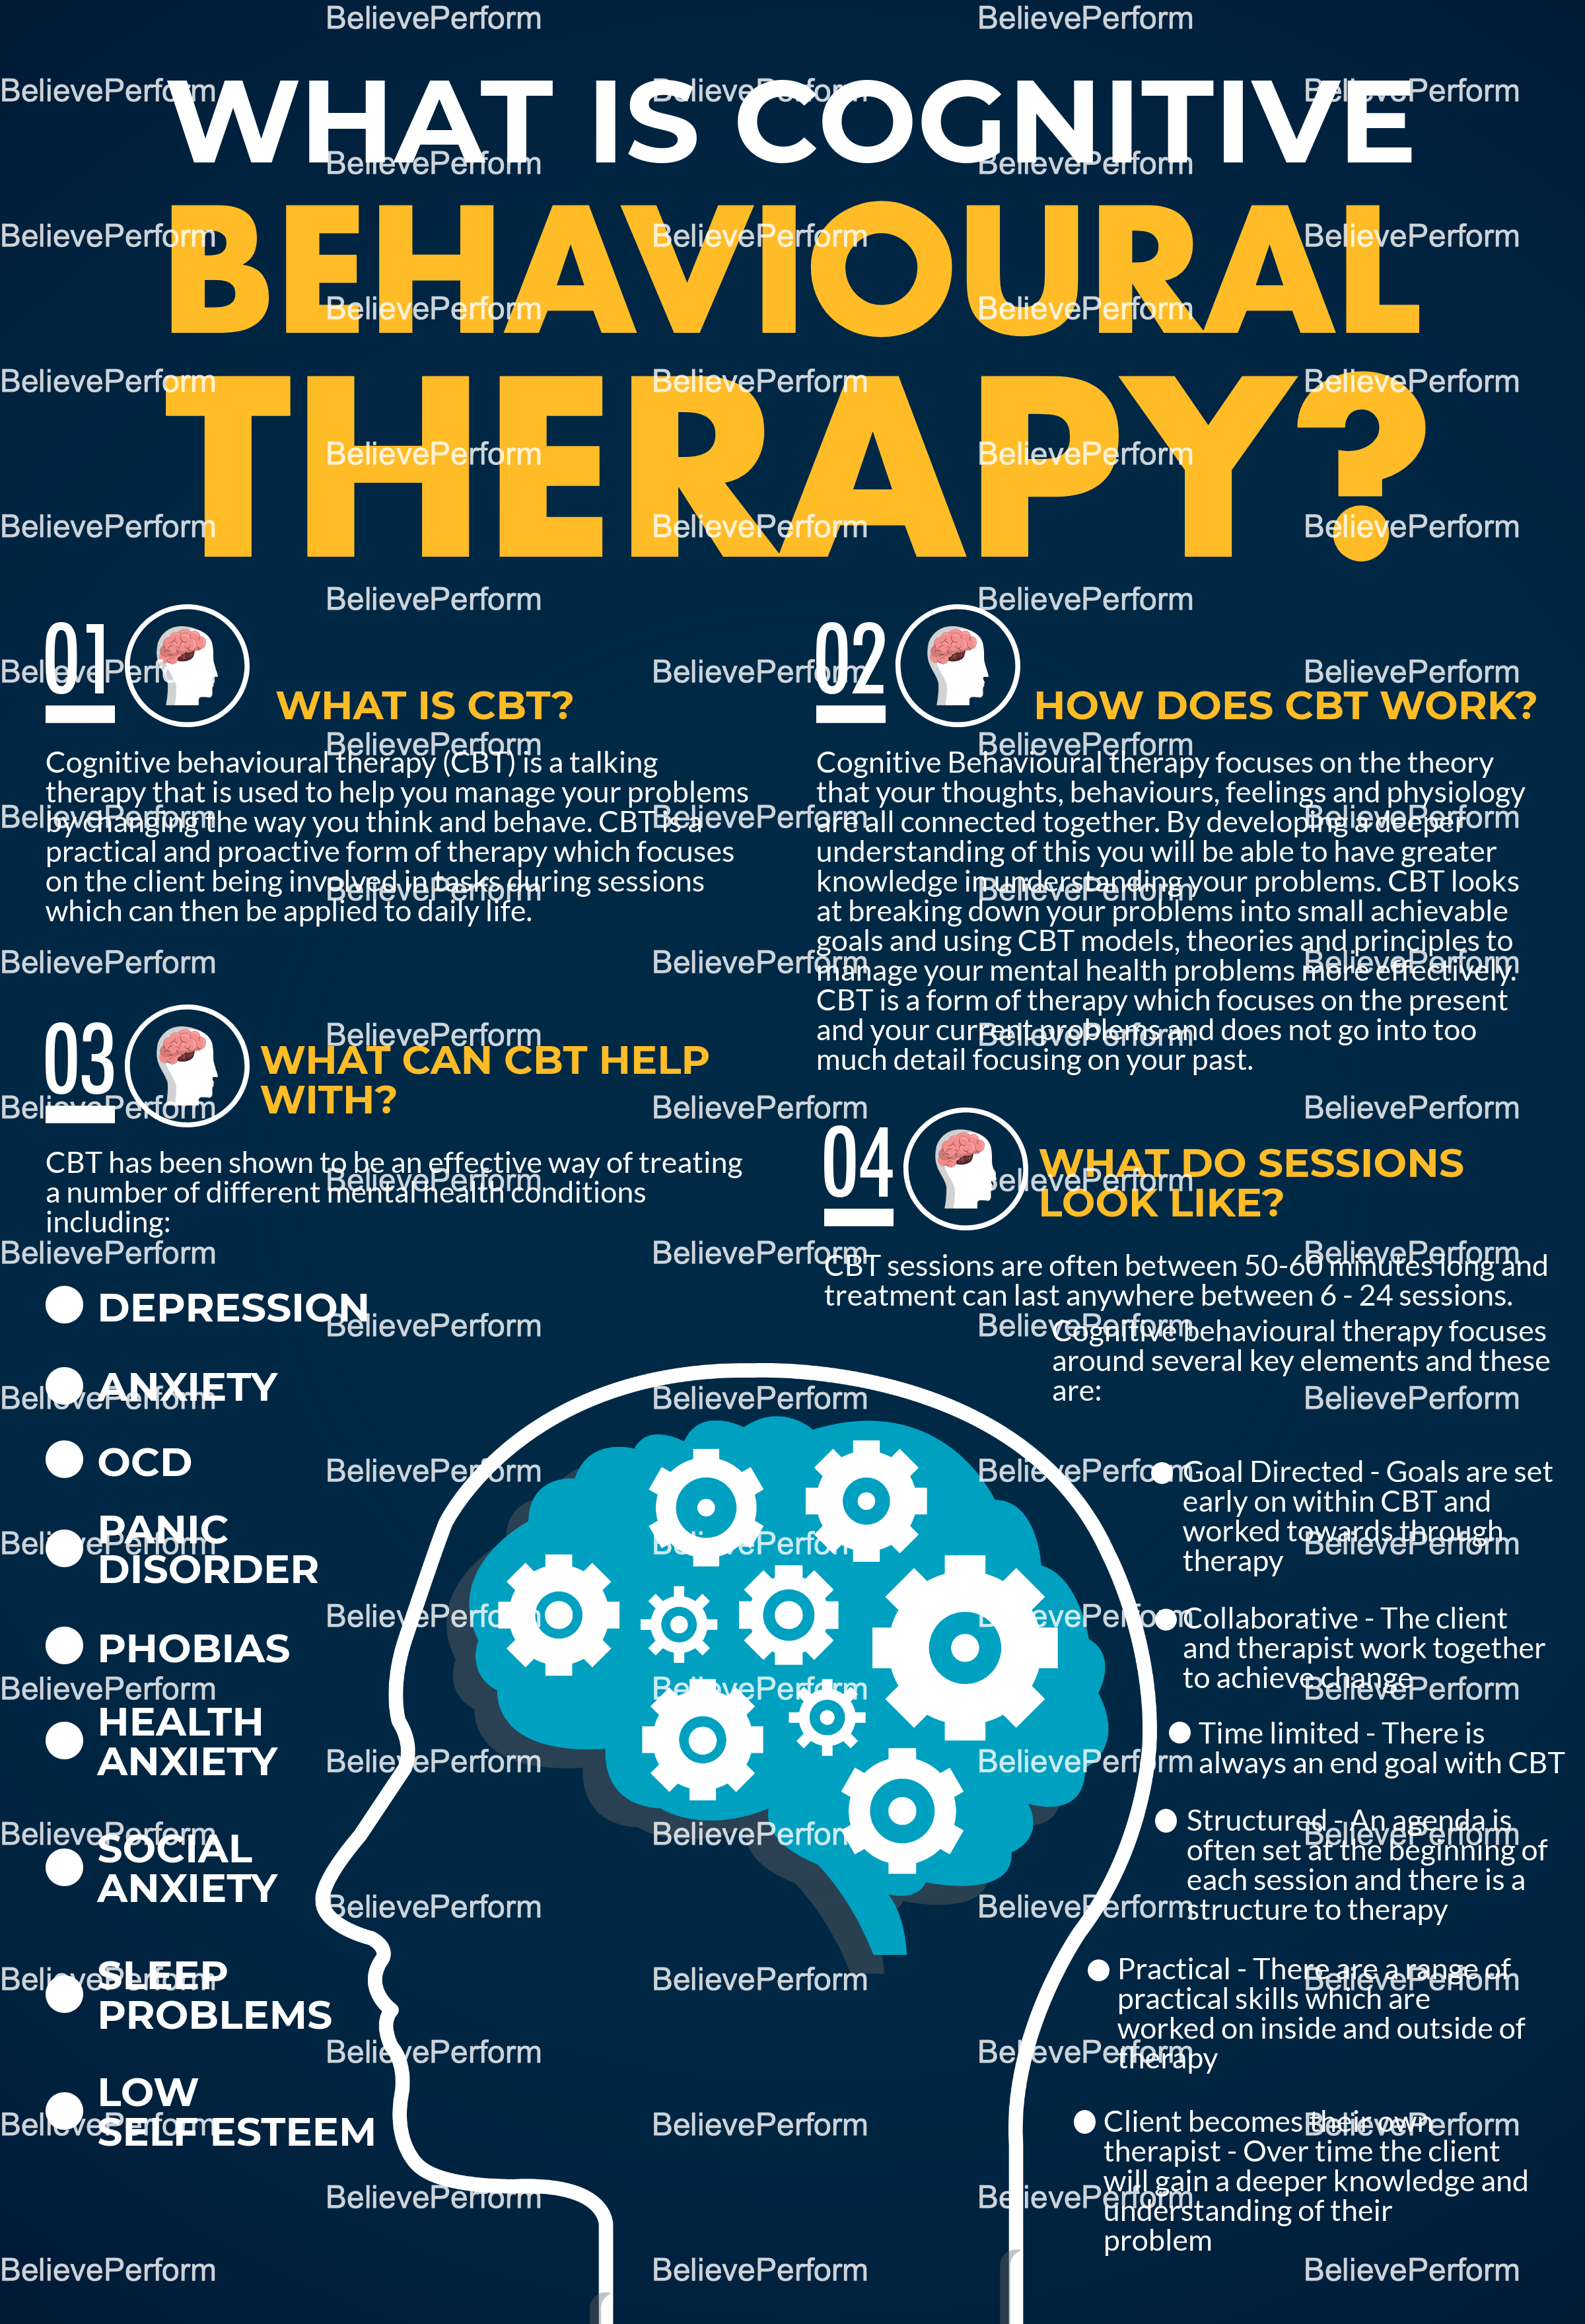
There's also the question of active ingredients. What exactly in CBT produces change? Is it cognitive restructuring? Behavioral experiments? The therapeutic alliance? A growing body of research suggests the alliance may matter more than the specific techniques. Patients who rate their therapeutic relationship highly show better outcomes regardless of which CBT protocol they received. This doesn't mean techniques don't matter. It means they operate within a relational context that either supports or undermines them. A poorly delivered CBT session by a therapist the patient doesn't trust is less effective than a good session from someone the patient feels understood by.
Specific complications and workarounds
One problem that comes up regularly and rarely gets addressed in training is the patient who is highly skilled at arguing with their own thoughts. These are often educated, analytical people who can generate three balanced alternative thoughts for every negative one. On paper, they're doing cognitive restructuring perfectly. In practice, they're using intellectualization as a defense mechanism. The argument becomes a form of rumination rather than genuine perspective shift. The workaround I use with these patients is to stop engaging with the content of their thoughts entirely. Instead of helping them reframe, I ask what happens when they don't reframe. What does the thought feel like in their body? What do they do when they have it? We shift from cognitive work to acceptance-based strategies. The patient learns to let the thought exist without needing to resolve it. This approach, drawn from third-wave CBT models like ACT, tends to produce faster change with this particular presentation than traditional cognitive restructuring ever does. Another complication is trauma-related material that surfaces during standard CBT work. A patient being treated for panic disorder might accidentally trigger a trauma memory during an exposure exercise. Standard CBT protocols weren't designed with this contingency in mind. The therapist needs to know how to pivot without abandoning the treatment structure. The approach I use is to pause the exposure, validate the trauma material, and schedule a specific session to address it using a trauma-informed protocol before resuming the original CBT work. Continuing the panic-focused protocol without acknowledging the trauma creates a risk of worsening symptoms and damage to the therapeutic alliance.
Practical considerations for implementation
If you're considering CBT for yourself or recommending it to someone, there are practical details that affect outcomes more than most people realize. Therapist competence matters enormously. CBT is deceptively simple to learn and surprisingly difficult to master. The difference between a competent and a barely competent CBT therapist is visible in outcomes. Look for someone who has completed formal CBT training, preferably from an established program like the Beck Institute or the Academy of CBT. Ask about their supervision frequency. Even experienced CBT therapists benefit from regular case consultation. The number of sessions needed varies widely. Twelve to twenty sessions is the standard range for most conditions. But some patients improve in six to eight sessions. Others need thirty or more. The initial assessment should include a discussion of expected timeline and a plan for monitoring progress. If there's no measurable improvement after six to eight sessions, the treatment plan should be revised, not continued unchanged.

Workbook-based CBT is available for self-guided treatment of mild to moderate depression and anxiety. The evidence for this approach is mixed but generally positive. Self-guided CBT produces smaller effect sizes than therapist-led CBT but is still significantly better than no treatment. The key factor is adherence. People who complete the full program get meaningful benefits. Most people don't complete the full program. Structure and accountability, even from a support group or online community, substantially improve completion rates. One specific resource that's widely available and well-regarded is the workbook "Feeling Good" by David Burns. It covers the core cognitive restructuring techniques in an accessible format. For panic disorder, "Panic Disorder: A Cognitive Perspective" by David Barlow and Susan Evans is more specific. These books aren't substitutes for therapy in moderate to severe cases but can be useful adjuncts or starting points for mild presentations.
Bottom line
CBT is the most researched and most widely available form of psychotherapy for a reason. It produces reliable change for a broad range of conditions. But it's not a universal solution. It works best for patients who can engage cognitively, complete homework, and tolerate the discomfort that change requires. It works less well for patients with severe personality pathology, active substance dependence, or cognitive impairments that limit abstract thinking. The quality of the therapist matters as much as the model itself. And the skills only stick when the patient continues using them after treatment ends, which means the treatment needs to actively prepare for that transition rather than assuming it will happen automatically.