What Cognitive Research And Therapy Actually Looks Like In Practice
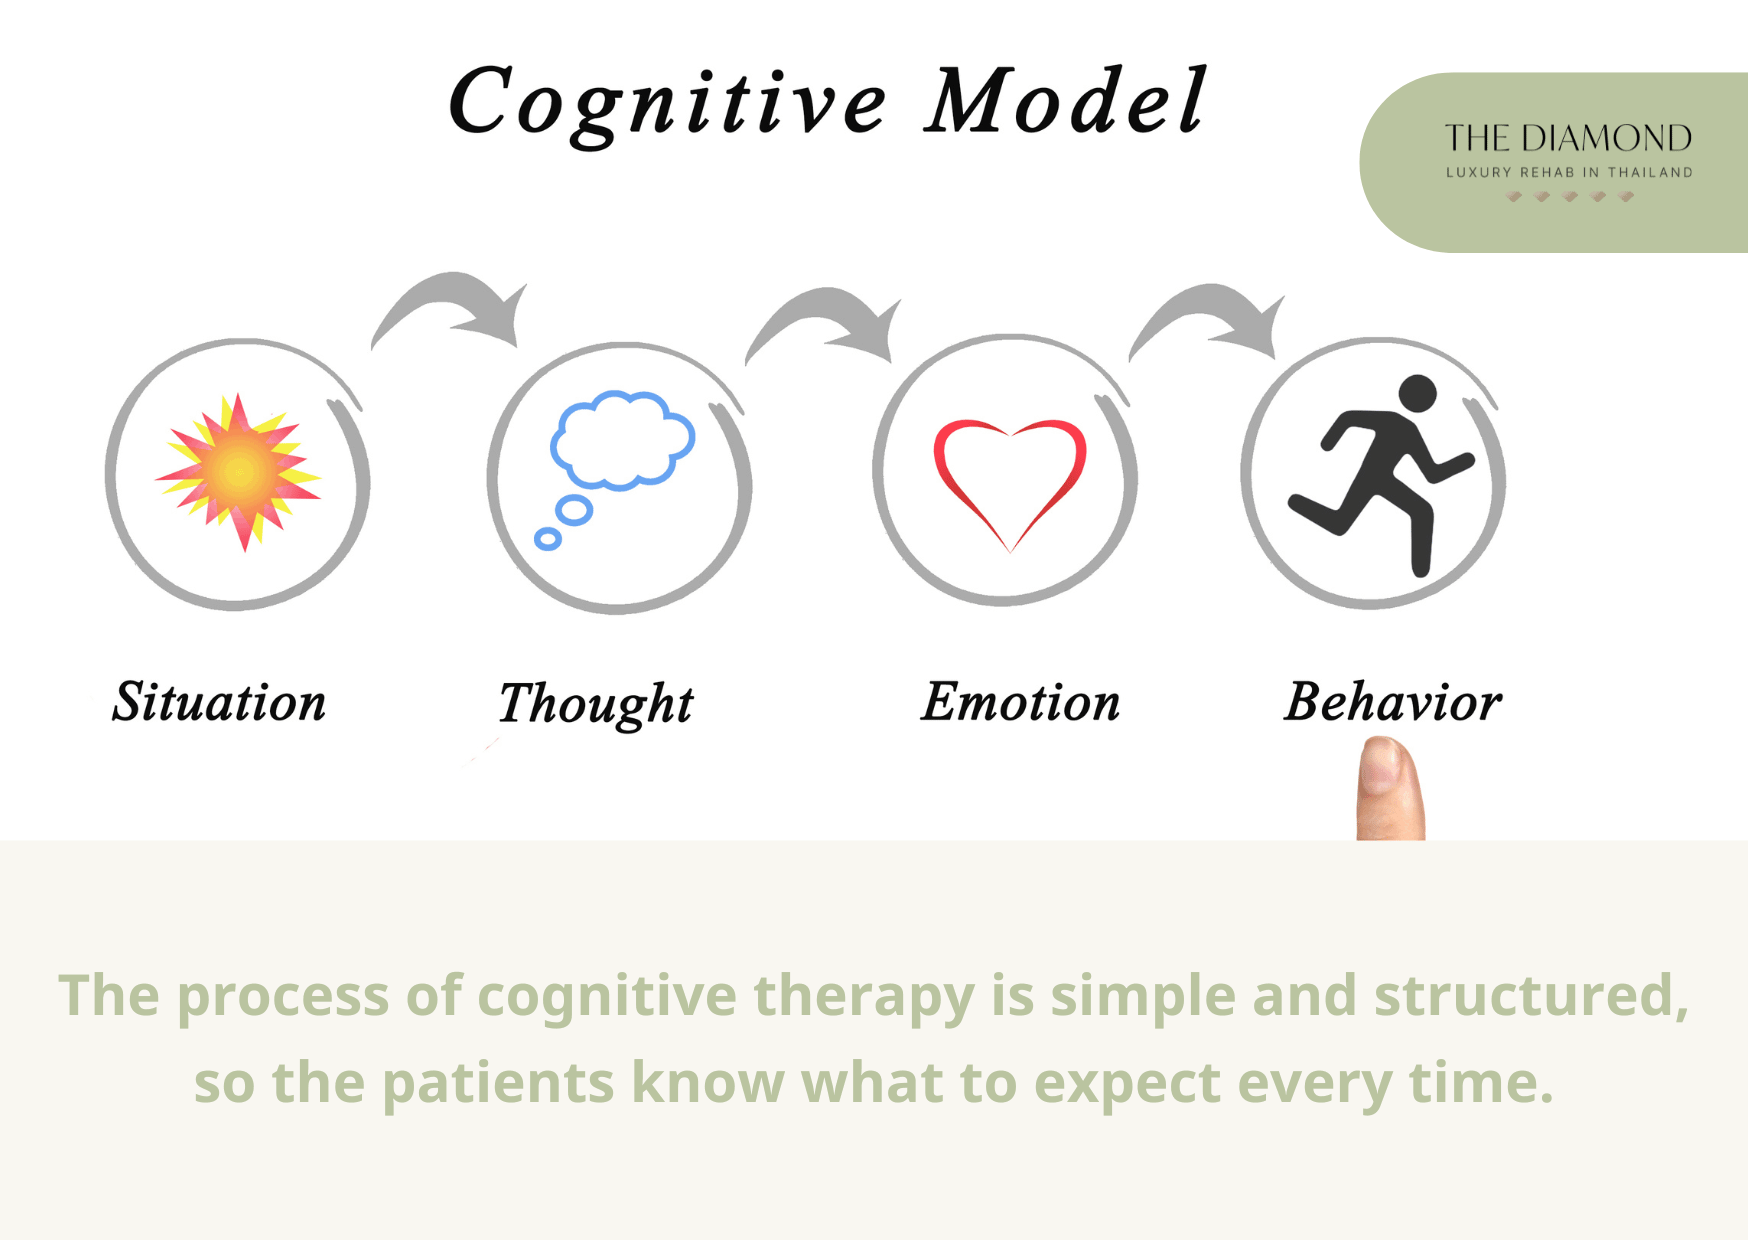
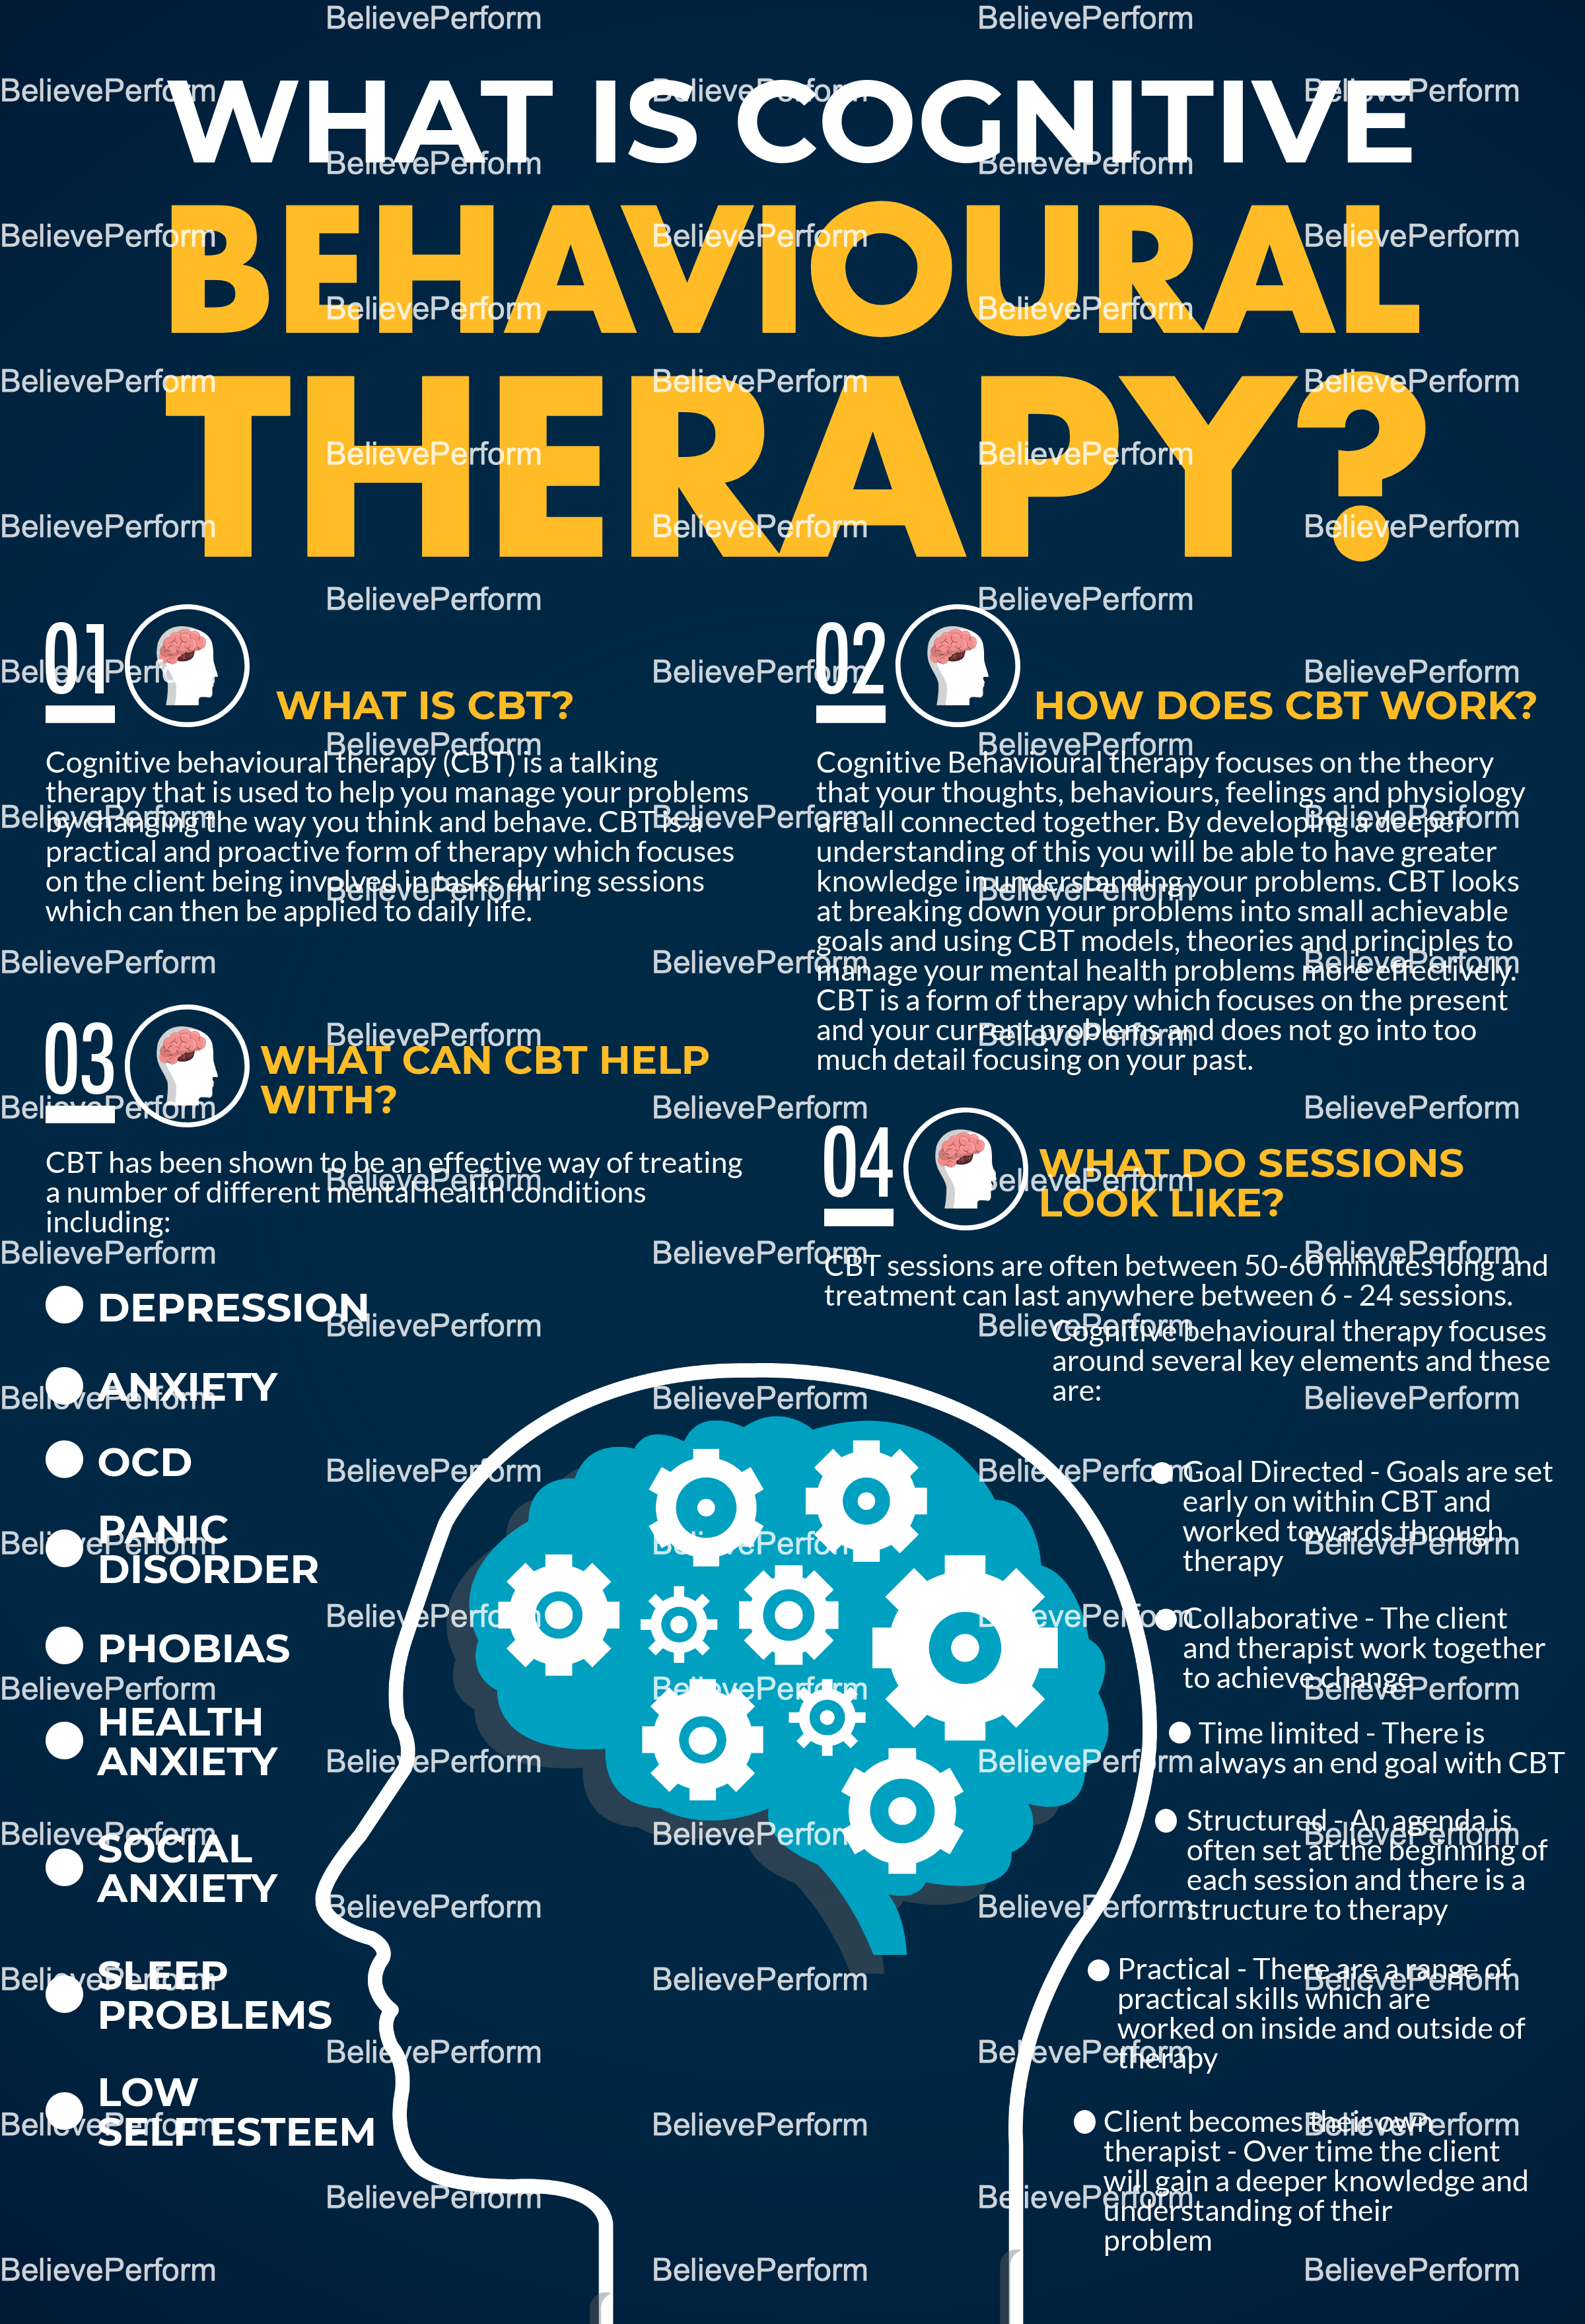
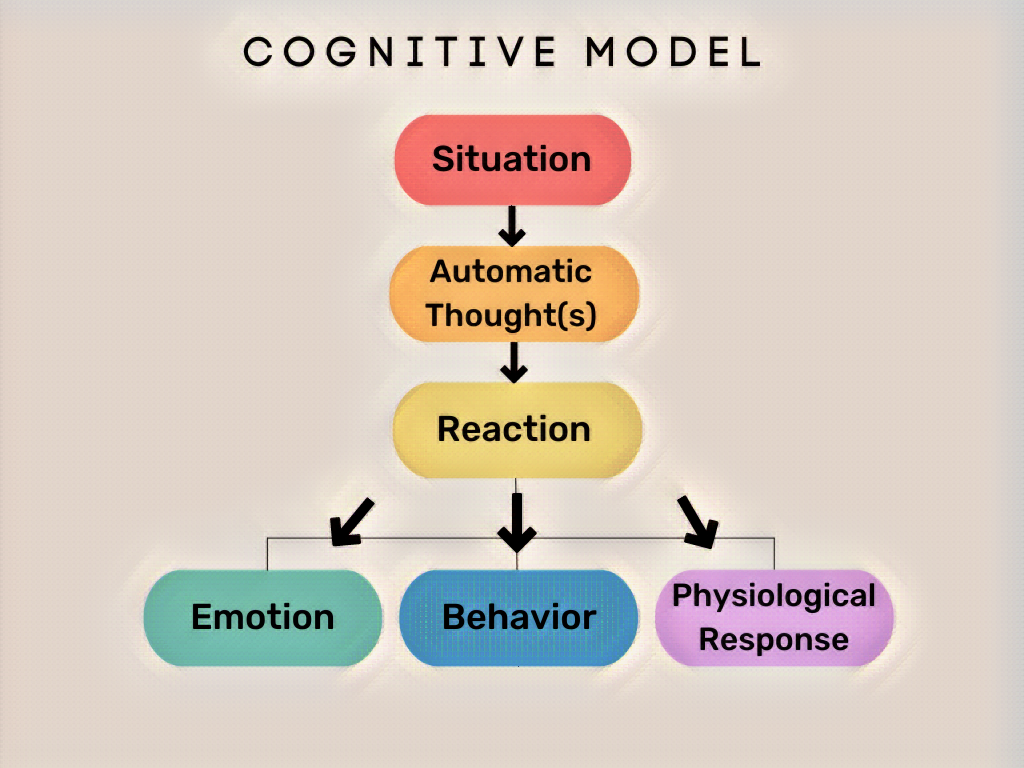
Cognitive Research And Therapy sits at the intersection of clinical psychology and behavioral science, and most people walking into it have no idea what they're signing up for. It's not a single modality. It's a framework that pulls from cognitive behavioral techniques, neurocognitive assessment, and emerging research on how thought patterns reinforce or disrupt mental health outcomes. I've spent enough years around this space to say: the gap between the textbook definition and what happens in a real clinic is enormous. When someone comes to therapy with anxiety or depression, the traditional CBT approach is to identify cognitive distortions and restructure them. Cognitive Research And Therapy expands that by incorporating standardized neuropsychological assessments, longitudinal tracking of thought patterns, and sometimes biometric feedback. The idea is to move beyond episodic symptom management and actually map the architecture of how a person's cognition operates under stress, during routine tasks, and across different emotional states.
The Cognitive Research And Therapy Process Explained
Here's how it typically unfolds in a legitimate clinical setting. The first phase is assessment, and this is where most people who shop around for providers get it wrong. They expect a thirty-minute intake and then a treatment plan. Real cognitive research and therapy protocols usually involve a baseline session that includes validated instruments like the Beck Depression Inventory, the Spielberger State-Trait Anxiety Inventory, and increasingly, computerized cognitive testing batteries such as the Cogstate or Cambridge Neuropsychological Test Automated Battery. These tools generate data on attention, working memory, processing speed, and executive function that neither a standard clinical interview nor patient self-report can capture alone. I ran into a specific problem with one patient where the standard assessment tools were giving contradictory results. She scored in the mild range on depression inventories but showed significant impairments on processing speed and cognitive flexibility tasks. The discrepancy wasn't a testing error. It turned out she had been masking her symptoms for years through high-functioning anxiety, which is a profile that routinely slips through conventional screening. The workaround I ended up using was to add the Trail Making Test parts A and B alongside the Stroop task, which exposed the executive dysfunction that the questionnaires completely missed. That data then shaped an entirely different intervention strategy focused on cognitive remediation rather than just talk-based restructuring. After the assessment phase, the therapy component blends structured cognitive work with ongoing monitoring. Some clinics use digital platforms where patients complete brief daily cognitive exercises and mood logging. Others stick to weekly sessions with periodic reassessment every eight to twelve weeks. The key difference between this and standard therapy is that progress isn't measured primarily by how the patient feels. It's measured by whether the cognitive metrics are moving in the right direction alongside reported symptom changes.
Common Misunderstandings That Waste Time And Money
One thing nobody tells you about cognitive research and therapy is that it's not appropriate for every case. People with active psychosis, severe personality disorders without comorbid cognitive components, or untreated substance dependence often don't benefit from the standard cognitive research framework. The structured nature of the interventions requires a certain level of introspective capacity and cognitive stability. Pushing someone who isn't ready into this model usually means you're spending six months trying to build foundational skills that should have been addressed first. Another pitfall is the assumption that more testing equals better outcomes. I've seen clinics run extensive neuropsychological batteries that take four to six hours and produce pages of data that never actually inform the treatment plan. That's not thoroughness. That's billing optimization. A well-designed cognitive assessment for therapy purposes should be targeted and actionable. If you can't map a specific test result to a specific intervention choice, you're collecting noise, not signal. The counter-intuitive part that most beginners miss is that cognitive research and therapy often shows its strongest results with conditions outside the obvious ones. There's growing evidence for its application in chronic pain management, where cognitive restructuring around pain perception and attentional bias modification can reduce subjective pain scores by meaningful margins. The same framework helps with insomnia when the issue is cognitive arousal rather than purely behavioral. And for ADHD in adults, the combination of cognitive remediation and therapy addresses the executive function deficits that medication alone doesn't fully resolve.
Get the Full Details

What You Should Actually Look For
If you're considering this approach, the provider credentials matter more than the label on their door. Look for someone with training in both clinical psychology and psychometrics. A therapist who only knows CBT but has never administered a formal cognitive assessment isn't doing cognitive research and therapy. They're doing CBT with a different name. The professional organizations that certify this kind of work include the American Psychological Association's Division 40, which covers clinical neuropsychology, and the National Academy of Neuropsychology. You should also ask about the data they collect and how they use it. A legitimate provider will show you your baseline scores, explain what each measure means, and discuss how treatment adjustments will be informed by repeat testing. If they can't articulate that clearly, move on. This field has enough charlatans capitalizing on the sound of scientific language without you feeding the problem. The cost is another practical consideration. A full cognitive assessment battery can run anywhere from five hundred to two thousand dollars depending on the instruments used and whether it's covered by insurance. Many plans treat neuropsychological testing as a separate benefit with its own copay structure. Therapy sessions on top of that will follow your standard mental health coverage terms. Factor in that a complete protocol might include three to five assessment sessions plus eight to twenty therapy sessions before you're evaluating whether it's working. Budget accordingly instead of assuming this is a quick fix.
I've also noticed that the field is shifting toward hybrid models that combine technology-assisted cognitive training with traditional therapy. Apps and computer programs for cognitive remediation have improved significantly, and some studies suggest that home-based practice between sessions can accelerate progress by roughly thirty percent compared to session-only approaches. The tradeoff is that these tools require patient compliance, and compliance drops sharply when the exercises feel repetitive or disconnect from the actual therapeutic goals. The best providers I've worked with integrate digital tools selectively rather than making them the centerpiece. The honest bottom line is that cognitive research and therapy is a legitimate and increasingly important approach when applied correctly, but it's not a universal solution and it's frequently misrepresented by clinics looking to charge premium prices for rebranded services. The people who benefit most are those with clear cognitive profiles that can be measured and tracked, providers who actually understand psychometrics rather than just the therapy model, and patients who are prepared for a longer, data-driven process instead of the rapid breakthrough narrative that dominates the mental health marketing space.