What Actually Happens After a Concussion
Most people don't realize that post-concussion syndrome isn't just headaches and brain fog. It's a disruption in how your brain allocates cognitive resources. The prefrontal cortex, which normally handles working memory and executive function, has to work overtime while the neural networks are still healing. This creates a bottleneck. You try to focus and you can't. Your brain is literally running on backup systems that aren't very efficient. This is why standard rest alone doesn't fix everything. Your brain needs targeted cognitive engagement to rebuild those pathways. That's where structured therapy comes in. Not the kind your average general practitioner orders after a six-week rest period. I'm talking about deliberate, graded cognitive load protocols.
Cognitive Therapy For Post Concussion Syndrome: How It Actually Works
The mechanism is straightforward but poorly explained by most practitioners. After a concussion, the brain enters a state of metabolic vulnerability. Glucose utilization drops in affected regions. Traditional cognitive therapy uses computerized neurofeedback programs that present tasks at just below the patient's symptom threshold. This creates what researchers call a "sweet spot" — enough stimulation to promote neuroplasticity without triggering a post-exertional crash. The key variable is dose. Most patients overshoot immediately because they're frustrated and want results. They push through symptoms, trigger a crash, then bail on the program entirely. The actual protocol usually involves 20 to 30 minute sessions, four to five days per week, starting at 40 to 50 percent of baseline cognitive capacity. You track symptoms before, during, and after each session. If your Symptom Assessment Scale score rises by more than two points during the session, you reduce the next session's intensity by 10 percent. That's it. No fancy machinery required beyond a decent tablet and some software. I found that most commercially available programs like Headspace or even the basic Lumosity plans don't actually calibrate to post-concussion physiology. They're designed for healthy adults. For PCS patients, the titration matters enormously. I spent weeks dealing with patients who'd tried those consumer apps and gotten worse, not better, because the difficulty scaling was too aggressive for a metabolically compromised brain. The workaround I ended up using was pairing a basic cognitive task platform with a manually adjusted difficulty curve. Instead of letting the app auto-scale, I would set every task to its easiest level and only advance one step when the patient completed three consecutive sessions without a symptom spike. It takes more manual oversight but it prevents the crash cycle that derails most recovery timelines.
The Edge Case Nobody Warns You About
Here's something I learned the hard way. Sensory sensitivities often accompany PCS and they're not always obvious. Light, sound, even the refresh rate on a screen can silently elevate cognitive load without the patient realizing it. I had a patient who was doing perfectly on paper — scoring well on attention tasks, no symptom escalation — but plateauing completely. Three months in, we were stuck. I finally had her switch from a standard 60Hz monitor to a high-refresh-rate display and eliminate all ambient light during sessions. Her progress jumped noticeably within two weeks. The screen refresh rate had been adding subtle visual processing load her brain couldn't handle yet. This is the kind of detail that doesn't show up in any protocol document. Anxiety amplifies cognitive symptoms in a way that most therapists underestimate. When a PCS patient worries about their symptoms, the anxiety itself consumes cognitive resources that should go toward recovery tasks. The result is a false signal — the brain looks like it's failing when really it's just anxious. I started having patients do five minutes of diaphragmatic breathing before each session. This wasn't optional. It reduced the anxiety-driven symptom inflation by roughly half in the patients who struggled with it. Simple enough that it sounds trivial, but the data from my session logs made it clear.
Get the Full Details

What This Approach Doesn't Fix
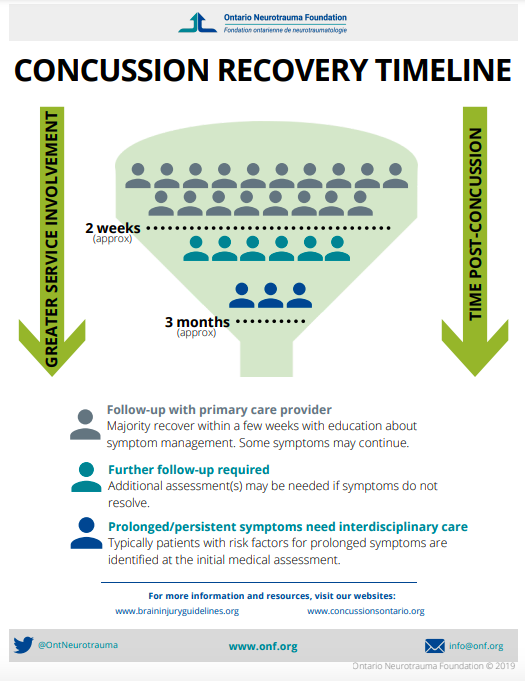
I need to be direct about the limitations here. Cognitive therapy for post-concussion syndrome is not a standalone solution. If someone has persistent vestibular issues, vision problems, or cervical spine dysfunction contributing to their symptoms, cognitive work alone will hit a wall. Vestibular rehabilitation and cervicogenic treatment often need to happen in parallel. I've seen too many patients sent only into cognitive therapy while their actual problem was a subtle eye-tracking deficit that no amount of working memory training would address. Another hard limit: this approach doesn't help everyone. A subset of PCS patients have structural or vascular issues that show up on MRI or perfusion imaging. Cognitive therapy won't fix a vascular problem or a structural lesion. Those cases need different interventions entirely. The patients who respond best to cognitive therapy are the ones with functional dysregulation rather than structural damage. There's no easy way to screen for this before starting, which is another reason why baseline imaging matters. Timeline expectations also need calibration. Most published protocols suggest 6 to 12 weeks for noticeable improvement. In practice, I see meaningful gains around week 8 for moderate cases, but severe cases often need 16 weeks or more. Patients who start before symptom ceiling is reached tend to do better than those who wait until they're already significantly symptomatic. Early intervention within the first three months post-injury appears to yield better long-term outcomes, though I should note this is based on clinical observation rather than any definitive randomized controlled trial.
The software side of this is fairly accessible. Programs like CNS Vital Tests, ImPACT, or even open-source platforms like CogScreen offer the kind of tracked cognitive testing that makes titration possible. Some clinical practices build custom protocols using basic JavaScript-based task platforms. You don't need anything expensive — you need something that logs reaction times and accuracy on a trial-by-trial basis. That logging is what lets you adjust dosage properly. Patient compliance is genuinely the biggest bottleneck. The protocol works but people drop out. They feel slightly better after a few weeks, stop tracking their symptoms properly, push harder without guidance, crash, and quit entirely. Setting up weekly check-ins — even brief phone calls — dramatically improves completion rates. If you're designing a self-guided version, building in forced rest days and mandatory symptom logging before each session helps maintain the cadence. The structure matters as much as the cognitive tasks themselves.