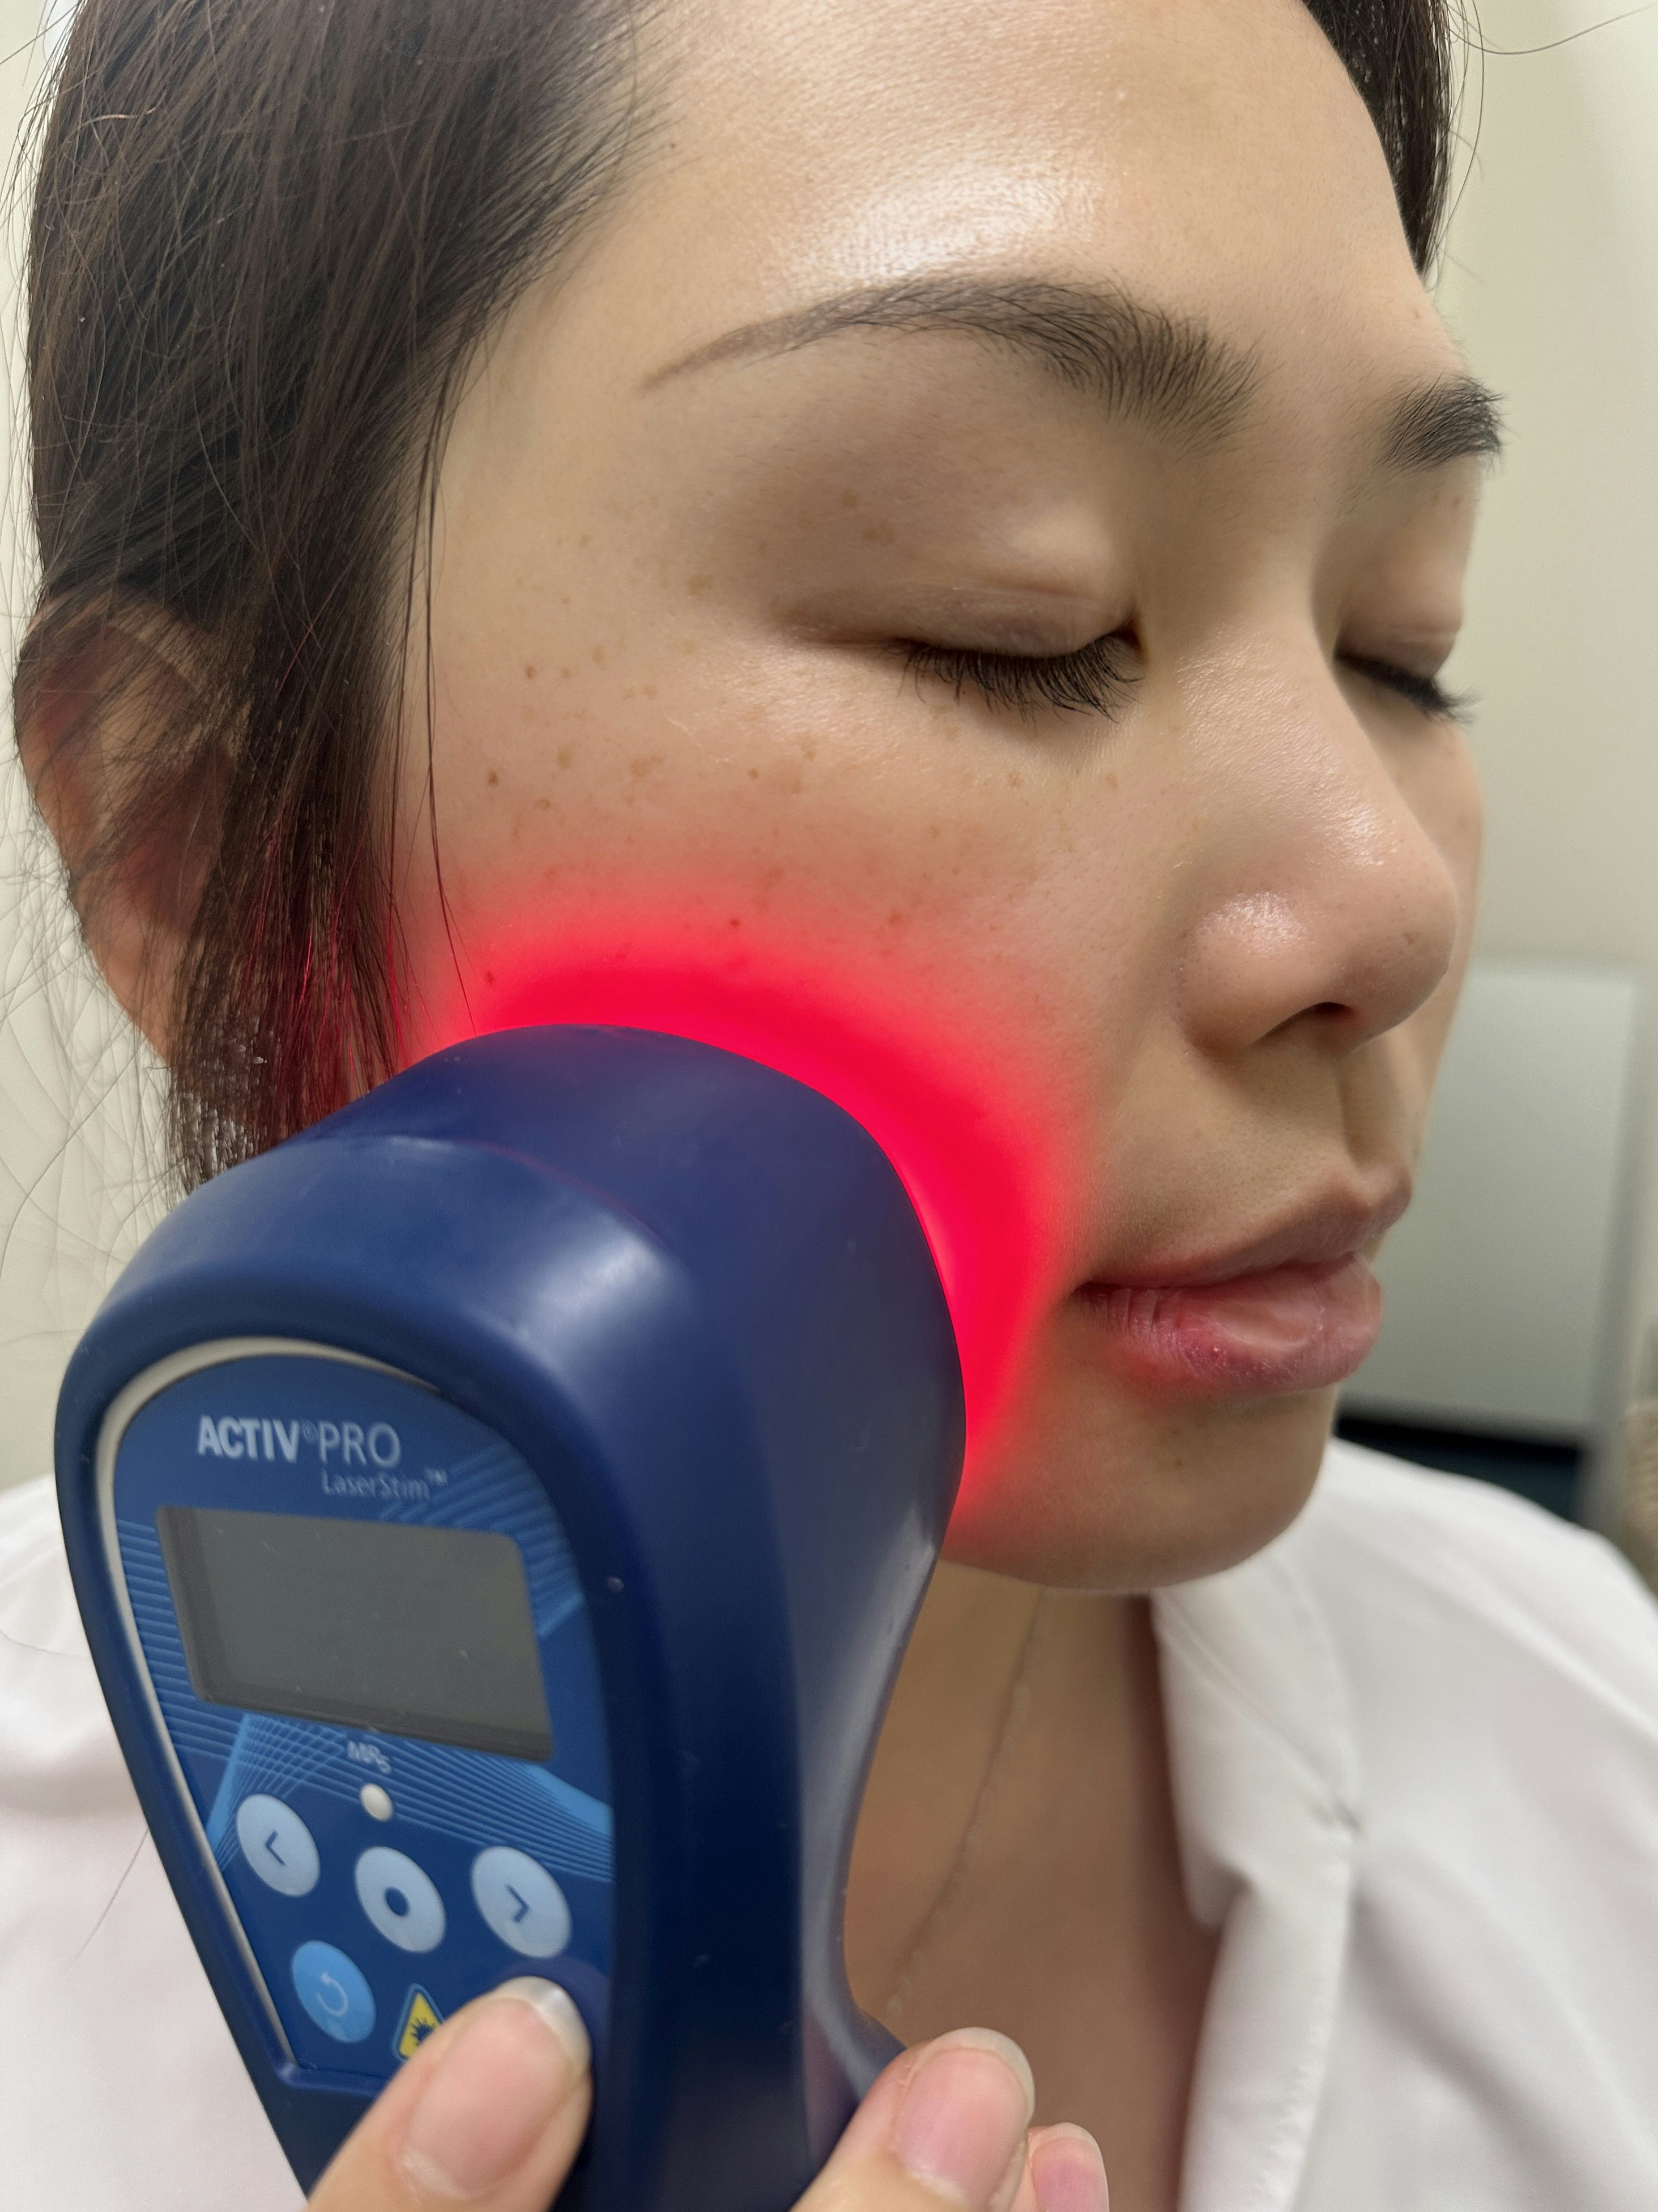
Low-Level Laser Therapy and the Trigeminal Nerve
Trigeminal neuralgia is one of the more miserable chronic pain conditions out there. The kind where even a breeze hitting your face can set you off. Most people know it as tic douloureux, and for good reason — the pain is sharp, electric, and comes in waves that leave you doubled over. Standard treatments like carbamazepine or oxcarbazepine work for a while, then stop. Microvascular decompression surgery carries real risk. So people end up exploring peripheral options, and cold laser therapy keeps coming up in forums and clinical discussions. I've spent years working with nerve pain patients and the equipment side of things, so I'll cut to how this actually works rather than giving you a textbook definition.
How Cold Laser Therapy For Trigeminal Neuralgia Actually Works
It's technically called low-level laser therapy or photobiomodulation. A diode laser or LED array emits light at specific wavelengths — usually in the red to near-infrared range, somewhere between 600 and 1000 nanometers. That light penetrates the skin and underlying tissue, gets absorbed by cytochrome c oxidase in the mitochondrial membrane, and triggers a cascade that increases ATP production, modulates reactive oxygen species, and shifts ion channel activity. In plain terms, the nerve becomes less excitable. The trigeminal branches get some inflammatory mediators dialled down, and the pain signalling along those A-delta and C fibers slows out. This isn't a cure. It's a neuromodulation technique, and the effect is usually temporary unless you stack enough sessions to build a cumulative response. I'd say a typical short-term reduction in firing frequency shows up after three to five treatments, and patients tend to need maintenance sessions every week or two once they find their baseline.
What It Feels Like During a Treatment
You won't feel much. That's the whole point of "cold" laser — there's no thermal damage. The tip of the applicator goes near the trigger zones along the V1, V2, or V3 distribution of the trigeminal nerve. Sometimes that's just outside the eyebrow, along the cheekbone below the eye, or near the angle of the jaw. The light pulses on and off, usually in the 808 to 905 nanometer range. Each point gets maybe sixty to ninety seconds of exposure, and a full facial treatment runs about ten to fifteen minutes depending on how many branches are involved. The patient sits in a chair, sometimes wearing protective goggles if the device puts out anything above Class II, though most therapeutic units are well within safe exposure limits for brief facial treatment. There's no heat, no vibration, no sensation worth describing. Some people report a mild warmth, but that's usually from ambient room temperature or anxiety, not the laser itself. What matters more is what happens after. A subset of patients feel a bit of fatigue or a temporary increase in symptoms in the first twenty-four hours. It's not common, maybe one in five, but it's real enough that I always warn people going in. Think of it like a nerve recalibrating — it doesn't always go in the direction you'd prefer.
Get the Full Details

Where Beginners Mess Up
Most people I see trying this at home with consumer-grade devices run into the same problems. The first is wavelength selection. A lot of off-the-shelf lasers are stuck at 650 nanometers or even lower, which scatters too much in tissue and never reaches the trigeminal branches meaningfully. You want something at least 808 nanometers for V2 and V3, and ideally a dual-wavelength unit that can hit both red and near-infrared. The second problem is power density. A 5 milliwatt pointer-style device is useless for neural tissue. You're looking at classes that deliver somewhere around 50 to 200 milliwatts per applicator head, coupled with sufficient energy density — measured in joules per square centimeter — to actually do something at the nerve level. A decent protocol aims for about 4 to 10 J/cm² per treatment point. That usually means a few hundred millijoules per application depending on the spot size. Run the numbers wrong and you waste time. Go too high and you risk inhibitory effects — the Biphasic Curie-Weiss curve is real, and overdoing the dose can make symptoms temporarily worse instead of better.
A Specific Problem I Ran Into
Working with a patient who had pure V1 involvement was frustrating because the orbital branch sits deep behind the orbital rim. The laser energy has to travel through bone and dense connective tissue before it ever reaches the nerve trunk. Surface-level treatment of the forehead gave almost nothing. The workaround was switching to transnasal placement — positioning the fiber optic applicator just inside the nostril, angled toward the lateral nasal wall where the anterior ethmoidal nerve exits. That brought the light source within a centimeter or two of the ophthalmic division's proximal pathway. Energy delivery improved dramatically, and that patient went from scoring eight out of ten on the pain scale down to a three after eight sessions. It's a niche approach that most protocols don't mention, and it requires a device small enough to fit in that space without causing discomfort. Here's what I'd start with for a new case. Use an 808 nanometer diode laser at around 100 milliwatts output, applied to the following points along the affected trigeminal branch: Each point gets 60 to 90 seconds of treatment, delivering approximately 6 to 8 J/cm². Sessions three times per week for two weeks, then reassess. If there's less than 30 percent improvement after ten sessions, the protocol probably isn't going to work for that individual, and you should reconsider the diagnostic picture or move to a different modality.
Cold laser therapy for trigeminal neuralgia is not going to fix vascular compression. If there's a loop of the superior cerebellar artery pressing on the trigeminal root entry zone, as happens in the majority of classic TN cases, no amount of photobiomodulation is going to move that vessel. You're treating peripheral symptom modulation, not the underlying structural cause. For some patients — the ones with secondary TN from demyelinating disease, post-herpetic neuralgia, or idiopathic cases where no compression is found — the peripheral approach can still matter because there's no surgery to point toward. It's also not fast. You won't walk in and walk out pain-free. The onset of benefit typically takes four to eight sessions, and even when it works, the effects taper off if you stop treatments entirely. Maintenance is usually necessary, and the cost-addition of repeated sessions adds up over months. If you're considering this, make sure you're working with someone who understands nerve anatomy and laser physics, not just a spa technician with a red-light device. The difference between a useful treatment and a waste of money is largely in the wavelength specification, the power output, and whether the operator knows where the trigeminal branches actually run beneath the surface.