How to Use the C-SSRS Without Screwing It Up
The Columbia Suicide Severity Rating Scale isn't a diagnosis tool. It's a screening instrument. People conflate the two constantly, and it costs you clinical credibility when you try to present C-SSRS results as a definitive assessment. The scale ranks suicidal behavior from ideation to completed suicide across specific severity levels, and each level has a defined behavioral anchor that you cannot stretch or interpret loosely. Most users grab the free version from the University of Pennsylvania's website and start applying it immediately. That's the right instinct, but here's what nobody tells you about the implementation side. The adult version takes roughly 10 to 15 minutes in a controlled setting. In an emergency department during a busy shift, it stretches to 20 or 25 minutes because you're navigating through interrupted responses and incomplete answers. The child-adolescent version runs longer. Factor in translation time if you're working with a patient who doesn't speak English fluently.
What the Columbia Suicide Severity Rating Scale Actually Measures
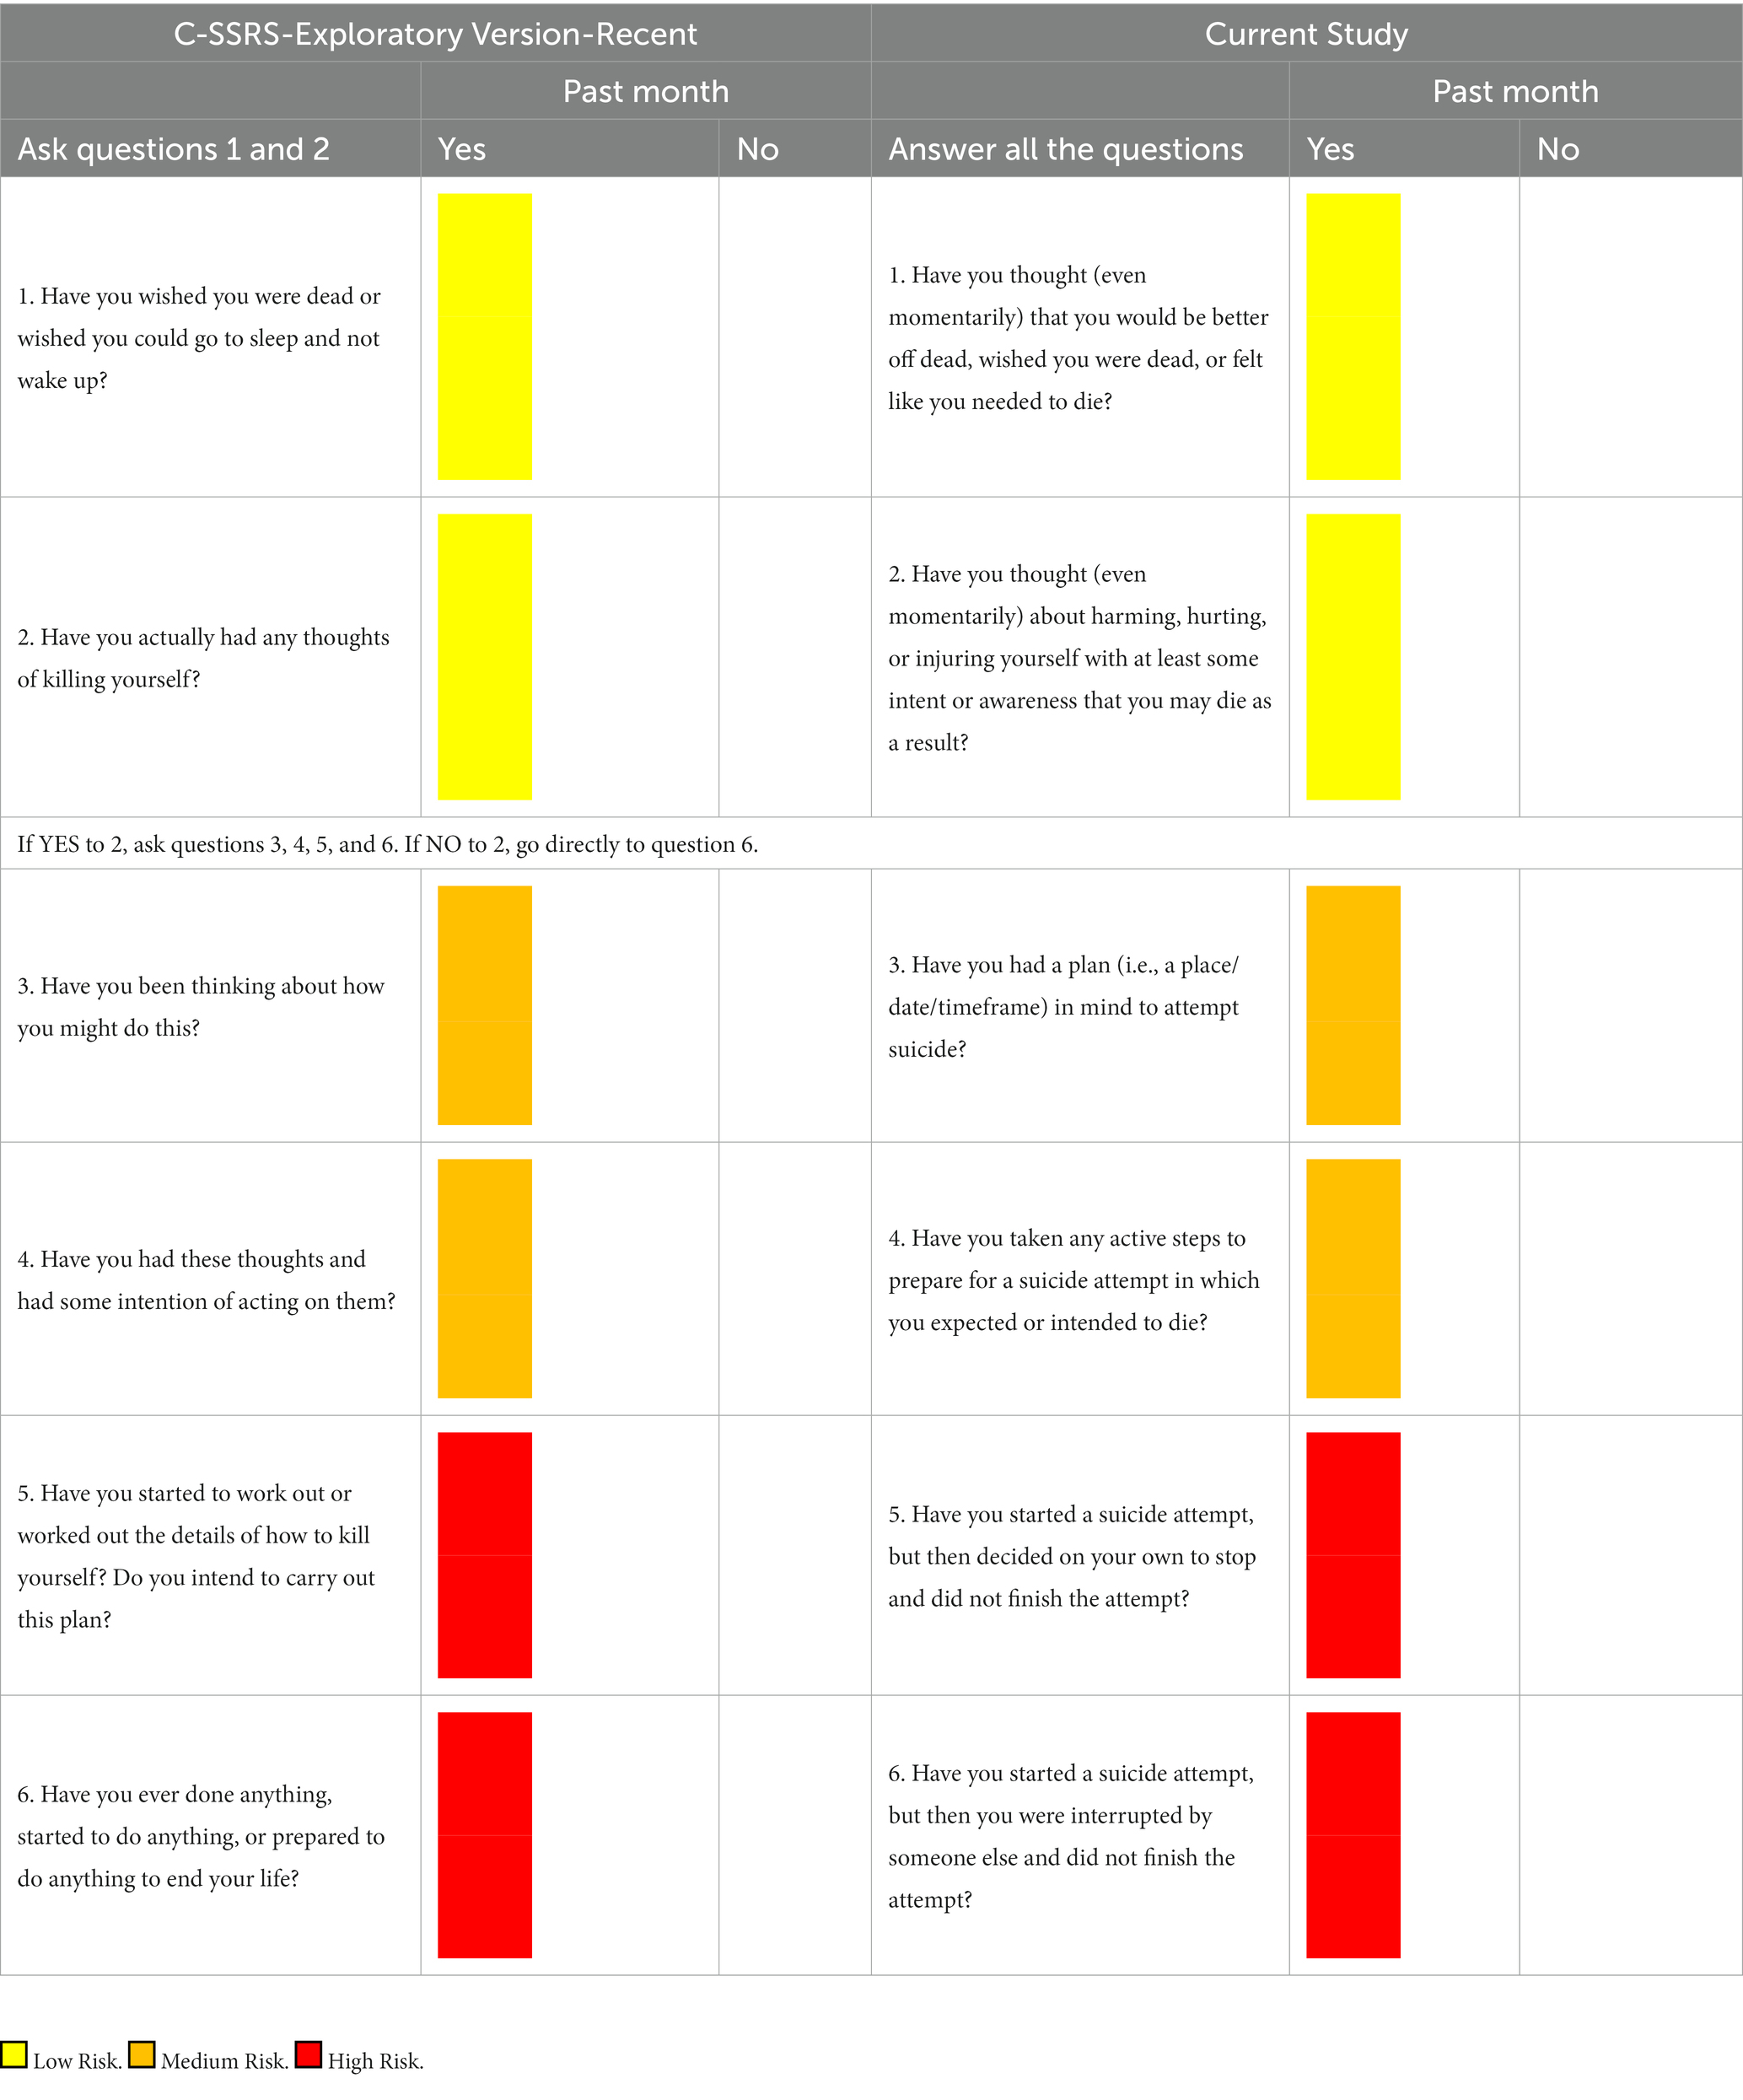
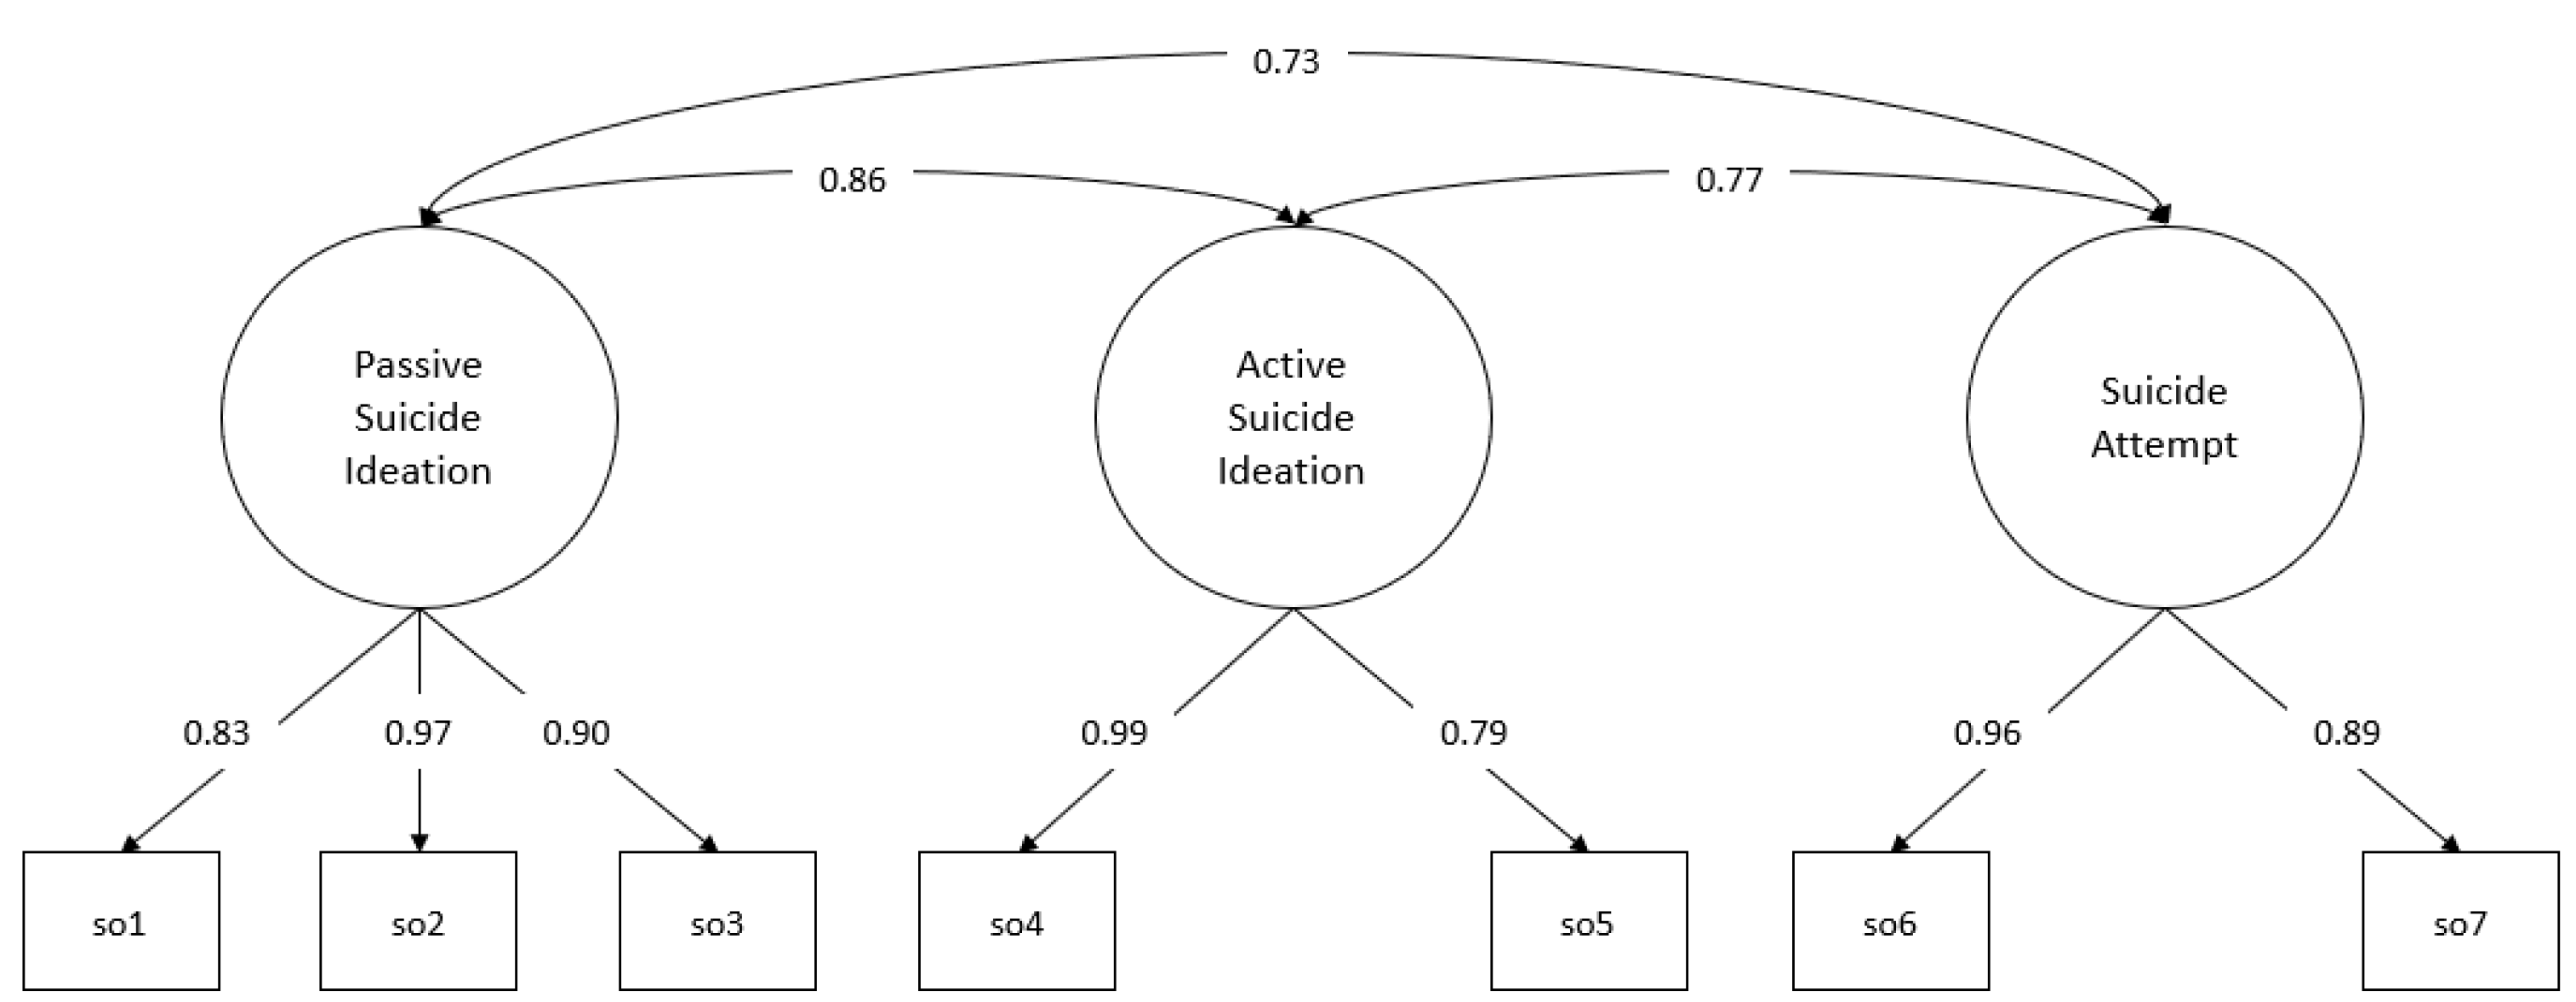
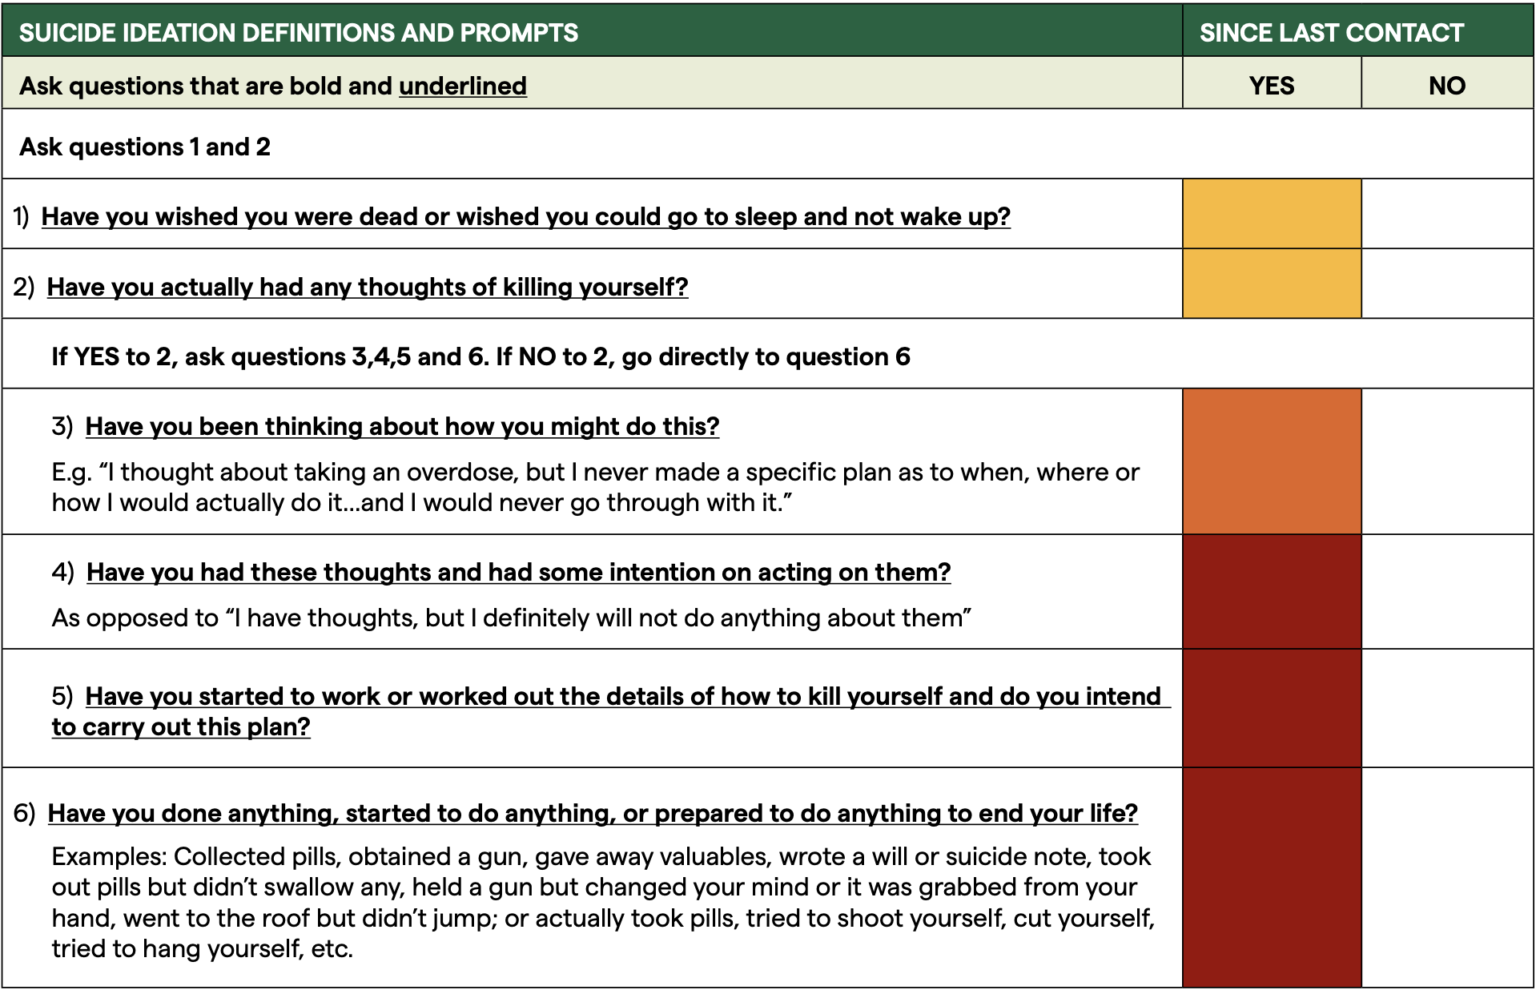
The scale breaks into two main domains: suicidal ideation and suicidal behavior. The ideation domain covers three subtypes that people routinely misorder. Actual ideation means the person has thought about killing themselves with some degree of intention. Active ideation without a plan means they want to die but haven't formed a method. Active ideation with a plan and intent is where clinical urgency spikes. Between those three categories sits the most commonly misunderstood distinction: the difference between passive ideation and active ideation without a plan. Passive ideation is thinking death would be easier, without any active desire to act on it. That distinction matters because it changes your risk stratification entirely, and the scale treats them as separate scoring branches. Behavioral items cover abortive self-interruption, self-interrupted attempts, interrupted attempts, and actual attempts. Abortive self-interruption is when someone starts the behavior and stops themselves. That's clinically significant even though it doesn't register as an attempt. You'll see people skip that item because it feels less dramatic than a full attempt, but missing it underestimates risk.
A Practical Workflow
Open the current version from the C-SSRS institutional site. You need an Institutional Review Board registration number only if you're using it for research. For clinical practice, just create a user account and download the administrator guide along with the assessment form. The form itself is freely available in multiple languages, which is useful if you're working across populations. Start with the ideation screen. Ask the standardized questions in order. Do not improvise phrasing. The scale's reliability depends on consistent administration, and researchers have validated the wording specifically. If a patient says something vague like "I just want it all to stop," probe toward the scale's defined categories. Are they having thoughts of actually ending their life? Do they have a plan? Do they intend to carry it out? The behavioral section comes after. If ideation scores zero across all items, you generally do not proceed to behavioral questioning unless there's a clinical reason. Administering unnecessary behavioral questions can trigger distress without adding diagnostic value. That's not in the manual explicitly, but it's a standard clinical judgment call after you've used this enough times.
Get the Full Details

The Edge Case That Broke Me For a While
Early in my career I was administering the C-SSRS to a 67-year-old man admitted for pneumonia. He scored a zero on ideation across every category. The form read clean. Then he told me quietly, between breaths, that he hadn't wanted to die but he'd stopped taking his blood pressure medication deliberately because he figured he'd outlive it at this point. The C-SSRS didn't capture that. The scale asks about active intent to end life, not about passive withdrawal from life-sustaining treatment. A patient can be slowly opting out of care without endorsing suicidal ideation on the standard items. My workaround was simple and it wasn't elegant. After the C-SSRS came back negative, I asked a supplemental question: have you been doing anything to intentionally shorten your life, even indirectly? That opened the door. The conversation moved from ideation to behavioral self-neglect, which is a different risk construct entirely. I documented both the C-SSRS score and the supplemental finding separately. The scale didn't fail. It just measured what it was designed to measure, and what the patient was doing fell outside that scope.
Common Pitfalls That Beginners Miss
The first major mistake is treating the scale as a pass-fail checklist. A low score does not mean a patient is safe. The C-SSRS has known gaps. It misses ideation that's fleeting or minimally endorsed because the threshold for a positive response is higher than you might expect. A patient who says "sometimes I think life isn't worth living" without reaching the threshold for passive ideation won't trigger a positive screen, but that patient still deserves follow-up. The second mistake is scoring based on what you think the patient means rather than what they actually said. The scale requires you to code verbatim responses against behavioral anchors. If a patient describes buying pills but says they don't intend to take them, you code that as acquisition without intent, not as an attempt. The distinction is legally and clinically meaningful. Rushing through this coding process is the fastest way to produce unreliable data. The third mistake is ignoring the intensity and frequency modifiers. Two patients can both endorse ideation, but one reports daily intrusive thoughts with high intensity and the other reports a passing thought once last month. The scale captures both, but the risk profile is fundamentally different. Document the modifiers precisely.
Limitations You Need to Accept
The C-SSRS is not sensitive to all forms of suicidal thinking. It was designed for breadth of coverage across settings, not depth of phenomenological nuance. Cultural expressions of distress don't always map onto the scale's item structure. A patient from a background where suicidal language is stigmatized may underreport significantly. A patient with cognitive impairment may understand the questions but respond inconsistently due to executive dysfunction rather than psychological state. The scale assumes a baseline level of verbal comprehension and introspective capacity that not all patients possess. It also doesn't account for non-suicidal self-injury unless you're using a supplementary module. NSSI and suicidal behavior are correlated but distinct constructs, and relying solely on the C-SSRS will miss patients who self-harm without suicidal intent. Pair it with a separate NSSI assessment if your population includes that demographic. For research purposes, the scale works well because it's standardized and widely validated. For individual clinical decision-making, it's one data point among many. Use it alongside collateral history, clinical observation, and other validated instruments. The PHQ-9 item 9 screens for suicidal ideation but uses different thresholds. The AUDIT identifies substance-related risk factors. Combining tools gives you a fuller picture than any single instrument can produce.

The download is free. The training materials are adequate but not exhaustive. If you plan to use this in a high-volume setting, invest time in inter-rater reliability practice. Run through the administrator guide examples with a colleague until your scoring aligns. Inconsistent scorers produce inconsistent data, and that undermines whatever system you're trying to build around the assessment.