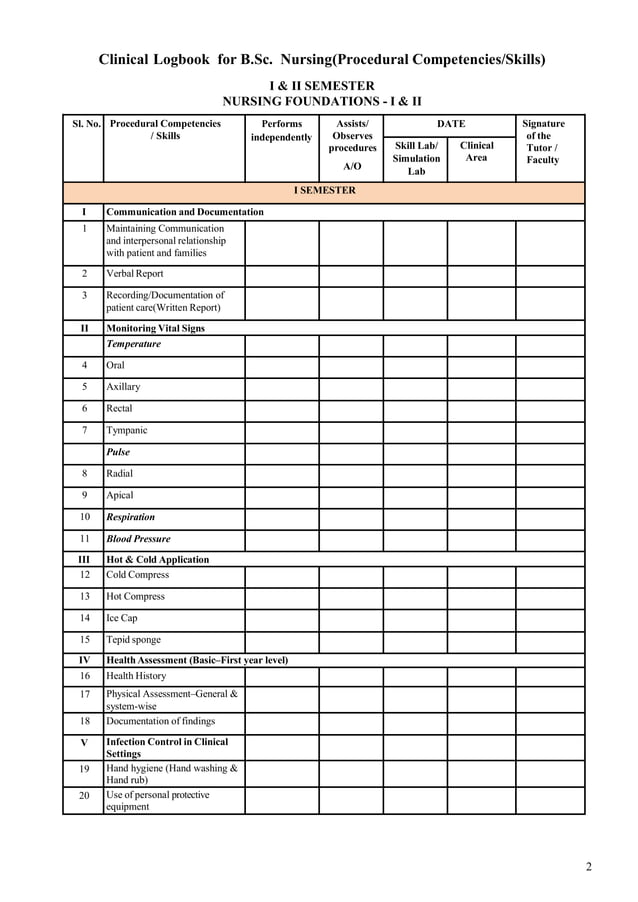
So You Need to Build a Comprehensive Nursing Logbook
A Comprehensive Nursing Logbook is essentially a structured record-keeping system that tracks patient care across shifts, treatments, medication administrations, and clinical observations. It's not one single tool — the term covers everything from paper binders with pre-printed charts to digital EHR modules designed specifically for nursing workflows. The core function is documentation compliance, communication continuity, and legal traceability. I spent about four years managing logbooks for a 60-bed acute care ward before we transitioned to a digital system. The paper version was a nightmare of missing pages, illegible entries, and the constant anxiety that you'd signed off on something you couldn't prove you actually assessed. Digital didn't fix everything, but it fixed the ones that mattered most.
What Goes Into a Comprehensive Nursing Logbook
The components vary by jurisdiction and facility type, but a solid logbook covers these areas: patient admission assessments, vital signs trending, medication administration records with dual-signature verification, nursing interventions and responses, wound care documentation, fall risk and pressure ulcer monitoring, discharge summaries, and incident reports. Some facilities layer in specialized tracking for isolation protocols, restraint use, and telemetry readings. What most people miss is the handoff section. The shift-to-shift communication portion is where documentation breaks down most often. A logbook without a standardized SBAR-style handoff template is just a collection of data with no narrative thread. I made it mandatory that every outgoing nurse wrote a three-line summary: current stability status, anything that changed in the last four hours, and what needs watching next shift. Cut my weekend chart audit errors by roughly sixty percent.
The Practical Workflow
Documentation happens in real time, not at the end of a shift. That's the single biggest mistake I see — nurses batching their charting at 10 PM because they were too busy actually caring for patients during the day. Real-time entries are more accurate and legally defensible. Retrospective charting introduces memory gaps and, worse, creates a pattern that looks like you're fabricating records during an audit. Here's what a typical entry cycle looks like on a busy med-surg floor: Admission: Complete head-to-toe assessment within the first hour. Document baseline vitals, fall risk score (Morse or Hendrich — know which one your facility uses), pain level, skin integrity, and any existing lines or tubes. This sets the reference point for everything else.
Get the Full Details

Medication passes: Scan or log each dose at administration time. The "five rights" check (right patient, drug, dose, route, time) needs to be documented, not just performed mentally. I've seen auditors flag entire shifts because the MAR showed medications given but no verification signature beside them. Hourly rounding documentation: If your facility requires hourly rounding, log it when you do it, not when you remember to do it. There's a difference that shows up in accreditation surveys. Shift handoff: Use your template. Don't skip it because you're tired. The person taking over your patients depends on those three lines being accurate.
A well-maintained logbook for a full patient load on a standard 12-hour shift takes about 25 to 40 minutes of focused documentation time, split across the shift. If you're spending two hours at the end of your shift charting, something in your workflow is broken — probably the real-time entry habit.
Digital vs. Paper: The Actual Trade-offs
Paper logbooks have zero technical failures. They don't crash, they don't need passwords, and they're readable during a power outage. The downsides are significant though: no autocomplete, no allergy alerts, no integration with pharmacy or lab systems, and physical storage that takes up entire rooms in large facilities. Filing and retrieval for a single patient chart can take ten to fifteen minutes if you're not organized, which most people aren't under pressure. Digital systems add decision support — drug interaction flags, dosing calculators, allergy cross-references — but they introduce new failure modes. System downtime happens. I was on a six-hour downtime during a flu surge and realized we hadn't practiced enough paper backup drills. We documented on scratch paper and transcribed later. It was sloppy and stressful. Every facility should have a documented downtime procedure and quarterly drills. The hybrid approach works best for most mid-sized hospitals: digital as primary, paper as documented backup with a clear activation protocol. The problem is that too many facilities treat paper backup as theoretical. When the EMR goes down, nurses pull out blank forms and realize they've never been trained on them.

Common Pitfalls That Cause Audit Failures
Corrections matter. Strikethrough a paper entry with a single line, initial and date it. Never use white-out or black out text. Digital systems should use the edit-with-audit-trail function, not deletion. Auditors can tell the difference and the implication is different too. Late entries need to be flagged as late. Document the actual time of entry and note that the observation occurred at an earlier time. This is standard practice but consistently overlooked. A late entry without the timestamp is just an inaccurate entry, and that's a compliance violation in most jurisdictions. Co-signed entries require both signatures to be present at the time of verification. One nurse writing "checked by" and signing five minutes later is documentation fraud if it's not recorded as a retrospective verification. Some facilities allow retroactive co-signatures within a defined window — know what yours allows and follow it exactly.
Here's a specific edge case I ran into: a patient on our unit had a negative pressure wound therapy device installed mid-shift. The logbook entry captured the dressing change and the nurse noted the device was applied, but didn't document the specific suction pressure setting or the canister empty time. The device alarm went off four hours later and the oncoming nurse had no record of what pressure was being used. We had to call wound care to re-establish parameters. It wasn't catastrophic, but it was completely avoidable. Now our facility's logbook template has a dedicated field for NPWT settings that must be filled before the shift handoff.
Retention and Legal Considerations
Nursing logbooks are legal documents. Retention periods vary by location and facility type — typically seven to ten years for adult records, longer for pediatric records in some jurisdictions. Digital systems should have immutable audit logs with read-only backup copies stored off-site or in a cloud environment with proper access controls. If you're designing a logbook system, involve the charge nurses and the wound care specialists, not just administrators and IT. The people who actually write in these books know where the gaps are. I've sat through too many requirement-gathering meetings where someone from compliance insisted on a field for "patient mood assessment" that nobody actually uses, while the field for "catheter removal time and rationale" was buried three screens deep.

Building Your Own Comprehensive Nursing Logbook Template
Start with your facility's required minimums, then add the fields that matter for your patient population. An ICU logbook looks very different from a psych unit logbook. An oncology floor needs more frequent lab value tracking and symptom management documentation. A geriatric unit needs pressure ulcer staging fields and confusion assessment method tracking. The template should take no more than three minutes to complete per routine entry. If it takes longer, you've added fields that duplicate information already captured elsewhere or you've made the format unnecessarily complex. Every field should answer a question that someone — a doctor, an auditor, another nurse — actually needs answered. Review and update the template quarterly with input from frontline staff. Documentation requirements change. New guidelines come out. Your logbook should reflect current practice, not the practice from three years ago when someone copied a template from another facility and never revised it.