Getting Real About Therapy in Educational Settings
I spent about six years working directly with a school district on implementing therapeutic support for students with complex needs. The work was unglamorous, frequently frustrating, and occasionally effective. Most of the people writing about this online have never had to negotiate between a 37-minute window in a nurse's office and a child who genuinely cannot regulate when the bell rings. That gap between theory and practice is where the actual work happens. The term Considerations For Educationally Relevant Therapy covers a pretty wide range of activities. It can mean speech-language pathologists embedded in classrooms, occupational therapy for students with sensory processing difficulties, or behavioral health services delivered within a school day. Sometimes it overlaps with mental health counseling. Often it doesn't. The categories blur in practice even when the paperwork keeps them separate.
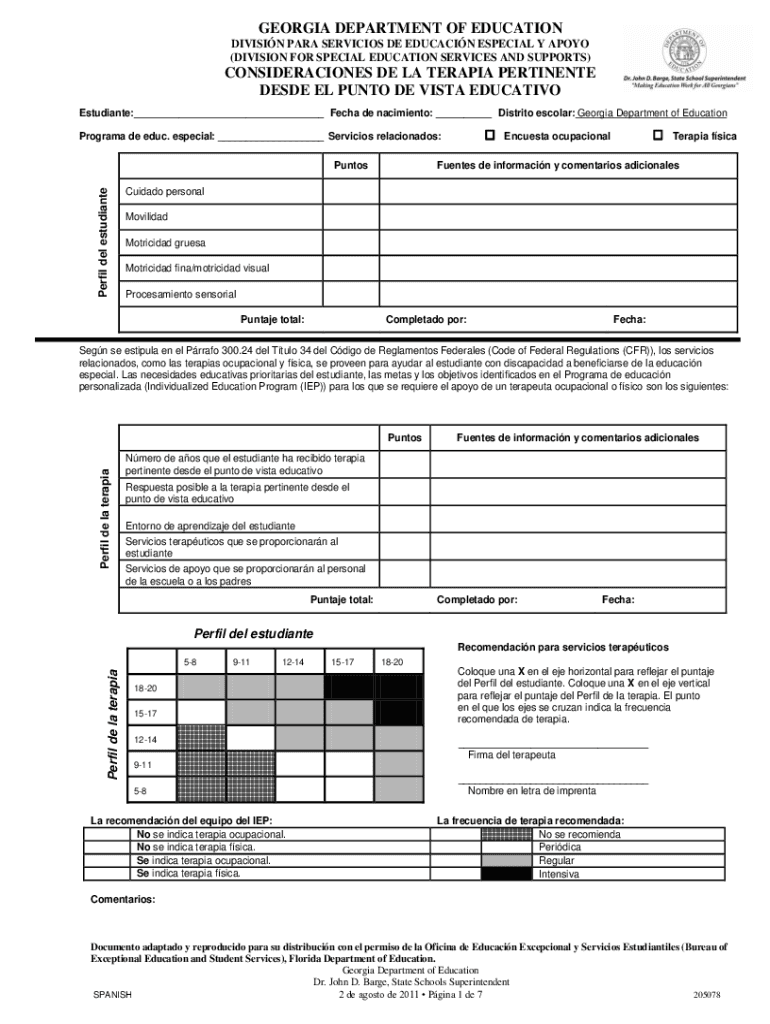
Considerations For Educationally Relevant Therapy
The biggest factor most people miss isn't the clinical model. It's scheduling. A student might qualify for sixty minutes of occupational therapy per week. In a clinic that sounds fine. In a public school where therapists rotate between three buildings and eight rooms, you are looking at maybe twenty-two effective minutes per visit after transition time, equipment setup, and documentation. You plan your goals around those twenty-two minutes. Everything else is fiction. Data collection requirements in educational settings are absurdly detailed compared to private practice. A school therapist might need to log frequency, duration, stimulus type, student response, and level of prompting for every single trial. That takes approximately forty-five minutes of paperwork for every hour of direct service. I learned early to batch my data entry. I kept a standardized spreadsheet open on my laptop during sessions and filled in rows during natural pauses rather than trying to complete everything afterward. This cut my documentation time from roughly two hours per day down to about twenty minutes per day. The next thing people get wrong is the assumption that a clinical diagnosis translates directly into an educational intervention. It does not. A student can have a formal diagnosis of autism spectrum disorder and still not qualify for therapy services under IDEA if the district determines the disability does not adversely affect educational performance. That's the legal standard. It's also the standard that creates the most contested IEP meetings I've ever attended. I once worked with a child who had significant dysregulation but scored right at the district threshold on academic testing. Her eligibility was challenged twice before we settled on a 504 plan with therapeutic supports. That took four months of advocacy and about sixty pages of supporting documentation.
Interdisciplinary coordination is another layer that textbooks rarely address with honest detail. When a student receives both speech therapy and counseling in the same building, those providers often operate in complete silos. The speech therapist doesn't know the counselor is working on anxiety around peer interactions. The counselor doesn't know the speech goals involve group participation. I started a shared binder system where each provider logged their session focus and any behavioral observations in a simple format. It wasn't fancy. It was three rings and index cards. But after six months of use, our team started noticing patterns we were completely missing before. One pattern led to a modification in the speech therapist's approach that reduced the student's avoidance behaviors by about half within eight weeks. Parent engagement in educational therapy looks very different from private practice. Parents in the school system are often navigating multiple bureaucracies simultaneously. They may not have the bandwidth for the kind of homework reinforcement that private clinicians expect. I stopped assigning weekly practice sheets to most of my school-based cases. Instead, I identified two or three functional goals that could be woven into existing routines like morning routines or homework time. Progress slowed slightly on some metrics but parent compliance improved dramatically, and that made the difference on long-term outcomes. There are real limitations to this model. School-based therapy cannot replicate the intensity or continuity of full-time clinical treatment. A student seeing a therapist once a week for forty-five minutes is not going to make the same progress as a student in daily intensive therapy. This is not a criticism of school therapists. It's a structural constraint that everyone involved needs to understand before expectations get set. If a family needs clinical-level intervention, the school can coordinate referrals and provide supporting services, but it cannot replace that level of care.
Get the Full Details
Documentation is another legitimate bottleneck. Many states require therapists in educational settings to maintain records that meet both educational compliance standards and healthcare privacy standards simultaneously. HIPAA and FERPA overlap creates situations where you cannot share information with teachers that would be helpful to their work, and you cannot share with parents what you've documented in the student's educational record without going through specific procedures. It's slow and sometimes counterproductive, but it's the framework you operate within. The quality of support varies enormously depending on your location and funding source. Rural districts often have one therapist covering an entire county. Urban districts may have more staff but also higher caseloads and more complex student populations. Neither model is inherently better. They just present different problems. In my experience, the rural setting forced more creative scheduling and closer collaboration with community providers, while the urban setting allowed for more specialized services but required constant triage of competing demands. Measurement of progress in educational therapy settings tends to rely heavily on IEP goal attainment scaling. That system works reasonably well for discrete skills like articulation targets or fine motor tasks. It becomes much less useful for broader goals around emotional regulation or social skills. I found that adding brief narrative progress notes alongside the formal scaling gave a much clearer picture of what was actually happening. Those notes don't replace the required forms. They exist alongside them and tend to be the only thing that actually captures meaningful change over a semester.
If you are considering implementing or expanding therapy services in an educational context, start by mapping the actual time available for direct service before you write any policy documents. Everything downstream depends on that number being realistic rather than optimistic. Then identify one or two students who would benefit most and run a pilot with tight feedback loops. You will learn more from three months of that process than from reading twenty policy manuals.




